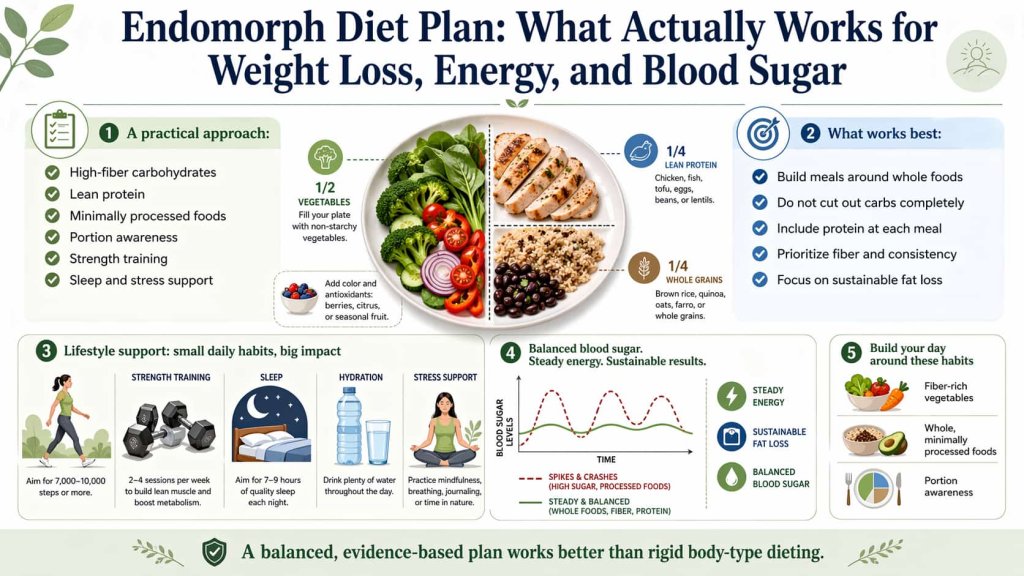
Why the standard advice doesn't work for endomorphs
Most people who identify as endomorphs because they gain weight easily and have a broader frame end up following generic cutting protocols that fail within six to eight weeks. I ran into this repeatedly when I started coaching people who fit the somatotype description. The issue isn't willpower. It's that standard caloric deficit models assume a metabolic rate that these bodies simply don't operate at. A 500-calorie deficit that works for an ectomorph will stall out for an endomorph somewhere around week three. The weight doesn't move. Not because they're cheating, not because they're lying about their food intake. The physiology just changes under sustained deficit. I've seen this enough times to stop recommending the same template across the board. There's a specific way to approach a Diet For Endomorph Weight Loss that acknowledges insulin sensitivity patterns, leptin resistance tendencies, and the slower basal metabolic rate that comes with higher body fat percentage as a baseline rather than a failure state.
The Diet For Endomorph Weight Loss Protocol
Here's what actually works. You start with protein at 1.6 to 2.2 grams per kilogram of target body weight. That means if someone weighs 100 kilograms and is aiming for 85 kilograms, they're eating roughly 170 grams of protein daily, not 120 grams like most plans suggest. The higher protein serves two purposes. It preserves lean mass during a deficit, and it keeps thermic effect of food elevated, which matters more than people realize for endomorph body types that tend to downregulate NEAT quickly when calories drop. Carbohydrate timing becomes the differentiator. Endomorphs typically process carbs more slowly. The practical implication is that you front-load them around your training windows and keep non-training meals low carb. If someone trains in the evening, their higher carb meal should be pre-workout and post-workout. Breakfast and lunch stay moderate to low in carbohydrates. This isn't about being strict. It's about matching carb availability to actual utilization. I had a client once who stuck to 40 grams of carbs at breakfast and lunch and 80 to 120 grams only around his workout. He lost 0.7 kilograms per week consistently for fourteen weeks. Another client who spread 120 grams evenly across all three meals stalled at 0.2 kilograms per week after six weeks despite matching total calories exactly. Same calories. Different carb distribution. Completely different results. Fats stay at 0.6 to 0.9 grams per kilogram of body weight. Not too low. Very low fat diets crash hormone production, and for people already struggling with metabolic adaptation, that's counterproductive. Keep fats moderate and prioritize omega-3 sources because inflammation management matters more for endomorphs than it does for other body types. Higher body fat correlates with chronic low-grade inflammation, and that inflammation interferes with leptin signaling, which makes satiety signals less reliable.
What most guides leave out
The thing nobody explains clearly is the refeed strategy. Most people either don't refeed at all or they do it wrong by turning it into a cheat day. A proper refeed for an endomorph is a single day where you increase carbohydrates to 2 to 3 grams per kilogram of body weight while keeping protein at the same level and dropping fat to near zero. This isn't psychological. It's a deliberate leptin spike that tells your body it hasn't entered starvation mode. Without it, metabolic rate can drop 10 to 15 percent over six to eight weeks of continuous deficit. With it, you maintain roughly 5 to 8 percent less downward drift. I learned this the hard way. Early on I had a client who was dropping weight steadily for five weeks and then completely stalled. Her calories were the same. Her steps were the same. Her sleep was the same. Nothing changed except her metabolic rate had adapted downward significantly. We added one refeed day every seven days and she resumed losing 0.5 kilograms per week the following week. That single adjustment made the difference between a failed cut and a successful one. No extra supplements. No new exercises. Just one day of higher carbs at the right interval.
Get the Full Details

The realistic limitations
This approach requires discipline around meal timing and carbohydrate management. If you're traveling frequently or your schedule is unpredictable, consistency drops and so does results. The refeed days also require planning. You can't just eat whatever you want and call it a refeed. A refeed with 200 grams of fat and 150 grams of carbs isn't a refeed. It's just a high-calorie day that will set you back. The carb source matters too. White rice, potatoes, and oats work better than whole grains for refeeds because they're faster to digest and produce a cleaner insulin response when you need it. Another limitation is that this doesn't work well for people with pre-diabetic conditions or diagnosed insulin resistance without medical supervision. The carb manipulation strategy assumes a functioning insulin response. If someone has significant insulin resistance, the carb cycling approach needs to be modified or replaced with a lower carb foundational approach altogether. In those cases, a ketogenic or very low carb protocol under medical guidance tends to produce better results than any carb manipulation scheme.
Supplements that actually move the needle
Caffeine before training. About 3 to 6 milligrams per kilogram of body weight. It increases lipolysis slightly and improves training performance, which matters because endomorphs often struggle to maintain training intensity during a deficit. Creatine monohydrate at 5 grams daily. It helps preserve strength and lean mass during caloric restriction. Fish oil at 2 to 3 grams of combined EPA and DHA daily. This addresses the inflammation issue I mentioned earlier and may improve insulin sensitivity over time. None of these are magic. But together they support the protocol rather than replacing it. What doesn't help much is fat burners, CLA, green tea extract in isolation, or any supplement marketed specifically for endomorphs. Those are marketing products. The protocol itself does the work. Supplements are marginal at best unless you're missing something like vitamin D, which many people with higher body fat percentage are deficient in, and deficiency correlates with poorer metabolic outcomes.
Tracking and adjustment
Weigh yourself daily under the same conditions and track the weekly average. Take waist measurements every two weeks. Use those two data points to adjust. If the weekly average weight hasn't dropped for two consecutive weeks, reduce daily calories by 150 to 200 or add 2,000 to 3,000 daily steps. Don't drop calories further than that in a single adjustment. Small increments prevent metabolic shock and make it easier to identify what actually caused a stall. Body composition changes matter more than scale weight for endomorphs because these body types tend to hold water differently during caloric deficits. A 0.5 kilogram fluctuation in water weight can look like regaining on the scale when it's just glycogen and sodium shifting. That's why the weekly average is necessary. Daily numbers are noise. Two-week averages tell you the real trend. This isn't a quick fix. The realistic timeline is 0.5 to 0.8 kilograms of fat loss per week for someone starting at a higher body fat percentage, tapering to 0.3 to 0.5 kilograms as you get leaner. Going faster usually means losing muscle or triggering severe metabolic adaptation that makes the next phase harder. Patience here isn't philosophical advice. It's a practical requirement based on how endomorph physiology responds to sustained deficits.