Setting Up a Practical Diet For Gerd And Acid Reflux
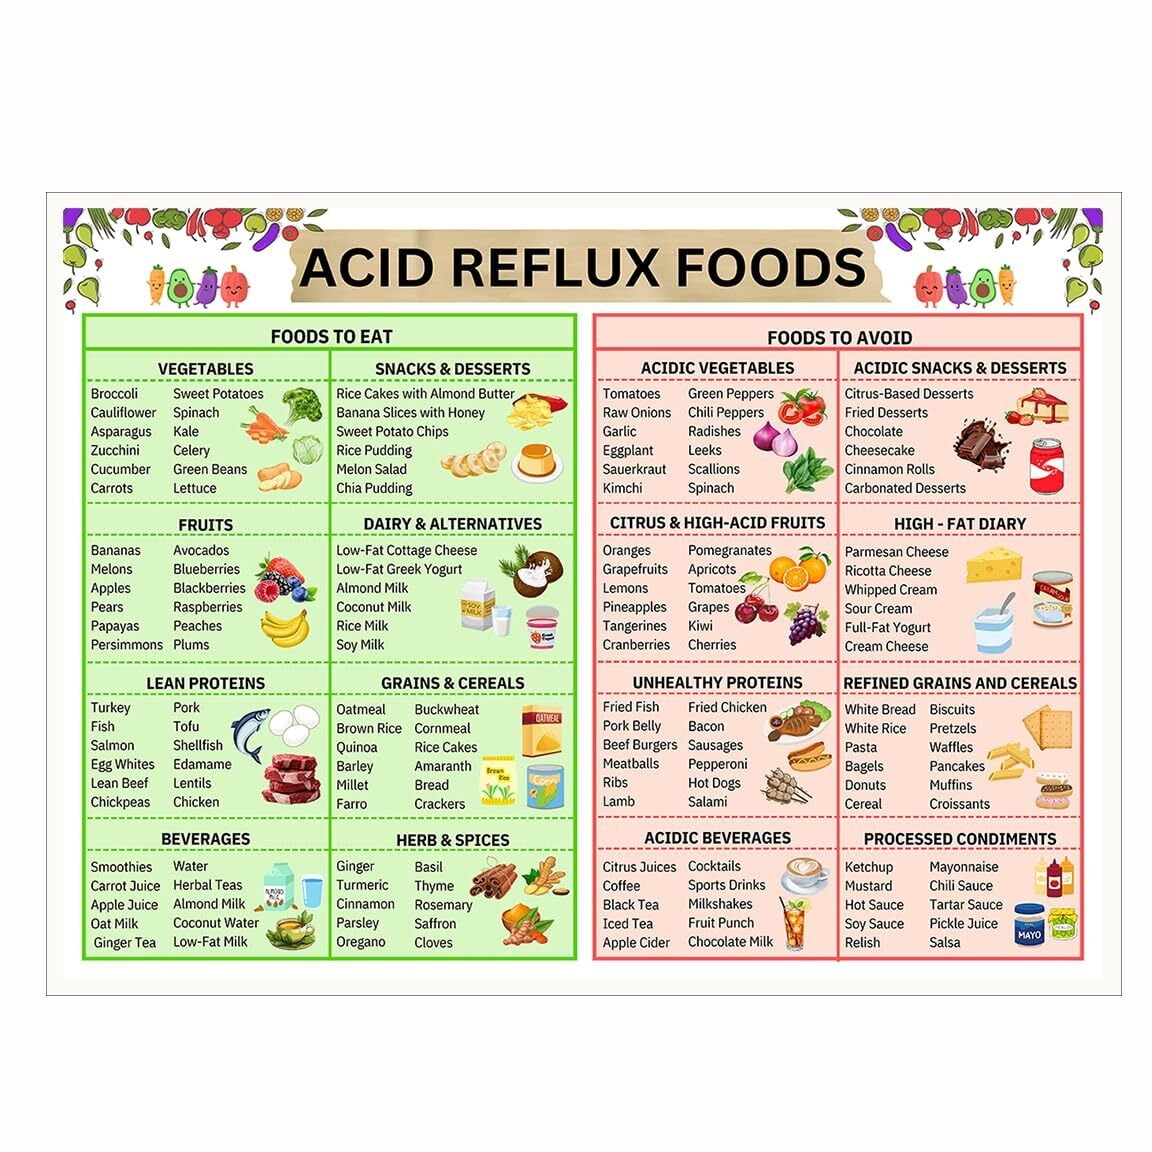
The standard advice on reflux diets is mostly correct but wildly oversimplified. Most people who get diagnosed with GERD end up eating like a bird for a few weeks, feeling a bit better, then sliding right back into bad habits because nobody explained the actual mechanics of what's happening. Here's what it actually looks like in practice. The fundamental problem with GERD is that the lower esophageal sphincter (LES) — the muscular valve between your esophagus and stomach — isn't closing properly or is being pushed open repeatedly. Your diet's job is to reduce the frequency and severity of those openings and to make any reflux that does happen less damaging to your esophageal tissue. Avoid the usual suspects first. These are the items that directly relax the LES or irritate already-inflamed tissue:
- Fatty and fried foods — they delay gastric emptying, meaning food sits in your stomach longer and creates more opportunity for reflux
- Chocolate — contains methylxanthines that relax smooth muscle, including the LES
- Peppermint and spearmint — direct LES relaxants; people often miss this one because mint is in so many things
- Citrus and tomato products — the acidity directly burns exposed esophageal tissue even if they don't cause the reflux itself
- Caffeine and alcohol — both relax the LES and increase acid secretion
- Carbonated beverages — the gas increases intragastric pressure and physically pushes content upward
That's the elimination list. But the more important part is what you build your diet around, not just what you remove. A typical safe plate includes lean proteins (chicken breast, fish, turkey), non-citrus vegetables (leafy greens, broccoli, asparagus, carrots), oatmeal or other whole grains, and low-acid fruits like melons and bananas. This is where the standard advice falls short. Getting your trigger foods right means nothing if you're eating a large meal at 8 PM and lying down at 9:30 PM. Gravity is one of your primary defenses against reflux, and once you're horizontal, you've removed it. The practical rule is simple: finish eating at least three hours before you lie down. No snacks after dinner if you're going to bed soon. This isn't about willpower — it's physics. When your stomach is full and you're supine, the contents have nowhere to go but up through a weakened valve.
I also learned this the hard way. About five years ago, I was managing my own reflux reasonably well on a strict elimination diet. Then I started doing intermittent fasting and shifted my last meal to around 7 PM. At 10 PM I'd get burning in my chest so bad I'd sit upright in a chair for an hour trying to get through it. Turns out the fasting window had shrunk my stomach's resting volume to the point where even a normal-sized dinner at 1 PM felt like a massive meal by 7 PM. I was eating smaller total calories but packing them into a narrow window with no buffer before sleep. Cutting my evening meal down to half size and adding a small protein snack at 4 PM fixed it immediately. Portion distribution matters as much as food choice.
Get the Full Details

Some Counter-Intuitive Things Worth Knowing
Not everything on the classic trigger list affects everyone equally. I've seen people handle tomato sauce fine but get wrecked by a single square of dark chocolate. Others are fine with coffee but cannot touch onions. The trigger list is a starting framework, not a universal rulebook. The only way to figure out your personal threshold is systematic elimination and reintroduction over a four-to-six week period. Track everything you eat and any symptoms, then reintroduce one item at a time and watch for a response over the next 24 to 48 hours. Another thing most people don't know: slimentary fiber can actually help. Oatmeal, psyllium husk, and other soluble fibers absorb stomach acid and give your LES something to work around. This isn't a treatment for severe erosive esophagitis by any means, but for mild to moderate daily reflux, adding a serving of oatmeal or a psyllium supplement with dinner can noticeably reduce nighttime symptoms. Weight is the biggest modifiable factor outside of food itself. Even a ten to fifteen pound loss can dramatically reduce intra-abdominal pressure on the LES. But if you're already at a healthy weight, diet modification becomes your primary lever, and the details above matter more.
What This Approach Doesn't Fix
A strict GERD diet won't resolve a hiatal hernia. It won't fix a fundamentally malformed LES. If you have severe erosive esophagitis or Barrett's changes, diet alone is not sufficient — you need medical management. PPIs and H2 blockers address the acid production side of the equation that diet cannot touch. The diet is a supporting intervention, not a cure, and anyone telling you otherwise is either selling something or doesn't understand the condition. For mild to moderate non-erosive GERD, a properly structured elimination diet combined with timing and portion control can reduce symptoms significantly for many people within two to four weeks. For severe cases, it's one tool in a broader treatment plan. There's no shortcut around the basic work: identify your triggers, manage your meal timing, control your portions, and know when to get a gastroenterologist involved instead of just adjusting your plate.




