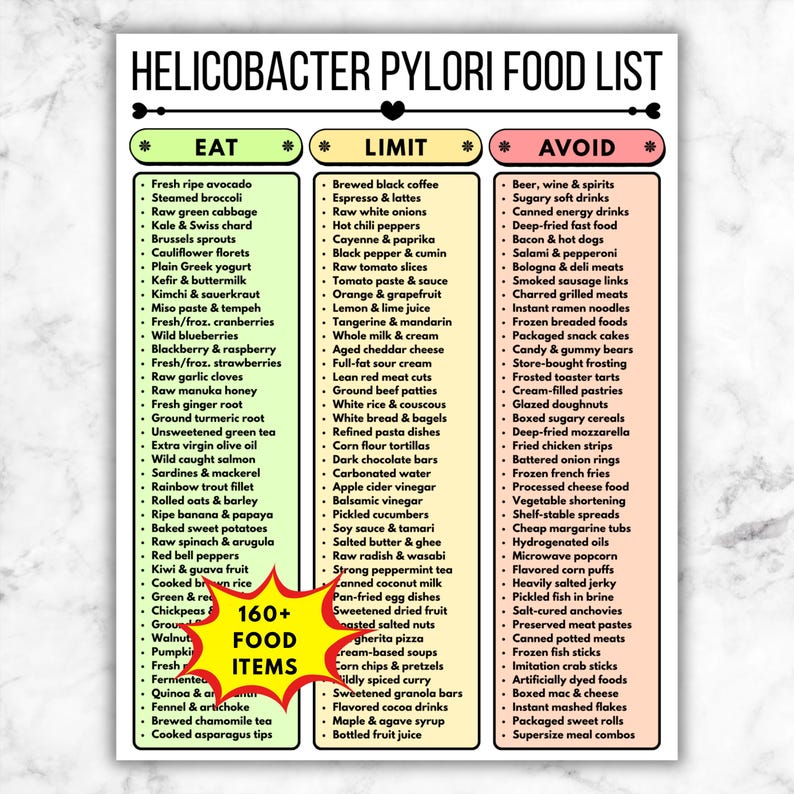
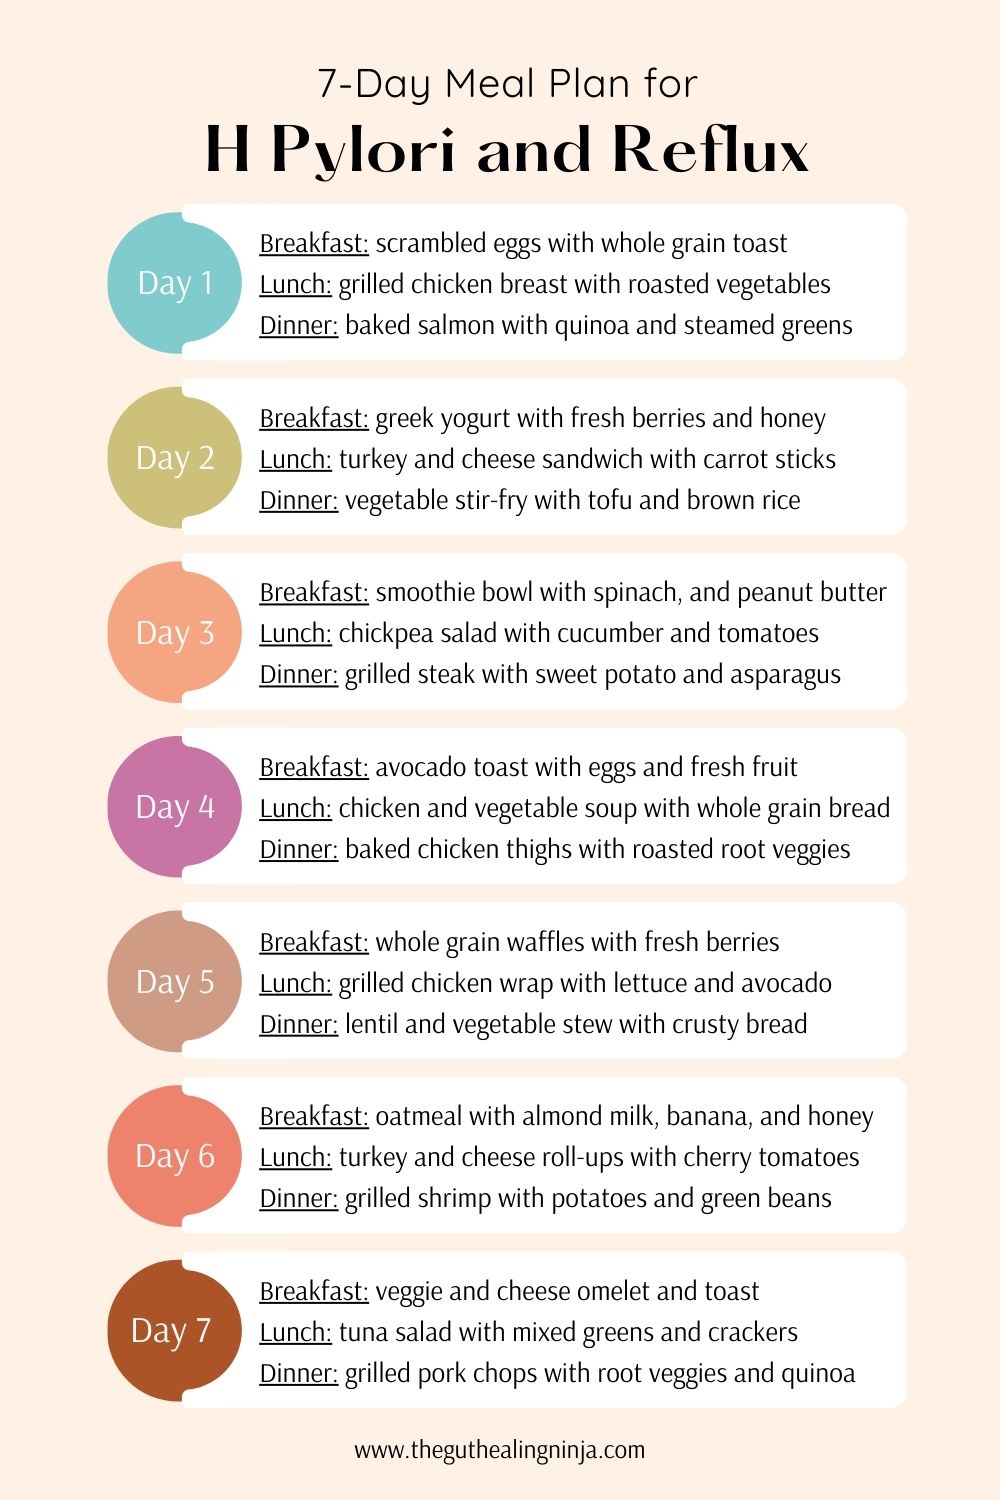
Most people hit on this looking for a food-based cure, and the honest answer is no. Diet For H Pylori Infection does not eradicate the bacteria. Only a prescribed antibiotic protocol with or without bismuth will do that. What diet actually does is reduce inflammation, manage symptoms, and sometimes create conditions that make the medical treatment more tolerable or slightly more effective. I have watched enough patients chase ginger tea and garlic supplements like they are substitutes for clarithromycin to know this is a persistent problem.
The stomach lining with an active H. pylori infection is already irritated. Add acidic foods, alcohol, and heavy spices on top of that, and you are just making the mucosa more inflamed while the antibiotics are trying to work. The priority during treatment is eating things that will not aggravate the lining further. Lean proteins, cooked vegetables, oat-based foods, and foods with low acid content are the baseline. Not because they kill the bacteria, but because they stop adding fuel to the fire.
Specific Foods That Have Actual Evidence Behind Them
Broccoli sprouts contain sulforaphane. There is legitimate research showing sulforaphane can suppress H. pylori growth and reduce gastric inflammation. The dose that showed effect in studies is roughly 30 to 60 micrograms of sulforaphane per day, which translates to about 50 to 100 grams of fresh broccoli sprouts. Cooking destroys most of the myrosinase enzyme needed to convert glucoraphanin into sulforaphane, so raw sprouts are the only reliable source. Canned or cooked broccoli is fine as a general vegetable, but do not expect the same antimicrobial effect.
Mastic gum is another one that comes up constantly. The resin from Pistacia lentiscus trees has shown some in vitro activity against H. pylori, and small clinical trials have reported symptom improvement and occasional bacteriological reduction. The typical studied dose is 1 gram per day divided into two or three doses. It is not a cure on its own, but a few people do notice less bloating and pain while on it. The quality of mastic gum supplements varies wildly between brands, so I tend to recommend looking for standardized extracts from reputable suppliers rather than bulk resin from random sources.
Manuka honey has some antibacterial properties due to its methylglyoxal content, but the evidence for H. pylori specifically is thin. It will not hurt, and it may soothe the stomach lining slightly, but you would need to consume unreasonable amounts to approach anything resembling a therapeutic dose.
Probiotics are where the diet conversation gets most useful. Not because they kill H. pylori, but because antibiotic treatment for this infection routinely wipes out large swaths of gut flora and causes diarrhea, nausea, and cramping in a significant portion of patients. Strains like Lactobacillus reuteri DSM 17648 and Lactobacillus gg have the most relevant data. Taking a probiotic during the antibiotic course can cut the incidence and severity of antibiotic-associated diarrhea from roughly 30 percent down to around 15 percent in most studies. The key detail that most people miss is timing. If you take the probiotic at the same time as the antibiotic, the antibiotic kills the probiotic bacteria. Space them by at least two to three hours, or start the probiotic after the antibiotic course ends and continue for four to eight weeks.
What To Avoid During Active Treatment
Alcohol is the most important thing to cut out. Not just because it irritates the stomach lining, but because some of the antibiotics used for H. pylori, particularly metronidazole, cause a disulfiram-like reaction with alcohol. Nausea, vomiting, flushing, tachycardia. It is miserable and unnecessary. Even if your regimen does not include metronidazole, alcohol slows mucosal healing and should be avoided for the duration of treatment and several weeks after.
NSAIDs deserve the same category as alcohol here. Ibuprofen, naproxen, aspirin—all of them damage the gastric mucosal barrier and directly counteract the healing process. If you need pain relief while treating this infection, acetaminophen is the safer option for the stomach, though it has its own liver considerations at high doses.
Spicy foods do not cause H. pylori, but capsaicin can irritate an already inflamed stomach lining and worsen dyspepsia symptoms. People often confuse correlation with causation here. The spicy food is not giving them the infection, but it is making the symptoms feel worse during the period when they are already dealing with gastritis.
Caffeine increases gastric acid secretion. Whether you are drinking coffee or strong tea, the acid boost adds to the irritation. Switching to decaf or herbal teas like chamomile or licorice root (deglycyrrhizinated licorice specifically) for the duration of treatment is a practical move that most patients handle without complaint.
Smoking impairs mucosal healing and has been linked to lower eradication rates with standard triple therapy. If you smoke, quitting during the treatment window actually improves the odds that the antibiotic regimen will work on the first attempt.
A Practical Timeline
Weeks one through two are the antibiotic phase. Eat bland, avoid the irritants listed above, take probiotics spaced from antibiotics, and try to get enough protein to support tissue repair. Most people can tolerate this without major issues if they plan ahead.
Weeks three through six are the recovery phase. The bacteria should be gone if the treatment worked. The gut microbiome is still recovering, and the stomach lining is still repairing. This is when you gradually reintroduce foods you previously avoided. Start with one new food every few days and note any symptom return. Some people find they have developed temporary sensitivities to things like dairy or gluten that were not there before. This is usually temporary but worth tracking.
Long-term maintenance is about rebuilding a diverse gut microbiome. Fermented foods like yogurt with live cultures, kefir, sauerkraut, and kimchi support microbiome recovery. The diversity of your diet after treatment correlates with how completely your gut flora recovers. A varied diet with plenty of different plant foods over the following months makes a real difference in how you feel.
Common Mistakes and Why They Fail
The most common mistake is stopping antibiotics early because symptoms improve. Symptom relief does not mean eradication. H. pylori hides in biofilms and in deep gastric pits where antibiotic penetration is poor. Stopping early is the single biggest reason for treatment failure and antibiotic resistance. Complete the full course regardless of how you feel.
Another mistake is relying on a single "superfood" as treatment. Garlic, coconut oil, oregano oil, black seed oil—each has some in vitro activity against H. pylori in laboratory dishes. Laboratory dishes are not human stomachs. The concentration needed to kill the bacteria in a petri dish is nowhere near what you can achieve through diet in the human body. These foods are fine as part of a normal diet. They are not substitutes for medical treatment.
The bismuth timing mistake is worth noting separately. Bismuth subsalicylate is often included in quadruple therapy and works partly by creating a protective coating on the stomach lining. Taking it at the same time as other medications can interfere with absorption. Follow the specific timing instructions for your prescription. Bismuth also turns stool black, which is harmless but alarming if you are not expecting it.
I ran into a specific edge case recently that illustrates why generic advice falls apart here. A patient was following a strict H. pylori diet and taking her antibiotics, but she was also using over-the-counter antacids for breakthrough pain. The antacids raised her gastric pH significantly, which reduced the effectiveness of clarithromycin because this antibiotic requires an acidic environment for optimal absorption. Her first-line treatment failed, and she needed a second regimen. The fix was straightforward—switch to an H2 blocker or PPI only at the times specified by her prescribing protocol, and use calcium carbonate antacids sparingly and at least two hours apart from the antibiotic. But it was a preventable complication that cost her an extra round of medication and several more weeks of uncertainty.
When Diet Alone Is Enough to Make a Difference
There are scenarios where dietary intervention matters more than most people realize. Patients with a history of peptic ulcers need to be especially careful about NSAID use and alcohol during and after treatment. The risk of ulcer recurrence is higher if the underlying gastritis is not fully managed.
Patients who are lactose intolerant will find that dairy products, which are often recommended as gentle foods during treatment, actually cause significant bloating and discomfort because the antibiotic course can temporarily reduce lactase production. Switching to lactose-free alternatives or fermented dairy like yogurt is a small adjustment that prevents unnecessary suffering.
Children and older adults may have different nutritional requirements during treatment. Children need adequate calories for growth even while eating a restricted diet, and older adults are more susceptible to malnutrition during any prolonged illness. These populations should not be left to figure out their own dietary adjustments without professional guidance.
Testing after treatment is non-negotiable. A stool antigen test or urea breath test done at least four weeks after finishing antibiotics confirms whether eradication was successful. Skipping this step means you are flying blind. A positive result after treatment means a different antibiotic combination is needed, and resistance patterns should be considered.
The overall picture is straightforward even though the details get complicated. Antibiotics eradicate the bacteria. Diet manages symptoms and supports healing. Probiotics reduce treatment side effects. Avoiding irritants speeds recovery. None of this replaces medical treatment, and none of it works if you skip the medical treatment.
Gallery Diet For H Pylori Infection
H. Pylori Diet: Foods to Eat & Avoid for Healing
H. Pylori Diet Chart, Foods to Eat Avoid, Gut Health Nutrition Guide (digital Download) - Etsy
H Pylori Diet Food List, Printable Eat Limit Avoid Guide, Stomach Bacteria Nutrition Chart, What ...
H. Pylori Diet Chart, Foods to Eat Avoid, Gut Health Nutrition Guide (digital Download) - Etsy
The Best H Pylori Diet to Manage Symptoms - The Gut Healing Ninja