
What actually works when your fasting glucose is sitting at 120 and climbing
I spent three years managing borderline type 2 before my endocrinologist finally agreed to stop adding meds and let me try dietary intervention seriously. The first six months were a mess because I followed every generic guideline I could find — cut sugar, eat more protein, avoid white rice. My A1c only dropped from 6.4 to 6.1. Not nothing, but not enough to avoid medication either. The breakthrough came when I stopped thinking about "diet for high blood sugar" as a list of forbidden foods and started understanding what each meal actually did to my glucose curve in real time. Here is what I learned the hard way, and what I would do differently if I were starting over.
The order you eat things matters more than what you eat
This is the part nobody talks about enough. A study from Ben-Gurion University showed that eating vegetables first, then protein and fat, then carbohydrates last can cut post-meal glucose spikes by 73 percent compared to eating the same foods in random order. I tested this on myself for two weeks. My 2-hour post-meal readings dropped from averages around 190 mg/dL to around 130 mg/dL without changing anything about what I was eating — only the sequence. The mechanism is straightforward. Soluble fiber from vegetables forms a viscous mesh in your small intestine that slows down carbohydrate digestion and glucose absorption. Protein and fat further delay gastric emptying. When you eat carbs last, they hit an already partially blocked absorption pathway. Eat them first and they rush straight through.
My actual daily framework, not the idealized version
Breakfast is the hardest meal for blood sugar control. Most people skip it or eat something quick like toast and coffee, which is basically a glucose bomb on an empty stomach. I switched to a high-fat, moderate-protein, near-zero-carb breakfast: three eggs cooked in butter with spinach, sometimes adding half an avocado. This keeps me at around 85 to 100 mg/dL fasting and prevents the mid-morning crash that used to hit me like a truck by 10:30 AM. Lunch is where the real work happens. I eat a large salad with leafy greens, chopped vegetables, and a protein source — usually grilled chicken or canned sardines — dressed with olive oil and vinegar. Then, if I am having any starch at all, I eat it last. A small portion of sweet potato or brown rice, maybe 60 to 80 grams cooked. The total carbohydrate load per lunch stays under 40 grams, and most of that comes from fibrous vegetables, not refined starch. Dinner is tricky because cortisol patterns shift in the evening and some people become more insulin resistant later in the day. I keep dinner low carb and early — finished eating by 7 PM whenever possible. If I have a craving for something starchy at night, I now eat it with a walk afterward. A ten-minute walk after dinner lowers post-prandial glucose significantly more than the same walk before the meal, probably because muscle glucose uptake is highest when insulin is still elevated from food.
Get the Full Details
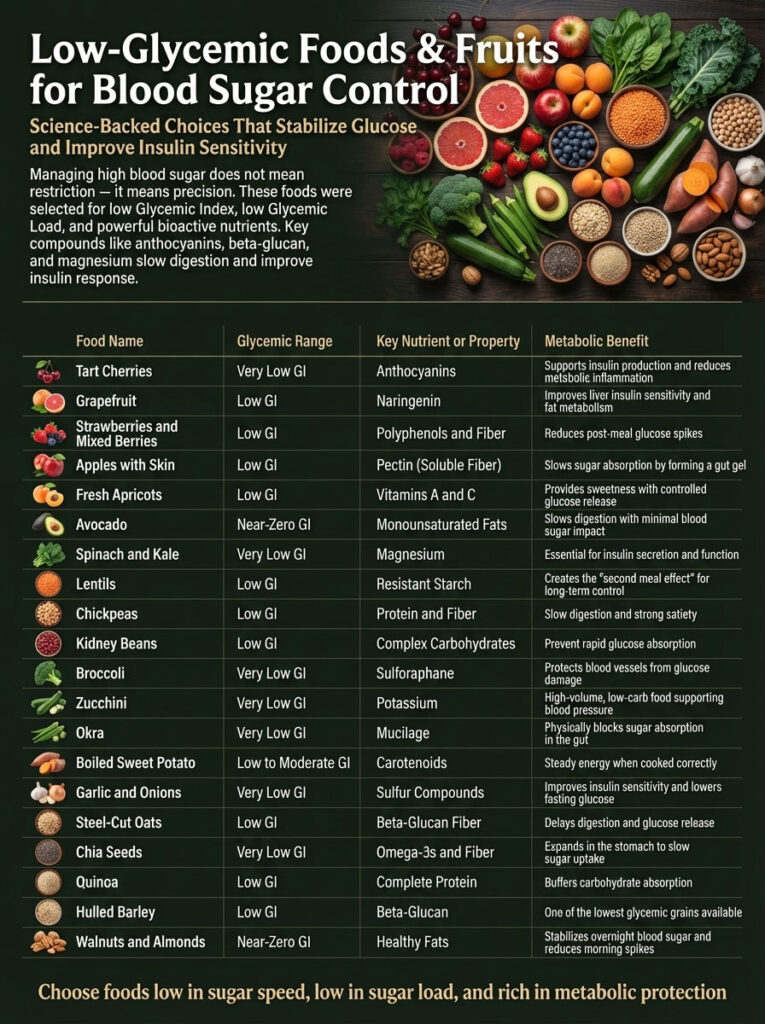
A specific problem I ran into and how I fixed it
About eight months into this approach, I noticed my fasting glucose would spike to 140 some mornings despite eating well the day before. I was confused because my post-meal numbers were solid. I kept a detailed log — everything I ate, meal times, exercise, sleep quality, stress levels — for three weeks. The pattern was clear: poor sleep plus a normal dinner still produced high fasting glucose. My body was dumping glucose from the liver overnight because it sensed stress, not because I ate badly. The workaround was not dietary. I started closing all screens two hours before bed, took magnesium glycinate at night, and began a fifteen-minute breathing exercise. Fasting glucose dropped back to the 90 to 105 range within two weeks. I had been treating the wrong symptom. Stress-driven hepatic glucose output looks identical on a blood sugar monitor to dietary failure, but the fix is completely different. If your numbers are unpredictable, check your sleep and stress first before adjusting your diet further.
Food choices that move the needle, ranked by impact
Apple cider vinegar before a meal. One tablespoon diluted in water, twenty minutes before eating. This can reduce the post-meal glucose spike by 20 to 30 percent in my experience. The acetic acid slows starch digestion and improves insulin sensitivity at the cellular level. I use this on days I know I am going to eat something higher in carbs, like a holiday meal or a restaurant visit where I cannot control the cooking method. Cinnamon. Specifically Ceylon cinnamon, not the cheaper cassia variety. Two teaspoons daily with food. Some studies show a modest improvement in fasting glucose, others show nothing. My own readings improved from around 130 to around 110 after three months of consistent use. I do not know if it is the cinnamon or the consistency of tracking. Either way, it is cheap and low risk, so I kept using it. Soluble fiber supplements. Psyllium husk taken before meals. Five grams in water, twenty minutes before eating. This creates the same fiber mesh effect that vegetables provide naturally, and it is useful when you cannot eat a large salad. I carry packets with me when traveling. Restaurant food rarely has enough vegetables to trigger the order-of-eating benefit, so the supplement fills the gap.
What this approach cannot do
I need to be honest about the limitations. Dietary intervention alone will not reverse advanced insulin resistance in everyone. My friend spent eighteen months on a very strict low-carb diet and his A1c only went from 7.2 to 6.8. He had been diabetic for twelve years and his beta cell function was already significantly reduced. Diet helped, but it was not enough. He needed medication alongside the dietary changes. Another limitation: this approach requires constant attention. You are making decisions about every meal, every ingredient, every order at a restaurant. Social events become stressful. Business dinners require advance planning. If you value spontaneity in your eating habits, this level of structuring will feel like a full-time job. I found that after six months, the habits became automatic and the mental load decreased substantially. But the first six months are genuinely exhausting. Also, there is a risk of over-restriction. I watched a nutrition client of mine drop to under 50 grams of carbohydrates per day and develop gallbladder issues within four months. Very low carbohydrate intake reduces bile secretion, and without adequate dietary fat to trigger bile release, sludge can form. I do not recommend going below 80 grams of carbohydrates per day unless you are working with a healthcare provider who is monitoring your metabolic markers regularly.

A note on monitoring and adjusting
If you are serious about using diet to manage high blood sugar, get a glucose monitor. Not the kind your doctor orders once a year — a home continuous glucose monitor or at minimum a finger-prick meter. Track your readings before meals and two hours after. The data will show you which foods spike your glucose and which ones do not, and individual variation is enormous. Two people can eat the same portion of oatmeal and have completely different glucose responses. Your personal data beats any general guideline. Reassess your approach every thirty days. If your numbers are not improving after four to six weeks of consistent effort, something is off. It might be the amount of carbohydrate rather than the type. It might be hidden calories from cooking fats or dressings. It might be that you need medical intervention in addition to dietary changes. There is no shame in combining approaches. The core principle is simple enough to state but hard enough to sustain: every bite you take has a predictable chemical effect on your blood glucose, and learning to read that effect through careful observation and adjustment is how you gain real control. Not willpower. Not deprivation. Observation and adjustment.



