Why These Two Conditions Share The Same Table
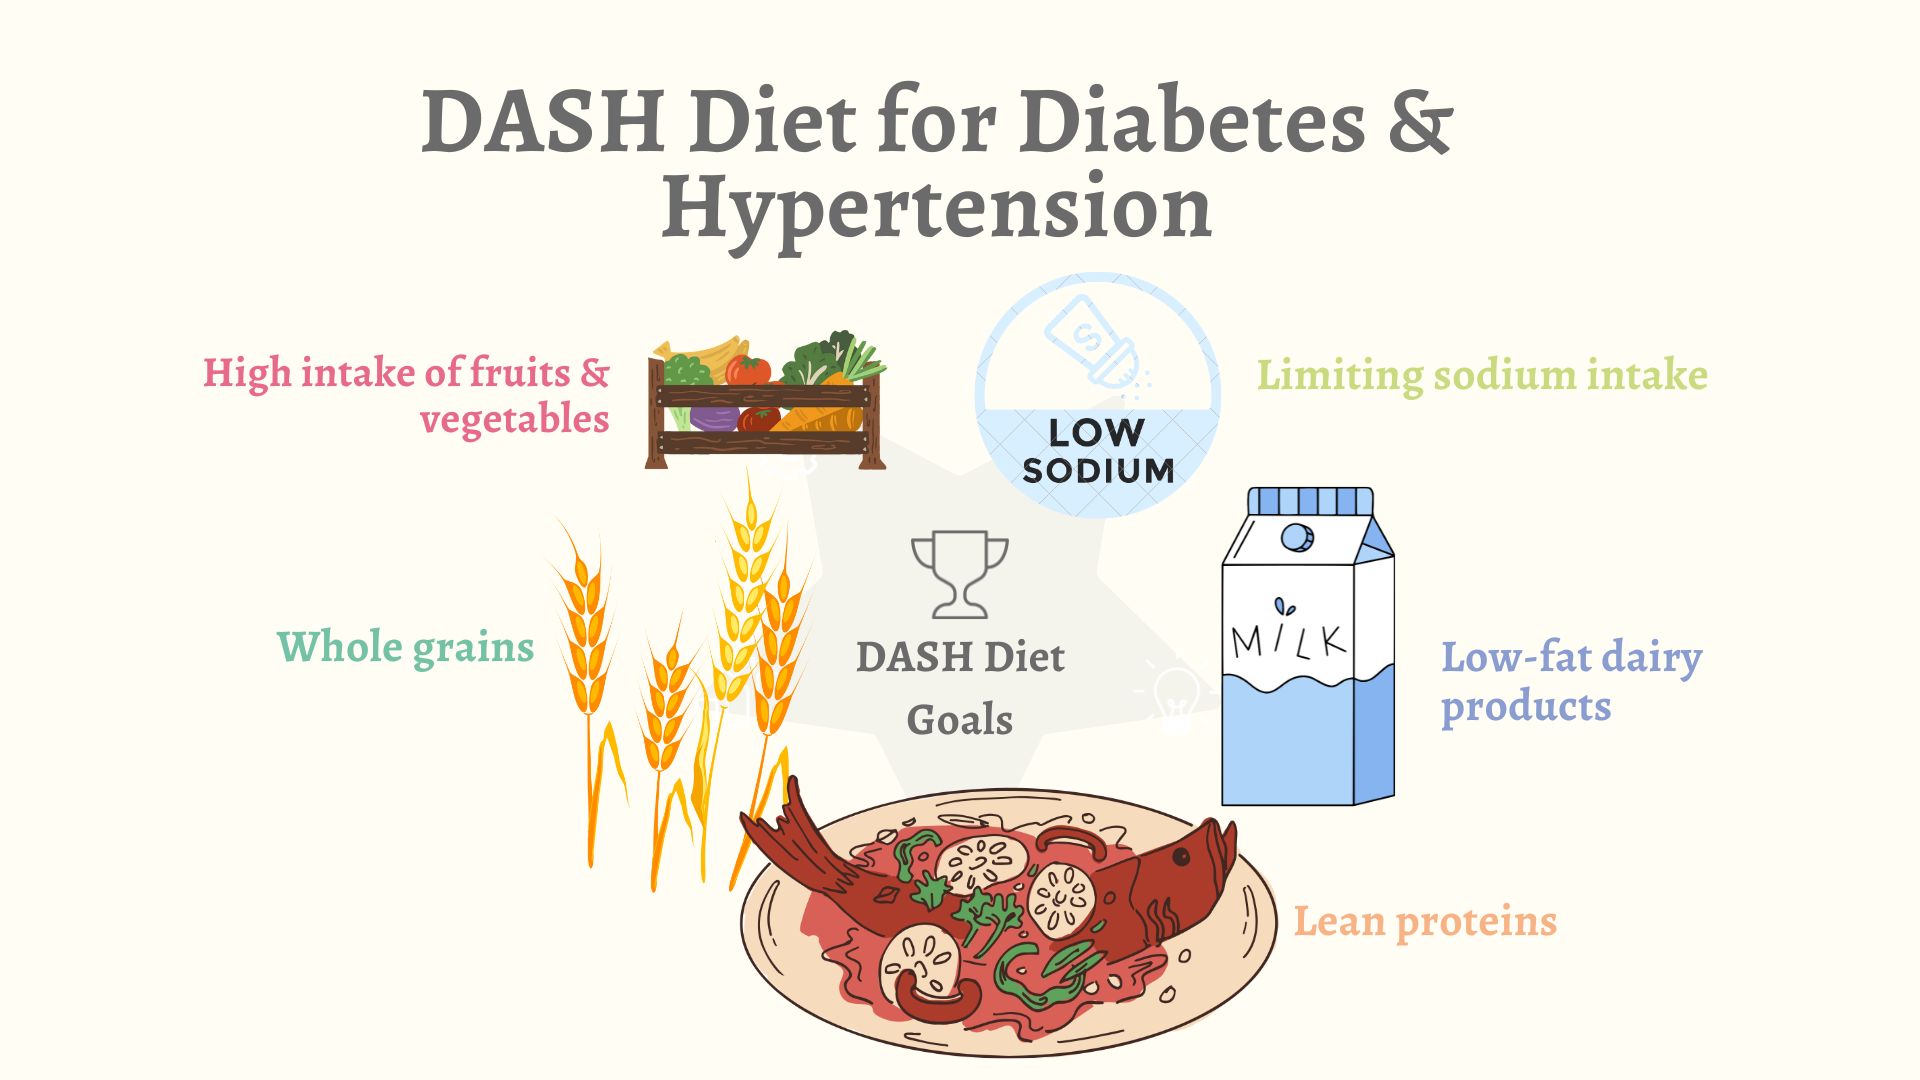
I spent years watching patients undo their progress at the grocery store. Not because they didn't understand the advice, but because the advice was usually too vague to actually use. You get told to eat healthier and then you're left staring at a shelf of "whole grain" crackers that spike blood sugar anyway. The overlap between hypertension and diabetes management is massive. Both conditions respond to the same levers: sodium reduction, glycemic control, and overall caloric quality. That means you don't need two separate diets. You need one diet that hits both problems without becoming miserable. The foundation is straightforward. You reduce sodium to somewhere under 1,500 milligrams per day, prioritize foods that don't cause rapid glucose spikes, and keep saturated fat low. But the part nobody tells you is that these two goals sometimes pull in opposite directions. A food might be low-sodium but high-glycemic. Or it might have decent fiber but a sodium content that sneaks up on you. Managing both conditions simultaneously means you can't optimize for one metric and ignore the other. The DASH diet is the clinical standard for hypertension. The Mediterranean diet is the closest equivalent for diabetes. When you combine them, you get something that looks like this: vegetables and fruits make up roughly half your plate, lean proteins like fish and poultry take up a quarter, whole grains round out the rest, and added sugars are basically eliminated. The sodium target from DASH pairs with the glycemic load management from diabetes guidelines, and the result is a single eating pattern that addresses both conditions without requiring you to live differently depending on which number you're checking.
Here is the practical framework most people can actually follow:
- Anchor every meal around a non-starchy vegetable. This isn't decorative. It fills you up, it dilutes the glycemic impact of everything else on your plate, and it adds potassium, which helps counteract sodium's effect on blood pressure.
- Choose whole grains over refined ones, but pay attention to preparation. Overnight oats have a lower glycemic impact than instant oatmeal because the cooking process changes the starch structure. This matters more than most people realize.
- Protein at every meal slows glucose absorption. That's not a suggestion. It's basic physiology. Even a small amount of lean protein with a carbohydrate-containing meal reduces the postprandial glucose spike significantly.
- Read labels for sodium, not just sugar. Processed foods marketed as "low sugar" or "diabetic-friendly" often compensate with sodium or artificial additives that don't help either condition.
I encountered a specific edge case recently that illustrates why surface-level advice falls apart. A patient was eating what she thought was a perfectly healthy breakfast: Greek yogurt with granola and berries. The granola had eight hundred milligrams of sodium per serving, nearly a quarter of her daily limit. The yogurt was fine. The berries were fine. The granola was the problem, and she couldn't see it because granola is perceived as wholesome. The workaround was simple: she switched to plain Greek yogurt with nuts and seeds she toasted herself, adding fresh berries and a small drizzle of honey if needed. Same texture, same satisfaction, a fraction of the sodium, and better glycemic control because she eliminated the refined flour and added sugar from the granola. Sodium affects blood pressure through fluid balance. Excess sodium holds water in your bloodstream, increasing volume and therefore pressure against vessel walls. Reducing sodium decreases that volume. The effect is dose-dependent and relatively immediate, which is why some patients see measurable blood pressure changes within a couple of weeks of cutting sodium. Glucose management works differently but complements the same pattern. When you eat carbohydrates that digest quickly, blood glucose rises sharply. The pancreas releases insulin to clear that glucose. Over time, repeated spikes contribute to insulin resistance, which is the core mechanism of type 2 diabetes. Choosing carbohydrates that digest more slowly, combining them with fiber and protein, and reducing overall carbohydrate load where appropriate all blunt those spikes.
Get the Full Details

The two mechanisms intersect at the vascular level. Chronic high glucose damages the endothelium, the inner lining of blood vessels. Damaged endothelium is less able to regulate vascular tone, which makes blood pressure harder to control. This is why dietary management of one condition benefits the other beyond just the individual metrics. You're treating the same tissue with the same approach.
What Most People Miss
Portion size is the silent failure point. A meal can consist of entirely the right foods and still produce a problematic glucose response if the total carbohydrate load is too high for the individual's capacity. This is why a cup of cooked quinoa, which is a solid choice on paper, can raise blood sugar as much as a smaller portion of white rice if the person eating it has significant insulin resistance. The food isn't the only variable. The person's metabolic state matters just as much. Another common blind spot is the assumption that "natural" sugars are metabolically neutral. Honey, maple syrup, coconut sugar, agave nectar — they all raise blood glucose. Agave is particularly misleading because it has a lower glycemic index than table sugar, but that index is measured in isolation. When you consume agave with a meal, the overall glycemic load still matters, and the fructose content in agave adds metabolic that doesn't help either condition. The potassium-sodium ratio deserves more attention than it gets. Most people get way too much sodium and not enough potassium. Potassium helps the kidneys excrete sodium and relaxes blood vessel walls. Foods like spinach, sweet potatoes, beans, and avocado address both conditions while improving this ratio. But potassium supplements are risky without medical supervision, especially for anyone on certain blood pressure medications like ACE inhibitors, which can already raise potassium levels. Food sources are the safe route.
What This Approach Does Not Do
A diet plan will not replace medication for everyone. Some patients with advanced hypertension or significant insulin resistance will continue to need pharmacological support regardless of dietary changes. The diet reduces the required dose in many cases, but it is not a universal substitute. I've seen people try to power through dietary changes alone while their numbers were far too elevated to wait and see, and that delay caused unnecessary damage. The approach also requires consistent effort. One good week won't reset months of poor habits. Blood pressure and fasting glucose respond to sustained patterns, not single meals. The margin for error shrinks if you want reliable results, which means occasional deviations need to be deliberate rather than accidental. For people who struggle with food preparation or have limited access to fresh ingredients, this pattern can be expensive and time-consuming. Canned beans, frozen vegetables, and canned fish are acceptable substitutes that maintain the nutritional profile at a lower cost and effort. The principle matters more than the freshness of every ingredient.

Putting It Together Day To Day
A typical day following this combined approach might look like this: breakfast of eggs with spinach and a small portion of steel-cut oats, lunch of a large salad with mixed vegetables, chickpeas, grilled chicken, and an olive oil-based dressing, dinner of baked salmon with roasted broccoli and a modest portion of quinoa, and snacks of apple slices with almond butter or plain yogurt with a handful of walnuts. The sodium stays under two thousand milligrams. The glycemic load stays moderate. The variety prevents boredom. Tracking isn't strictly necessary if you learn to estimate portions visually, but for the first few weeks, using a tracking app or simply noting what you eat helps you catch the sodium surprises and hidden sugars that most people don't notice until they have a data point. I typically recommend this for about three weeks, after which the pattern becomes intuitive enough that formal tracking isn't required. The combination of these two conditions is not a reason to be more restrictive. It's a reason to be more precise. The overlap in what helps each condition means you aren't balancing competing demands. You're addressing both with a single coherent approach, and that's actually simpler than managing them separately if you have the right framework in place.



