Managing What Goes In Matters Just As Much As What The Machine Pulls Out
Most people think dialysis is the treatment and diet is secondary. That's backwards. The machine handles waste removal, but it doesn't handle electrolyte balance, fluid shifts, or protein loss nearly as well as it should. What a patient eats between sessions determines whether they survive the table time comfortably or spend three hours cramping and hypotensive. This isn't theoretical. I watched a woman at my clinic nearly lose consciousness after a high-potassium meal because her dialysate potassium was set to 2.0 and she'd eaten three bananas that morning. The tech had to intervene with calcium gluconate and a potassium-free bicarbonate bath. It was entirely preventable. Let's start with the macronutrients because that's where most confusion lives. Dialysis actually increases protein needs. The process strips amino acids and small proteins during each session — roughly 6 to 12 grams per treatment depending on the membrane and blood flow rate. Hemodialysis patients typically need 1.0 to 1.2 grams of protein per kilogram of body weight daily, and peritoneal dialysis patients often require even more because glucose absorption from the dialysate causes additional protein catabolism. Most patients are eating 0.6 to 0.8 grams per kilogram, which is malnutrition-level intake. The fix isn't complicated. It's adding an extra egg, a handful of nuts, or a scoop of whey isolate to whatever they're already eating. The problem is phosphorus in protein sources, which brings us to the next piece. Phosphorus management is where people get tripped up. Everyone knows to avoid dairy and nuts, but the real issue is bioavailability. Phosphorus in plant sources like beans and whole grains is bound to phytates and only about 40 to 50 percent is absorbed. Phosphorus in animal products and processed foods with phosphate additives is 90 to 100 percent absorbed. A patient can eat a serving of black beans and be relatively fine, but the same amount of phosphorus in a processed cheese snack or a cola drink is essentially all available. Reading ingredient lists for phrases like "phosphoric acid," "pyrophosphate," and "hexametaphosphate" is non-negotiable. Those additives are in everything from deli meats to frozen meals to some bread brands. I had a patient who switched to a "heart-healthy" whole grain cereal and didn't realize the phosphorus additive in it was adding 400 milligrams to his daily load. His phosphate levels went up despite eating "better." The workaround was switching to plain oatmeal with fresh fruit, which he could control completely.
Potassium is the immediate danger. High potassium causes cardiac arrhythmias and can kill between dialysis sessions. The average hemodialysis patient should keep potassium under 2,000 milligrams daily, sometimes less. But the counter-intuitive part is that leaching vegetables doesn't destroy all the potassium — it reduces it by maybe 30 to 50 percent depending on the method. Cutting potatoes into small pieces and soaking them in warm water for two hours before rinsing and cooking removes more potassium than slicing them large and boiling briefly. Double-boiling is the most effective method. You boil in plenty of water, drain that water, then boil again in fresh water and drain. This can remove up to 70 percent of the potassium from starchy vegetables. The texture suffers, sure, but the alternative is an emergency room visit. Fluid restriction is the hardest part for most patients. The standard advice is 500 milliliters plus whatever urine output they still have. Some patients drink nearly a liter a day between sessions and gain four or five kilograms of fluid weight. That's dangerous. Rapid fluid removal during dialysis drops blood pressure, causes muscle cramps, and over time damages the heart muscle through repeated strain. The practical tip nobody emphasizes enough: salt makes you thirsty. Reducing sodium to under 2,000 milligrams a day often does more to control fluid intake than willpower alone. Salty food triggers thirst that water alone doesn't satisfy comfortably. If a patient cuts sodium and still can't manage fluid, they need to talk to their nephrologist about adjusting dry weight targets or trying a longer, slower dialysis schedule. Vitamin supplementation deserves its own callout. Water-soluble vitamins — B-complex and C — are lost during dialysis in significant amounts. Standard multivitamins designed for healthy adults often contain fat-soluble vitamins A, D, E, and K in doses that can accumulate to toxic levels in kidney patients. Renal-specific vitamins like Nephro-Vite or Renavite are formulated for dialysis patients. They replace what's lost without overloading what can't be excreted. I've seen patients take ordinary Centrum supplements for months and develop vitamin A toxicity symptoms — dry skin, joint pain, headaches — because their kidneys couldn't clear the excess. The renal-formulated versions are cheap and widely available through dialysis centers.
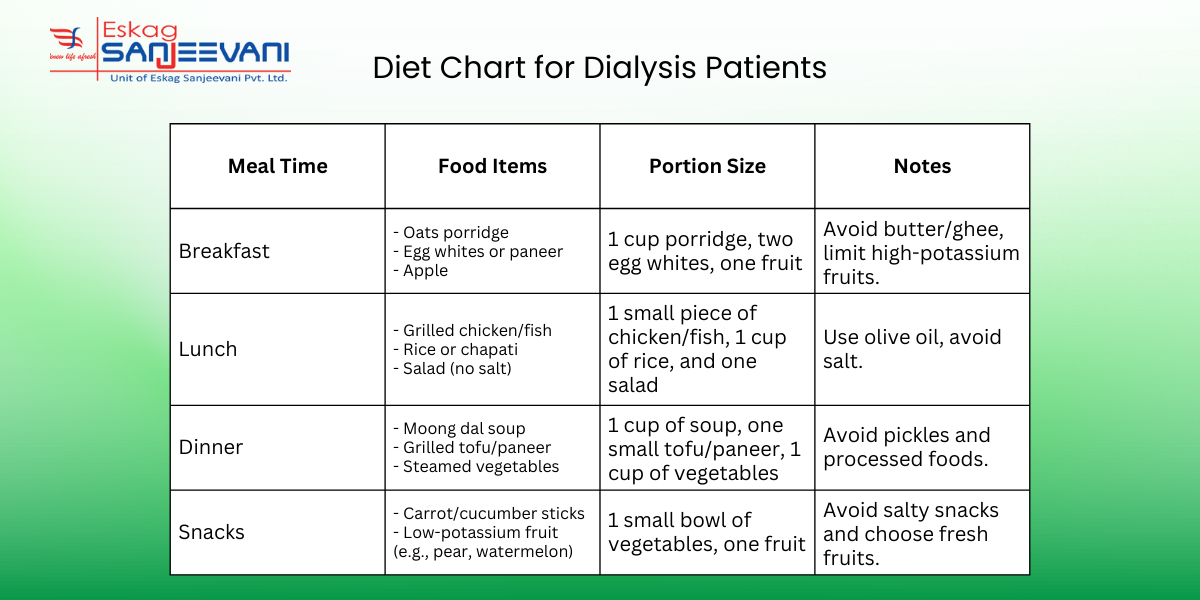
One thing dialysis diet guidelines consistently get wrong in patient handouts is the framing around fruit. Fruits are often demonized because of potassium, but berries, apples, and grapes are relatively low in potassium and high in antioxidants that reduce the chronic inflammation driving cardiovascular disease in dialysis patients. A small bowl of strawberries is fine. Two bananas are not. The nuance matters, and most patient education materials don't provide it. They just say "avoid high-potassium foods" and leave patients confused about what's actually safe. The biggest limitation of any dietary plan for dialysis patients is that it requires constant attention to things most people stop thinking about after a few weeks. Food logging, label reading, meal prep adjustments — it accumulates. Burnout is real and common. Patients who do this perfectly for three months often slide back because the cognitive load is exhausting. The workaround that actually works is batching. Cook in volume on weekends, portion into containers, and stick to a rotating menu of five or six verified-safe meals. Variation comes from sauces and seasonings, not from discovering new ingredients each day. This reduces decision fatigue and makes adherence sustainable.
Get the Full Details