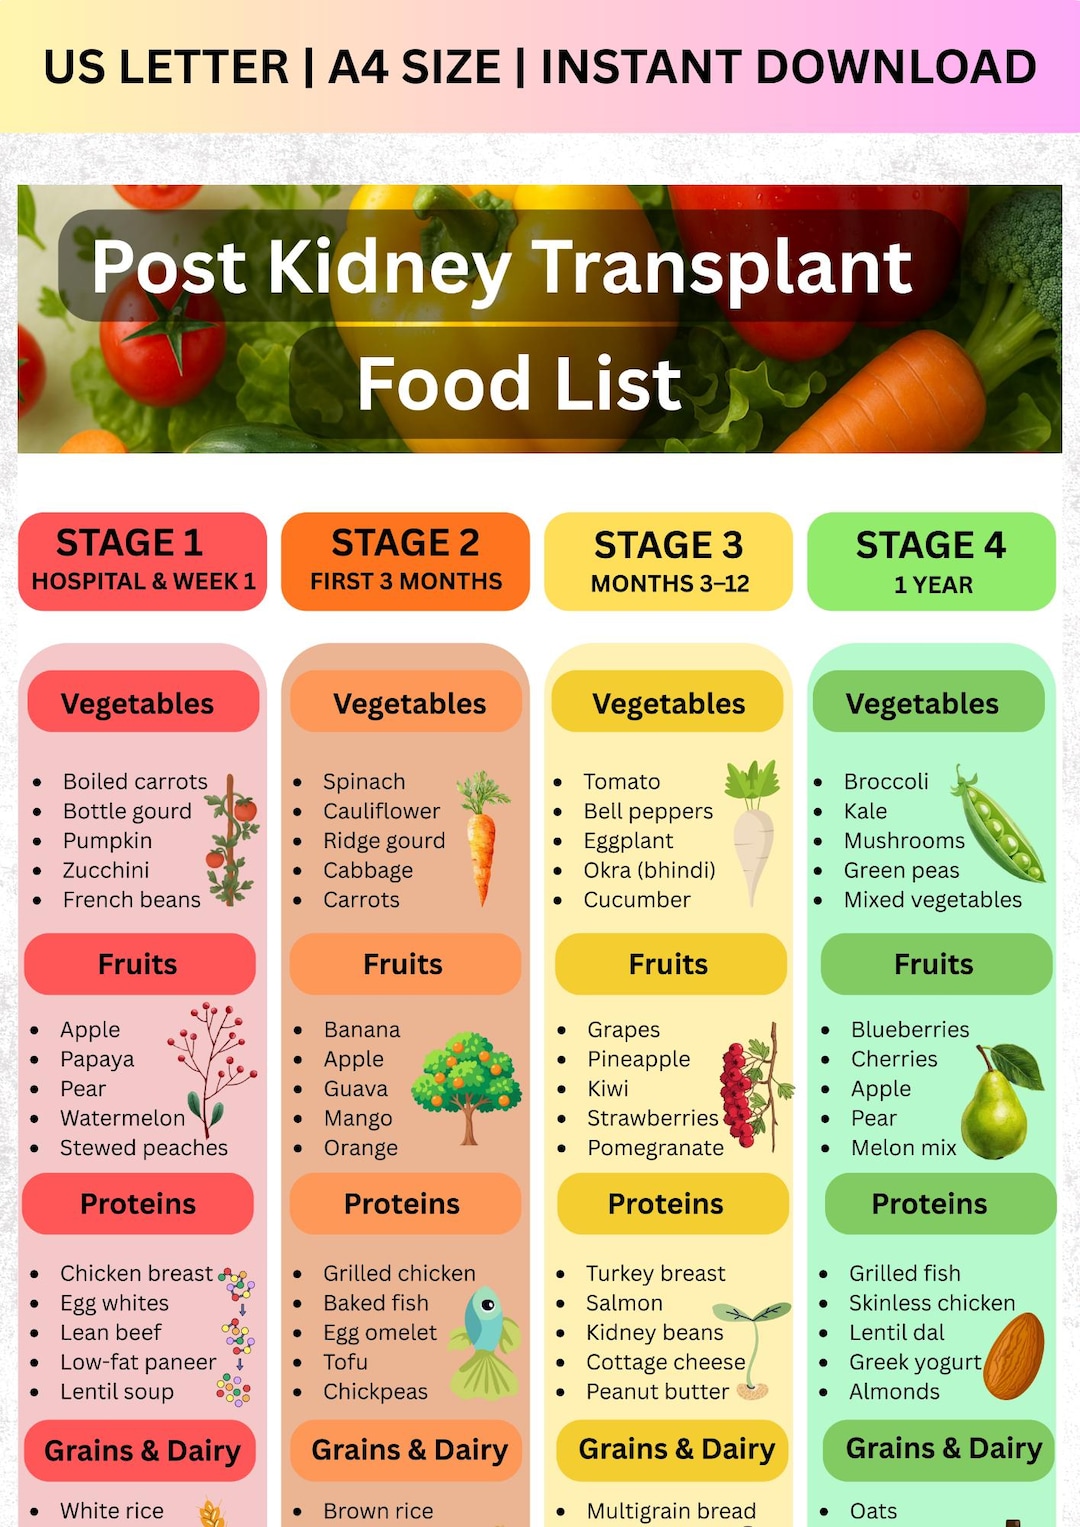
What Actually Happens After the Transplant
The first thing people get wrong is thinking the diet resets once surgery is done. It doesn't. Your new kidney works harder than your old one ever did, but the immunosuppressants you'll be on change how your body processes everything. Tacrolimus, prednisone, mycophyllate — these drugs mess with blood sugar, blood pressure, potassium levels, and lipids. You're managing a healthy organ while your medication creates a whole secondary set of problems. That's the reality most pamphlets skip over. Here's what it actually looks like in practice, not what the transplant center hands you on a glossy sheet. Sodium needs to stay under 2,300 milligrams a day, preferably closer to 1,500. The prednisone alone makes you retain water like crazy. I remember one patient, late fifties, came back three weeks post-op with his ankles swelling to the point where he couldn't wear shoes. He'd been eating canned soup and deli meat because it was "easy." One bowl of that soup had nearly his entire daily sodium allowance. We cut him down to cooking at home with fresh ingredients and swapped deli meats for grilled chicken breast. Swelling went down in four days. That's not dramatic, that's just chemistry. Protein intake shifts too. Pre-transplant you're often told to limit protein because your kidneys can't handle the waste products. Post-transplant, you need more protein to heal and to counteract the muscle-wasting effects of steroids. The sweet spot is usually around 1.0 to 1.3 grams per kilogram of body weight. For someone weighing 75 kilograms, that's roughly 75 to 97 grams of protein daily. You can hit that with a combination of eggs, fish, lean poultry, and maybe a handful of Greek yogurt. Don't go overboard on supplements. Your new kidney doesn't need any extra help clearing protein waste, and high-dose protein powders are just adding unnecessary load.
Potassium is where things get tricky. If your new kidney is functioning well, potassium should normalize on its own within a few weeks. But if there's any delayed graft function or your creatinine stays elevated, your potassium can run high. Bananas, oranges, potatoes, tomatoes, spinach — these are fine for most people with good graft function. They become dangerous if your potassium is already creeping up. I've seen patients at a follow-up appointment whose potassium was 5.8 and they had no idea why. Turns out they'd started a "healthy diet" full of avocado and sweet potato thinking they were doing the right thing. We had to pull back hard and monitor weekly until the numbers stabilized.
The Medication-Food Interactions Nobody Warns You About
Grapefruit is the classic one, but it's worth understanding exactly why. Tacrolimus and cyclosporine are metabolized by CYP3A4 enzymes in your gut and liver. Grapefruit contains furanocoumarins that irreversibly inhibit those enzymes. This isn't a mild interaction. A single grapefruit or a glass of grapefruit juice can increase tacrolimus blood levels by 200 to 300 percent. I had a patient who ate half a grapefruit every morning for a week and then showed up with tremors and headaches. His trough level was through the roof. We had to hold the dose and restart at a lower level. That's a two-week setback from something that costs three dollars at the grocery store. St. John's Wort does the opposite — it induces CYP3A4 and can drop your tacrolimus levels fast enough to risk rejection. People take it for "mood support" without telling their transplant team. Make sure yours knows everything you're putting in your body, including over-the-counter supplements. Timing matters with food too. Mycophenolate mofetil causes GI upset in a significant number of patients. Taking it on an empty stomach makes that worse. Some people find they can tolerate it better with a small amount of food, but high-fat meals can reduce absorption by up to 40 percent. So a handful of crackers is fine. A bacon and cheese sandwich is not. The guidance here is inconsistent across centers, so ask your pharmacist specifically about your formulation.
Get the Full Details

Weight Gain and Blood Sugar
Most transplant patients gain weight after surgery. The combination of prednisone increasing appetite, improved taste and smell as uremia resolves, and reduced physical activity during recovery creates a perfect storm. I've seen patients gain 15 to 20 pounds in the first three months. That's not unusual. The problem is that weight gain worsens insulin resistance at a time when prednisone is already pushing your blood sugar up. New-onset diabetes after transplantation affects roughly 20 to 30 percent of recipients, depending on the immunosuppressive regimen. The practical move is to prioritize protein and fiber early and often. Protein keeps you fuller longer and helps preserve muscle mass that steroids are trying to break down. Fiber slows glucose absorption. Most transplant patients are dramatically under-fibered because they spent years on renal diets that restricted fruits and vegetables. Now that those restrictions are lifting, the natural reaction is to overload on them. Ease into it. Your gut flora has been through some things.
Food Safety Is Not Optional
You are immunocompromised. This isn't theoretical. Listeria, Salmonella, E. coli — these organisms that would give a healthy person a bad day can cause sepsis in you. Raw or undercooked meat, unpasteurized dairy, raw sprouts, deli meats that aren't heated to steaming, sushi, soft-serve ice cream machines. These are real risks. I worked with a patient who ate pre-packaged coleslaw from the grocery store salad bar and ended up in the hospital with Listeria. She survived, but it was a terrifying month she didn't need. Heat deli meats until they're steaming before eating. Avoid anything labeled "raw" unless you accept the gamble. Pasteurized only for dairy and juices. Here's the part that isn't intuitive: lab values don't always match dietary advice in a straightforward way. Your phosphorus might be normal, but your PTH is elevated. That means your bone metabolism is being disrupted by the medications and the transplant itself, not necessarily by what you're eating. Calcium and vitamin D supplementation is common, but the dosing is highly individual. Too much calcium can contribute to vascular calcification, which is already a concern in kidney patients. Your team should be tracking intact PTH, 25-hydroxy vitamin D, calcium, and phosphorus regularly. If they're not, ask. Another counter-intuitive point: you may be told to restrict potassium, but if your lab values are normal and your graft function is good, aggressive potassium restriction is unnecessary and may do more harm than good. Fruits and vegetables have benefits that outweigh the potassium risk in most post-transplant patients. The restriction should be guided by your actual lab work, not a blanket rule. If your potassium is consistently above 5.0, then you adjust. Below that, you eat like a person with a working kidney who happens to be on immunosuppressants.
The long-term picture also involves cardiovascular risk. Kidney transplant recipients have higher rates of heart disease than the general population. Saturated fat, added sugars, and excess sodium compound the lipid and blood pressure issues that come with the medications. This isn't about perfection. It's about stacking small choices in the right direction over years rather than weeks.