What actually works when you're eating around PKD
Most people find out about dietary changes after their nephrologist mentions salt or protein. That's the entry point. Everything else builds on top of it. I've watched patients go years without realizing how much a few simple adjustments matter, and I've also seen people overthink it until they're eating nothing but anxiety and steamed vegetables. The core issue with polycystic kidney disease is that your kidneys are already under stress from cyst growth. The diet isn't going to shrink cysts. Nobody will sell you that lie on a legitimate forum, but supplement companies sure will. What the diet does is slow the secondary damage—blood pressure, inflammation, mineral imbalances—that compounds on top of the PKD itself.
Diet For Polycystic Kidney Disease: The basics nobody rushes through
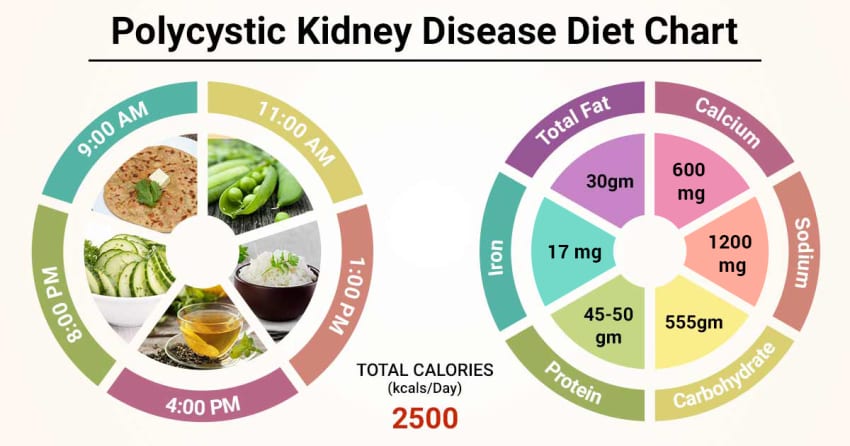
Sodium is the first thing to down. Not because salt directly causes cysts, but because PKD patients have a much higher rate of hypertension, and high blood pressure accelerates kidney function decline independently of the cysts. Aim for under 2,000 milligrams a day. Most people in the US eat between 3,000 and 3,500 without thinking about it. The drop isn't dramatic in week one, but by month three your blood pressure numbers usually improve enough that your doctor takes notice. Protein intake needs to be moderate, not aggressive. The old advice was to slash protein hard. The current guidance is more nuanced: around 0.8 grams per kilogram of body weight for someone with preserved kidney function, tapering lower as eGFR declines. The reason is that high protein increases glomerular filtration pressure, which stresses already compromised nephrons. I had a patient once who was doing keto at 140 grams of protein daily while his eGFR was already in the low 40s. We cut him to about 55 grams, and his proteinuria dropped noticeably within six weeks. He hated the food at first. It took three weeks of meal prep adjustments before he stopped complaining. Phosphorus and potassium management depends entirely on your lab values. This is where generic PKD diet advice falls apart. If your phosphorus is normal and your potassium is normal, you don't need to restrict either. Restricting unnecessarily leads to malnutrition, which is its own problem. Get the labs. Then adjust. I see this mistake constantly in online forums where people copy-paste restrictions from someone in stage 4 CKD and apply them to their own stage 2 PKD.
Hydration is the one area where PKD has unique recommendations compared to other kidney diseases. There's evidence from animal models and some human studies that high water intake suppresses vasopressin, which may slow cyst growth. The typical recommendation is 3 to 4 liters daily, spread throughout the day. Not all nephrologists agree on this, and your fluid restrictions may differ if you already have reduced kidney function or heart issues. But for someone with early-stage PKD and normal cardiac function, adequate hydration is one of the few dietary levers that might actually affect the disease course itself.
Get the Full Details

What people get wrong
The biggest misconception is that you need a special diet from day one. If your labs are normal and your blood pressure is controlled, you don't need to live like a monk. You need to avoid the things that are proven to cause harm—excess sodium, excessive protein, uncontrolled blood sugar—and build from there. A lot of patients I talk to spend their first six months obsessing over every ingredient instead of just cleaning up the big items. Another common trap is the supplement angle. N-acetylcysteine, herbal remedies, "kidney detox" teas. Some of these have actual research behind them. Most don't. The ones that do tend to be expensive and require consistent long-term use with monitored labs. The ones that don't are just taking your money and potentially stressing your liver. I had a patient who started a "natural PKD protocol" from a wellness blog that included high-dose turmeric, astragalus, and a bunch of other extracts. His liver enzymes spiked. We spent two months figuring out which supplement was responsible. It was probably the turmeric at 4 grams daily, but honestly, we never isolated it completely. He stopped everything and went back to diet and hydration alone. His labs stabilized. There's also the issue of fiber and gut health. Newer research is looking at the gut-kidney axis and how gut dysbiosis might contribute to inflammation in CKD patients. For PKD specifically, the evidence is thin, but ensuring adequate fiber—25 to 30 grams daily from food sources—doesn't hurt and may help with blood pressure and lipid management. Don't reach for supplements here. Beans, oats, vegetables, fruit. It's boring and it works.
When diet isn't enough
Let me be clear about the limitations. Diet for polycystic kidney disease will not stop cyst growth. It will not regenerate kidney tissue. It will not replace medication or monitoring. What it does is remove unnecessary stressors from an organ system that is already working harder than it should. Think of it as damage control, not a cure. If your eGFR is declining faster than expected, if your blood pressure won't come down despite lifestyle changes, if you're dealing with pain from large cysts—those are conversations for your nephrologist, not your meal planner. Tolvaptan is an FDA-approved medication for PKD that actually targets cyst growth. It has significant side effects, including excessive urination and potential liver toxicity, but it's a real treatment option for fast-progressors. Diet doesn't replace that conversation. The practical takeaway is straightforward. Track your sodium. Match your protein to your kidney function stage. Hydrate adequately if your doctor agrees. Get your labs every three to six months and adjust accordingly. Don't chase miracles on forums. And for god's sake, don't start any supplement regimen without running it past your nephrologist first.




