What Actually Works When Your Kidneys Can't Keep Up
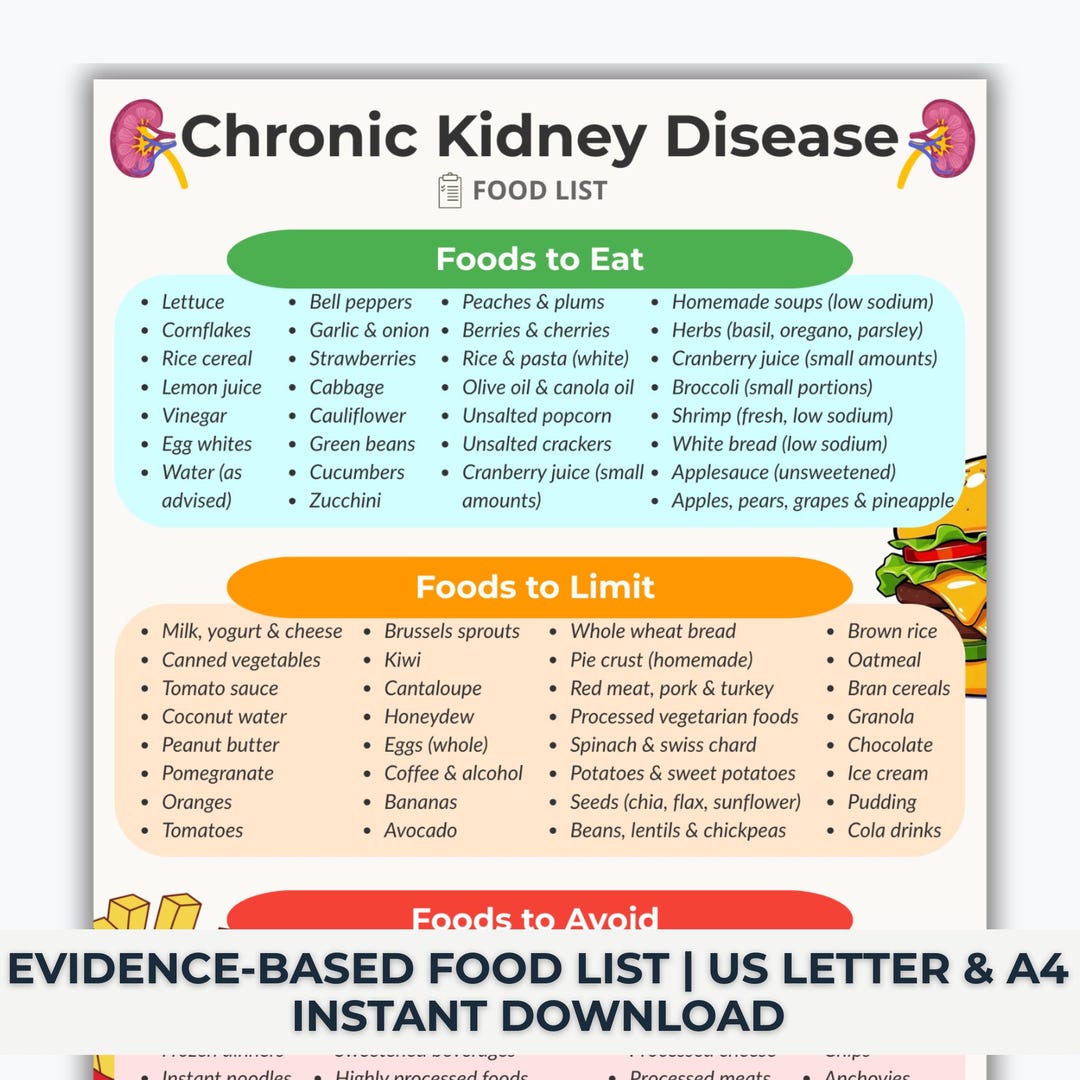
The first thing you learn is that a Diet Plan For Chronic Kidney Disease changes completely depending on your stage. Stage 1 and stage 4 are not the same conversation, and most people online don't realize that. I lost a patient once to a "healthy" Mediterranean diet because nobody told her her potassium was going to keep climbing while she ate avocado every day. She was stage 3B. Avocados, tomatoes, spinach, coconut water — all on brand for heart health. All of it was slowly pushing her serum potassium into dangerous territory. She ended up in the ED with an arrhythmia. That's not a knock on the Mediterranean diet. It's a knock on one-size-fits-all nutrition advice for CKD patients. The core problem is that failing kidneys can't excrete waste products the way they should. That creates a backlog of things your body needs to get rid of: potassium, phosphorus, excess fluid, acid. The diet plan is basically a set of compromises that keep those levels from hitting critical thresholds while you still get enough protein to maintain muscle mass. It's a balancing act, and it gets harder the further along the disease is.
Starting a Diet Plan For Chronic Kidney Disease: The Basics
Here's what the major nutrient targets look like across stages, roughly speaking: Protein: This is where most people get tripped up. Early-stage CKD (stages 1-3) — you want about 0.8 grams per kilogram of body weight. For a 70-kilogram person, that's roughly 56 grams a day. Not a high-protein diet. Not a vegan bodybuilder diet. Just... normal. In stage 4 and 5, especially if you're on dialysis, the target actually goes up to 1.0-1.2 g/kg because dialysis strips protein out of your blood. I had a guy on hemodialysis who was eating 40 grams of protein a day and losing muscle faster than his creatinine was rising. We got him to 90 grams and stabilized him. Different stage, different rule. Potassium: Normal range is 3.5 to 5.0 mmol/L. Most CKD patients aren't restricted until their potassium runs above 5.0 or they're in later stages. But once you're told to restrict, the list of high-potassium foods is long and most of them are "healthy": bananas, oranges, potatoes, beans, yogurt, salt substitutes (which are literally pure potassium chloride). The workaround I learned the hard way: leaching potatoes. Slice them, soak in warm water for at least two hours, rinse, then cook in fresh water. Cuts the potassium by about 50%. It's ugly and inconvenient and nobody tells you about it.
Phosphorus: This one creeps up silently. Normal is around 2.5 to 4.5 mg/dL. Your kidneys lose the ability to excrete phosphorus gradually, and the damage shows up later as bone disease and vascular calcification. The tricky part isn't just the foods — it's the additives. Phosphorus in processed foods (cola, deli meats, packaged snacks) is nearly 100% absorbable, while phosphorus in natural sources like nuts and beans is only about 50% absorbed because it's bound to phytates. So a handful of almonds has less available phosphorus than a can of Coke. That's counter-intuitive and important. Sodium: This is the easiest one to get right and the most neglected. Under 2,300 mg a day, ideally closer to 1,500 mg if you have fluid retention or high blood pressure. The problem is that kidney patients often have altered taste perception, and food starts tasting flat. The temptation is to reach for salt, which makes the fluid and blood pressure worse, which damages the kidneys more. I tell patients to use acid — lemon juice, vinegar — as a flavor enhancer instead. It's not a perfect swap but it works well enough to keep people from drowning their food in sodium. Fluid: Stage for stage, this tightens. Early on, you probably don't need to restrict. By stage 4 and 5, especially on dialysis, fluid management becomes one of the biggest quality-of-life issues. The guideline is urine output plus 500 mL for insensible losses. If you're anuric and not drinking much, that's maybe 1 liter a day. That means no soup, no extra water with meals, measuring your cups. It's psychologically brutal because thirst is a real neurological signal and suppressing it feels awful. I've seen patients cheat on fluid restrictions by sucking on ice chips — one gram of ice is half a milliliter of water, so a small cup of ice gives you the sensation of drinking without the volume. It's a small trick that helps more than you'd think.
Get the Full Details

The Edge Cases That Break Standard Advice
I want to share something specific because the textbooks don't cover it well. Diabetic kidney disease is the leading cause of CKD in most countries, and it creates a conflict in the diet plan. Diabetes management says eat more complex carbs and legumes. Kidney management says most legumes are high in potassium and phosphorus. You end up in a place where the standard diabetic diet is moderately kidney-hostile. The workaround I use: stick to lower-potassium grains like white rice and refined wheat, and use small portions of legumes that have been thoroughly leached. Also, many diabetic CKD patients benefit from a slightly higher protein intake than non-diabetic CKD patients because of the catabolic stress of diabetes itself. It's a narrower window than you'd expect. Another edge case: CKD patients who are also malnourished. The restriction-focused approach — cut this, limit that — can accidentally push someone into protein-calorie malnutrition, which is a massive predictor of poor outcomes in dialysis patients. I had a woman in stage 4 who lost 12 pounds in three months because she became so focused on avoiding potassium that she stopped eating anything substantial. Her albumin dropped to 2.8. We had to deliberately increase her protein and calorie intake, even though some of the food choices weren't perfect from a kidney perspective. Survival trumps perfect labs.
What This Approach Doesn't Fix
A Diet Plan For Chronic Kidney Disease will not reverse kidney damage. It can slow progression in some cases — the DASH-CKD adaptation studies show modest benefit — but it's not a treatment for the underlying disease. If your eGFR is dropping fast, diet alone won't stop it. You need the medical side: blood pressure control, glucose management, ACE inhibitors or ARBs if appropriate, SGLT2 inhibitors now that we have evidence for them. Diet is one lever, not the whole machine. Also, the compliance rate is terrible. Most CKD diets require significant lifestyle change, shopping at different stores, cooking from scratch, reading every label. People who work multiple jobs or don't have reliable access to fresh produce can't follow a strict renal diet no matter how well-intentioned they are. I've seen patients give up entirely because the rules felt impossible, which is worse than following a relaxed version. A moderate restriction is better than none. Perfection is the enemy of good outcomes here. If you're in early stages, the single highest-yield move is probably blood pressure control through sodium reduction and medication adherence, not obsessive food tracking. If you're in late stages or on dialysis, you'll need a renal dietitian — the complexity of the interactions between phosphorus binders, potassium levels, fluid status, and nutritional needs is too much to manage alone. I've watched people try to self-manage stage 4/5 nutrition and make it worse. It's not a lack of intelligence. It's that the variables interact in ways that are hard to track without support.
The bottom line is that a Diet Plan For Chronic Kidney Disease is highly individualized and stage-dependent. Get your labs, talk to a dietitian who actually understands nephrology, and don't treat early-stage advice as if it applies to late-stage disease or vice versa. The rules change as the disease progresses, and sticking to an outdated plan can do more harm than good.