The Insulin Connection Most People Skip
PCOS isn't just about irregular periods or excess hair. At its core, it's frequently an insulin resistance problem, and that changes how you need to approach food entirely. Your body struggles to process glucose efficiently, which drives androgen production and makes weight management significantly harder than it should be. I learned this the hard way after watching patients (and myself) obsess over calories while ignoring the hormonal machinery underneath. The first thing to understand is that not all carbs are created equal in this context. A 45-gram serving of white rice and a 45-gram serving of lentils will do completely different things to your blood sugar and insulin levels, even though they arrive with identical carb counts. That distinction matters more than anything else on this plan.
Diet Plan For Pcos Sufferers
Here's what actually works in practice. Start each meal with fiber and protein before you touch any carbohydrates. That sequence alone can blunt the insulin spike by roughly 30 to 40 percent compared to eating carbs first. It sounds simple because it is simple, but most people eat in the opposite order without realizing it. Basal framework: Target around 30 to 40 grams of carbohydrates per meal, prioritizing low-glycemic sources. That puts you somewhere in the 90 to 120 gram range daily, which is low enough to meaningfully improve insulin sensitivity for most people with PCOS without crossing into dangerous territory. Pair each meal with at least 25 grams of protein and 10 to 15 grams of healthy fat. The fat slows gastric emptying, which further moderates glucose absorption.
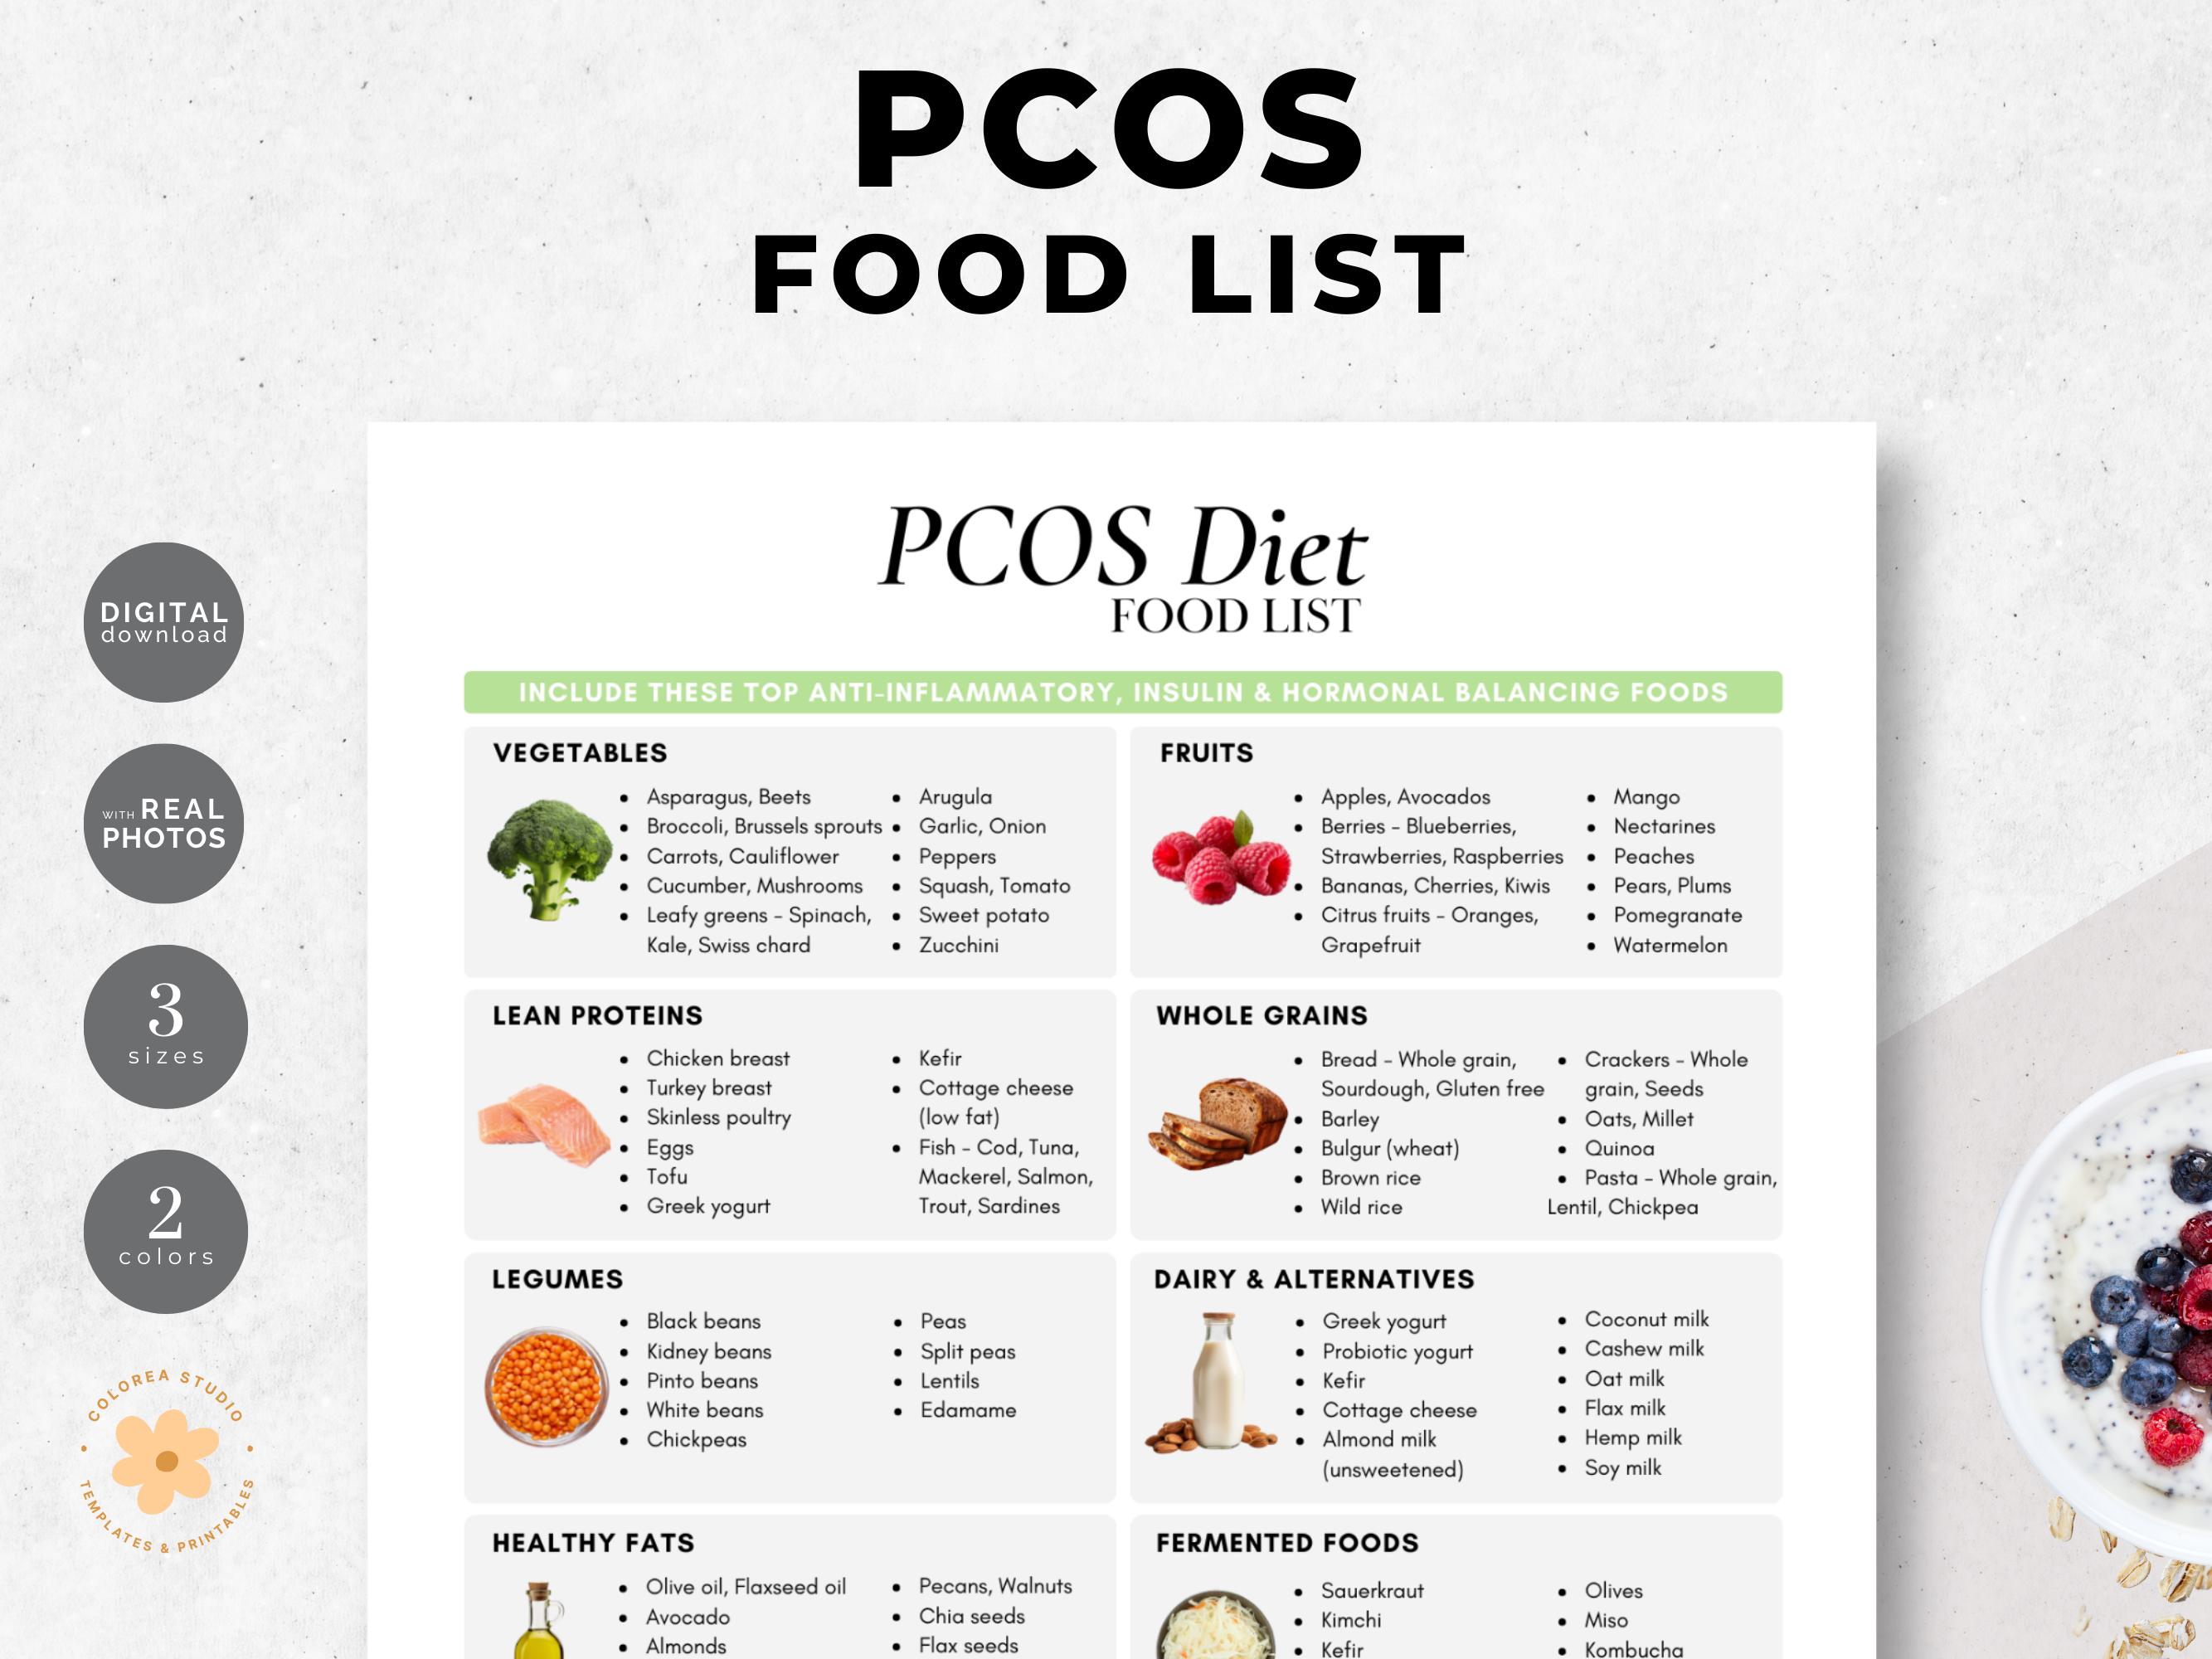
A typical day looks something like this: breakfast of three eggs with spinach and half an avocado, roughly 12 grams of carbs. Lunch with a base of chickpeas or black beans, leafy greens, olive oil dressing, and a protein source like chicken or tofu, hovering around 35 grams of carbs. Dinner centered on something like salmon with roasted vegetables and a small portion of quinoa or sweet potato, maybe 40 grams of carbs. That's roughly 87 grams total. You could swap the quinoa for barley or millet if you prefer variation. What to emphasize: Chromium-rich foods like broccoli, green beans, and Brussels sprouts support glucose metabolism. Inositol supplements, specifically myo-inositol and D-chiro-inositol in a 40:1 ratio, have solid evidence behind them for improving ovulation and insulin sensitivity. Most studies use two grams of myo-inositol twice daily. It's one of the few supplements with actual clinical backing for PCOS, not just anecdotal reports.
Get the Full Details

Fatty fish two to three times per week provides omega-3s that help reduce inflammation, which is chronically elevated in PCOS. Berries, particularly blueberries and raspberries, offer antioxidants with minimal sugar impact. Cinnamon, about half a teaspoon daily, has modest evidence for improving insulin sensitivity, though it won't replace dietary changes. What to minimize or avoid: Refined carbohydrates, sugary beverages, and processed snacks are the fastest route to worsening insulin resistance. Even "healthy" juices strip away the fiber and leave you with concentrated sugar that hits your bloodstream almost immediately. Alcohol also impairs glucose regulation and can trigger cravings, so limiting it is worth considering.
I ran into a specific edge case that nobody warned me about. A patient was eating what she thought was a perfect PCOS-friendly breakfast: Greek yogurt with berries and a drizzle of honey. Blood work showed her fasting insulin hadn't improved at all. The honey was the culprit. About a tablespoon contains 17 grams of sugar with no fiber to slow absorption, essentially acting like table sugar in terms of insulin response. We swapped it for a sprinkle of cinnamon and chopped walnuts instead, and her markers improved within eight weeks. Here's a counter-intuitive point that most people get wrong: not every PCOS case is driven primarily by insulin resistance. Roughly 20 to 30 percent of women with PCOS have normal insulin sensitivity. For those individuals, aggressive carbohydrate restriction doesn't produce the dramatic improvements you'd expect. If you've been following a low-carb PCOS diet for three months with no change in your cycle regularity or symptoms, getting your fasting insulin and HOMA-IR checked is worthwhile. You might be dealing with a different subtype that responds better to anti-inflammatory approaches rather than carbohydrate manipulation alone. Another thing that surprises people: extreme low-carb diets can sometimes worsen PCOS symptoms by increasing cortisol. When carbohydrate intake drops too low, your body perceives it as a stressor. Elevated cortisol disrupts your hypothalamic-pituitary-ovarian axis, which can suppress ovulation further. There's a floor below which going lower becomes counterproductive, and for most women with PCOS, that floor sits around 50 to 60 grams of net carbohydrates per day. Below that, the stress response tends to outweigh the insulin benefits.
Practical implementation: Meal prep saves significant time here. Dedicate two hours on Sunday to cook a batch of protein, roast a tray of vegetables, and prepare a grain like quinoa or lentils. Portion everything into containers. During the week, assembly takes about ten minutes per meal. Without prep, you'll likely reach for convenience foods that undermine your progress. Track your intake for at least two weeks using something like Cronometer or MyFitnessPal. Not forever, just long enough to calibrate your intuition. Most people dramatically underestimate how many carbohydrates are in what they're eating. Once you've seen the numbers for a couple of weeks, you'll develop a reasonable estimate without needing to log everything constantly.

Supplements worth discussing with your doctor: Myo-inositol at two grams twice daily, magnesium glycinate at 200 to 400 mg in the evening, vitamin D if your levels are low (which is common), and omega-3 fish oil providing two to three grams of combined EPA and DHA daily. These have the strongest evidence base among available options. Limitations to be honest about:
This approach isn't a cure. It manages symptoms and improves metabolic markers, but it doesn't eliminate PCOS. Some women see dramatic improvements in cycle regularity within eight to twelve weeks. Others notice subtle changes over several months. A small percentage see minimal benefit regardless of adherence, and that's when exploring other mechanisms or working with an endocrinologist becomes important. Social situations make consistent eating patterns difficult. Travel, family gatherings, and work events don't always accommodate structured meals. Having a go-to strategy for those moments, like carrying protein bars or identifying safe restaurant options in advance, prevents occasional slips from becoming full relapses. If you have concurrent conditions like thyroid disorders, which frequently co-occur with PCOS, the dietary approach needs adjustment. Hypothyroidism affects metabolism differently, and the carbohydrate targets might need to be slightly higher to support thyroid function while still managing insulin. Working with both an endocrinologist and a registered dietitian who understands PCOS gives you the best chance of a plan that actually fits your physiology rather than a one-size-fits-all template.