What Actually Works When Your Doctor Says Lower Your Blood Pressure
I spent about three years working with patients who had hypertension as a dietitian, and honestly the most frustrating thing wasn't the food choices. It was watching people try to combine every single recommendation at once and give up within two weeks. That's the thing nobody tells you about Diet Plans High Blood Pressure before you actually sit down to follow one. The science is solid but the implementation is messy, and most guides skip that part entirely. DASH stands for Dietary Approaches to Stop Hypertension and it was designed by the National Institutes of Health in the late 1980s. The original protocol targets 800 to 1,000 milligrams of calcium, 470 milligrams of potassium, and roughly 30 milligrams of magnesium daily while keeping sodium below 2,300 milligrams, ideally closer to 1,500. That sounds straightforward until you read a label and realize a single serving of canned soup has 890 milligrams of sodium. You are not failing because you are weak. You are failing because the food supply is engineered to make this diet hard to execute without planning. The first practical shift most people need is understanding that reducing sodium is only one lever. Increasing potassium, calcium, and magnesium through whole foods does more for blood pressure than sodium reduction alone in many cases. A 2021 meta-analysis in the Journal of the American Heart Association found that the combined effect of increased potassium intake and reduced sodium produced a greater drop in systolic blood pressure than either change independently. That is the counter-intuitive part beginners miss. They eliminate salt, eat bland food, and then wonder why their numbers barely move.
Diet Plans High Blood Pressure in Practice
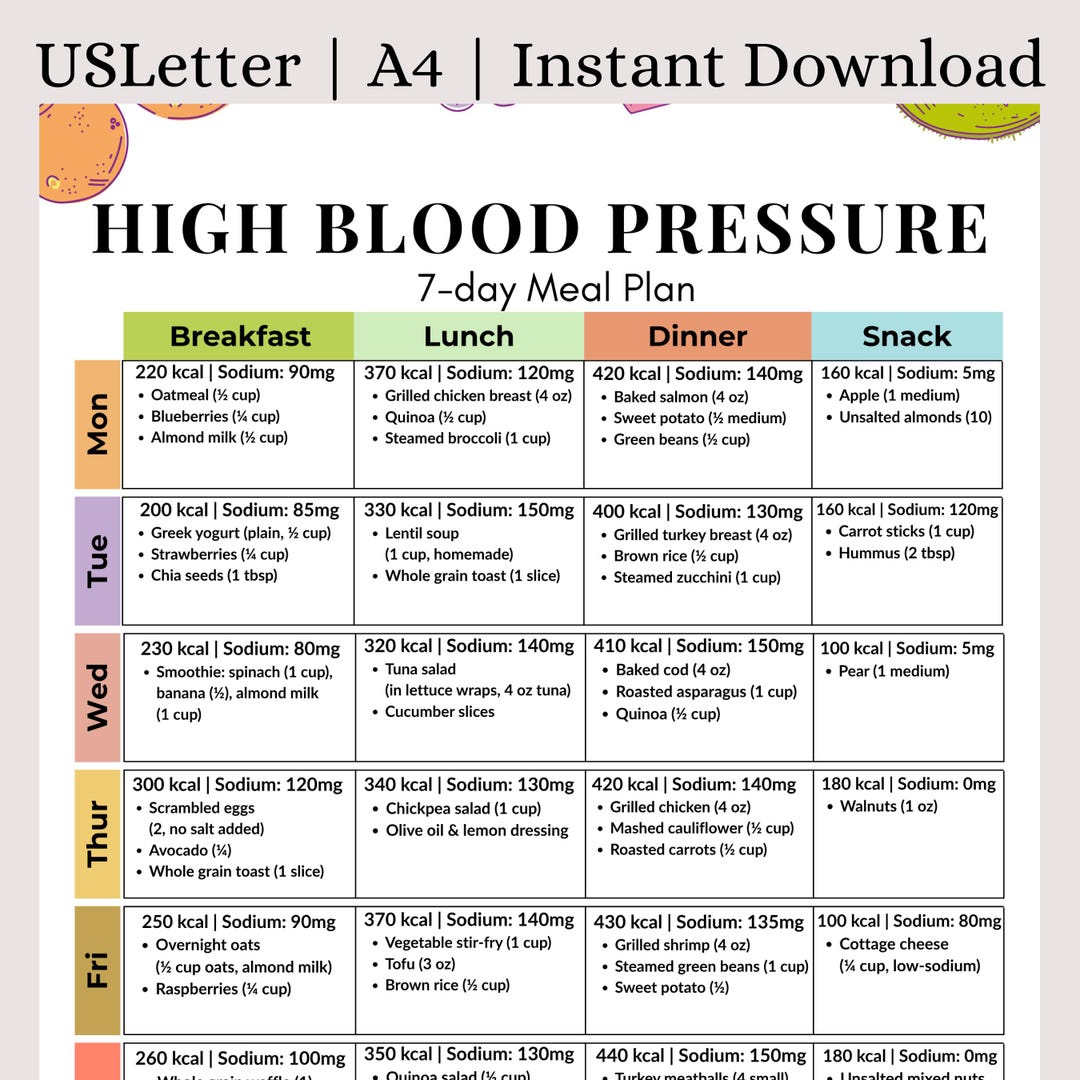
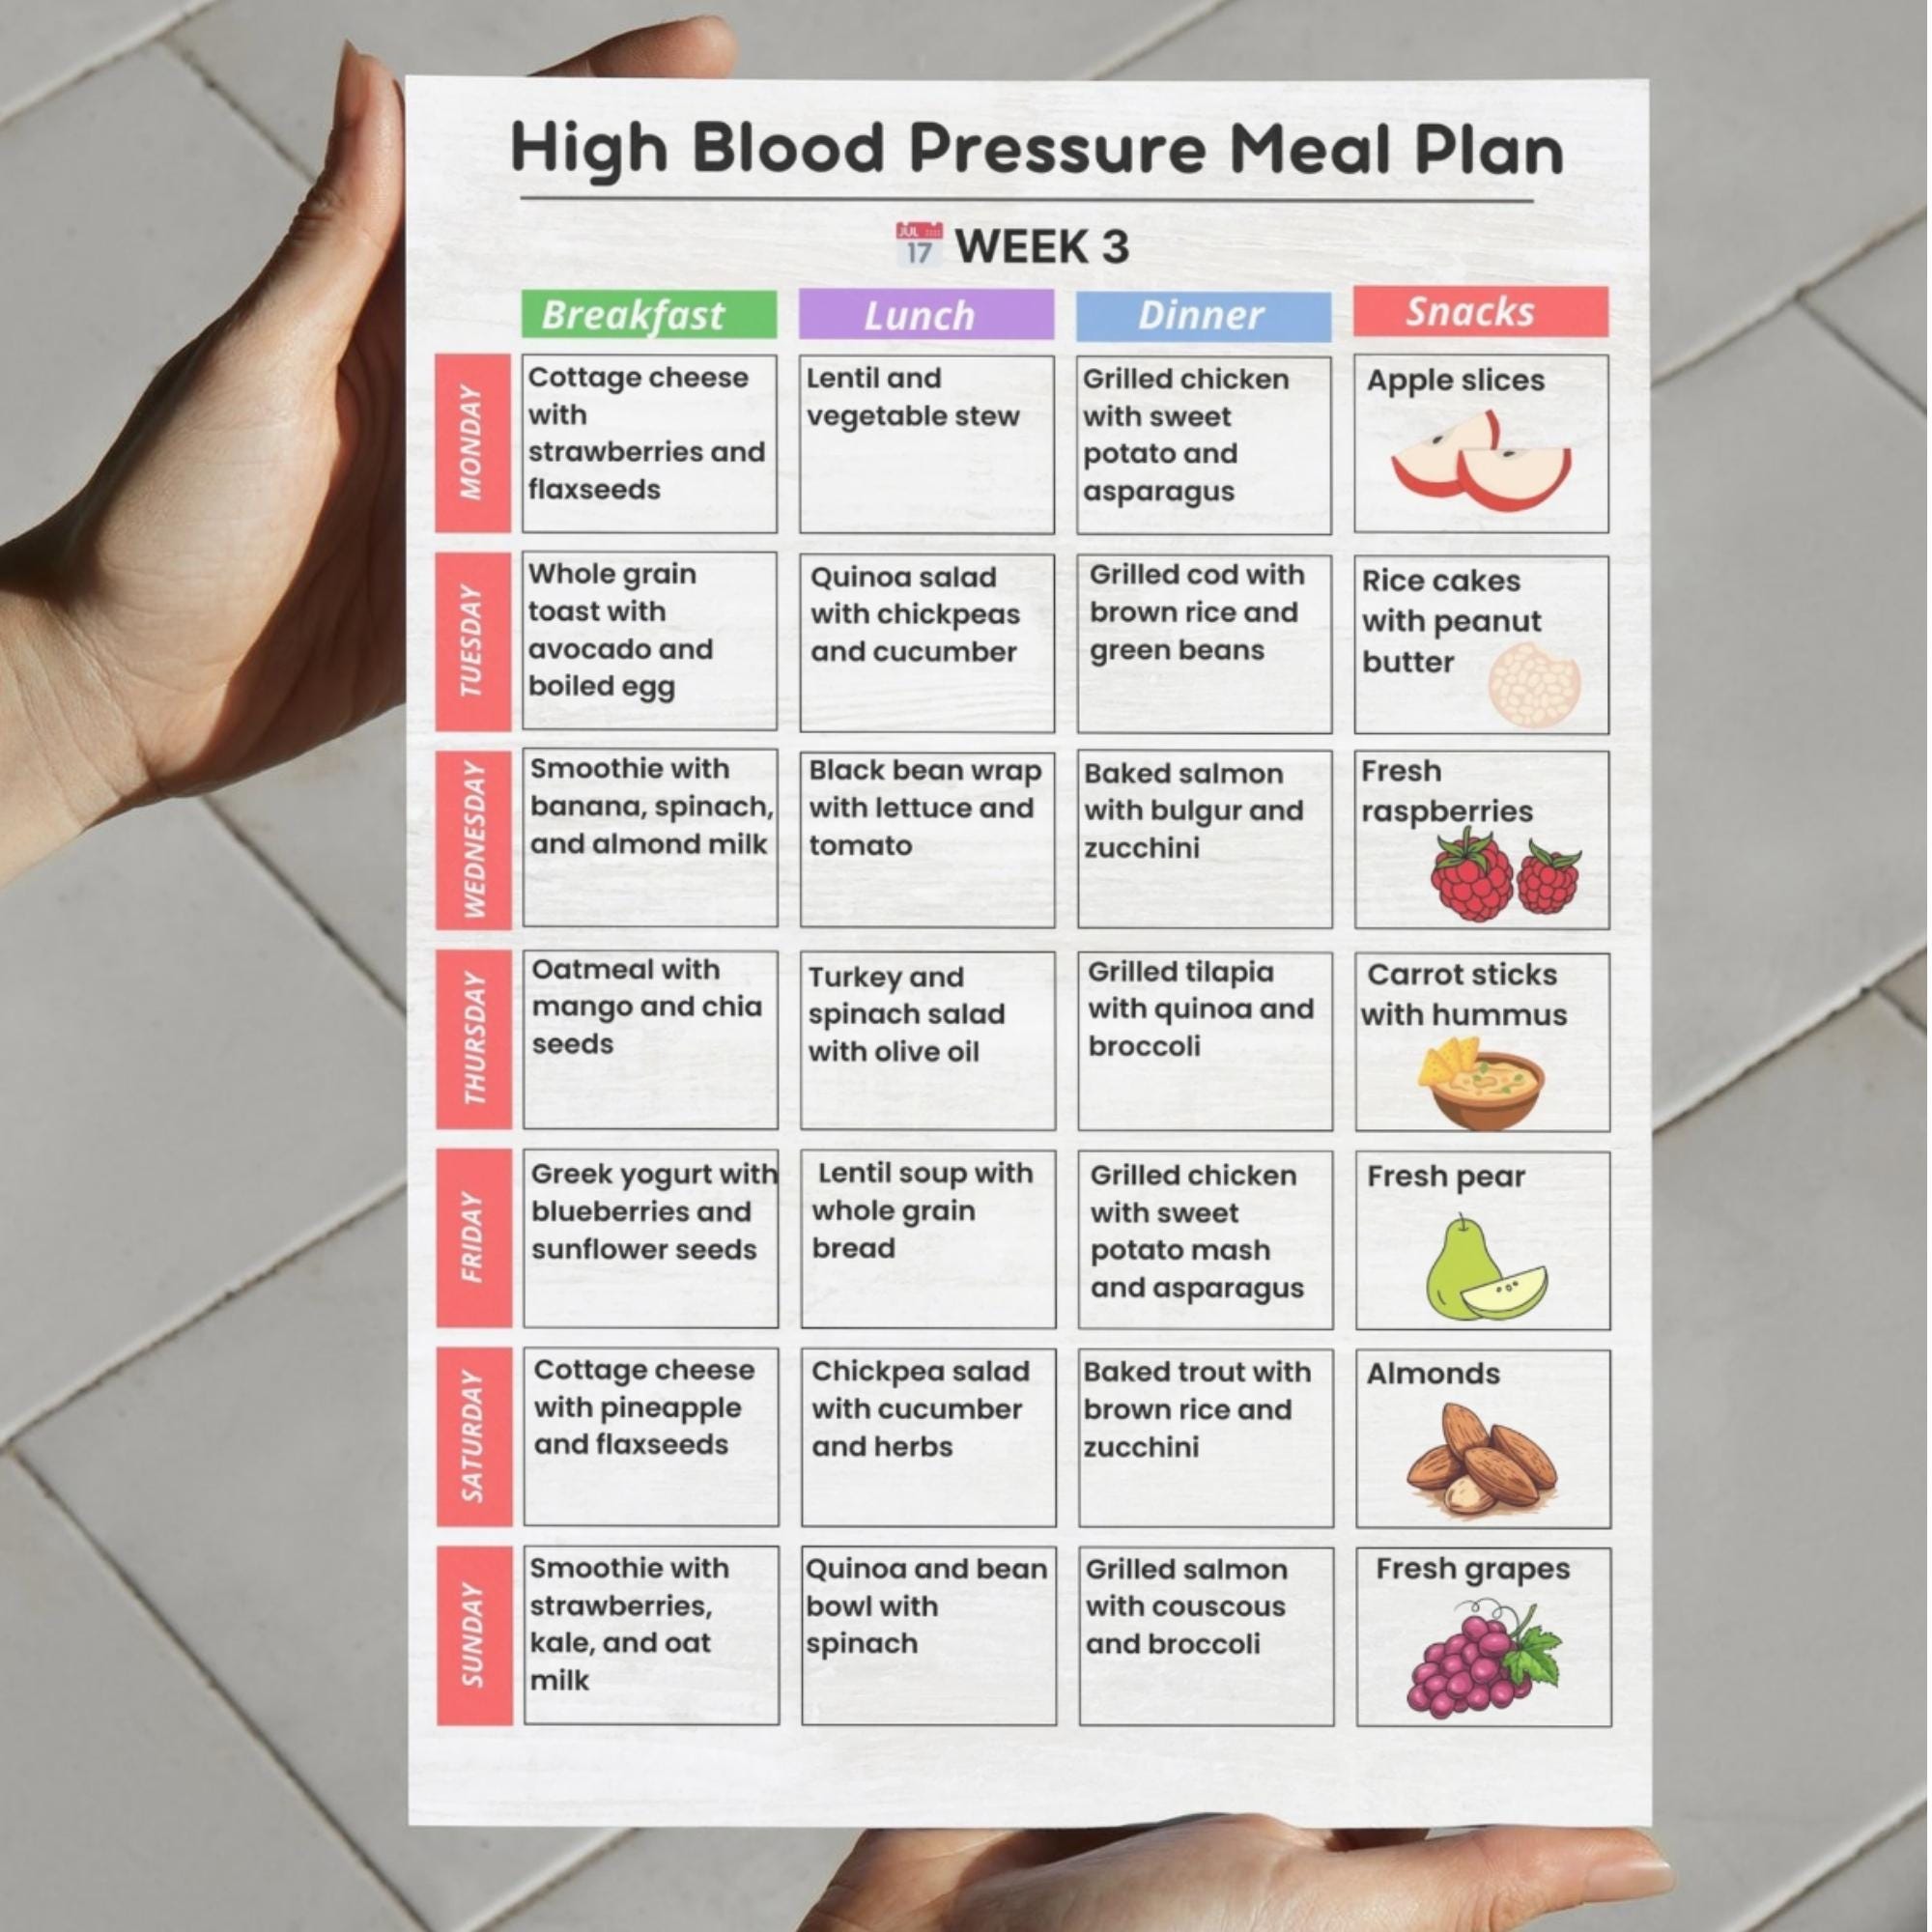
Let me walk through what a realistic weekly structure actually looks like. Breakfast is usually something like oatmeal made with low-fat milk, a banana, and a handful of walnuts. That single meal hits roughly 350 milligrams of potassium, 300 milligrams of calcium, and 80 milligrams of magnesium. Lunch might be a large salad with spinach, black beans, avocado, and grilled chicken, dressed with olive oil and lemon juice. That pushes you past 600 milligrams of potassium and close to 150 milligrams of magnesium before you even eat dinner. Dinner typically involves fish or lean poultry with roasted vegetables and a small portion of brown rice or quinoa. The goal is fiber, roughly 30 grams daily, because soluble fiber binds to bile acids and helps the body process cholesterol more efficiently. That is not directly about blood pressure but the vascular improvement matters over time. Most people on these plans see a systolic drop of about 8 to 11 millimeters of mercury within six to eight weeks if they stick to the framework consistently.
The Canning Soup Problem and a Workaround That Actually Sticks
Here is the edge case I ran into constantly. People who travel frequently or work long hours have almost no time to cook from scratch. They reach for convenience foods, which are sodium bombs. I had one patient, a nurse working 12-hour shifts, who kept blowing her daily sodium limit despite trying her best. She wanted to quit the plan entirely because she felt like she was failing at something her life literally depended on managing. The workaround was not willpower. It was buying low-sodium canned beans and rinsing them under running water for about 30 seconds, which removes roughly 40 percent of the added sodium. She also started keeping a container of pre-chopped vegetables in her bag alongside a single-serve packet of olive oil and a vinegar squeeze. When hunger hit at 3 AM between shifts, she could throw together something edible without processing 900 milligrams of sodium in one sitting. It was not glamorous. It kept her numbers down.
Get the Full Details

Ketogenic Diets and Blood Pressure: The Unexpected Angle
This is where it gets complicated. A lot of people ask me if keto works for hypertension. The short answer is that some patients see significant drops, but not for the reason they expect. On a ketogenic diet, insulin levels drop, which causes the kidneys to excrete more sodium and water. That initial fluid loss can lower blood pressure quickly, sometimes within days. But that effect plateaus. Once the body adapts, the numbers tend to stabilize at a modest reduction, not the dramatic drops people advertise online. More importantly, keto diets are often high in saturated fat because bacon, cheese, and butter become dietary staples. For someone with hypertension who also has elevated LDL cholesterol, this combination is risky. I would not recommend keto as a first-line approach for high blood pressure unless someone has already tried DASH or Mediterranean-style eating and failed, and even then it should be done with a clear eye on lipid profiles. The standard approach remains safer for the vast majority of people.
What Most People Overlook: Alcohol and Processed Meat
Alcohol is a direct vasopressor. Two drinks a day can raise systolic blood pressure by about 4 millimeters of mercury, and three or more drinks can push it even higher. Yet most diet plans for hypertension do not address alcohol with the emphasis it deserves because it is not a food group. It is a behavioral factor, and behavioral factors are harder to talk about than vegetables. Processed meat is another silent contributor. Bacon, deli turkey, salami, and hot dogs contain not just sodium but nitrites and nitrates, which can damage the endothelium, the lining of your blood vessels. Over time, endothelial dysfunction makes it harder for arteries to relax and widen, which is exactly what you want when you are trying to lower blood pressure. Swapping processed meat for fresh poultry, fish, or legumes is one of the single most effective changes you can make, and it is also one of the easiest. The difference between a $12 pack of bacon and a $4 can of black beans is not just cost. It is cardiovascular risk.
Supplements and Their Actual Role
Supplements are not a replacement for diet but they can fill gaps. Potassium supplements are effective, but they carry risk if you have kidney disease or take certain medications like ACE inhibitors or potassium-sparing diuretics. Hyperkalemia, dangerously high potassium in the blood, is a real and potentially fatal complication. I have seen patients end up in the emergency room because they started a supplement without checking with their doctor first. That is why food sources of potassium are always preferred over pills. Magnesium supplementation can help, typically around 300 to 400 milligrams daily of magnesium glycinate or citrate, and there is moderate evidence supporting a systolic reduction of about 2 to 4 millimeters of mercury. Coenzyme Q10 has similar modest effects. But again, these are supplements to an existing diet, not shortcuts around one.
The Realistic Timeline and When It Fails
If you commit to a structured approach like DASH for 12 weeks, you should see a measurable change on your home monitor within the first two to three weeks. If you are not seeing any movement after six weeks, the issue is usually either hidden sodium sources in your diet or an underlying secondary cause of hypertension that diet alone cannot fix. Conditions like renal artery stenosis, primary aldosteronism, or obstructive sleep apnea can drive blood pressure independently of what you eat. In those cases, diet adjustments help marginally but medication or procedural intervention is necessary. I do not say that to discourage anyone. I say it because people waste months blaming themselves for a medical problem that food cannot solve, and that guilt is counterproductive. The right next step after a reasonable trial of dietary change is going back to your doctor and asking about secondary causes, not starting yet another restrictive diet.