
What Actually Matters When You're Trying to Conceive
The diet to prepare for pregnancy isn't a fad. It's a cluster of small, unglamorous adjustments that most people overlook because they're boring. You'll find lots of articles telling you to eat superfoods and take every supplement on the shelf. That's not what moves the needle. The real stuff is about nutrient timing, baseline bloodwork, and removing the things that silently wreck fertility. I've sat through more preconception consultations than I care to count, and the patterns are always the same. The core protocol comes down to five things, and none of them require a degree in nutrition to implement. First, you're looking at folic acid at 400 to 800 micrograms daily, starting at least three months before conception. Not during. Three months before. Neural tube closure happens in the first four weeks of gestation, often before a person knows they're pregnant. Second, iron status matters more than people admit. Low ferritin correlates with ovulatory dysfunction in a significant subset of patients. Third, omega-3 intake, specifically DHA at around 200 to 300 milligrams daily, supports egg membrane fluidity and early embryonic development. Fourth, vitamin D levels should be checked and maintained above 30 nanograms per milliliter. Fourth is actually fifth because I just miscounted. The point stands though. Carbohydrate quality drives insulin sensitivity, and insulin resistance is a silent fertility killer regardless of whether you have PCOS or not. Swapping refined grains for whole food sources like quinoa, sweet potatoes, and legumes steadies glucose and reduces inflammatory load. Pairing carbs with protein and fat at every meal cuts the glycemic spike significantly. This isn't theoretical. A 2017 study in Human Reproduction showed that higher glycemic load diets were associated with increased ovulatory infertility risk by roughly 60 to 70 percent in women consuming high amounts of refined carbs daily.
Full-fat dairy versus low-fat dairy is another one of those counter-intuitive findings that catches everyone off guard. Multiple studies, including research from the Harvard Nurses' Health Study, found that full-fat dairy consumption was associated with a lower risk of ovulatory infertility while low-fat dairy showed the opposite trend. The mechanism likely involves the fat-soluble vitamins and conjugated linoleic acid in whole milk products. It sounds wrong when you hear it the first time. It's been replicated enough that it's now part of standard preconception counseling.
The Things Nobody Talks About Until It's Too Late
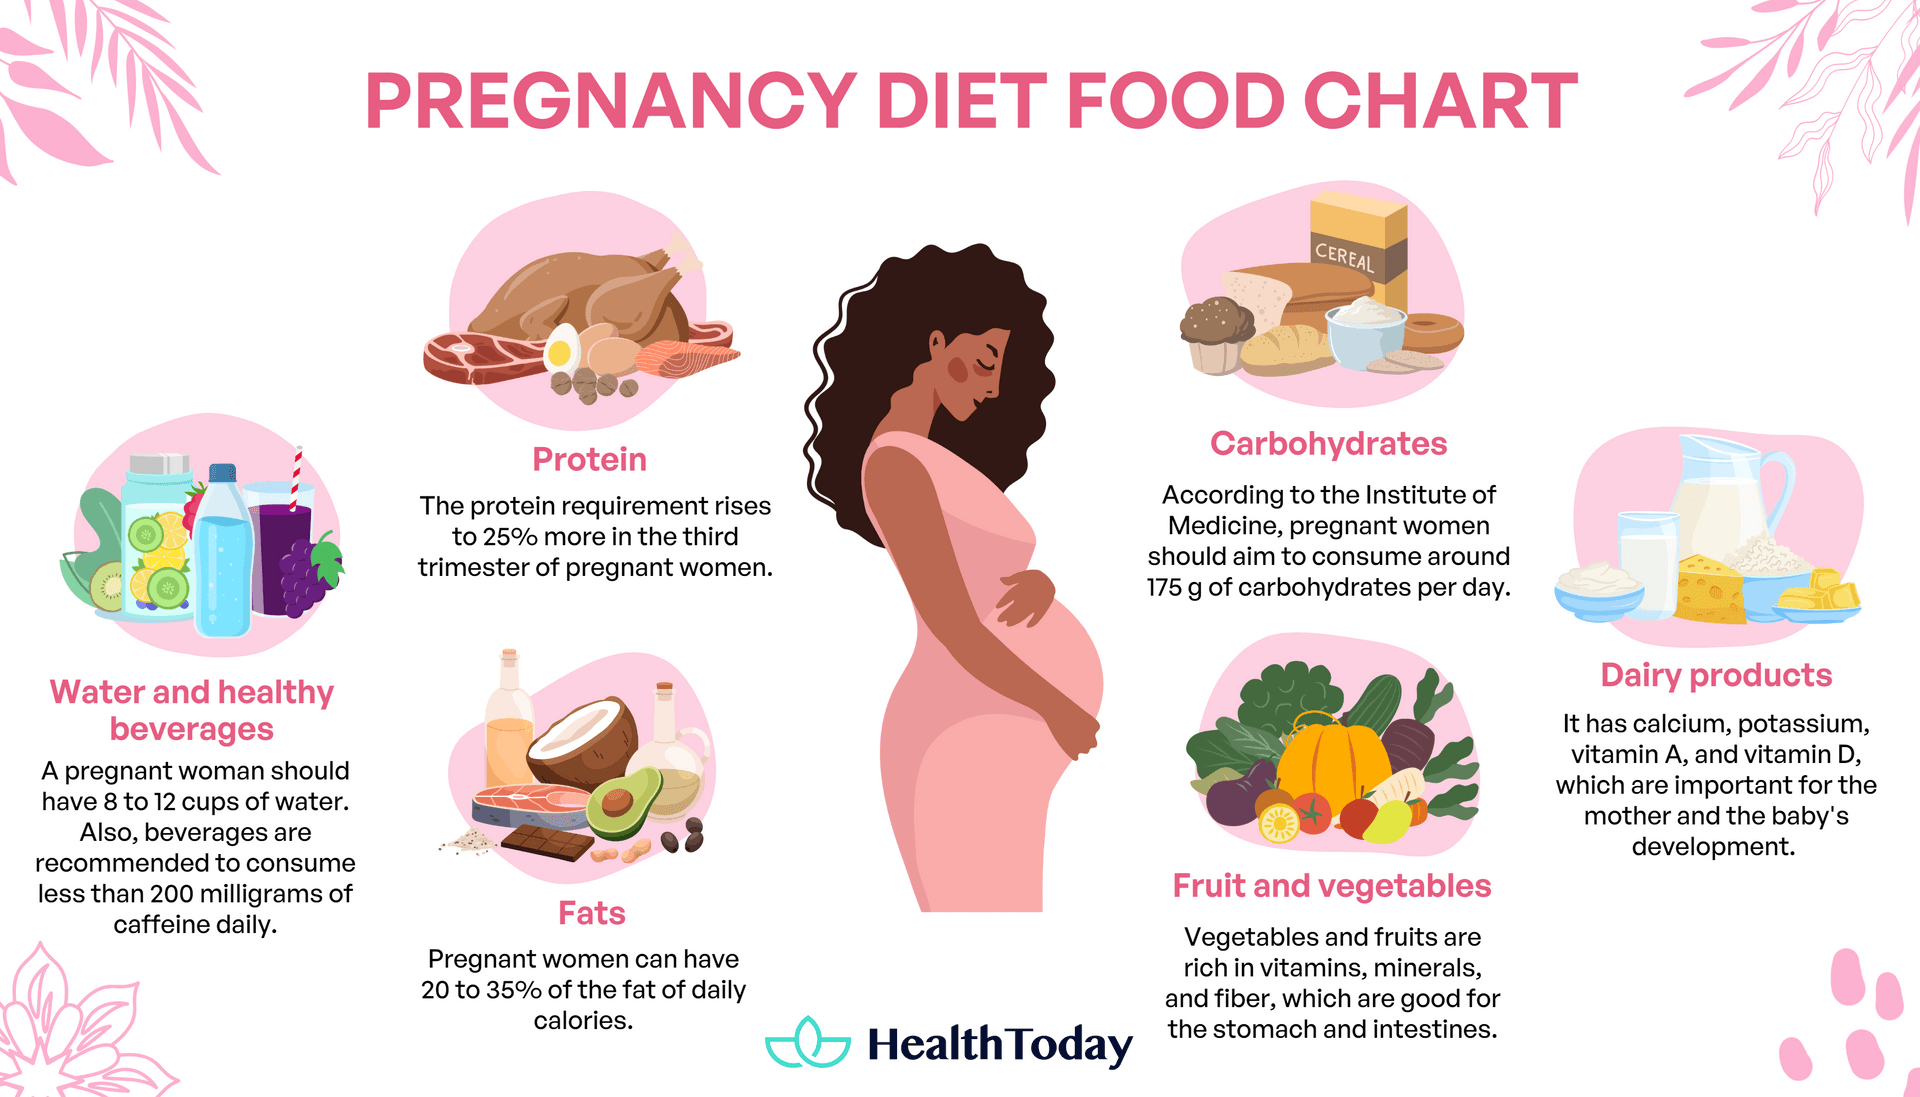
Most people focus on what to add. They rarely think about what to cut. Trans fats are the most consequential dietary item to eliminate entirely. Even small amounts, found in partially hydrogenated oils and many processed foods, increase ovulatory infertility risk by about 73 percent according to the same Nurses' Health Study data. Reading ingredient lists for "partially hydrogenated" is non-negotiable. It's also worth noting that vegetable oil blends labeled as "healthier" often still contain these fats depending on the processing method. Alcohol has a dose-response relationship with fertility outcomes. The data gets murky at low levels, but the clear signal is that heavy drinking significantly impairs both male and female fertility. For women, even moderate consumption during the periconception window can affect implantation rates. The practical takeaway is simple: zero alcohol from the moment you start trying until after a positive test, preferably longer. I've seen too many couples waste months wondering why implantation failed when the real issue was a weekend wine habit that continued past ovulation. Caffeine intake is another gray area that needs specificity. The American College of Obstetricians and Gynecologists recommends limiting caffeine to under 200 milligrams per day once you're trying to conceive. That's roughly one 12-ounce coffee. Two large lattes from a chain shop can easily exceed that. The concern isn't just about conceiving. High caffeine intake has been linked to increased miscarriage risk in several studies, particularly above 300 milligrams daily.
Get the Full Details

Seafood selection requires equal parts strategy and caution. Fish are excellent sources of omega-3s, which are critical for hormonal regulation and embryonic development. But mercury accumulation in certain species is a real problem. Shark, swordfish, king mackerel, and tilefish should be avoided completely. Salmon, sardines, and anchovies are safe and highly beneficial. The trick is balancing mercury exposure against omega-3 benefit, and that means varying your fish choices rather than eating the same type every day.
A Problem I Actually Ran Into
One edge case that comes up more often than you'd expect involves women with a MTHFR gene variant. Roughly 30 to 40 percent of the population carries at least one copy of this variant, and it affects how folate gets metabolized. Standard folic acid supplements don't convert efficiently in these individuals. I worked with a patient who was taking the recommended 800 micrograms of folic acid daily for four months before her first prenatal visit. Her red blood cell folate level was still in the low-normal range while her homocysteine was elevated. The workaround was switching to methylfolate, the active form, at 5 milligrams daily. Her levels normalized within eight weeks. If you're supplementing with regular folic acid and not seeing the bloodwork improvements you'd expect, asking your provider about MTHFR testing is reasonable. It's not a dramatic problem, but it's the kind of thing that wastes time and creates unnecessary anxiety when it goes unrecognized. Another practical issue is the gap between theory and execution. The Mediterranean-style diet is repeatedly cited as optimal for fertility, and the evidence backs it up. But asking someone to buy fresh fish, organic produce, olive oil, and specialty grains every week is unrealistic for a lot of people on tight schedules or limited budgets. The workaround I recommend is simpler than it sounds. Buy frozen salmon fillets instead of fresh. Use canned sardines and mackerel as cheaper omega-3 sources. Keep frozen berries for smoothies. Sort vegetables by what's cheapest at the store rather than what looks trendy. You don't need a perfectly curated pantry. You need consistent access to whole foods most of the week.
Male Fertility Gets Ignored Way Too Often
Diet affects sperm quality directly. Zinc, selenium, vitamin C, vitamin E, and CoQ10 all play roles in spermatogenesis and sperm motility. A diet low in antioxidants produces more oxidative stress, which damages sperm DNA fragmentation. This is measurable and it matters. Some clinics now include DNA fragmentation testing as part of a standard male fertility workup because conventional semen analysis misses a significant portion of male factor infertility. The dietary intervention is straightforward: increase intake of nuts, seeds, legumes, colorful vegetables, and lean proteins. Reduce processed meats and refined carbohydrates. The sperm cycle takes about 74 days, so any dietary changes need roughly two to three months to show up in lab results. Patience is required. Prenatal vitamins are the baseline, but the quality varies enormously between brands. Look for one that contains methylfolate instead of synthetic folic acid if possible, plus adequate iron, iodine, and vitamin D. Iodine deficiency is surprisingly common in women of childbearing age and is essential for fetal brain development. Most standard multivitamins don't include enough. Check the label. Myo-inositol is another supplement worth mentioning, particularly for women with PCOS. The evidence here is stronger than for most fertility supplements. Dosages around 2 to 4 grams daily have shown improvement in ovulation regularity and insulin sensitivity in clinical trials. It's not a cure for PCOS, but it's one of the few supplements with actual data behind it. The supplement market is full of products with little to no evidence. Avoid blends that contain proprietary mixes where the exact dosages aren't disclosed. If a company won't tell you how much of each ingredient is in their product, don't buy it. There's no excuse for that level of opacity in a supplement meant for preconception health.
Weight Matters, But Not in the Way You Think
Being underweight or overweight both affect fertility, but the relationship isn't linear or simple. BMI alone is a terrible predictor. Body composition, metabolic health, and where you carry fat matter more. Visceral fat around the organs is far more metabolically disruptive than subcutaneous fat. Two women with the same BMI can have dramatically different fertility profiles based on body composition and metabolic markers like fasting insulin and HbA1c. The practical approach is to focus on metabolic health indicators rather than the scale. Aim for regular meals, adequate protein, resistance training, and sleep. Those factors influence fertility independently of weight changes. Extreme exercise or restrictive eating patterns can stop ovulation entirely. I've seen this repeatedly in clients who treat diet prep like a bodybuilding cut. Low energy availability suppresses gonadotropin-releasing hormone, which shuts down the reproductive axis. If your period becomes irregular or stops during a diet, that's a hard signal to stop and reassess. Fertility preparation should not feel like punishment. If it does, you're doing something wrong.
What This Doesn't Fix
Diet alone won't overcome blocked fallopian tubes, severe endometriosis, advanced paternal factor infertility, or age-related egg quality decline. These are real constraints. A perfect preconception diet can improve your odds within your biological reality, but it doesn't erase structural or chromosomal issues. If you've been trying for twelve months without success if you're under 35 or six months if you're over 35, diet optimization is still worthwhile, but it's time to add a reproductive endocrinology consult to the equation. Don't let dietary guilt replace medical evaluation. Stress and sleep are equally important and equally overlooked. Cortisol elevation disrupts the hypothalamic-pituitary-ovarian axis. Chronic poor sleep reduces leptin sensitivity and increases cortisol, both of which interfere with regular ovulation. These aren't soft recommendations. They're physiologically grounded. A 2018 study in Fertility and Sterility found that women reporting poor sleep quality had significantly lower pregnancy rates per cycle compared to those with normal sleep patterns, independent of other lifestyle factors.
Bottom Line
The diet to prepare for pregnancy is about consistent fundamentals, not perfection. Eat whole foods most of the time. Prioritize omega-3s, folate, iron, and vitamin D. Eliminate trans fats and limit alcohol and caffeine. Track your actual bloodwork instead of guessing. Address male factors alongside your own. And recognize when diet has hit its ceiling and medical intervention is the next step. Nothing here is complicated. Complication comes from inconsistency, unrealistic expectations, and ignoring the parts of the process that feel inconvenient.


