
Where I actually start with patients who want to turn this around
The first thing people get wrong about reversing type 2 diabetes is they think it starts with what you eat. It doesn't. It starts with understanding why your insulin levels are stuck at baseline rather than cycling the way they should. The diet matters, obviously, but the mechanism matters more. If you skip the mechanism, you'll fall back into old habits within six months and wonder why nothing changed. Here's the practical version of how this actually works in real life. You need to drop your fasting insulin, not just your blood sugar. Those are two different numbers, and most doctors only check one of them. Fasting insulin tells you whether your pancreas is still working overtime or starting to give up. When fasting insulin drops below about 5 uIU/mL, you're usually out of the metabolic dysfunction zone. That's the target, not an A1C number alone.
What a Diet To Reverse Type 2 Diabetes Actually Looks Like
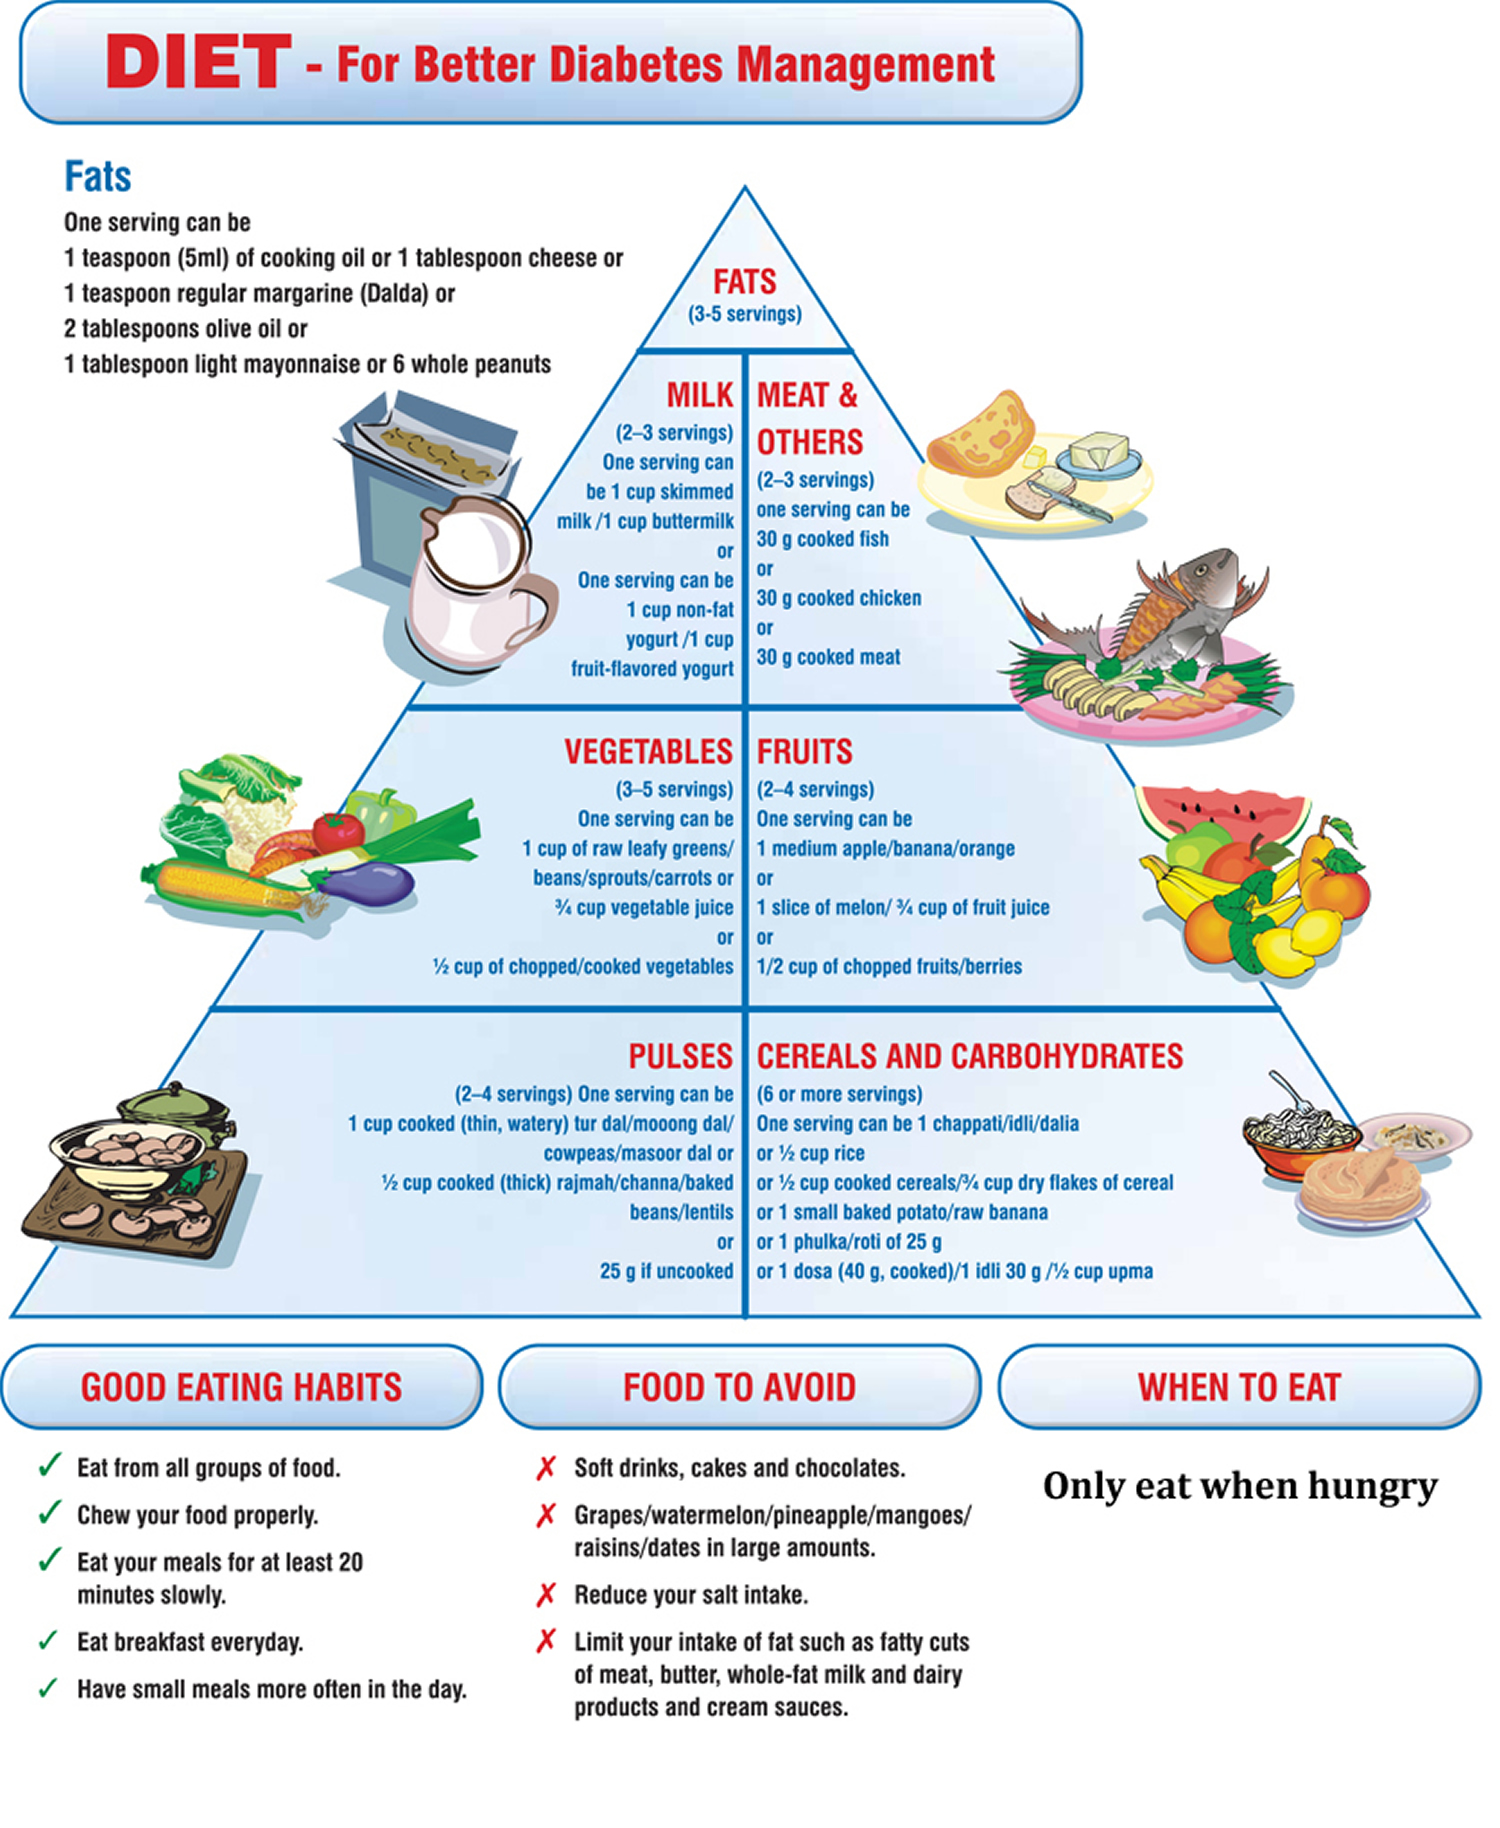
The eating pattern itself is straightforward once you strip away all the noise. You eliminate refined carbohydrates and added sugars completely. Not reduce. Eliminate. This includes white bread, pasta, rice, most fruits with high fructose content, and anything that comes in a bag with a nutrition label. You replace those calories with protein and fat from whole sources. Eggs, meat, fish, olive oil, butter, nuts. Vegetables that grow above ground get prioritized over starchy ones. The goal is to keep blood glucose stable throughout the day, which means your insulin has time to return to baseline between meals rather than being constantly stimulated. I don't recommend extreme carbohydrate restriction below 20 grams per day for most people because that introduces a lot of compliance problems and social friction. I start people around 50 to 80 grams of net carbs daily. That's enough restriction to drive meaningful metabolic improvement without making every restaurant visit a crisis. Most people see their fasting glucose drop into a normal range within two to four weeks on this pattern. A1C usually improves significantly within three months. The timing varies by how long someone has had diabetes and how much beta cell function remains. One thing nobody tells you about the early weeks: the dizziness and brain fog you might feel during the first seven to ten days isn't necessarily from low blood sugar. It's often your kidneys shedding excess water and sodium because insulin normally signals sodium retention, and when insulin drops, your kidneys flush both out. I had a patient who nearly drove himself to the ER after feeling lightheaded at work on day four of a very strict protocol. We resolved it by adding about a quarter teaspoon of salt to his morning water. That was the entire fix. He went from near-syncope to feeling normal within two hours.
The numbers that actually matter
Most people tracking this condition only look at fasting glucose and A1C. Those are useful but incomplete. You also want to track fasting insulin, triglycerides, HDL cholesterol, and ideally HOMA-IR if your doctor will run it. HOMA-IR is calculated from your fasting glucose and fasting insulin values and gives you a single number that reflects insulin resistance. A score below 1.0 is optimal. Below 2.0 is acceptable. Above 3.0 indicates significant insulin resistance. Tracking this number over time is more informative than A1C for measuring whether your actual metabolic state is improving, because A1C can stay stable even as insulin sensitivity improves slightly, while HOMA-IR drops clearly. Triglyceride-to-HDL ratio is another metric most people ignore. It's a strong predictor of cardiovascular risk in type 2 diabetes and responds quickly to dietary changes. A ratio above 3.0 is concerning. Below 2.0 is good. I've seen this ratio improve from 5.0 to 1.5 in about eight weeks on a disciplined eating pattern with no medication changes. That kind of improvement doesn't always show up meaningfully on a standard lipid panel review because most doctors focus on LDL only.
Get the Full Details
Edge cases and where this approach fails
This diet works for the vast majority of people with type 2 diabetes, but there are specific situations where it won't solve the problem on its own. If you've been diagnosed with type 1 diabetes or LADA (latent autoimmune diabetes in adults), calorie restriction and carbohydrate elimination won't restore insulin production because your beta cells have been destroyed by an autoimmune process. This is worth clarifying early because some functional medicine practitioners oversell reversal language to people with autoimmune diabetes, and that's irresponsible. Getting a C-peptide test and GAD antibody test can distinguish between type 2 and autoimmune forms. Another scenario where diet alone falls short is advanced pancreatic damage from long-standing uncontrolled diabetes spanning fifteen or twenty years. The beta cells may simply be exhausted beyond recovery. In these cases, dietary intervention still provides cardiovascular and metabolic benefits, but expecting full reversal is unrealistic. Medication adjustments remain necessary. I had a patient in his late fifties with an A1C of 11.2 who'd managed his diabetes poorly for about eighteen years. He adopted a very strict carbohydrate-restricted diet and lost 30 pounds. His A1C dropped to 6.1, which is remission by most definitions, but his C-peptide was still low-normal, meaning his pancreas was struggling. He maintained remission for three years before his medication needs gradually crept back up. Diet bought him time, but it didn't permanently fix the underlying capacity issue. There's also a practical limitation that gets glossed over in most articles. Social and economic reality. Eating this way requires cooking most of your meals at home, knowing how to read labels, and having consistent access to whole foods. People working multiple jobs, living in food deserts, or supporting large families on tight budgets find compliance much harder. I've recommended a Mediterranean-style pattern with moderate carbohydrate reduction as a fallback in these situations. It won't produce the same speed of improvement, but it's sustainable and still moves the needle meaningfully.
Medication interactions you need to watch
If you're currently taking insulin or sulfonylureas like glipizide or glyburide, dropping carbohydrates rapidly can cause dangerous hypoglycemia. This isn't theoretical. I've seen it happen repeatedly. Patients cut carbs, their blood sugar drops, they keep taking the same insulin dose, and they end up in the emergency room. The standard medical guidance is to reduce medication doses proactively as carbohydrate intake decreases, with frequent blood glucose monitoring. This should be done under physician supervision. Do not independently adjust your diabetes medications based on internet advice. Metformin is generally safe to continue since it works by reducing hepatic glucose output rather than stimulating insulin secretion. SGLT2 inhibitors carry a small risk of euglycemic ketoacidosis in some patients on very low-carbohydrate diets, so that combination warrants monitoring. Your prescribing doctor should be aware of your dietary changes so they can make informed adjustments.
What realistic progress looks like
Within two weeks, most people notice their cravings for carbohydrates diminish significantly. This isn't willpower. It's your gut microbiome and blood sugar regulation stabilizing. The hunger signals that used to drive you to the pantry every few hours quiet down. Energy becomes more consistent. Sleep often improves. Within four to eight weeks, lab values start reflecting the changes. Fasting glucose typically normalizes. Triglycerides drop. Blood pressure often improves without any medication changes, partly from weight loss and partly from reduced insulin-driven sodium retention. The period between months three and six is where most people either lock in the habit or lose momentum. The novelty has worn off, the initial weight loss has slowed, and daily adherence feels like work rather than a fresh experiment. This is the phase where most relapses happen. The people who maintain remission have typically built enough routine and social support that the diet feels like normal eating rather than a restriction. Cooking skills, meal prep systems, and family involvement during this window are strong predictors of long-term success.



