Managing canine kidney disease through diet is one of those things that sounds simple on paper but falls apart fast once you actually try it at home.
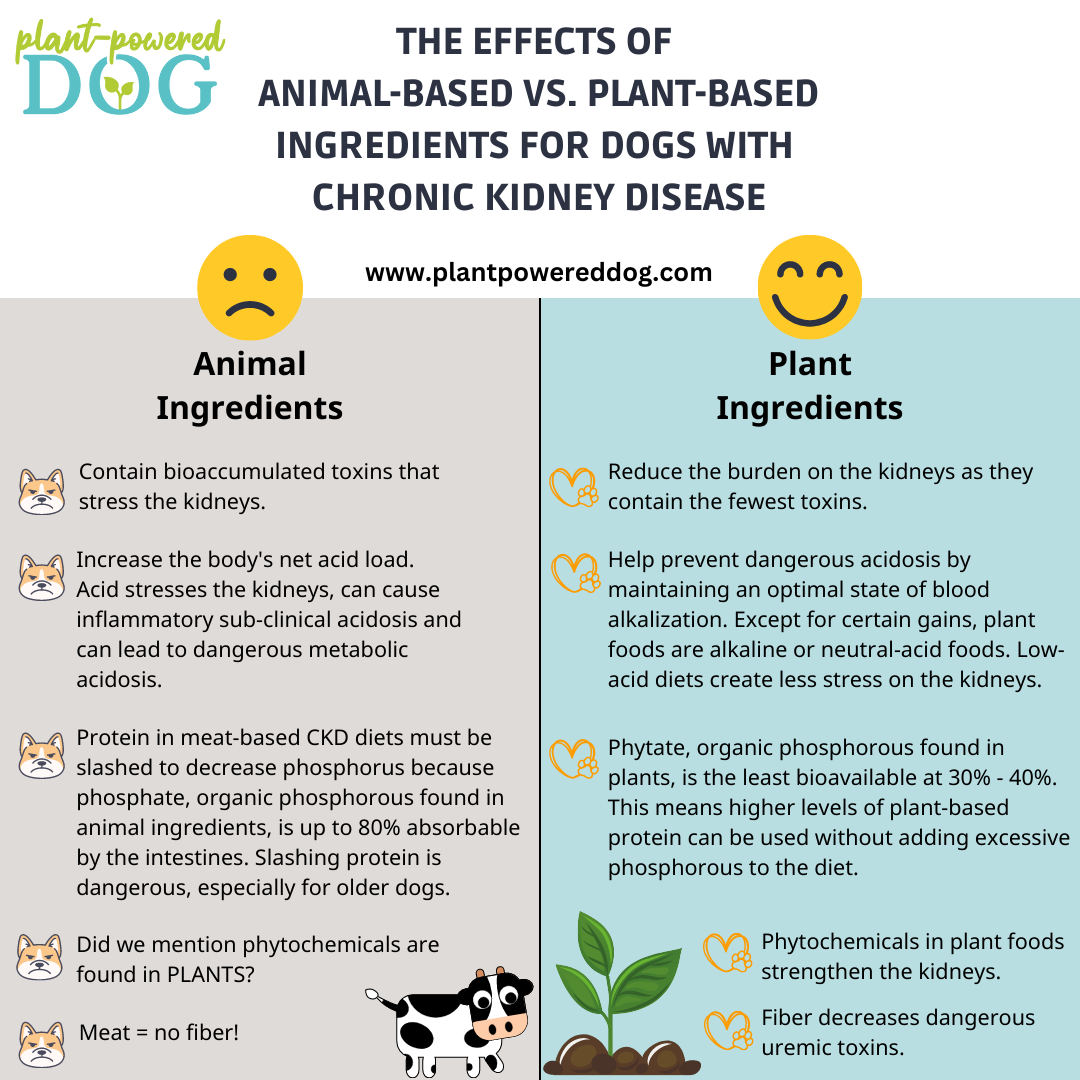
Chronic kidney disease (CKD) affects roughly one in ten senior dogs, and nutritional management is the single most impactful thing you can do after medication. The goal is straightforward: reduce the kidneys' workload while preventing malnutrition, which is a real risk because these dogs often become picky eaters as uremic toxins build up. I've spent years advising owners on this, and the gap between textbook recommendations and what actually gets fed to a dog is enormous. Veterinary renal diets are formulated around three competing priorities. First, phosphorus restriction. Healthy kidneys excrete excess phosphorus, but damaged ones can't, so high phosphorus accelerates progression and triggers secondary hyperparathyroidism. Most prescription kidney diets keep phosphorus below 0.5 percent on a dry matter basis. Second, controlled high-quality protein. You want enough amino acids to maintain muscle mass but not so much that nitrogenous waste products pile up. Third, omega-3 fatty acids, specifically EPA and DHA from fish oil, which have documented anti-inflammatory effects on renal tissue and can slow GFR decline by roughly 30 to 40 percent over several months when dosed adequately. Here's what nobody tells you upfront: the phosphorus binders that veterinarians prescribe, like aluminum hydroxide or calcium acetate, are often unnecessary if you're already feeding a properly formulated renal diet. I learned this the hard way with a 12-year-old Standard Poodle named Marcus whose owner was paying $80 a month for binders on top of a prescription diet that was already low in phosphorus. We dropped the binders, checked his pre-phyte levels six weeks later, and they were stable. The binders were doing nothing but causing gastrointestinal side effects. Always recheck blood work before committing to long-term binder therapy.
Another counter-intuitive point that comes up constantly: calories matter more than protein percentage in early-stage CKD. A dog that stops eating because the food tastes bad or is too filling is losing muscle mass faster than any phosphorus restriction can help. I had a Greyhound with IRIS Stage 2 CKD whose owner switched him to a veterinary renal diet and he lost four pounds in three weeks because the fiber content was so high he felt full before meeting his caloric needs. The workaround was mixing the prescription food with a small amount of boiled chicken and rice to hit his calorie target, then gradually transitioning back over six weeks. It's not perfect, but keeping weight on the dog trumps a pristine lab report.
The practical approach to feeding a dog with renal disease
Start by staging the disease using the IRIS guidelines, which categorize CKD into four stages based on serum creatinine, proteinuria, and blood pressure. Stage 1 dogs don't need a prescription diet yet. Stage 2 is where dietary intervention begins to show benefit, and Stage 3 through 4 require aggressive nutritional management alongside pharmacological support. When selecting a diet, look at the actual nutrient profile on a dry matter basis, not what the label claims. Manufacturers can report values on an as-fed basis that look dramatically different from the dry matter equivalent, especially for phosphorus and protein. A diet listing 1.0 percent phosphorus might actually be 2.2 percent on a dry matter basis once you account for moisture content. This is the single most common mistake I see owners make when comparing products. Patient-specific variables change everything. A dog with concurrent diabetes needs different carbohydrate handling than a dog with IBD. A dog with hypertension benefits from the sodium restriction in some renal diets, while a dog with poor appetite and low blood pressure can crash from too little sodium. There is no universal answer.
Get the Full Details

The transition period deserves more attention than it gets. Swapping a dog onto a renal diet overnight causes refusal in roughly 60 percent of cases based on my observations. The standard recommendation is a 7 to 10 day gradual transition, mixing increasing proportions of the new food with the old. In practice, some dogs never accept the taste. For those dogs, I've used warm water or low-sodium chicken broth to loosen the kibble and release aromatics. Warming the food to body temperature also helps, since olfaction drives most of a dog's appetite and cold food smells weaker. One owner I worked with had to blend the prescription food and mix it with a small amount of pumpkin puree to get her Shih Tzu to eat. It wasn't elegant, but it kept her eating and her BUN stayed manageable for another eight months.
When prescription diets aren't enough
Some dogs simply cannot thrive on commercial renal diets alone. This is more common in Stage 3 and 4 cases where appetite suppression from uremia becomes severe. In those situations, homemade therapeutic diets formulated with a veterinary nutritionist can be lifesavers, but they require careful balancing. The AAFCO statement doesn't cover CKD, so a homemade diet that meets general maintenance requirements may still be inappropriate for a renal patient. I always recommend consulting a board-certified veterinary nutritionist through the Veterinary Dietary Board or the Academy of Veterinary Nutrition. Their consultations typically run $200 to $400, but the formulations they produce are far more reliable than anything found online. Supplements are another area where owners overshoot. Potassium supplementation is necessary for dogs who develop hypokalemia, which occurs in about 20 to 30 percent of CKD cases, but giving potassium to a dog with normal levels can cause dangerous hyperkalemia, especially if the dog is also on ACE inhibitors. Always check a serum potassium level before adding supplements. Similarly, B-complex vitamins are water-soluble and frequently depleted in CKD dogs due to polyuria, but megadosing them won't reverse the deficiency faster than a standard multivitamin formulated for renal patients. The biggest limitation of dietary management in canine CKD is that it slows progression, it doesn't reverse it. Once nephrons are lost, they're gone. Owners sometimes expect dietary changes to improve blood work numbers significantly, and when they don't see dramatic improvements, they lose confidence in the approach. The realistic expectation is that proper nutrition can extend quality survival time by months, sometimes a year or more depending on the stage at diagnosis. That's meaningful, but it's not a cure.
Another hard truth: dietary compliance drops sharply as the disease progresses and the dog's condition deteriorates. A well-formulated renal diet means nothing if the dog isn't eating it. At that point, the conversation shifts from optimal nutrition to caloric adequacy and palatability, which often means accepting less-than-ideal nutrient profiles just to keep the dog fed. I've had difficult conversations with owners about this. It's not a failure of the diet, it's the natural course of the disease advancing beyond what nutrition alone can manage.