Understanding Two Different Approaches to Support
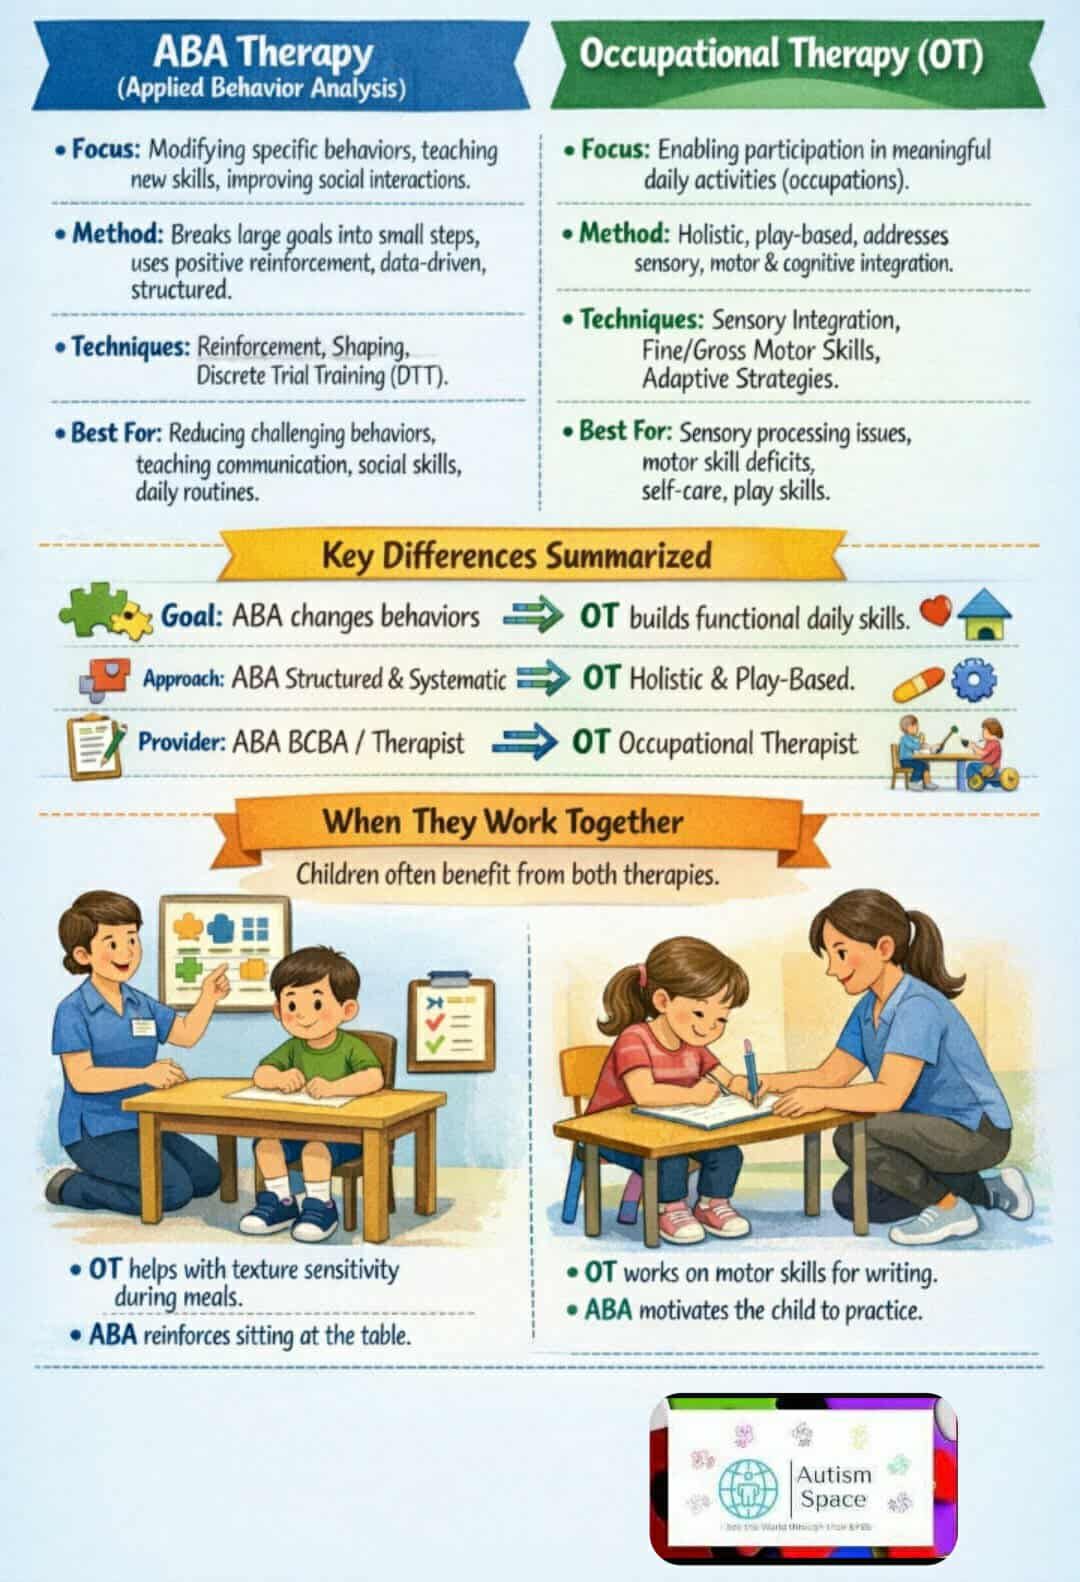
ABA and occupational therapy often come up in the same conversations, usually when someone is trying to figure out what kind of help a child or adult might need. People mix them up frequently because both can involve repetitive activities, structured sessions, and goals around daily functioning. They are fundamentally different disciplines with separate training requirements, theoretical foundations, and typical use cases. The core distinction comes down to what each field targets and how it approaches change. Applied behavior analysis is rooted in psychology and behaviorism. It breaks skills into small components and uses reinforcement strategies to teach or modify behavior. Occupational therapy is rooted in health and rehabilitation. It focuses on helping someone participate in meaningful daily activities by addressing physical, cognitive, and sensory challenges. I spent years coordinating care plans where families were confused about which route to pursue. One situation that stands out involved a nine-year-old who struggled with handwriting and classroom transitions. The family was told to pursue ABA because the child had an autism diagnosis. When we actually mapped out the problems, the handwriting issue was primarily a fine motor and sensory processing challenge, not a behavioral one. Occupational therapy addressed the motor planning and grip strength within six to eight weeks. The classroom transitions needed a behavioral component, which ABA could support. Treating them as interchangeable would have left half the picture untouched.
ABA focuses on behavior modification through structured reinforcement. Occupational therapy focuses on functional independence through sensory, motor, and cognitive support. The training path for each profession makes this difference clear. ABA practitioners typically hold a background in psychology or education and complete supervised hours before taking the Board Certified Behavior Analyst exam. Occupational therapists complete a master's degree in occupational therapy, pass a national board exam, and maintain clinical hours for licensure. The overlap in some techniques is real, but the educational foundation shapes what each professional notices first and how they intervene.
How Each Approach Actually Works in Practice
ABA sessions often look highly structured. You might see data sheets, discrete trial teaching, visual schedules, and consistent reinforcement systems. The therapist tracks frequencies, durations, or latencies of specific behaviors. Goals are usually stated as observable actions: a child will request a break using a card within three seconds, or a student will transition from preferred to non-preferred tasks with minimal prompting after four weeks of intervention. Occupational therapy sessions look different on paper and in person. An OT might set up a sensory diet, work on proprioceptive input through weighted tools, practice dressing skills, or modify the environment to reduce barriers. The focus is on participation. If someone cannot attend a meeting because the lighting causes sensory overload, the OT addresses the environmental factor rather than training tolerance through behavior procedures alone. One counter-intuitive point that beginners often miss is that ABA does not inherently address sensory needs, and occupational therapy does not inherently address behavioral function. I once watched an OT try to shape behavior using only environmental modifications for a nonverbal teen with severe self-injury. The injury was maintained by automatic reinforcement related to sensory input. Without a functional behavior assessment and contingency management, the occupational therapy strategies alone reduced frequency by maybe fifteen percent over three months. Adding targeted ABA dropped it to near zero within eight weeks. Both disciplines were necessary, but applying the wrong one first wasted time and allowed the behavior to persist.
Get the Full Details

Another pitfall is assuming that because both fields can work with autism, they are interchangeable. They are not. Autism is a neurodevelopmental condition, not a treatment. ABA and OT can both be appropriate depending on the individual's profile, but one does not replace the other in most comprehensive plans.
When To Choose One Over The Other
If the primary concern involves skill acquisition, problem behavior reduction, or teaching replacement responses, ABA is usually the first call. This includes situations like pica, aggression, severe elopement, or building academic and communication repertoires from scratch. The evidence base for ABA in these areas is extensive, and the data-driven nature of the work makes progress measurable in ways that help families and clinicians adjust quickly. If the primary concern involves daily living tasks, sensory regulation, motor coordination, or environmental access, occupational therapy is usually the stronger starting point. Dressing, feeding, handwriting, sensory defensiveness, ADHD-related executive function support, and post-injury rehabilitation all fall naturally within OT scope. Insurance coverage also tends to route these concerns toward OT rather than ABA. There is a practical bottleneck worth mentioning: ABA coverage is more widely mandated by insurance in the United States, but many plans still impose strict hour caps, require prior authorization, and limit provider networks. Occupational therapy coverage varies by plan type and state. Some plans cover OT under general health benefits with reasonable visit limits, while others restrict it heavily. Getting the right referral early matters because denials typically take two to four weeks to resolve, and during that window the intervention timeline slips.
What Happens When Both Are Needed
Many people benefit from both, but coordination is where things usually get messy. I have seen ABA therapists design reward systems that accidentally reinforced avoidance behaviors because they did not account for sensory triggers that the OT had identified. I have also seen OTs recommend sensory tools that interfered with ABA protocols because nobody communicated across disciplines. The fix is simple in theory and rare in practice: share assessment data, align on goals, and schedule brief coordination calls every few weeks. One edge-case workaround I rely on involves creating a shared goal matrix. Instead of each discipline writing its own isolated plan, I put the top three functional goals on a single page and note which discipline owns which component, which strategies overlap, and which might conflict. For example, if the goal is independent school attendance, the ABA plan might target reducing escape-maintained behavior during transitions, while the OT plan addresses sensory regulation and fine motor demands of classroom tasks. Writing that out publicly prevents the kind of cross-disciplinary interference I described earlier. Neither approach is complete without the other in complex cases. Neither approach works if the provider has not done a proper assessment first. And neither approach is appropriate when the concern is purely medical, such as seizures, medication management, or neurological deterioration. In those cases, a developmental pediatrician or neurologist should lead, with ABA and OT as supporting services if indicated.

The real answer to understanding the difference between ABA and occupational therapy comes down to matching the intervention to the function of the problem, not to the diagnosis on the chart. ABA changes behavior. Occupational therapy enables participation. Both are valid. Using the wrong one for the wrong reason is what creates the confusion in the first place.