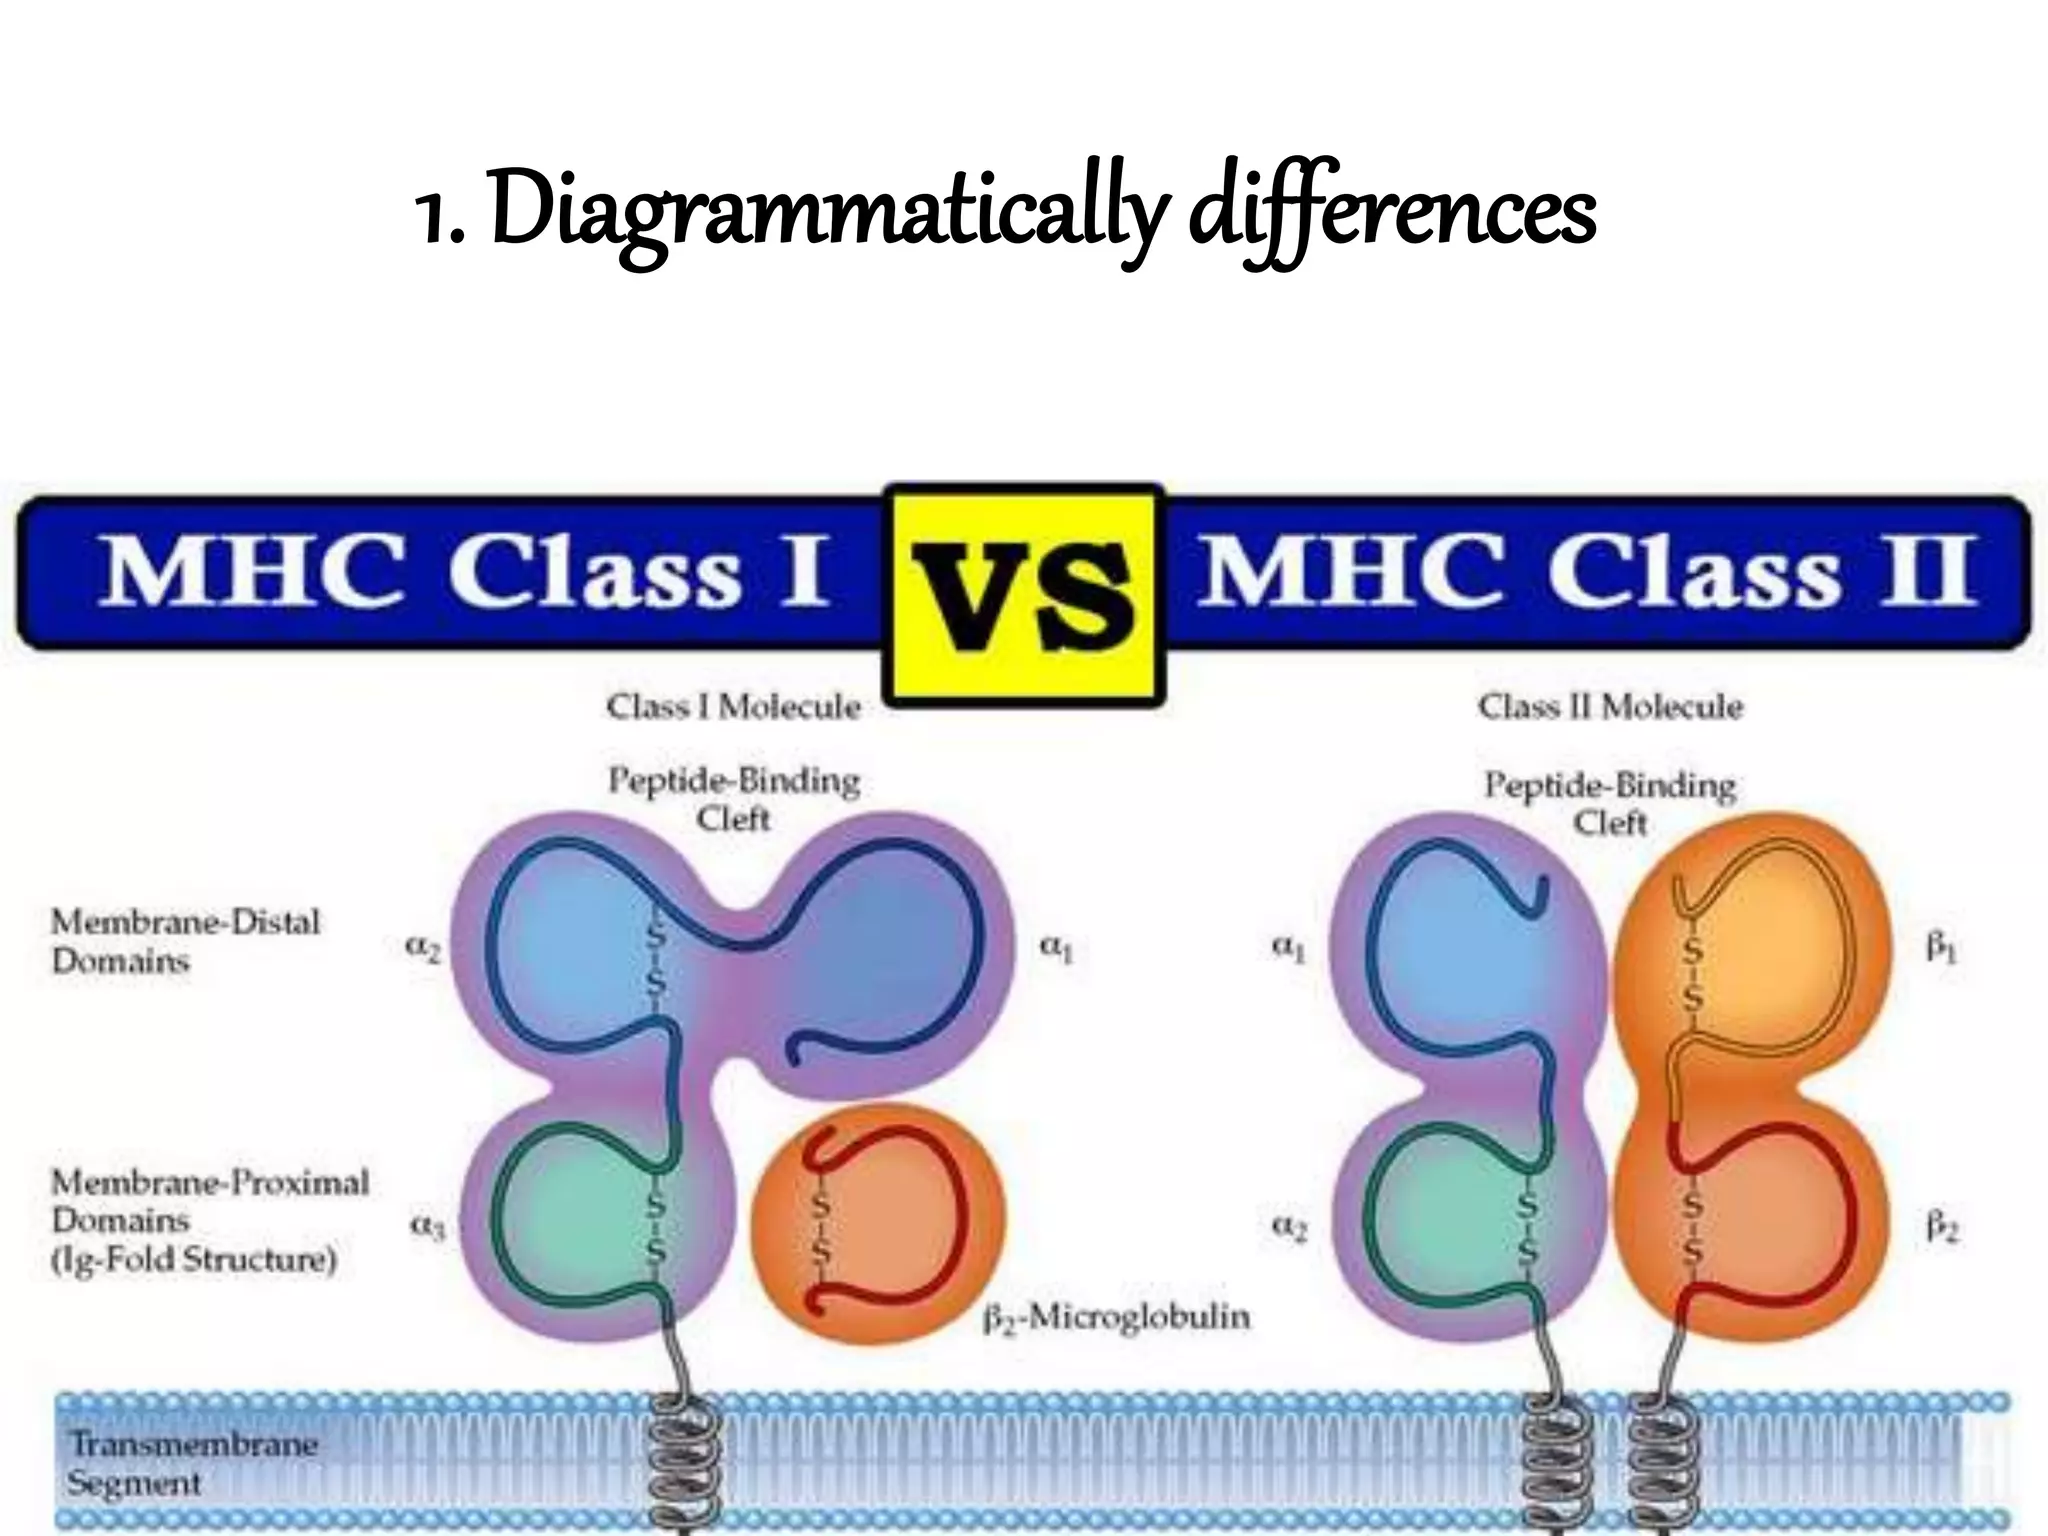
How MHC Class I and II Actually Work in Practice
MHC molecules are just cell surface proteins that present peptide fragments to T cells. Everyone learns the basic distinction in undergrad immunology — MHC I presents to CD8+ cytotoxic T cells, MHC II presents to CD4+ helper T cells — but the reality of working with them in a lab or clinic is messier than the textbook diagrams suggest. When I first started running flow cytometry panels for HLA typing, I kept messing up the gating strategy because I was treating MHC I and II as if they behaved identically across cell types. They don't. MHC I is expressed on virtually every nucleated cell in the body. MHC II is restricted mostly to professional antigen-presenting cells: dendritic cells, macrophages, B cells, and thymic epithelial cells. But here's the thing most people miss — you can induce MHC II expression on almost any cell type under inflammatory conditions. I learned that the hard way when I was troubleshooting a transplant rejection workup and kept seeing false-positive MHC II staining on endothelial cells that shouldn't have been expressing it at all. The patient had been on high-dose interferon-gamma therapy, which upregulates MHC II constitutively. If you're working with clinical samples from treated patients, always check the medication history before you assume abnormal expression patterns are pathological.
Understanding the Difference Between Mhc 1 And 2
The structural difference is where it all starts. MHC I has a single heavy chain paired with beta-2 microglobulin, forming a groove that holds short peptides — typically 8 to 10 amino acids. The ends of the groove are closed, which is why the peptides have to be short. MHC II has two similar chains, alpha and beta, and its peptide-binding groove is open at both ends. That lets it accommodate longer peptides, usually 13 to 25 amino acids, because the extra length just hangs off the sides. This structural detail matters enormously for how you process antigens. MHC I pulls peptides from the cytoplasm. Proteasomes chop up intracellular proteins — viral proteins, tumor antigens, self-proteins — into those short fragments. Then TAP transporters shuttle them into the endoplasmic reticulum, where MHC I molecules grab them with the help of chaperones like calnexin and tapasin. If tapasin is defective or downregulated, which happens in some viral immune evasion strategies, MHC I presentation drops significantly even though the MHC I protein itself is present. I've seen this in HPV-positive cancers where the virus deliberately suppresses tapasin expression, and the result is a tumor that looks normal on HLA-A and HLA-B staining but is essentially invisible to CD8+ T cells. MHC II takes the long route. Exogenous proteins get endocytosed, trafficked through endosomes and lysosomes where acidic proteases chop them up, and then MHC II molecules waiting in those compartments pick up the resulting fragments. The invariant chain, also called CD74, plays a critical role here. It blocks the peptide-binding groove in the ER so MHC II doesn't grab random ER peptides by mistake. CLIP — a fragment of the invariant chain — stays stuck in the groove until HLA-DM comes along and catalyzes its exchange for an actual antigenic peptide. Skip any step in that pathway and your MHC II presentation goes to zero, and you get a condition called bare lymphocyte syndrome type II, which is devastating because patients can't mount proper helper T cell responses.
There's a third category people often forget about — cross-presentation. Some dendritic cell subsets can take exogenous antigen and funnel it onto MHC I, essentially breaking the rule that MHC I only handles endogenous material. This is crucial for generating CD8+ T cell responses against tumors and viruses that don't directly infect dendritic cells. The mechanism involves routing antigens through the cytosol via Sec61 or from phagosomes into the ER, but the exact pathway depends on the dendritic cell subset and the antigen source. If you're designing a vaccine, understanding whether your antigen will be cross-presented or just presented on MHC II changes everything about your adjuvant and formulation choices. Functionally, the downstream consequences are stark. MHC I presentation triggers CD8+ T cells to become cytotoxic killers. They recognize the peptide-MHC I complex, release perforin and granzymes, and induce apoptosis in the target cell. This is your primary defense against intracellular pathogens — viruses, some bacteria like Listeria — and cancer. MHC II presentation triggers CD4+ T helper cells, which don't kill anything directly. Instead, they secrete cytokines, help B cells make antibodies, activate macrophages, and coordinate the broader immune response. One pathway is about eliminating infected cells. The other is about orchestrating everything else. The genetic complexity is another practical headache. MHC I has three classical genes — HLA-A, HLA-B, and HLA-C — each highly polymorphic. MHC II has several too: HLA-DP, HLA-DQ, and HLA-DR, each with alpha and beta chains that both contribute to peptide binding. This polymorphism is why HLA matching matters so much in transplantation, but it also means your epitope predictions from one HLA allele rarely transfer cleanly to another. I spent months debugging why a vaccine candidate that looked great against HLA-A*02:01 peptides fell apart when we tested it in donors with HLA-B*07:02. The same peptide sequence, completely different binding affinity, completely different immune outcome.
Get the Full Details

diagnostically, the main pitfall is assuming that presence of MHC I or II protein means functional presentation. You can have normal surface expression and still have a broken antigen processing pathway. I recommend validating with functional assays — like testing peptide-specific T cell responses or using tetramer staining — rather than relying solely on flow cytometry for surface marker presence. Surface expression alone misses deficiencies in TAP, proteasome subunits, or the invariant chain pathway that are functionally silent until you actually challenge the system.