Understanding Shock: A Practical Guide For Clinicians
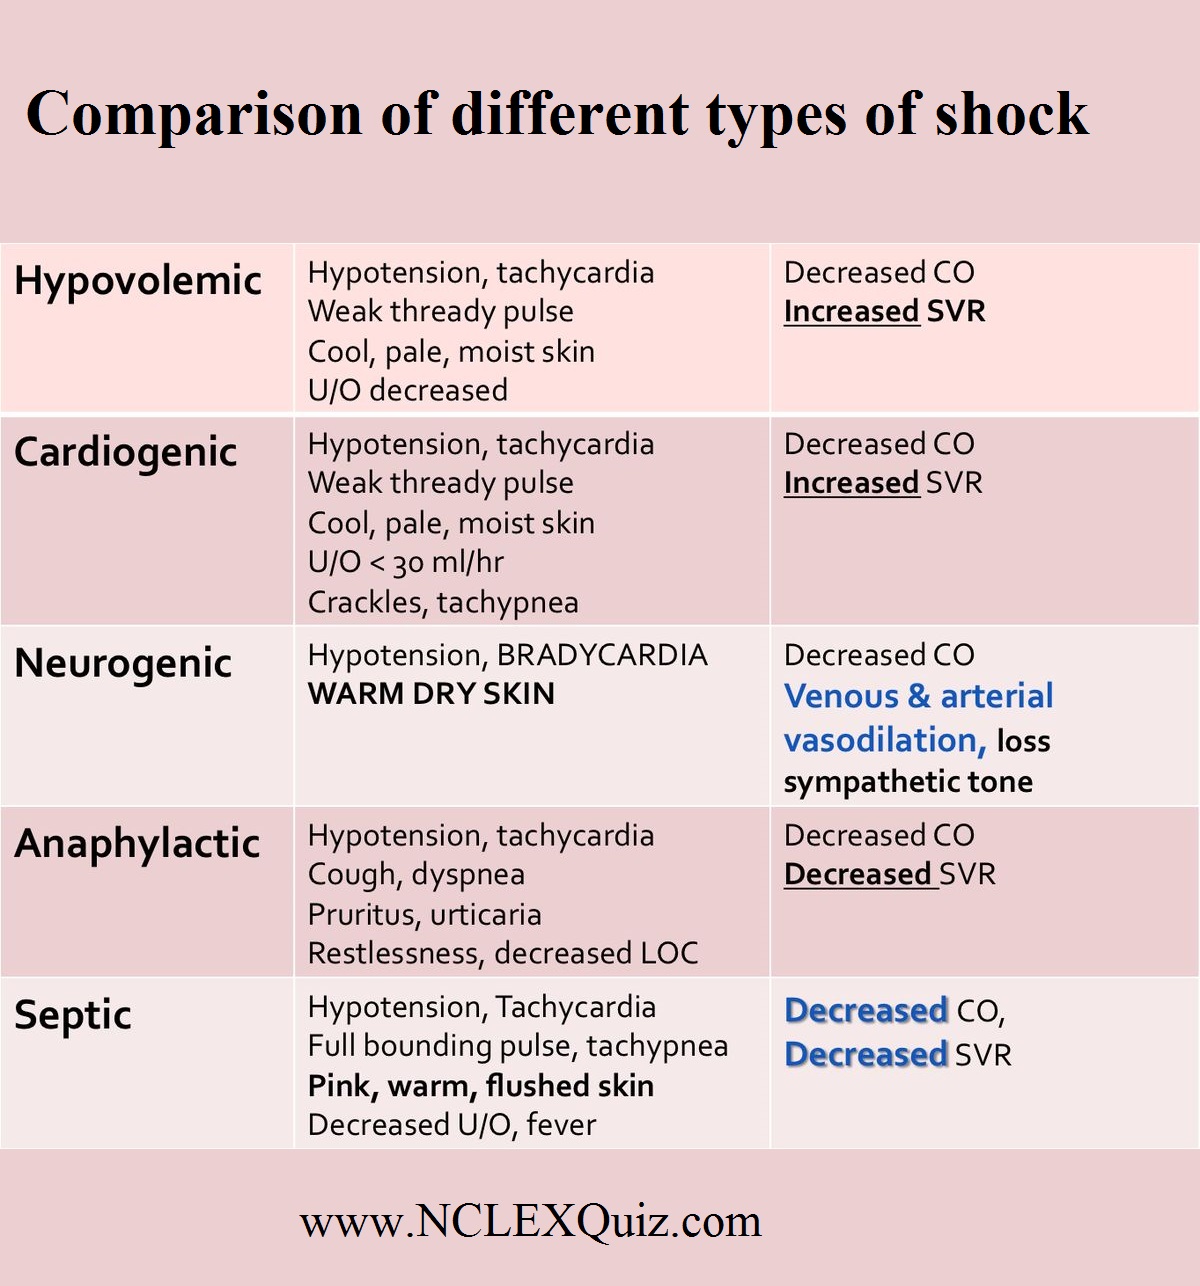
Shock is straightforward in theory and considerably more difficult in practice. It is not a diagnosis; it is a clinical syndrome characterized by inadequate tissue perfusion resulting in cellular hypoxia. The moment you stop thinking of it as a blood pressure number and start thinking about it as a perfusion problem, things get clearer. I organize shock into four mechanistic buckets. This framework actually works at 2 AM when you need to make a decision fast. Hypovolemic shock is the simplest one. The tank is empty. You lose blood, you lose fluid, you get shock. Hemorrhagic versus non-hemorrhagic matters for treatment but not for recognition. The classic signs are there: tachycardia, cool extremities, narrowed pulse pressure, delayed capillary refill. What most people miss is that compensatory tachycardia can be blunted. Beta-blockers, clonidine, athletic conditioning, advanced age, conduction abnormalities — all of these can mask the heart rate response and make hypovolemic shock look deceptively calm. I had a patient on metoprolol and carvedilol who was bleeding down from a GI source with a heart rate of 82. His blood pressure was 88 over 64 and his lactate was 5.2. He looked fine until he did not. If you are seeing unexplained hypotension with normal or near-normal heart rate in someone on rate-controlling medication, check your lactate and stop second-guessing yourself.
Cardiogenic shock means the pump is failing. Myocardial infarction is the most common cause in adult practice, roughly 80 percent of cases. But do not walk into this thinking it is always an anterior MI with ST elevations. I spent six months in a community hospital covering the floor and saw two patients with right ventricular infarctions who were hypertensive on arrival, then dropped their pressures the moment we gave them nitroglycerin. They were preload-dependent. The lesson: if you suspect cardiogenic shock and the patient has inferior ST changes, check a right-sided ECG before reaching for diuretics or nitrates. Fluid responsiveness testing matters here too, but interpretation is tricky because the failing ventricle responds differently than a normal one. I use a combination of passive leg raise with stroke volume monitoring via echocardiography or pulse contour analysis rather than relying on CVP, which is essentially useless in this population. Distributive shock encompasses septic, anaphylactic, neurogenic, and endocrine-mediated variants. Septic shock is the one you will see most and the one you will mess up most. The pathophysiology involves vasodilation from inflammatory mediators, capillary leak, and myocardial depression. You need fluid resuscitation, vasopressors, source control, and antibiotics. The order matters less than the speed. Every hour of delay in appropriate antibiotics after recognition of septic shock increases mortality by roughly 4 to 7 percent according to the big studies. I do not wait for cultures. I do not wait for the CT scan if the patient is unstable. I start broad-spectrum coverage and move aggressively. Neurogenic shock is distinct from spinal shock and people conflate them constantly. Neurogenic shock is the hemodynamic consequence of loss of sympathetic tone, usually from a spinal cord injury above T6. You get hypotension with relative bradycardia. The bradycardia is what separates it from hypovolemic shock, which presents with tachycardia. Treatment is fluids first, then vasopressors. Phenylephrine or norepinephrine works. Atropine helps with the bradycardia component. I learned this the hard way managing a patient with a C5 fracture who was tachycardic because we assumed the tachycardia was compensation for blood loss and poured fluids into him while missing the neurogenic component entirely. His oxygenation deteriorated from volume overload before we connected the dots. Check the spine in any hypotensive trauma patient before you assume hemorrhage.
Obstructive shock means something is physically blocking circulation. Pulmonary embolism, cardiac tamponade, tension pneumothorax, and severe aortic stenosis all fall here. The key insight is that obstructive shock looks like cardiogenic shock on surface examination — same hypotension, same cold extremities, same elevated filling pressures — but the treatment is radically different. Thrombolytics for PE, pericardiocentesis for tamponade, needle decompression for tension pneumothorax. You diagnose these with bedside ultrasound. If you do not have a portable echo in your resuscitation bay, you are flying blind. I run aocused cardiac and lung ultrasound on every undifferentiated shock patient. It takes three minutes and has changed my practice more than anything else I have encountered.
Get the Full Details
Putting It Together In Real Time
When a patient walks through the door in shock, your diagnostic algorithm should be rapid and sequential. Assess airway and breathing. Obtain two large-bore IVs. Draw lactate, CBC, basic metabolic panel, coagulation studies, type and cross, blood cultures before antibiotics if it does not delay treatment. Start warm crystalloid. If the patient does not respond, you need to classify the shock within minutes. The mixed bag is where things get interesting and where mistakes happen. Sepsis with underlying coronary disease can produce a combined distributive and cardiogenic picture. Trauma patients frequently have hemorrhagic shock layered on top of neurogenic shock from spinal injury. Endocrine emergencies like adrenal crisis mimic distributive shock but require glucocorticoids, not just fluids and pressors. I had a case with a patient presenting in refractory shock who was ultimately diagnosed with Addisonian crisis. The blood pressure would not budge despite norepinephrine at high doses. The clue was hyperpigmentation and a history of autoimmune thyroiditis. Hydrocortisone 100 mg IV resolved the shock within an hour. Without that medication, the catecholamines were essentially useless because the vascular smooth muscle requires cortisol for proper receptor expression and function. Monitoring adequacy of resuscitation is where experience really matters. Lactate clearance is useful but has limitations. A normal lactate does not exclude ongoing shock, particularly in hepatic dysfunction where lactate clearance is impaired. Base deficit, venous-arterial CO2 gradient, ScvO2, and clinical perfusion markers all add information. No single number tells you the whole story. I track lactate trends every two to four hours initially, watch the base gap, and continuously reassess clinical signs. Mental status, skin mottling, urine output — these remain relevant despite all the advanced monitoring available.
Specific Pitfalls That Wasted My Time
I will give you two specific situations that caught me off guard and cost time I could have saved. The first involved a patient with severe sepsis who was non-responsive to initial fluid bolus and required vasopressors. We added norepinephrine and the MAP improved, but urine output remained poor. I kept escalating pressors and adding fluids when I should have checked for abdominal compartment syndrome. The patient had undergone extensive resuscitation for intra-abdominal sepsis. The distended abdomen with firm tones and rising peak airway pressures gave it away. Decompression relieved the obstruction and renal perfusion recovered. I learned to measure bladder pressure routinely in refractory shock after that episode. It takes thirty seconds and prevents a catastrophic delay. The second pitfall involved what I thought was straightforward anaphylactic shock. The patient had a known penicillin allergy and developed hypotension and urticaria after exposure. I gave epinephrine, fluids, antihistamines, and steroids. The blood pressure stabilized transiently then crashed again. The issue was biphasic anaphylaxis, which occurs in roughly 1 to 20 percent of cases depending on the study. The initial episode responded, but the second wave hit four hours later when I had downgraded the level of care. I should have admitted the patient for observation regardless of initial response. Biphasic reactions do not follow a predictable timeline and can occur up to 72 hours later in rare cases. The standard recommendation is at least four to six hours of monitoring after resolution of the acute episode, longer if the presentation was severe or if epinephrine was required more than once.
When Standard Protocols Fail
Refractory shock deserves a frank discussion. About 20 to 30 percent of patients with septic shock do not respond to standard first-line vasopressor therapy. In those cases, I consider adding vasopressin at 0.03 units per minute as a norepinephrine-sparing adjunct. If that fails, methylene blue at 1 to 2 mg per kilogram IV over 30 minutes has been used successfully in catecholamine-resistant vasoplegic shock, though the evidence base is primarily retrospective and small trials. Hydroxocobalamin is another salvage option with a more favorable safety profile in some contexts. I mention these because you need to know what exists when first-line therapy stops working. The alternative to trying something is watching the patient die, and that is not an acceptable clinical choice. For cardiogenic shock, inhaled nitric oxide or epoprostenol can help right ventricular failure by reducing pulmonary vascular resistance without systemic hypotension. Iliopoplasic counterpulsation or VA-ECMO should be considered early in appropriate candidates rather than as a last resort. Timing matters enormously. ECMO initiation after prolonged low-flow states yields significantly worse outcomes. The mechanical circulatory support team needs to be involved at the decision point, not after the patient is near death.

Recording And Communicating Shock Status
Documentation is not paperwork. It is clinical reasoning made visible. When I write up a shock case, I include the mechanism classification, the initial resuscitation steps with volumes and agents, the hemodynamic parameters at each time point, the lactate trajectory, and the response to each intervention. This creates a clear chain of custody for the clinical decision-making and is essential for handoff, quality review, and legal protection. It also forces you to be precise about what you are doing and why. Vague notes like "patient in shock, treated" are unacceptable and provide zero clinical value. The Different Types Of Shock framework I have outlined covers the vast majority of clinical scenarios you will encounter. The exceptions are rare and usually involve unusual endocrine, toxicologic, or hematologic causes. When in doubt, return to the fundamentals: restore perfusion, identify the mechanism, treat the cause, and monitor relentlessly. The medicine does not change no matter how much technology advances around it.