What You Need to Know Before You Start Studying Tissue Classification
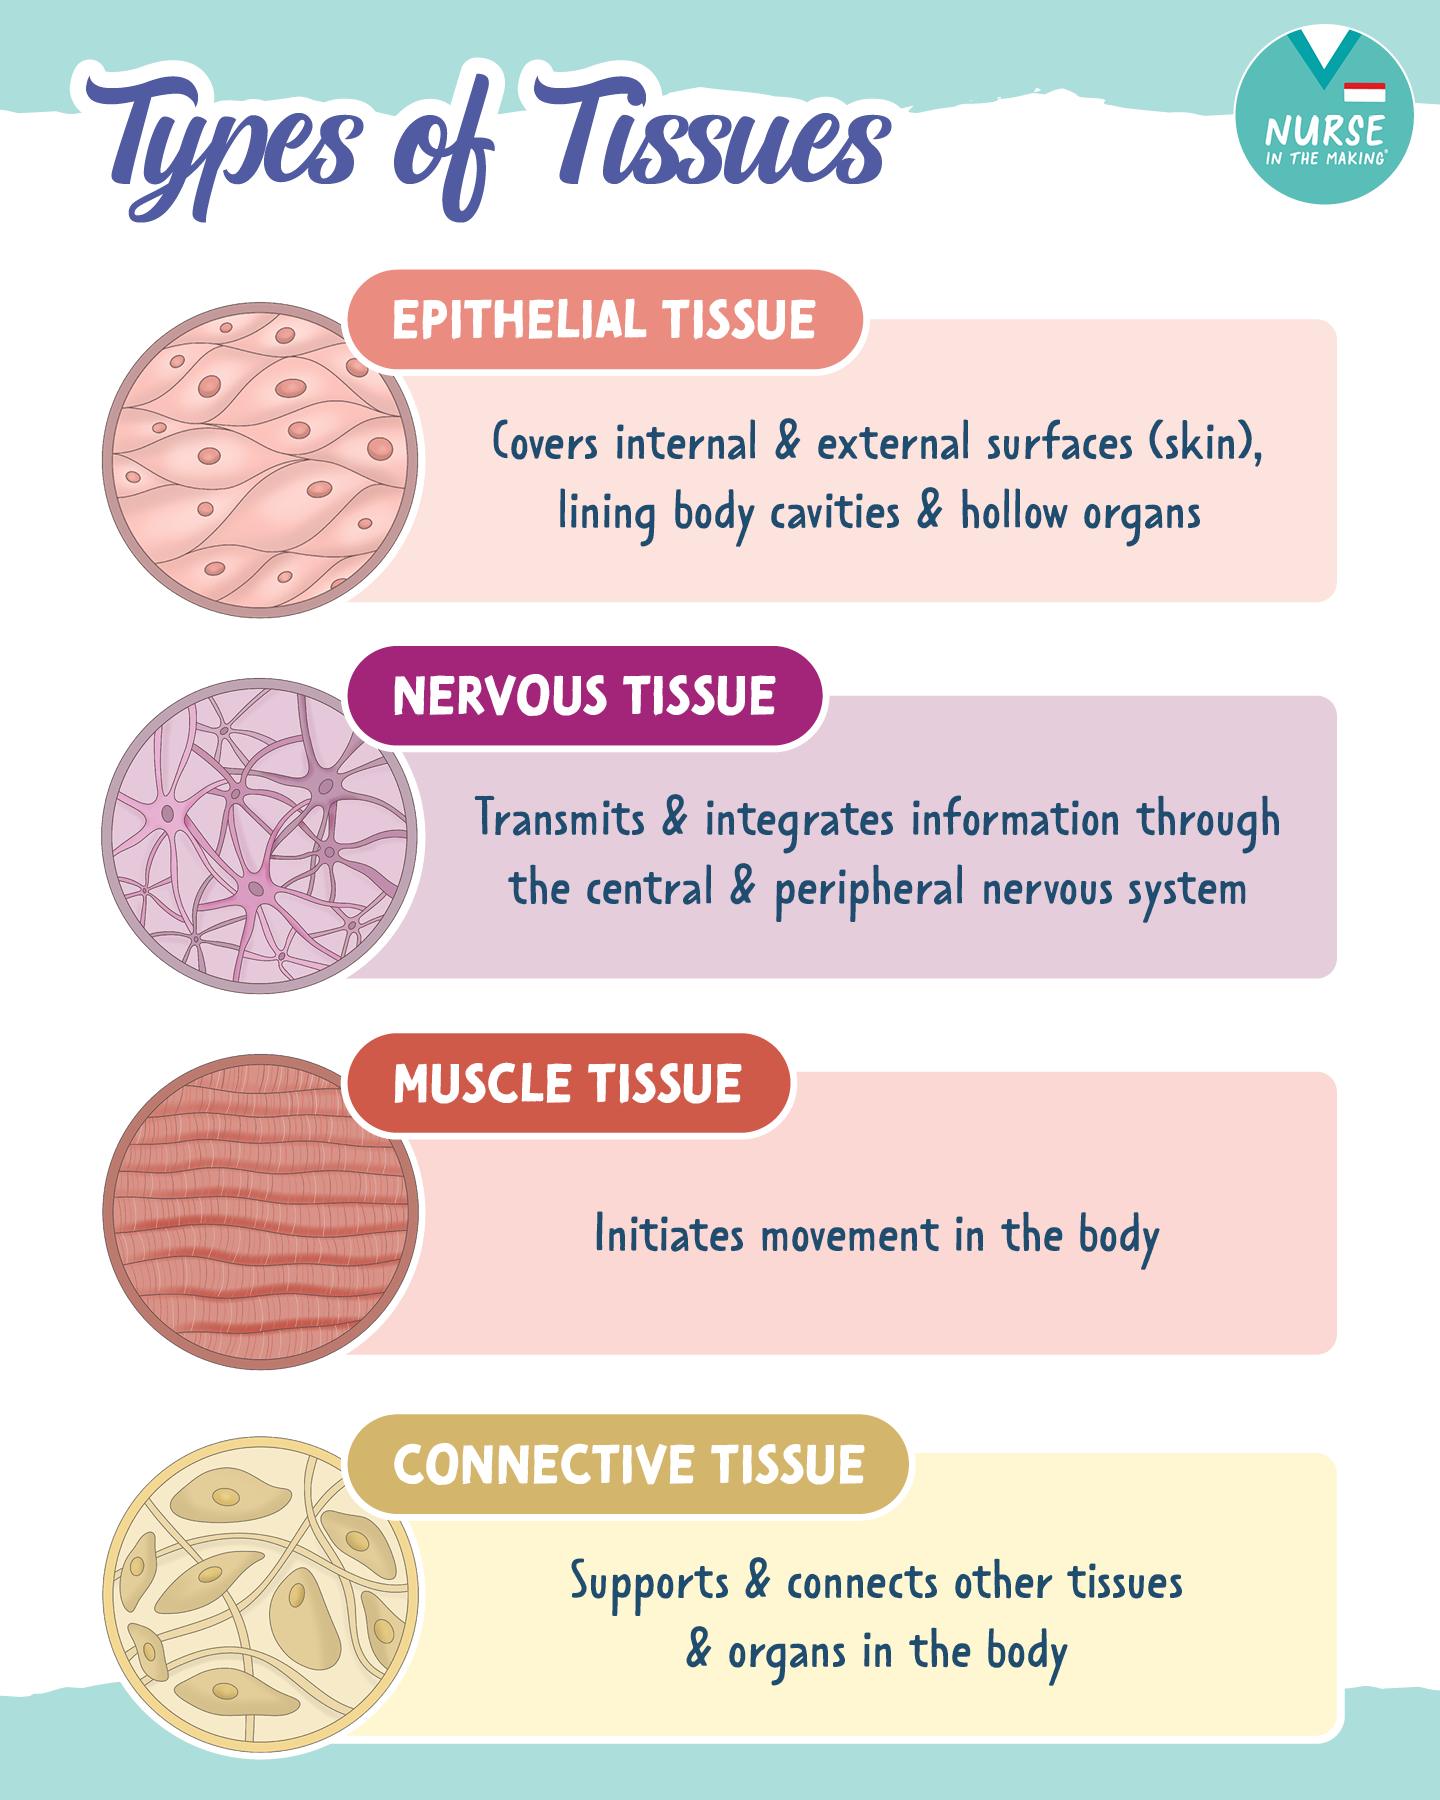
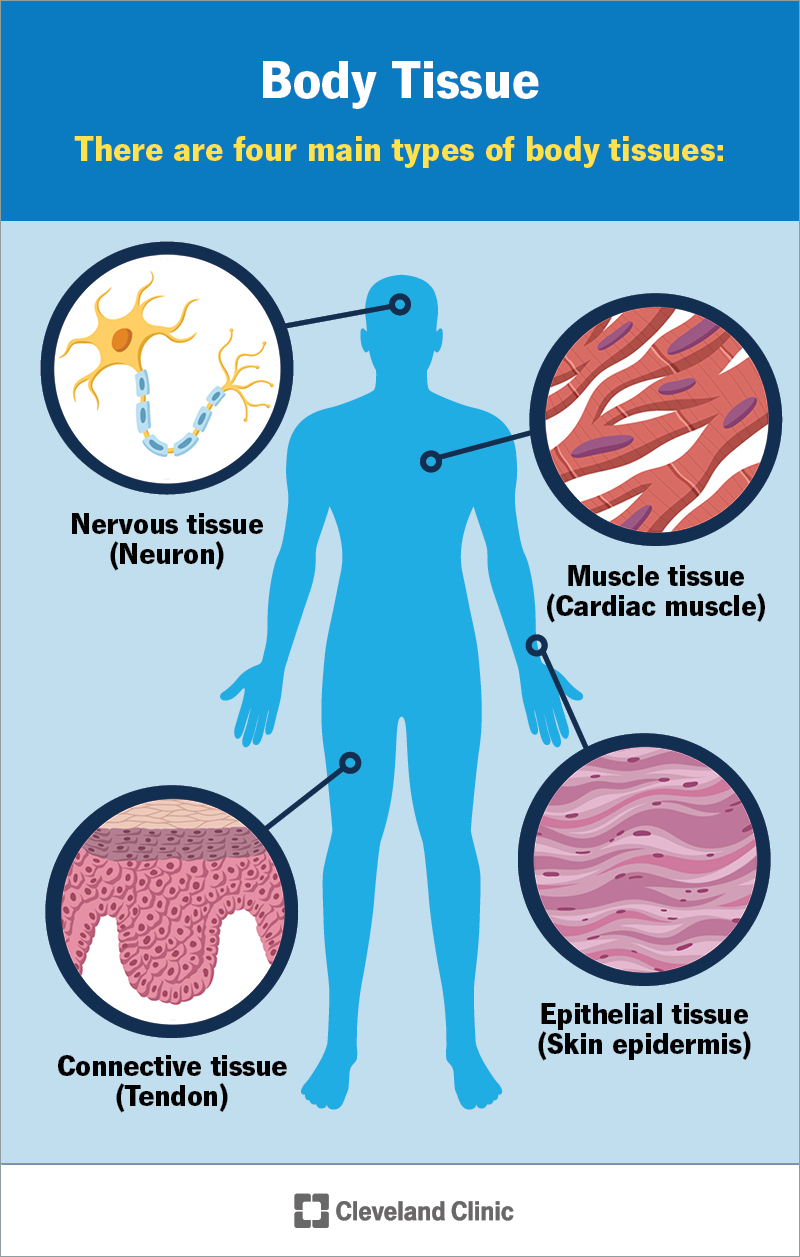
When I first started doing histology work in a lab setting, I treated tissue types like they were just categories to memorize. That approach fell apart pretty quickly once I started looking at actual slides under the microscope and realized the textbook diagrams don't match real biological samples. The Different Types Of Tissues framework is useful as a starting point, but it breaks down in practice because biology doesn't respect neat boxes. There are four classic tissue types: epithelial, connective, muscle, and nervous. That's the standard model. But here's the thing most intro courses skip—the boundaries between them are fuzzy, and some tissues exist in places that make classification feel like an exercise in willpower rather than observation.
Understanding Different Types Of Tissues in Practice
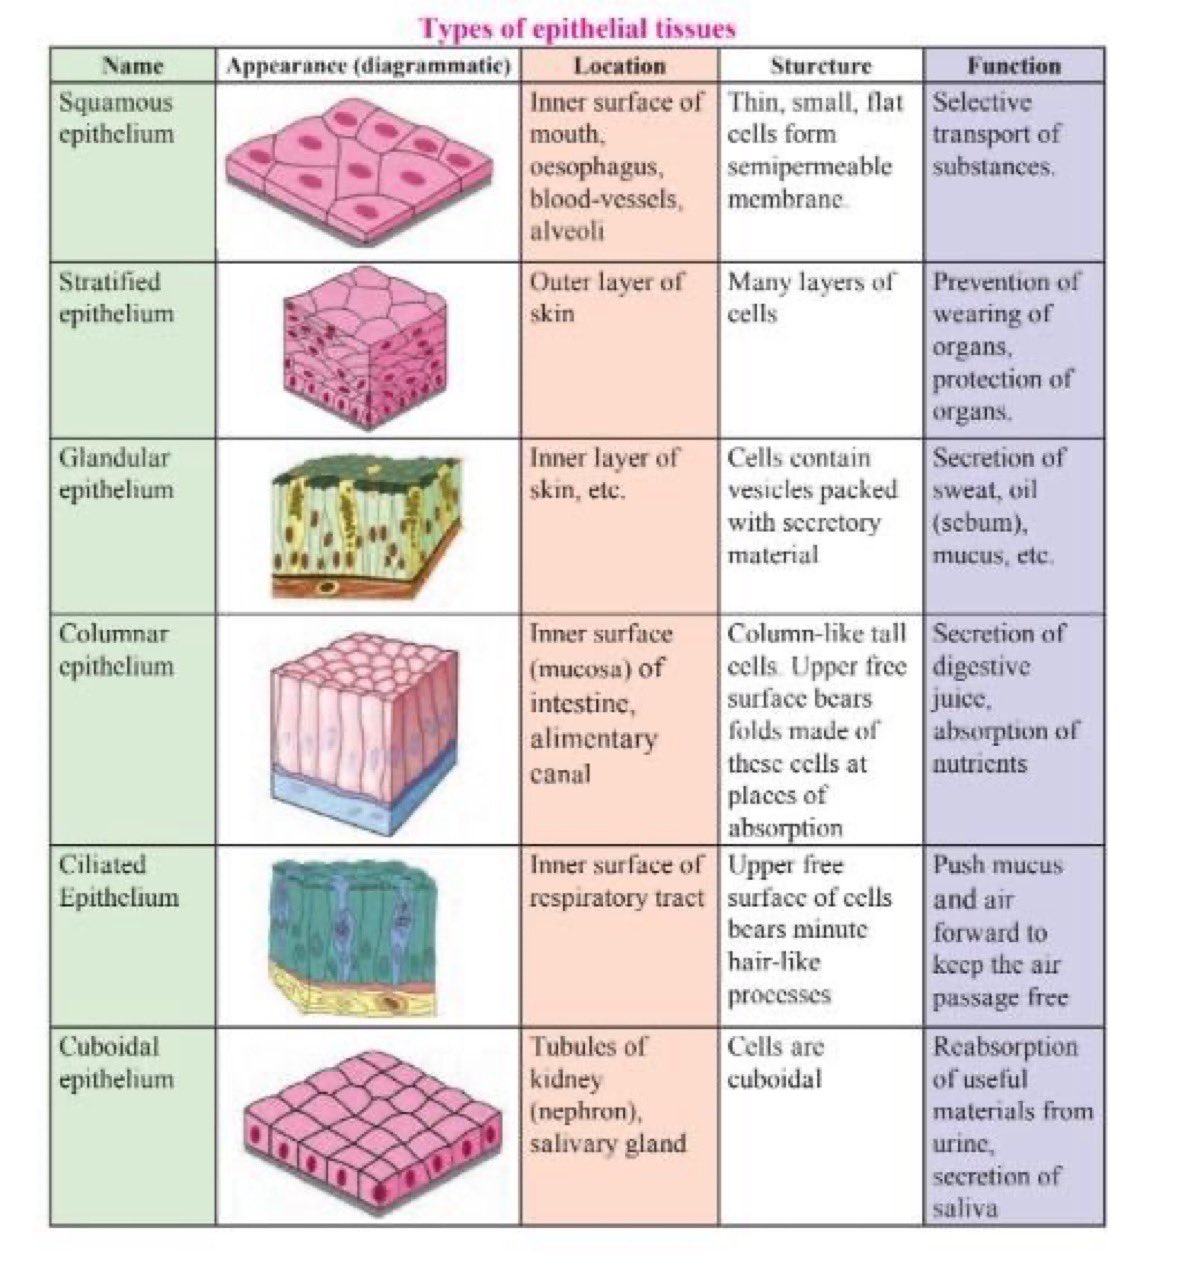
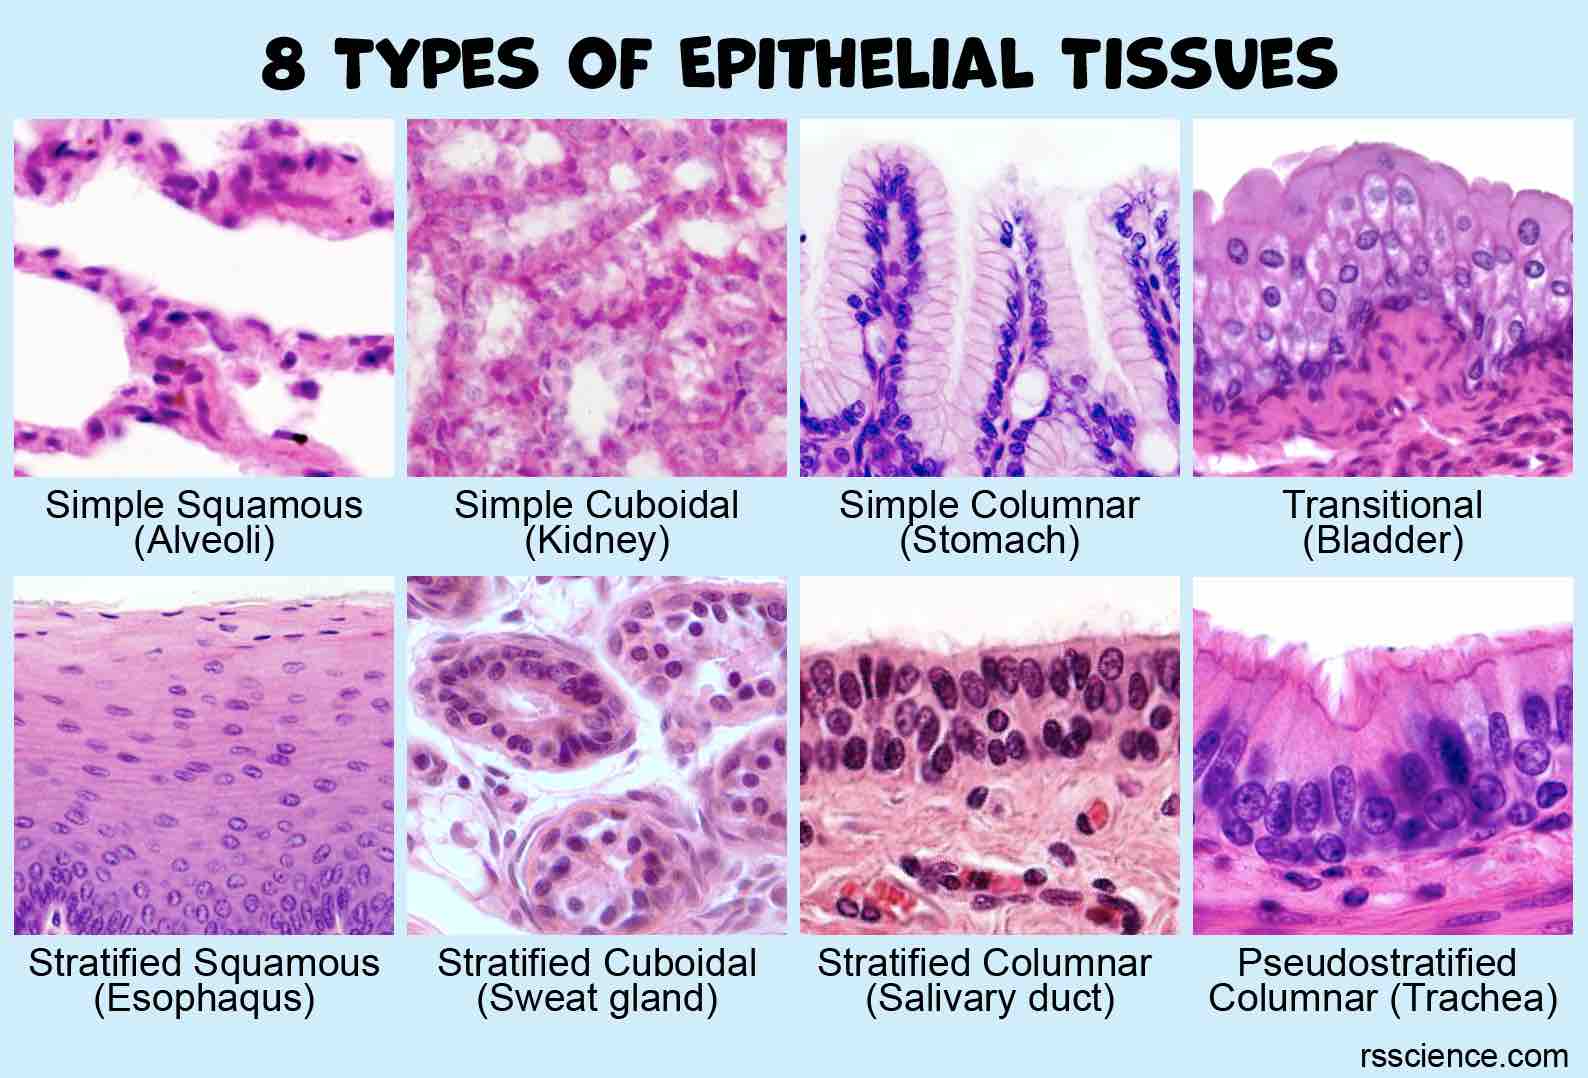
Epithelial tissue covers surfaces and lines cavities. You'll see it as stratified squamous in the skin, simple columnar in the gut, and transitional in the bladder. The trick is recognizing it on a slide when the staining isn't clean. I once spent forty-five minutes trying to classify a section that turned out to be an artifact from a fold in the tissue. The cells looked disorganized and I was about to write it off as pathological until my supervisor pointed out the microtome had just bunched it up. Connective tissue is the most diverse category and also the most annoying to work with. Loose areolar, dense regular, dense irregular, adipose, cartilage, bone, blood. Each subtype has its own staining characteristics and structural markers. Dense regular connective tissue in a tendon runs parallel and stains differently than dense irregular in the dermis where fibers run in multiple directions. If you're learning this for an exam, the fiber orientation is what separates the subtypes, not just cell type. Muscle tissue comes in three varieties: skeletal, cardiac, and smooth. Skeletal is striated and multinucleated with peripheral nuclei. Cardiac is striated but branched with intercalated discs and central nuclei. Smooth lacks striations entirely and has spindle-shaped cells with central nuclei. The intercalated discs are your diagnostic feature for cardiac muscle. Without them you're guessing. I found that remembering the nuclear position across all three types helped me distinguish them faster than trying to recall every structural detail on the spot.
Nervous tissue is made up of neurons and glial cells. Neurons have a cell body, dendrites, and an axon. Glial cells are the support structures—astrocytes, oligodendrocytes, microglia, ependymal cells in the CNS, and Schwann cells in the PNS. The problem with nervous tissue on slides is that neurons don't stain uniformly. Silver stains work better for visualization but they're fragile and expensive. Hematoxylin and eosin, which you'll use most of the time, makes neurons look relatively featureless compared to what they actually are.
Get the Full Details

Where the Standard Model Falls Apart
Here's a counter-intuitive point: smooth muscle and myofibroblasts blur the line between muscle and connective tissue. Myofibroblasts have contractile properties but they're classified as connective tissue-derived cells. When you see them in wound healing or certain tumors, they can look like smooth muscle on H&E stain, and immunohistochemistry is required to tell them apart. I ran into this during a pathology rotation where a biopsy was initially called a leiomyoma because the spindle cells had eosinophilic cytoplasm. The SMA and desmin stains confirmed it was actually a myofibroma. One extra day of turnaround, but it changed the clinical management entirely. Another thing beginners miss: basement membranes are not tissue types. They're extracellular matrix structures that sit between epithelial and connective tissue. They don't count as a fifth category. You'll see them highlighted with PAS or silver stains, and they're critical for identifying epithelial origins in metastatic tumors, but they're a boundary structure, not a tissue type itself. The blood classification question comes up often too. Blood is connective tissue because it originates from mesenchyme and has an extracellular matrix (plasma). But students push back on this because blood doesn't look like anything else in the connective family. It's a valid confusion. The embryological origin is what matters here, not the appearance.
A Practical Workflow for Identifying Tissues
Start with the low-power scan. Don't jump straight into high magnification. At 4x you can see the overall architecture and figure out whether you're looking at a surface, a gland, a vessel wall, or a solid organ. Then move to 10x to identify the general tissue type. Save 40x and oil immersion for cellular detail. Learn the staining patterns cold. H&E is your default, but knowing when to request special stains saves time. Reticular stains for lymphoid organs, trichrome for collagen differentiation, Masson's trichrome to separate collagen from muscle. These take an extra day usually but they prevent misclassification that would take weeks to reverse. Use immunohistochemistry when morphology isn't enough. Cytokeratins for epithelial origin, vimentin for mesenchymal, S100 for neural crest derivatives. I've found that combining at least two markers in ambiguous cases cuts diagnostic uncertainty from maybe thirty percent down to under five percent.
What This Approach Doesn't Handle Well
The four-type model doesn't account for stem cell niches or regenerative interfaces where multiple tissue types merge functionally. Bone marrow is one example—hematopoietic tissue, stromal connective tissue, and fat coexist in the same space with interdependent functions. Calling it one thing or the other misses the point of how it actually works. Another limitation: the model was built on adult human histology. It doesn't map cleanly onto developmental stages, invertebrate anatomy, or pathological states where tissue architecture is rewired. Cancer is the biggest offender here. A poorly differentiated carcinoma can lose all epithelial markers and resemble mesenchymal tissue, which is why the IHC panel becomes non-negotiable in oncology pathology. If you need something beyond the standard framework, switching to a systems-based approach—organ-centric rather than tissue-centric—gives you more usable knowledge. Studying the kidney as an organ with epithelial tubules, connective capsule, smooth muscle in vessels, and nervous innervation tells you more about how tissues interact than memorizing each type in isolation.