Understanding Diffusion in Biological Systems
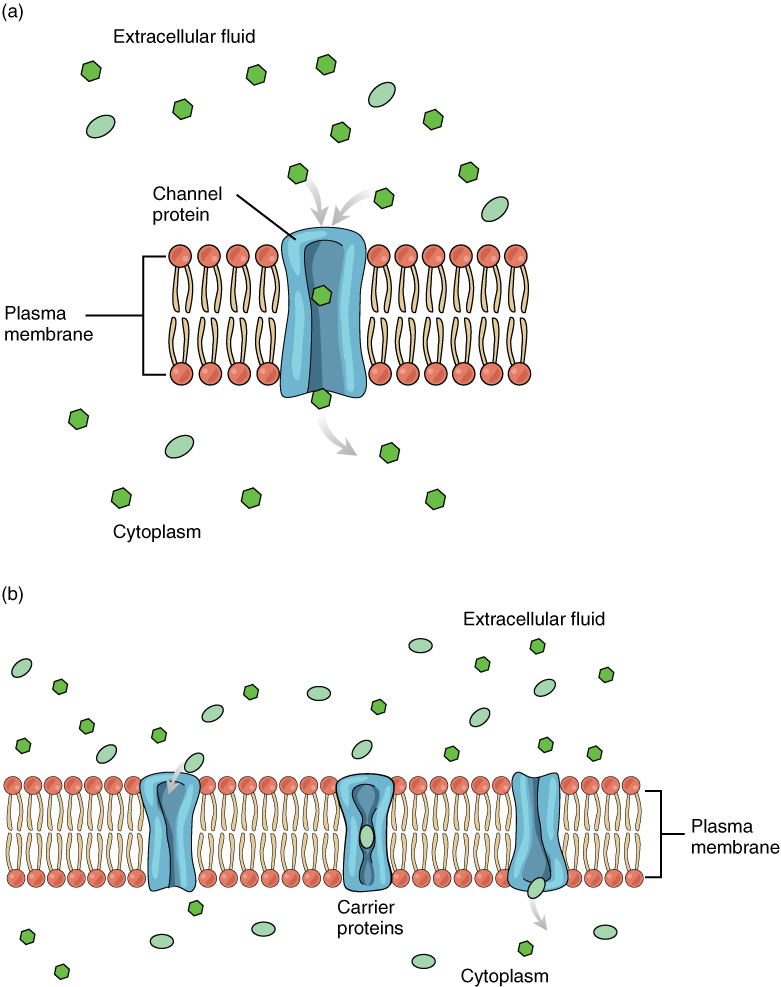
Difference is everywhere in living tissue, but most people only hear about it in the context of MRI machines. Before you can work with diffusion anatomy and physiology, you need to understand what's actually happening at the molecular level, because the imaging part is only as good as your grasp of the fundamentals. Water molecules are constantly bumping into each other and everything around them. In an open container they move freely in every direction. Inside the human body, that free motion gets restricted by cell membranes, organelles, fiber tracts, and extracellular matrices. That restriction is the entire signal. The anatomy side is about structure. Where are the barriers? What shapes do the compartments take? The physiology side is about function. How fast are molecules moving through those spaces, and what does that movement tell us about the state of the tissue? When you combine both, you get a picture that standard anatomical imaging simply cannot produce. Standard T1 and T2 weighted scans show you what things look like. Diffusion imaging shows you what things are doing at a microscopic scale. I spent years working with diffusion data in a lab that was transitioning from basic research into clinical pipelines. One of the first things I learned was that the terminology alone will trip you up if you're not careful. Anisotropic diffusion means directional preference. Isotropic diffusion means equal in all directions. White matter tracts are anisotropic. Cerebrospinal fluid in the ventricles is isotropic. Gray matter sits somewhere in between. Getting these straight matters when you're setting up your sequences or interpreting your maps.
How It Actually Works
Detection works by applying magnetic field gradients that make the phase of spinning protons dependent on their position. Apply a gradient, molecules move, their phase changes, and when you reverse the gradient the signal either refocuses or doesn't depending on whether the molecules stayed put or wandered away. The more they wandered, the more signal you lose. That signal loss is your measurement. The standard sequence is called spin-echo EPI with diffusion weighting. You apply two strong gradients on either side of a 180-degree refocusing pulse. The strength, duration, and spacing of those gradients determine your b-value. The b-value is what you control to make the measurement sensitive to different distances of diffusion. A b-value of 0 gives you a structural image with no diffusion weighting. A b-value of 1000 s/mm² is the clinical workhorse for brain imaging. Go higher and you're measuring slower diffusion or smaller compartments, but the signal drops dramatically and your scan time goes up. Direction matters too. If you only apply gradients in one direction, you'll miss everything happening perpendicular to it. You need multiple gradient orientations. Six is the absolute minimum, twelve is better, thirty-two is where most research protocols land, and sixty-four or more gives you solid coverage for anything beyond standard clinical work. The number of directions you sample directly affects the quality of your tensor fit and any downstream tractography.
I remember running into a specific problem with a dataset that looked completely fine on visual inspection. The b-values were correct, the directions were well distributed, the signal-to-noise ratio was decent. But when I computed the fractional anisotropy maps, the values in the brainstem were nonsensical. Some voxels showed negative FA. I spent about three days chasing ghosts before I realized the issue: there was a slight misalignment between the gradient table and the scanner coordinate system. The gradients had been exported from the sequence in the wrong convention. The fix was straightforward once I found it, but it required reorienting the entire gradient table and recomputing the tensors from scratch. It took about twenty minutes once I had the corrected table. The lesson was that hardware and software coordinate systems don't always match, and you should never trust the gradient directions without verifying them against a known phantom or at least checking for obvious pathologies in the raw data.
Get the Full Details
Tensors and What They Tell You
A diffusion tensor is a 3x3 symmetric matrix that describes diffusion in three dimensions. It has three eigenvalues and three eigenvectors. The eigenvalues represent the magnitude of diffusion along each principal axis. The eigenvectors point in those directions. From these you derive the standard scalar metrics. Fractional anisotropy ranges from zero to one. Zero means perfectly isotropic diffusion. One means diffusion is entirely restricted to a single direction. In healthy white matter, FA values typically range from 0.2 to 0.8 depending on the tract and the species. CSF sits near zero. Gray matter is usually between 0.1 and 0.3. Mean diffusivity is the average of the three eigenvalues. It tells you the overall rate of diffusion regardless of direction. In stroke, mean diffusivity drops within minutes because cytotoxic edema restricts water movement. That's why DWI is the gold standard for acute ischemic stroke detection. The lesion appears bright on high b-value images and dark on the apparent diffusion coefficient map.
Relative anisotropy and volume ratio are less commonly used but occasionally useful. Linear and planar component metrics help distinguish between different fiber geometries, which matters when you're trying to resolve crossing fibers in regions like the centrum semiovale.
Common Pitfalls and What People Miss
The biggest mistake beginners make is treating diffusion metrics as direct proxies for tissue integrity. They're not. A decrease in FA could mean loss of myelin, loss of axons, increased edema, crossing fibers, or even just a partial volume effect from a nearby CSF space. An increase in mean diffusivity is generally associated with tissue damage, but it can also reflect inflammation, gliosis, or other processes that increase extracellular space. The metrics are correlations, not causations. Another trap is ignoring eddy current distortions. The strong diffusion gradients induce currents in the scanner bore that warp the image. Modern scanners have hardware corrections, but they're not perfect. If you're processing data from older systems or doing research where pixel-level accuracy matters, you need to correct for eddy currents and head motion. FSL's eddy tool handles both in a single step, and it usually takes about ten to fifteen minutes per dataset on a modern workstation. Skipping this step will introduce systematic errors that look like biology but aren't. Motion is the third major issue. Even millimeter-scale movement during a scan can corrupt your data, especially at high b-values where the signal is already weak. You need to check your motion parameters before committing to any analysis. If subjects moved more than two voxels, you should probably exclude them or at least flag the data heavily. I once included a dataset that had a participant who slept through most of the scan but drifted about four millimeters during the last ten minutes. The resulting tractography looked plausible until I compared it to the contralateral hemisphere, where everything was obviously shifted. That cost me a week of reprocessing.

There's also the issue of crossing fibers. A single tensor can only model one dominant diffusion direction per voxel. In regions where fibers cross, bend, or fan out, the tensor model breaks down. You'll see artificially reduced FA and misleading eigenvector orientations. For those cases, you need higher-order models like Q-ball imaging, constrained spherical deconvolution, or diffusion spectrum imaging. These take longer to acquire and process, but they're necessary if you care about accurate tractography in complex regions.
Practical Workflow
Here's how I approach a typical diffusion project from start to finish. First, I convert the raw scanner data to NIfTI format using dcm2niix. This usually takes a few seconds. I immediately check the gradient table for consistency and verify that all volumes are present. Missing volumes are a common export error. Next, I run a quick visual inspection of the b=0 images and the highest b-value images. I'm looking for gross artifacts, signal dropout in the orbitofrontal cortex and temporal poles, and any signs of patient movement. If something looks wrong at this stage, I don't proceed further.
Then comes pre-processing. I correct for eddy currents and motion using FSL's eddy command. I remove brain tissue using bet, though for diffusion data I usually add the -m flag to generate a brain mask and apply it separately. I correct for Gibbs ringing if the data has high spatial resolution. I align the diffusion-weighted volumes to the b=0 reference using affine registration. This whole pipeline takes somewhere between ten and thirty minutes depending on the dataset size and my machine. After pre-processing, I fit the tensor model using fslmaths or DTIprep. I generate the scalar maps: FA, MD, AD, RD. I visually inspect each map for artifacts. I also check the residual maps to see if the tensor model is a good fit for each voxel. For region-of-interest analysis, I draw masks on the FA map or use an atlas like JHU-ICBM. I extract mean values and compare across groups. For tractography, I use deterministic or probabilistic approaches depending on the question. Deterministic tracking is faster and simpler but prone to terminating at regions of low FA or crossing fibers. Probabilistic tracking is slower but more robust in complex regions.

For statistics, I usually employ FSL's FEAT or TBSS for group-level analysis. TBSS is particularly useful because it aligns all subjects' FA maps to a common space and projects them onto a mean FA skeleton, reducing the misalignment problem that plagues voxel-based analyses.
When It Falls Apart
Different diffusion MRI has real limitations. It requires relatively long scan times, usually eight to twenty minutes for a complete protocol. Motion ruins everything. It's not suitable for uncooperative patients, pediatric populations without sedation, or any setting where scan time is constrained. The spatial resolution is limited, typically two to three millimeters isotropic in clinical practice, which means partial volume effects are a constant concern. The tensor model is an approximation. Real tissue diffusion is not Gaussian, especially at high b-values and in restricted environments. The biexponential model attempts to separate fast and slow diffusion components, but it introduces more parameters and more uncertainty. Multi-shell acquisitions help, but they require more scan time and more complex analysis. Tractography is the most controversial application. It can reconstruct white matter pathways, but the results depend heavily on algorithm choices, seed placement, and stopping criteria. Two researchers analyzing the same data with different parameters can produce different tracts. I've seen published tractography studies where the reported pathways didn't match known anatomy at all. The technique is useful for hypothesis generation and surgical planning, but it should never be treated as ground truth.
If you need to study microstructure without the ambiguities of tractography, consider combining diffusion MRI with other modalities. Myeloar stain with histology, quantitative susceptibility mapping with MRI, or MR spectroscopy can all provide complementary information. The multimodal approach is more work, but it produces more reliable conclusions.
What Actually Matters in Practice
Quality control is the single most important step, and it's the one people skip. I've reviewed enough papers to know that many published diffusion studies have undetected artifacts, uncorrected motion, or misaligned gradient tables. Before you publish or draw any conclusions, spend time looking at your raw data, your pre-processed data, your scalar maps, and your tractography results. Check every step. Document your parameters. Report your motion statistics. If you're doing group comparisons, show your alignment quality. Start simple. Don't jump into high-angular-resolution diffusion imaging or constrained spherical deconvolution until you understand the tensor model cold. Run a phantom scan if your institution has one. Simulate some data. Understand what the numbers mean before you apply them to real subjects. Keep your gradient table and sequence parameters documented. Scanner upgrades, software updates, and even different acquisition protocols can change the gradient directions and b-values subtly. If you're re-analyzing old data months later, you won't remember what you did. Write it down.
And finally, remember that diffusion MRI measures water movement, not biology directly. The biological interpretation requires care, controls, and often complementary methods. The technique is powerful, but it's easy to overstate what it can tell you.

