Putting labels on anatomy diagrams without losing your mind
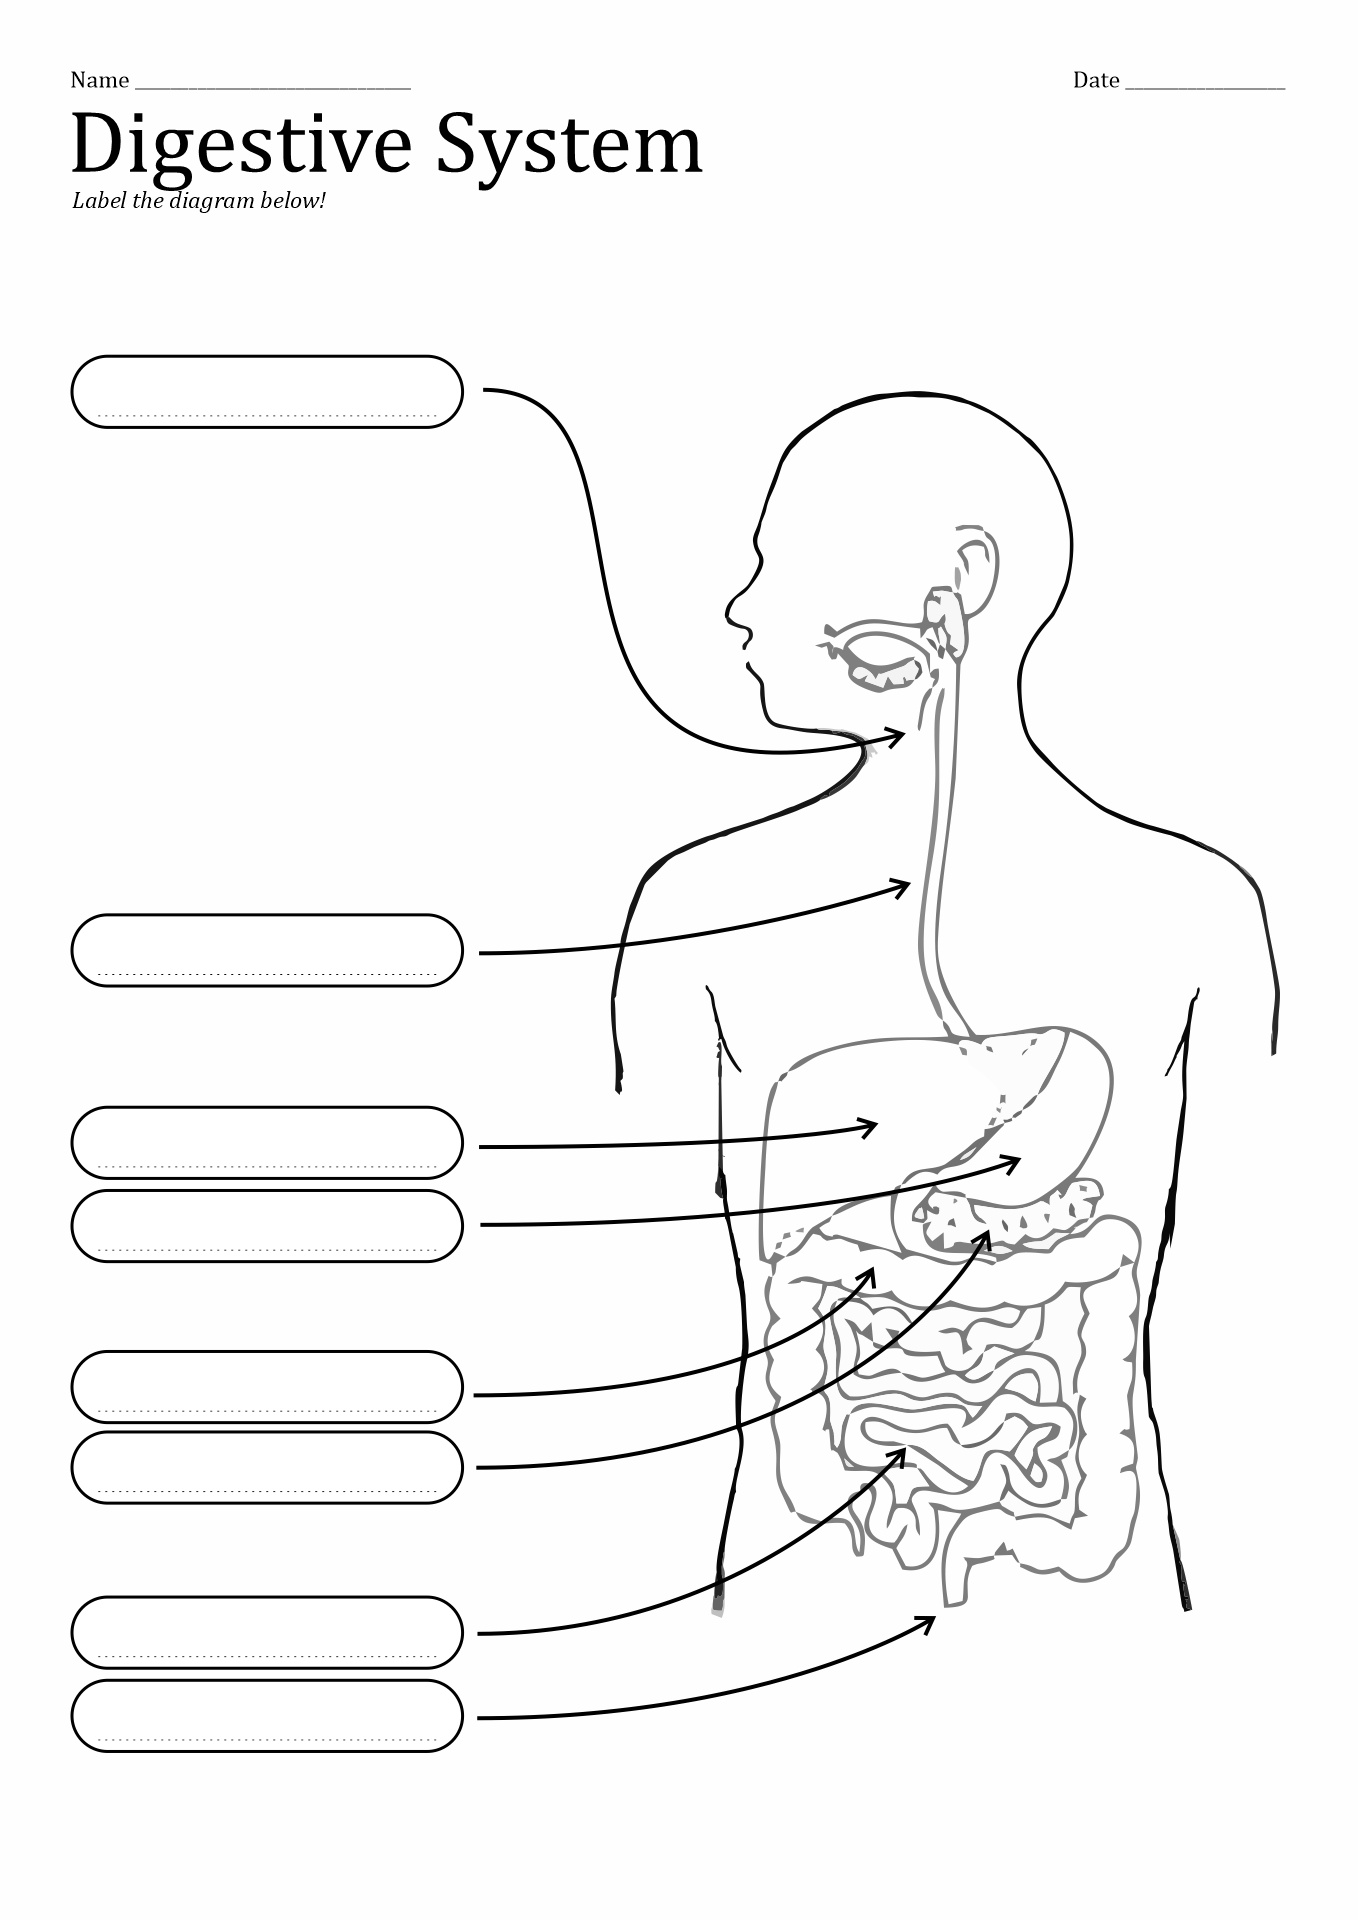
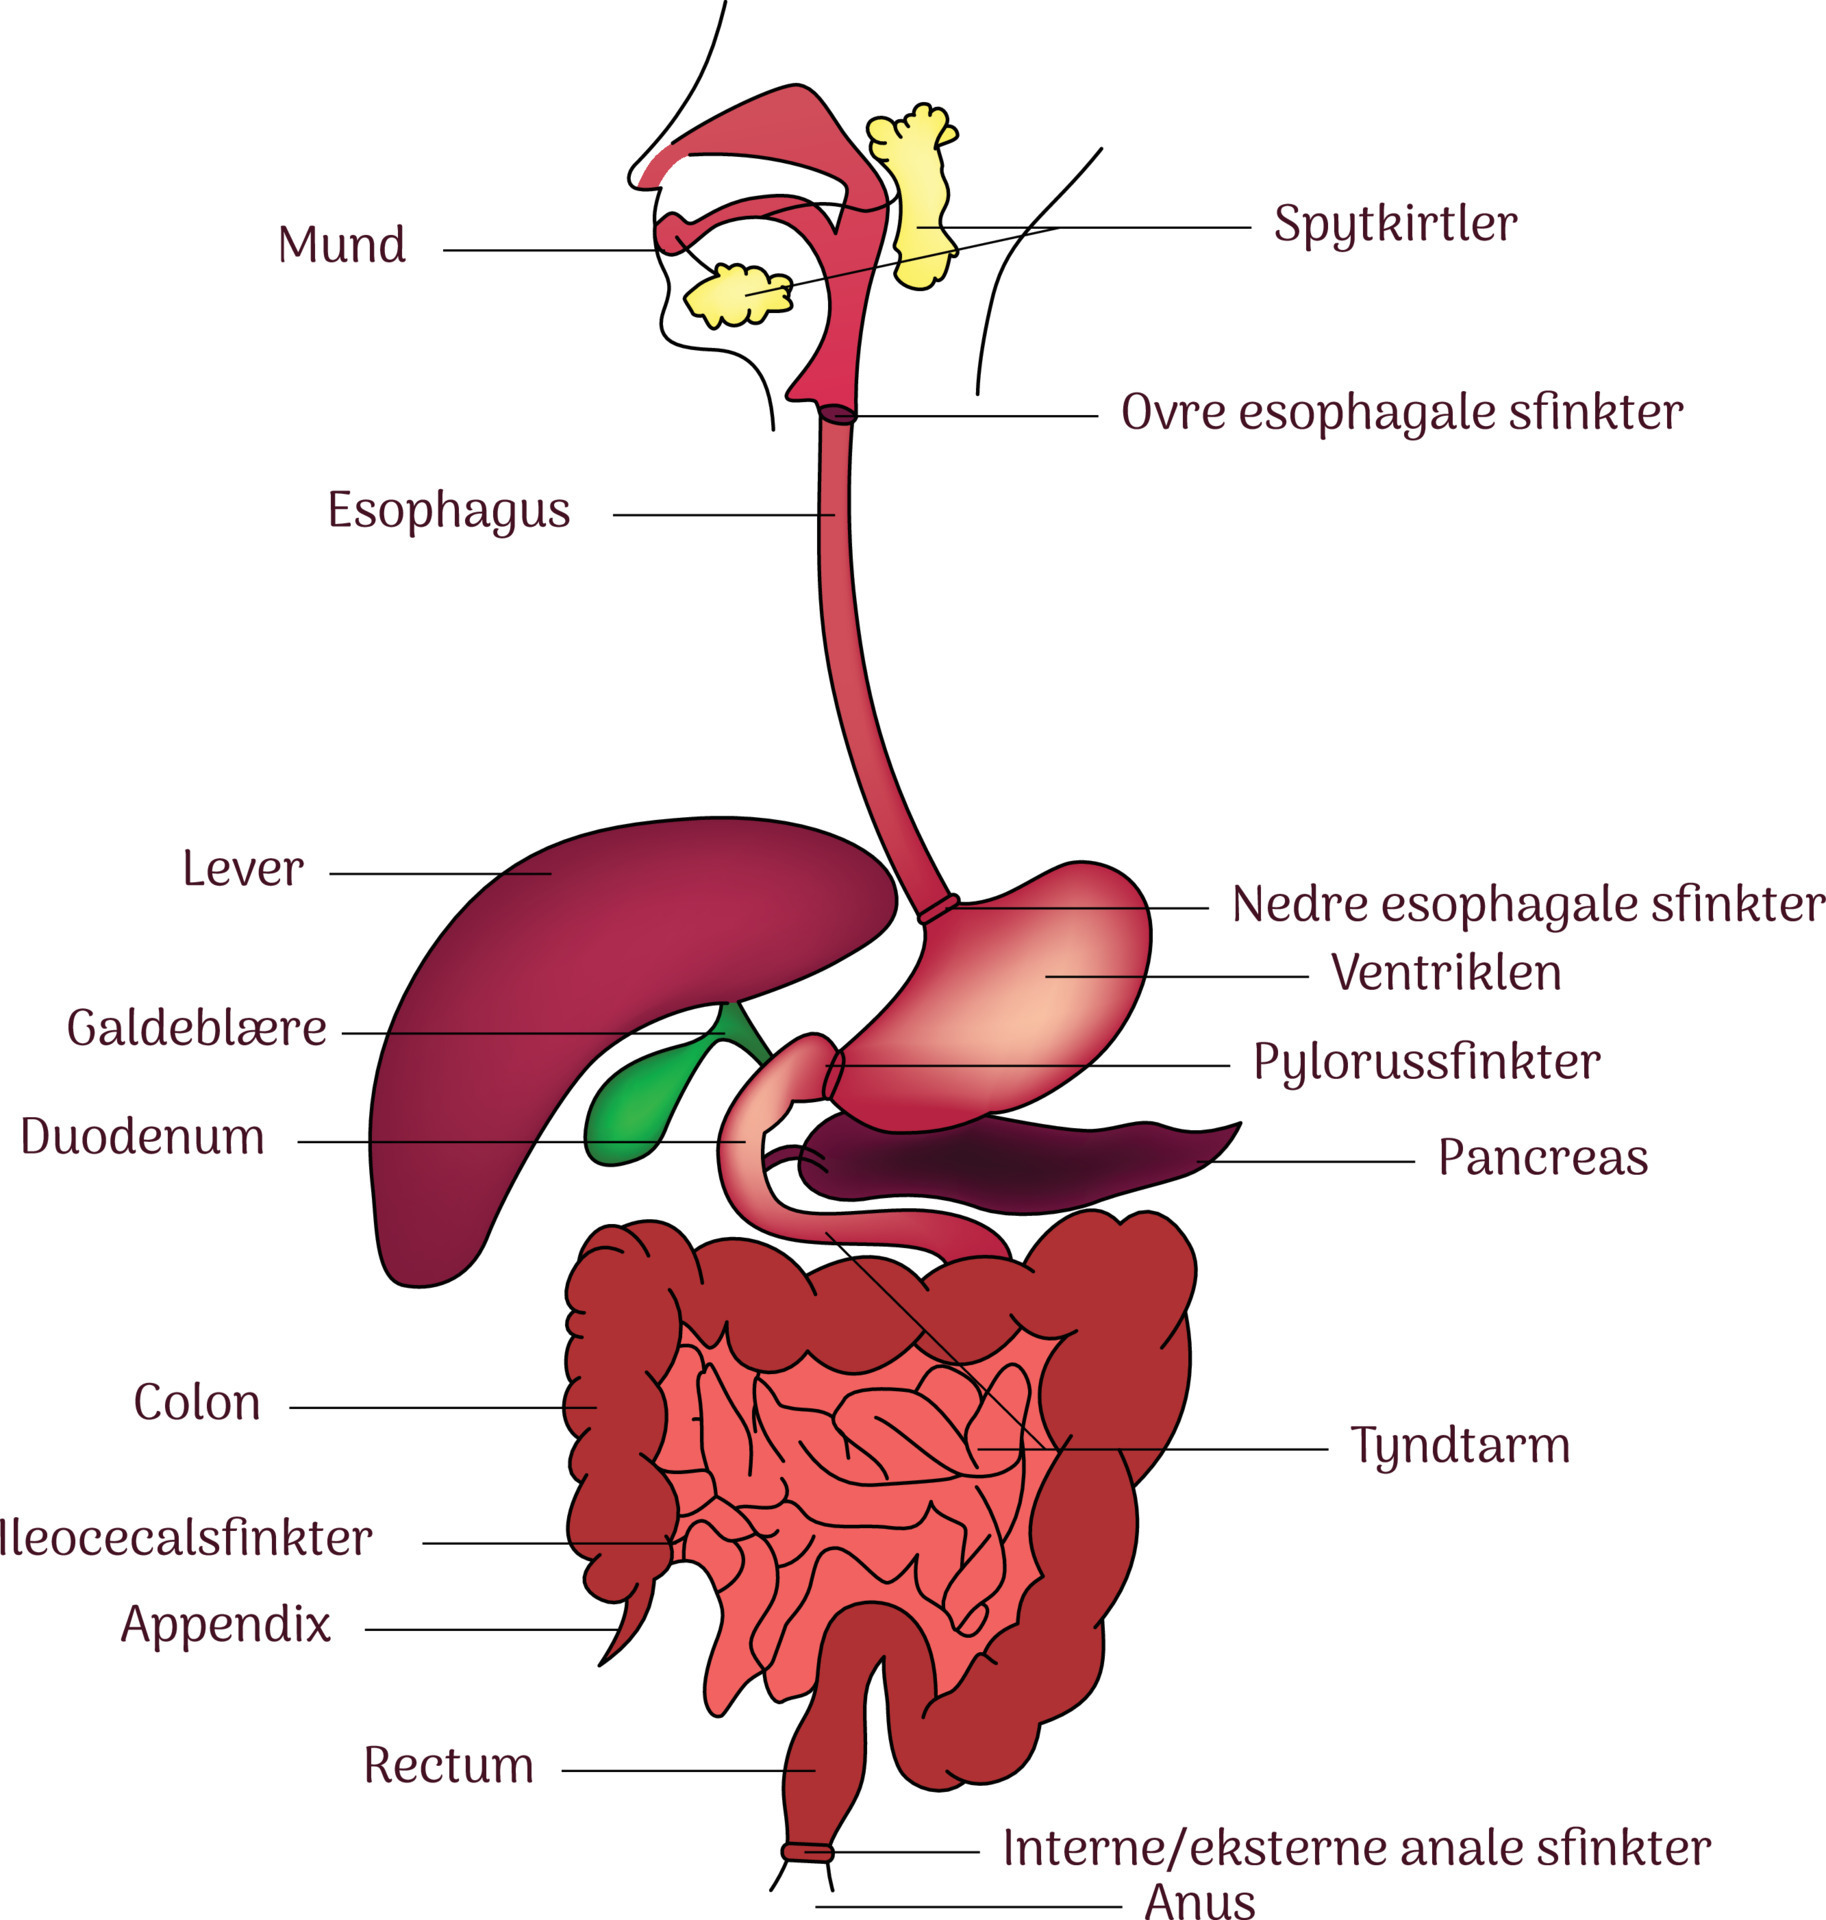
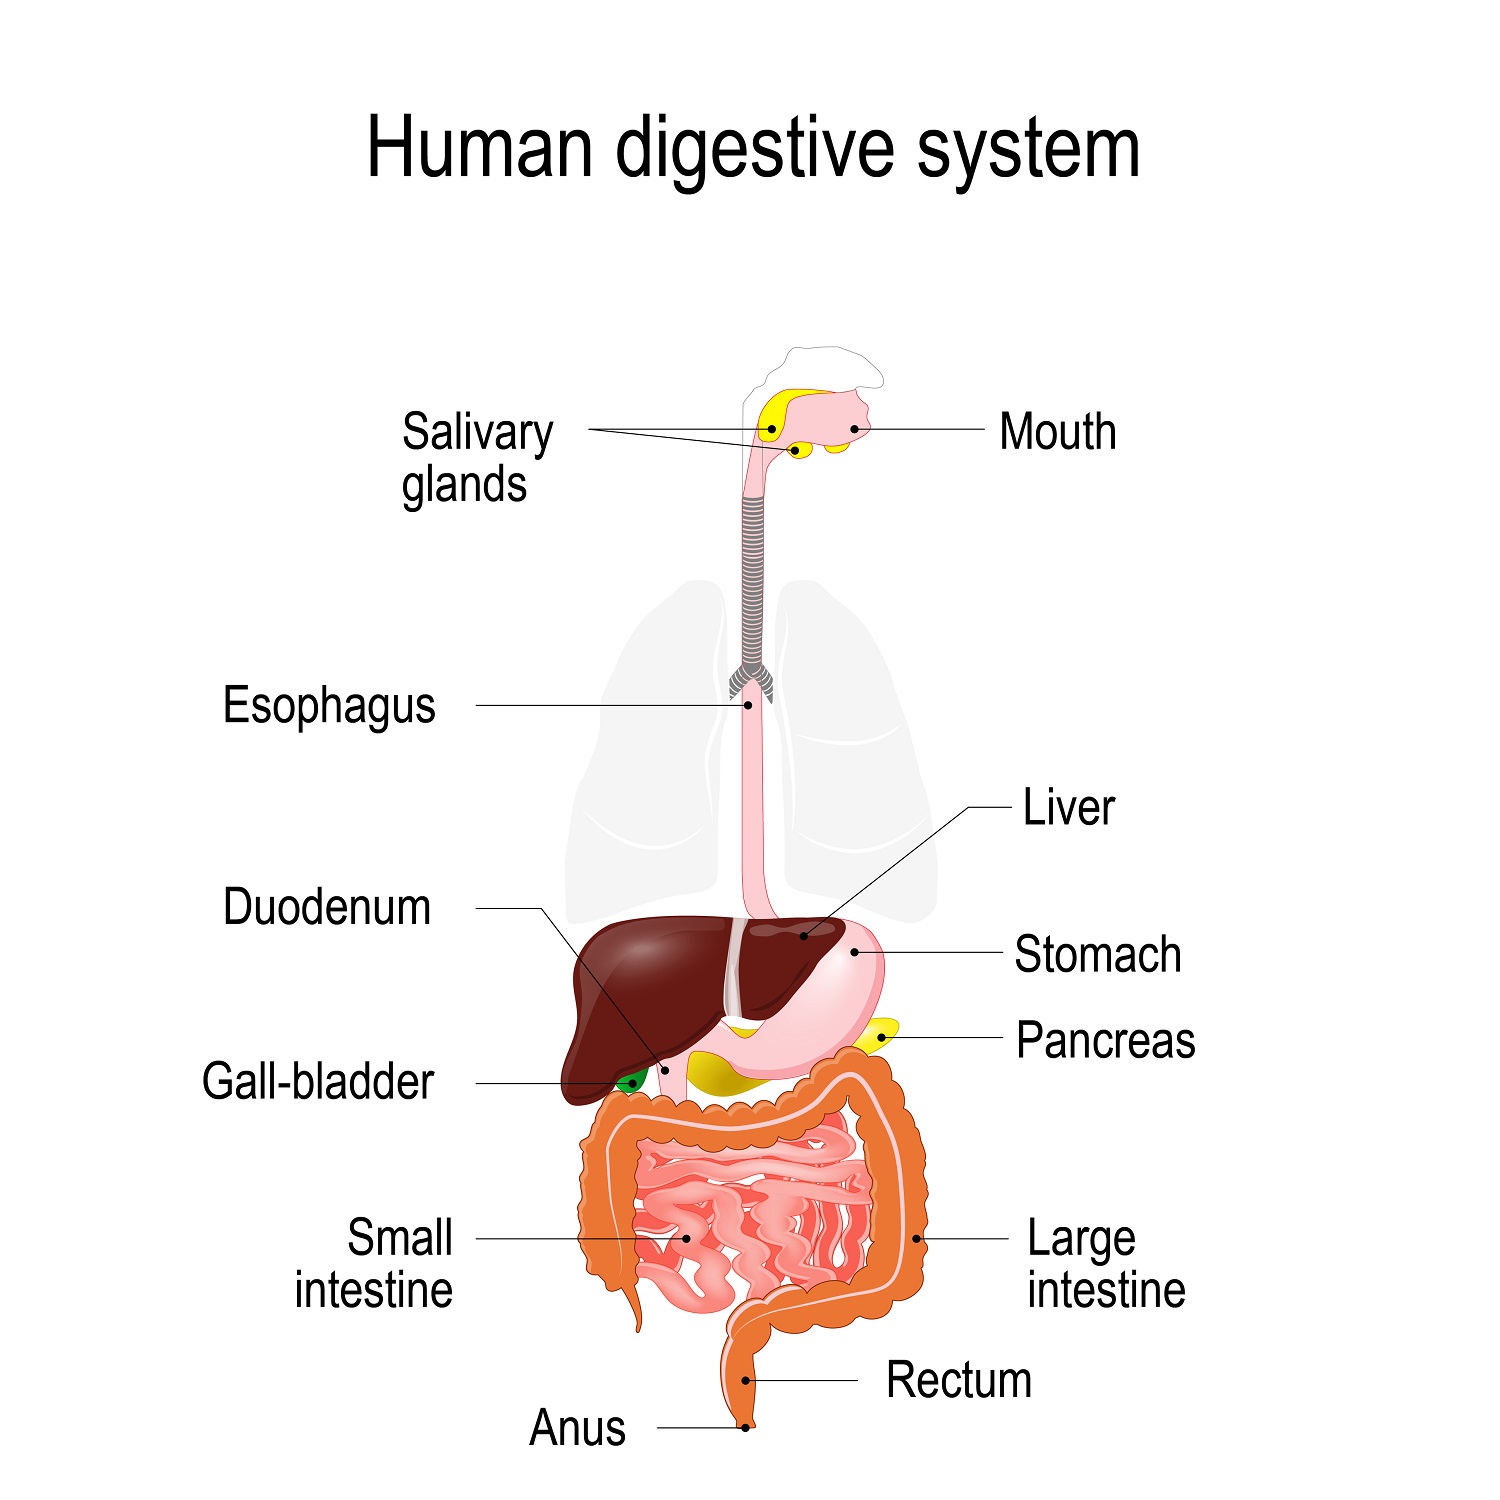
Most people treat digestive system diagram labeling as a straightforward exercise in matching words to pictures. It's not. The real difficulty comes from understanding what makes a diagram useful versus what makes it just another cluttered textbook illustration that nobody actually learns from. I've spent years grading student work and reviewing medical illustrations, and the difference is usually obvious within the first thirty seconds of looking at the page. The process begins before you even pick up a pen or open a drawing program. You need to understand the flow of material through the tract first. Food enters at the oral cavity, moves through the pharynx and esophagus into the stomach, then passes through the small intestine (duodenum, jejunum, ileum), into the large intestine (cecum, ascending colon, transverse colon, descending colon, sigmoid colon, rectum), and exits through the anal canal. The accessory organs — liver, gallbladder, pancreas, and salivary glands — sit alongside this main pathway and need to be labeled with their connections clearly indicated. I remember working with a set of diagrams where a student had labeled the "pancreatic duct" pointing to the space between the pancreas and the stomach wall instead of the actual duct opening into the duodenum. They got it wrong because they were matching terms to shapes visually without understanding the spatial relationships. The workaround was simple: trace the path of bile and pancreatic juices from the organs to where they actually empty. Once I showed them that, every labeling error in that section corrected itself because they finally understood what they were looking at rather than just guessing based on proximity.
Here's something beginners consistently miss. The order of labels matters more than most people realize. When labeling diagrams, the most important structures should get the clearest, most direct lines. Long winding leader lines that cross over other structures create visual noise and make the diagram harder to read. Keep leader lines short. Avoid having them cross each other whenever possible. This is why many published anatomical atlases use numbered callouts with a legend rather than direct labels — it's cleaner and reduces ambiguity significantly.
Practical steps that actually work
Start by printing or opening your diagram at a size where you can see fine details without straining. A diagram shrunk down to fit a phone screen is going to produce sloppy labeling no matter how much effort you put into it. Work from top to bottom following the anatomical path — mouth down through to the anus. This prevents you from labeling the same structure twice or skipping sections entirely. For the small intestine, don't just label "small intestine" as a single block. The duodenum is where the stomach connects and receives biliary and pancreatic secretions, so it needs its own label. The jejunum and ileum make up the bulk of the coiled mass and can share a general label, but distinguishing the ileum's connection to the cecum at the ileocecal valve is clinically relevant and often tested. The same principle applies to the large intestine — the haustra, taeniae coli, and epiploic appendages are structural features worth noting if the diagram is detailed enough. When dealing with the liver and gallbladder, pay attention to which lobe the gallbladder attaches to. It sits in a fossa on the visceral surface of the right lobe. Getting this wrong is one of the most common errors I see. Students will label the gallbladder near the left lobe because that's where it appears on a flat 2D representation, but in actual anatomy it's firmly anchored to the right. A quick reference to any standard cross-sectional anatomy atlas will correct this in about five minutes.
Get the Full Details

The esophagus deserves more precision than it typically gets. It passes through the diaphragm at the esophageal hiatus around the T11 vertebral level before connecting to the cardiac portion of the stomach. If your diagram shows the diaphragm or vertebral landmarks, labeling this relationship adds significant value. Most diagrams skip this detail, but it's clinically important because hiatal hernias occur when this junction fails.
Common pitfalls and where the method breaks down
The biggest limitation with diagram labeling exercises is that static 2D illustrations cannot accurately represent the three-dimensional relationships between organs. The stomach isn't a simple J-shaped bag sitting directly below the liver. It has a fundus that extends upward and to the left, a body, and a pyloric region that angles toward the right. Diagrams that show a simplified profile view will mislead students about spatial orientation. In those cases, supplementing your labeling with a brief note about 3D relationships — or using a model or 3D software — closes the gap considerably. Another issue arises with variable anatomy. The position of the cecum, for example, can vary. While it's typically in the right lower quadrant, a long mesentery can allow it to shift. Standard diagrams show the "textbook" position, but if you're labeling a diagram that shows an atypical arrangement, don't force labels to match a version that doesn't apply. Note the variation instead. This happens more often than you'd expect in clinical imaging scenarios. If you're working with digital diagrams or creating your own, vector-based tools like Inkscape or even basic presentation software give you the most control over leader line placement and text positioning. Raster-based editors tend to make fine adjustments painful. For hand-drawn diagrams, a lightbox or tracing paper over a reference image saves considerable time compared to freehand copying, though it doesn't guarantee accuracy if your source image has its own errors. Always cross-reference with an atlas or a reputable online resource like Netter's or Gray's Anatomy before finalizing anything.
The process I've described usually takes someone familiar with the material about twenty to thirty minutes for a complete, accurate labeling of a standard diagram. A beginner might spend two hours or more and still miss key relationships. The gap comes down to whether you're memorizing labels or understanding connections. Understanding connections is what carries through to exams, clinical work, and anything beyond a homework assignment.