Understanding Left-Side Subcostal Discomfort
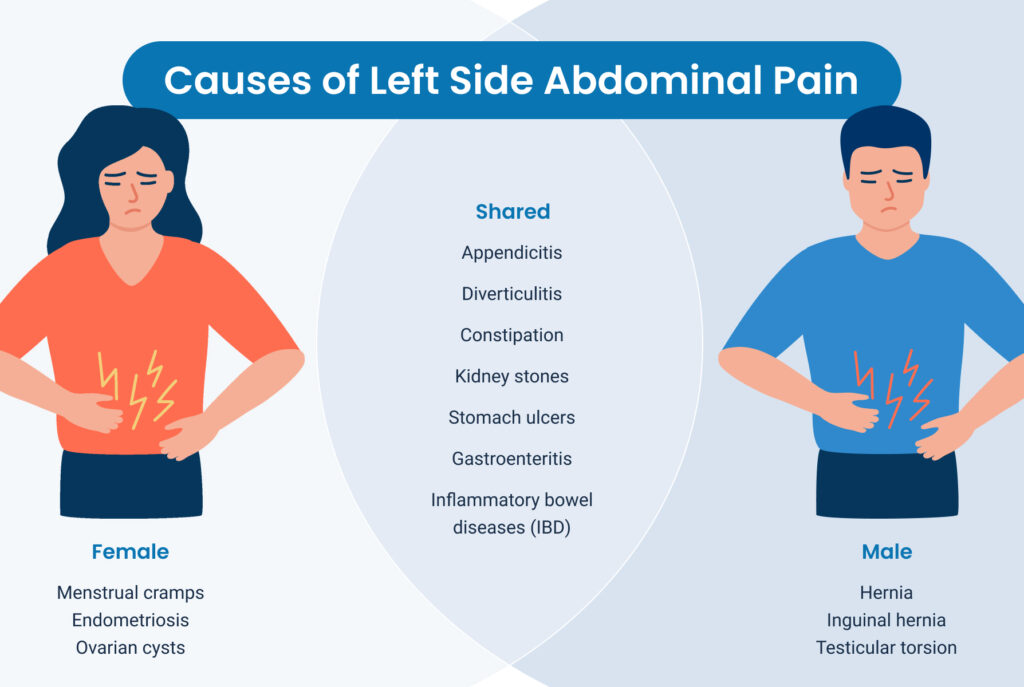
Most people who come across this topic are looking for answers because they felt something unusual under their left rib cage and went searching online. That is a normal reaction, but the internet will give you a dozen scary possibilities before you finish scrolling. The actual anatomy in that area is straightforward enough if you know where to look. The spleen sits right under the left rib cage, tucked against the back of the abdominal wall. The stomach is just below it. The tail of the pancreas extends toward that region. The left kidney is further back against the posterior abdominal wall. The splenic flexure of the colon passes right through this area and can cause genuine discomfort when it gets backed up with gas or stool. On the musculoskeletal side, you have the lower ribs, intercostal muscles, and the abdominal wall itself. I spent years dealing with unexplained left upper quadrant pain from two different sources before I figured out what was actually going on. One was chronic splenic flexure syndrome, which is just a fancy way of saying trapped gas at the bend of the colon under the ribs. The other was intercostal neuralgia from a compressed nerve root that happened to refer pain into that exact spot. Both felt similar on the surface. They responded to completely different treatments. This is the thing nobody warns you about - the symptoms overlap enough that self-diagnosis here is unreliable without some basic clinical evaluation.
Discomfort In Left Side Below Ribs: What It Actually Means
The phrase covers a range of conditions from benign and temporary to serious and requiring immediate attention. The key is learning to distinguish between them. Most cases of Discomfort In Left Side Below Ribs turn out to be gastrointestinal or musculoskeletal in origin. But a subset involves cardiac, pulmonary, or splenic pathology that should not be ignored. Here is how I approach it now, after dealing with this problem repeatedly. The first thing I check is timing and triggers. Does the discomfort appear after eating? That points toward gastric or splenic flexure involvement. Does it change with movement or deep breathing? That leans musculoskeletal or pleural. Is it constant and unrelenting regardless of position or activity? That raises a red flag for something visceral like splenic or renal pathology. Gas pain at the splenic flexure is by far the most common cause I encounter. It produces a sharp, stabbing sensation that can feel surprisingly severe. People often describe it as being on the verge of needing emergency care. It is not. The mechanism is simple. Gas accumulates in the colon at the sharp turn beneath the left rib cage. Pressure builds. The capsule stretches. The pain spikes. Then it moves. Usually within an hour of passing gas or having a bowel movement, the discomfort resolves completely. I developed a protocol for this a while back. When I feel the characteristic pressure building, I take simethicone 80mg, drink warm water, and walk. Not sit. Walk. Gravity and movement help mobilize the gas through the flexure. I time this from onset to relief and it consistently comes in under forty-five minutes if it is gas-related.
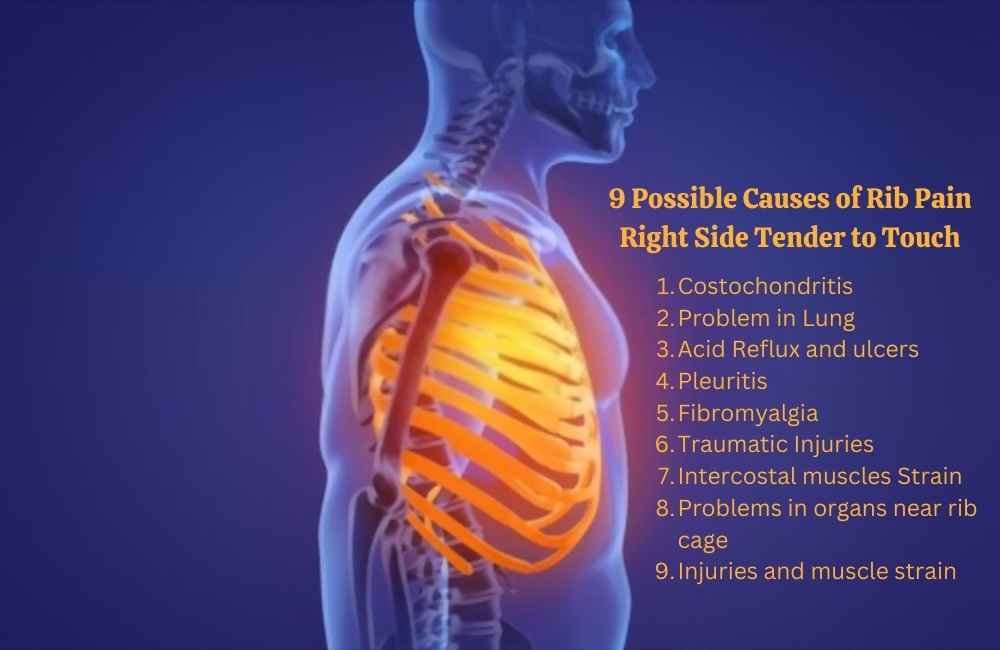
Costochondritis or intercostal muscle strain presents differently. The pain is usually reproducible with palpation. Press on the affected area and the discomfort returns or intensifies. With splenic flexure syndrome, pressing on the area does not typically reproduce the pain in the same way. That is one practical distinction worth noting. Muscle strain in this region can happen from sudden twisting, heavy lifting, or even prolonged poor posture. I once had a client who developed persistent left subcostal pain after moving furniture over a weekend. We spent two weeks working on diaphragmatic breathing exercises and gentle thoracic mobilization. The pain was coming from irritation of the lower intercostal nerves due to muscle tension in the obliques and quadratus lumborum. Tightness in those supporting muscles was pulling on the rib cage and compressing the nerve pathway. Core strengthening and myofascial release on the quadratus lumborum resolved it. The actual rib cage area was not the primary problem. Less common but more serious causes need to be mentioned. Splenic enlargement or rupture can present as left subcostal pain, usually following trauma or in the context of an underlying condition like mononucleosis. Gastric ulcers can refer pain to this area, though they more commonly cause epigastric discomfort. Pancreatitis typically causes central or left upper quadrant pain that radiates to the back and is accompanied by nausea and vomiting. Kidney stones on the left side produce severe flank pain that migrates anteriorly and inferiorly. Pleurisy causes sharp pain that worsens with breathing.
Get the Full Details

Cardiac issues, particularly angina or myocardial infarction, can present with left-sided chest or subcostal discomfort. This is less common than right-sided or central cardiac presentation, but it absolutely happens. Women in particular may experience atypical cardiac pain. Any left subcostal pain accompanied by shortness of breath, sweating, nausea, or radiation to the jaw or arm should be treated as a cardiac event until proven otherwise. I have one practical tip that saves time. Keep a symptom log for at least a week. Record when the discomfort occurs, what you were doing, what you had eaten, bowel movements, and intensity on a scale of one to ten. This single habit cuts down the diagnostic uncertainty significantly. After a week, patterns emerge that are not obvious in the moment. Most people who do this find their episodes cluster around specific triggers they had not considered. If you are dealing with this repeatedly and over-the-counter interventions are not helping after a couple of weeks, getting evaluated is the right move. A basic workup usually includes blood work, urinalysis, and possibly imaging. An ultrasound of the left upper quadrant is a reasonable first step and avoids radiation exposure. If the pain is persistent and the ultrasound is inconclusive, a CT scan provides more detail on the spleen, pancreas, and kidney.
The main pitfall people run into is assuming every episode of left subcostal discomfort is the same thing. It is not. Gas pain one day might feel identical to musculoskeletal pain the next, but the underlying cause and appropriate treatment differ. Learning to differentiate them through observation and tracking is the most useful skill you can develop here.