Understanding Disease Versus Illness: Why the Distinction Actually Matters In Practice
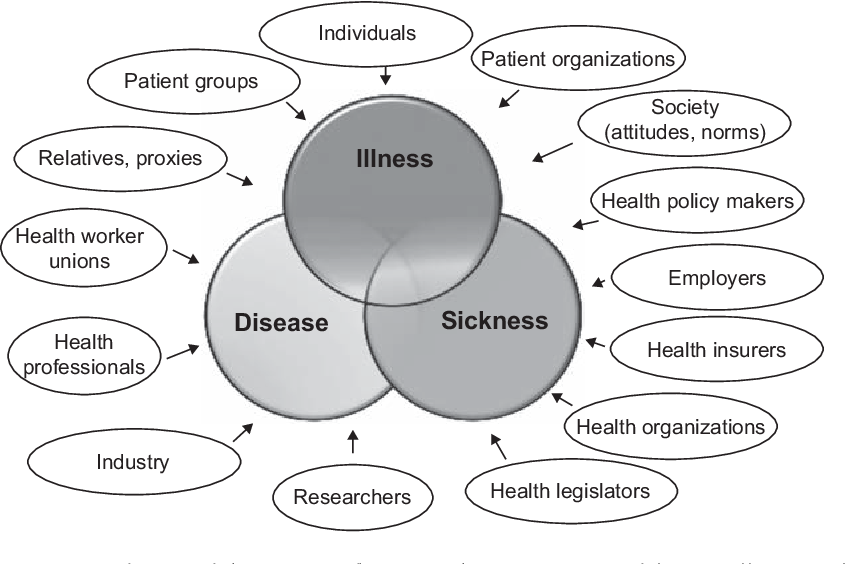
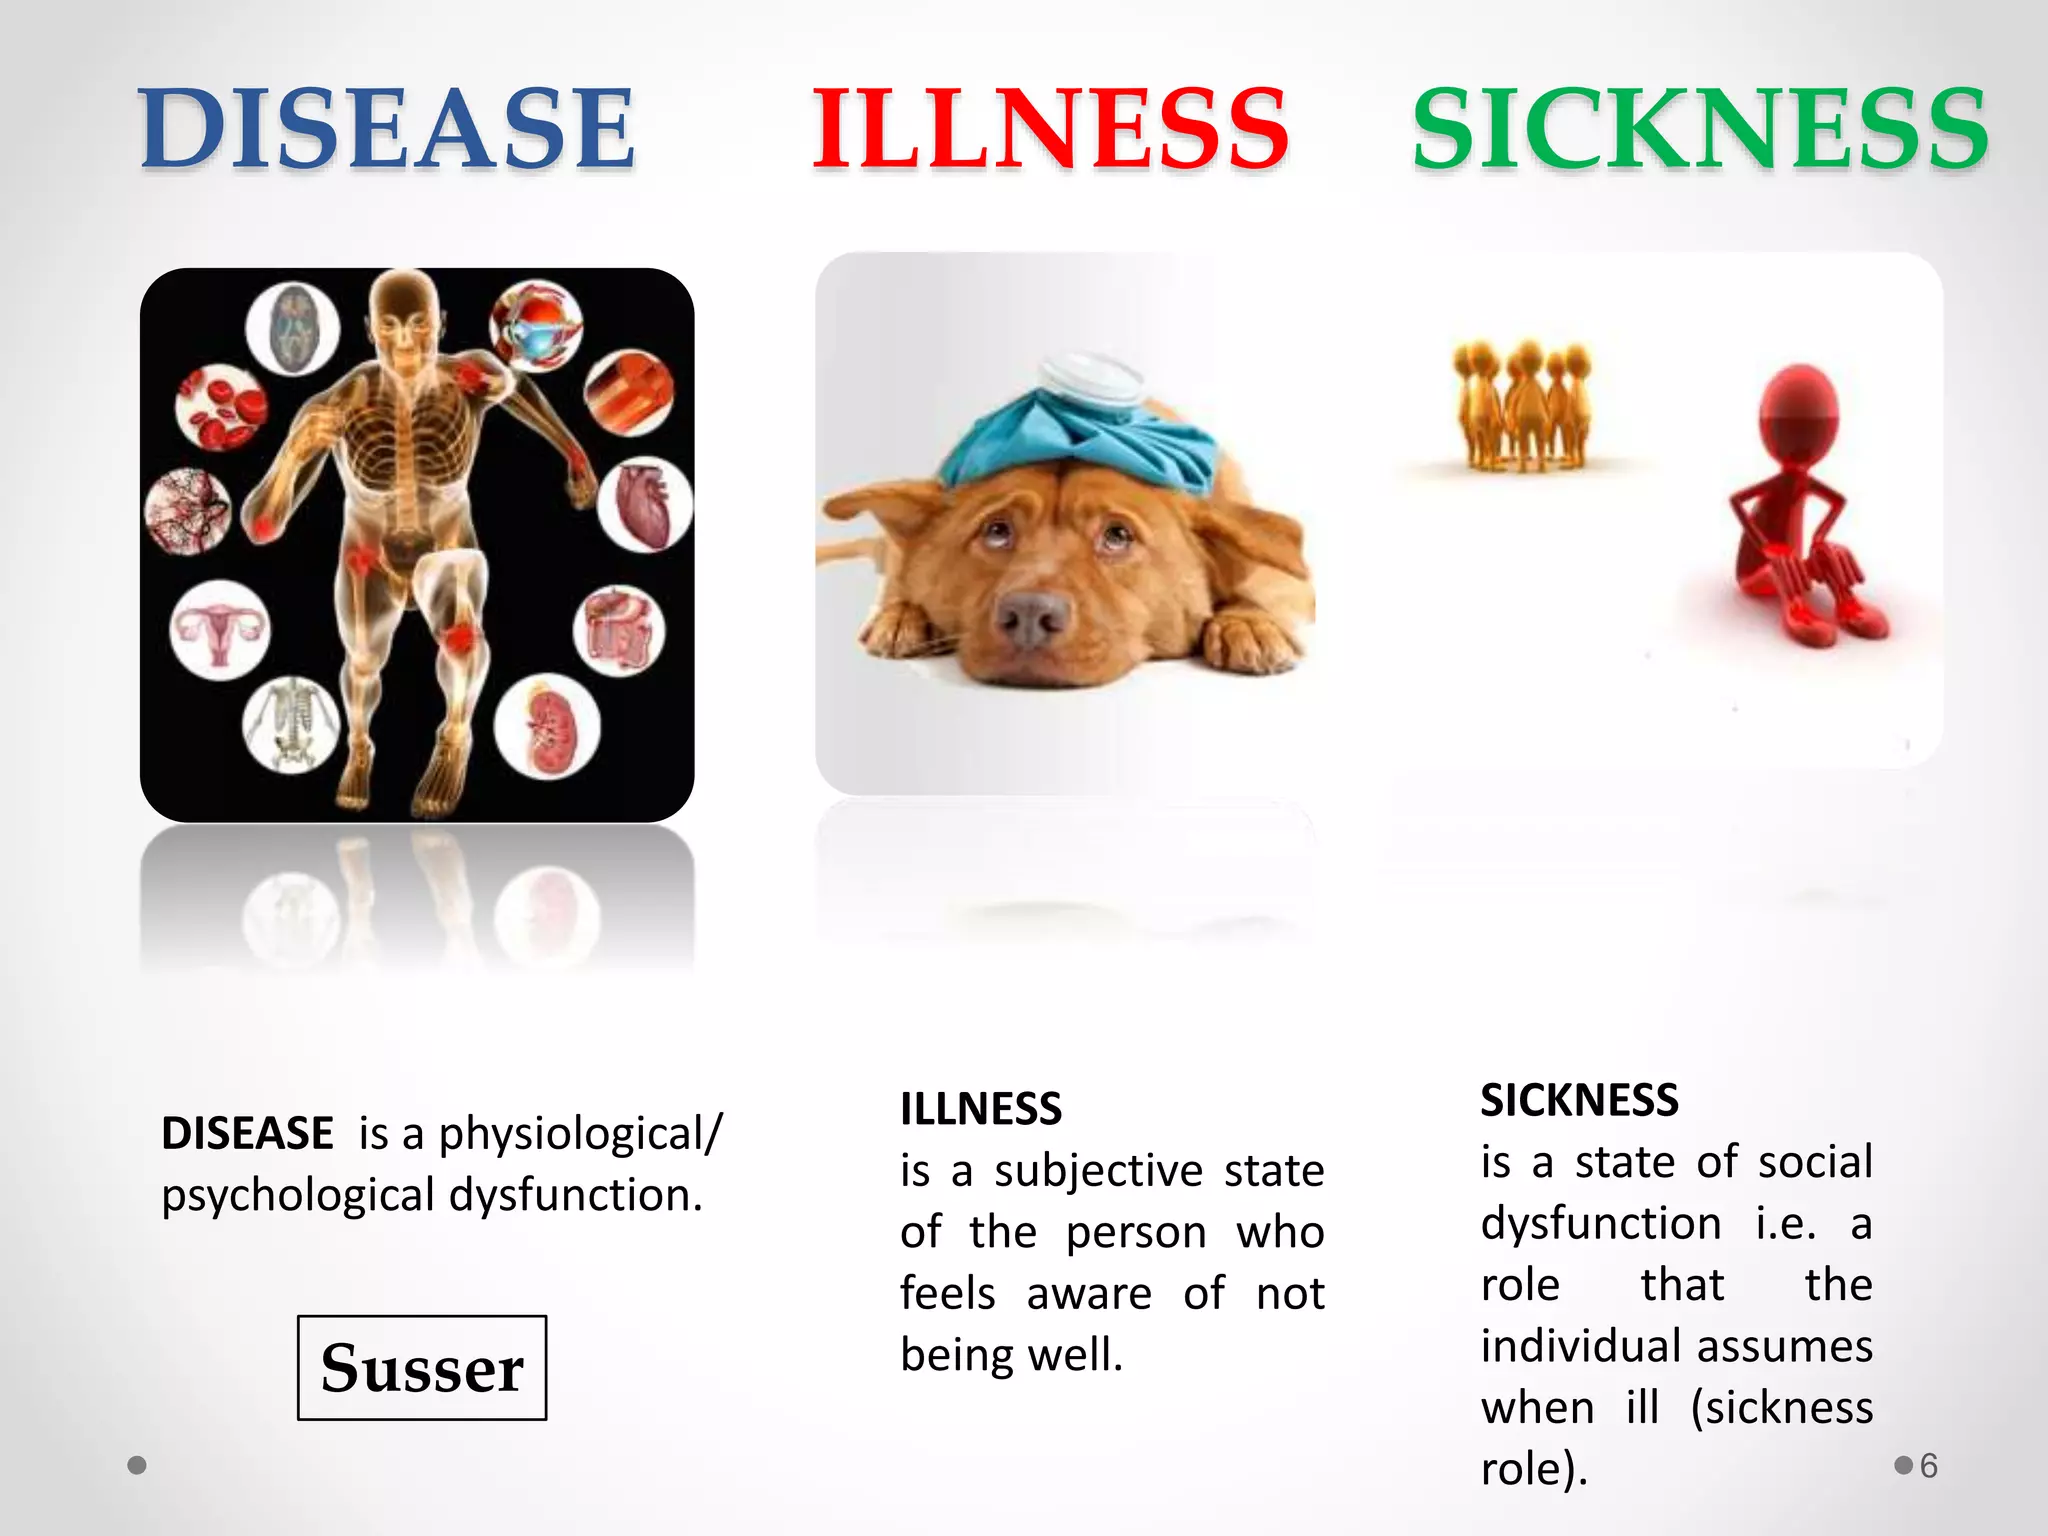
Doctors and patients often use disease and illness interchangeably, but they mean different things, and confusing the two creates real problems in clinical workflows. Disease refers to a biological abnormality — a pathogen, a genetic mutation, a structural change. Illness is the subjective experience of feeling unwell. You can have one without the other, and recognizing when they diverge is where most diagnostic errors start. I spent years working in internal medicine before moving into clinical research, and the hardest patients to manage were the ones where disease and illness didn't align. Take myocardial infarction versus non-cardiac chest pain. The biomarkers tell you one thing; the patient's presentation tells you another. When troponin is elevated but the pain doesn't fit an ischemic pattern, you don't just dismiss the symptom or ignore the lab value. You sit with the ambiguity until it resolves. Here is the operational difference that most beginners miss. Disease is objective. It exists on imaging, in labs, under a microscope. Illness is reported. It lives in the patient's narrative. A positive autoimmune panel is a disease finding. The chronic fatigue, brain fog, and widespread pain the patient describes is the illness. Both are real. Neither is sufficient on its own.
The clinical shortcut most people take is to treat the disease and assume the illness resolves with it. That works for infections and acute conditions where the pathology is straightforward. It fails for chronic multifactorial conditions. I saw this repeatedly with thyroid disorders. Patients with subclinical hypothyroidism — TSH slightly elevated, free T4 normal — often have zero illness symptoms yet get placed on levothyroxine because the lab value demands treatment. Conversely, patients with normal thyroid panels sometimes carry significant illness burden from other causes that the thyroid axis doesn't explain. The disease metric didn't match the illness experience in either direction. Another common trap is anchoring to a single disease marker and letting it override the full clinical picture. A positive ANA test is present in roughly 15 to 20 percent of healthy individuals, particularly women over thirty. If you treat every positive autoimmune screen as a disease diagnosis, your patient load balloons and your differential diagnosis collapses into noise. The workaround I adopted was to require that any disease label be paired with at least two independent clinical features before initiating treatment. One lab value plus one symptom is a hypothesis. Two or more independent findings is a working diagnosis. There is also the reverse situation where illness severity outpaces detectable disease. Functional somatic syndromes — fibromyalgia, chronic fatigue syndrome, irritable bowel syndrome — fall into this category. Standard lab panels come back normal. Imaging shows nothing. The patient is genuinely impaired. This is not a diagnosis of exclusion in the way some clinicians treat it. It is a diagnosis of symptom pattern recognition, and the evidence base supports specific management pathways even when no structural disease is visible. The downside of this approach is that insurance payers and some specialist networks still require a codable disease entity before approving treatment, which creates friction that delays care by weeks or months.
When you are building protocols or clinical pathways around these concepts, the most practical framework is to separate the diagnostic track from the symptomatic track. Diagnose the disease where you can identify it. Treat the illness symptoms regardless of whether a disease cause is confirmed. These are parallel processes, not sequential ones. Waiting for a definitive disease diagnosis before addressing severe symptoms is a common bottleneck that increases patient suffering and decreases adherence. The limitation most people don't talk about is that this dual-track model requires more time and more communication. You have to explain to a patient that their symptoms are being taken seriously even though the tests are normal. You have to document both tracks separately so other clinicians can follow your reasoning. In a fast-paced clinic with fifteen-minute slots, that explanation rarely fits. The result is abbreviated conversations where patients leave feeling dismissed even when you are actively managing their illness. For anyone designing patient education materials or clinical guidelines, the key takeaway is structural. Define disease clearly as the biological anomaly. Define illness clearly as the experienced symptom burden. State explicitly that both deserve attention and that treatment should address each where possible. Don't hide behind the assumption that patients already understand the difference. They usually don't, and the confusion erodes trust faster than almost anything else in a clinical encounter.
Get the Full Details