Breaking the Link
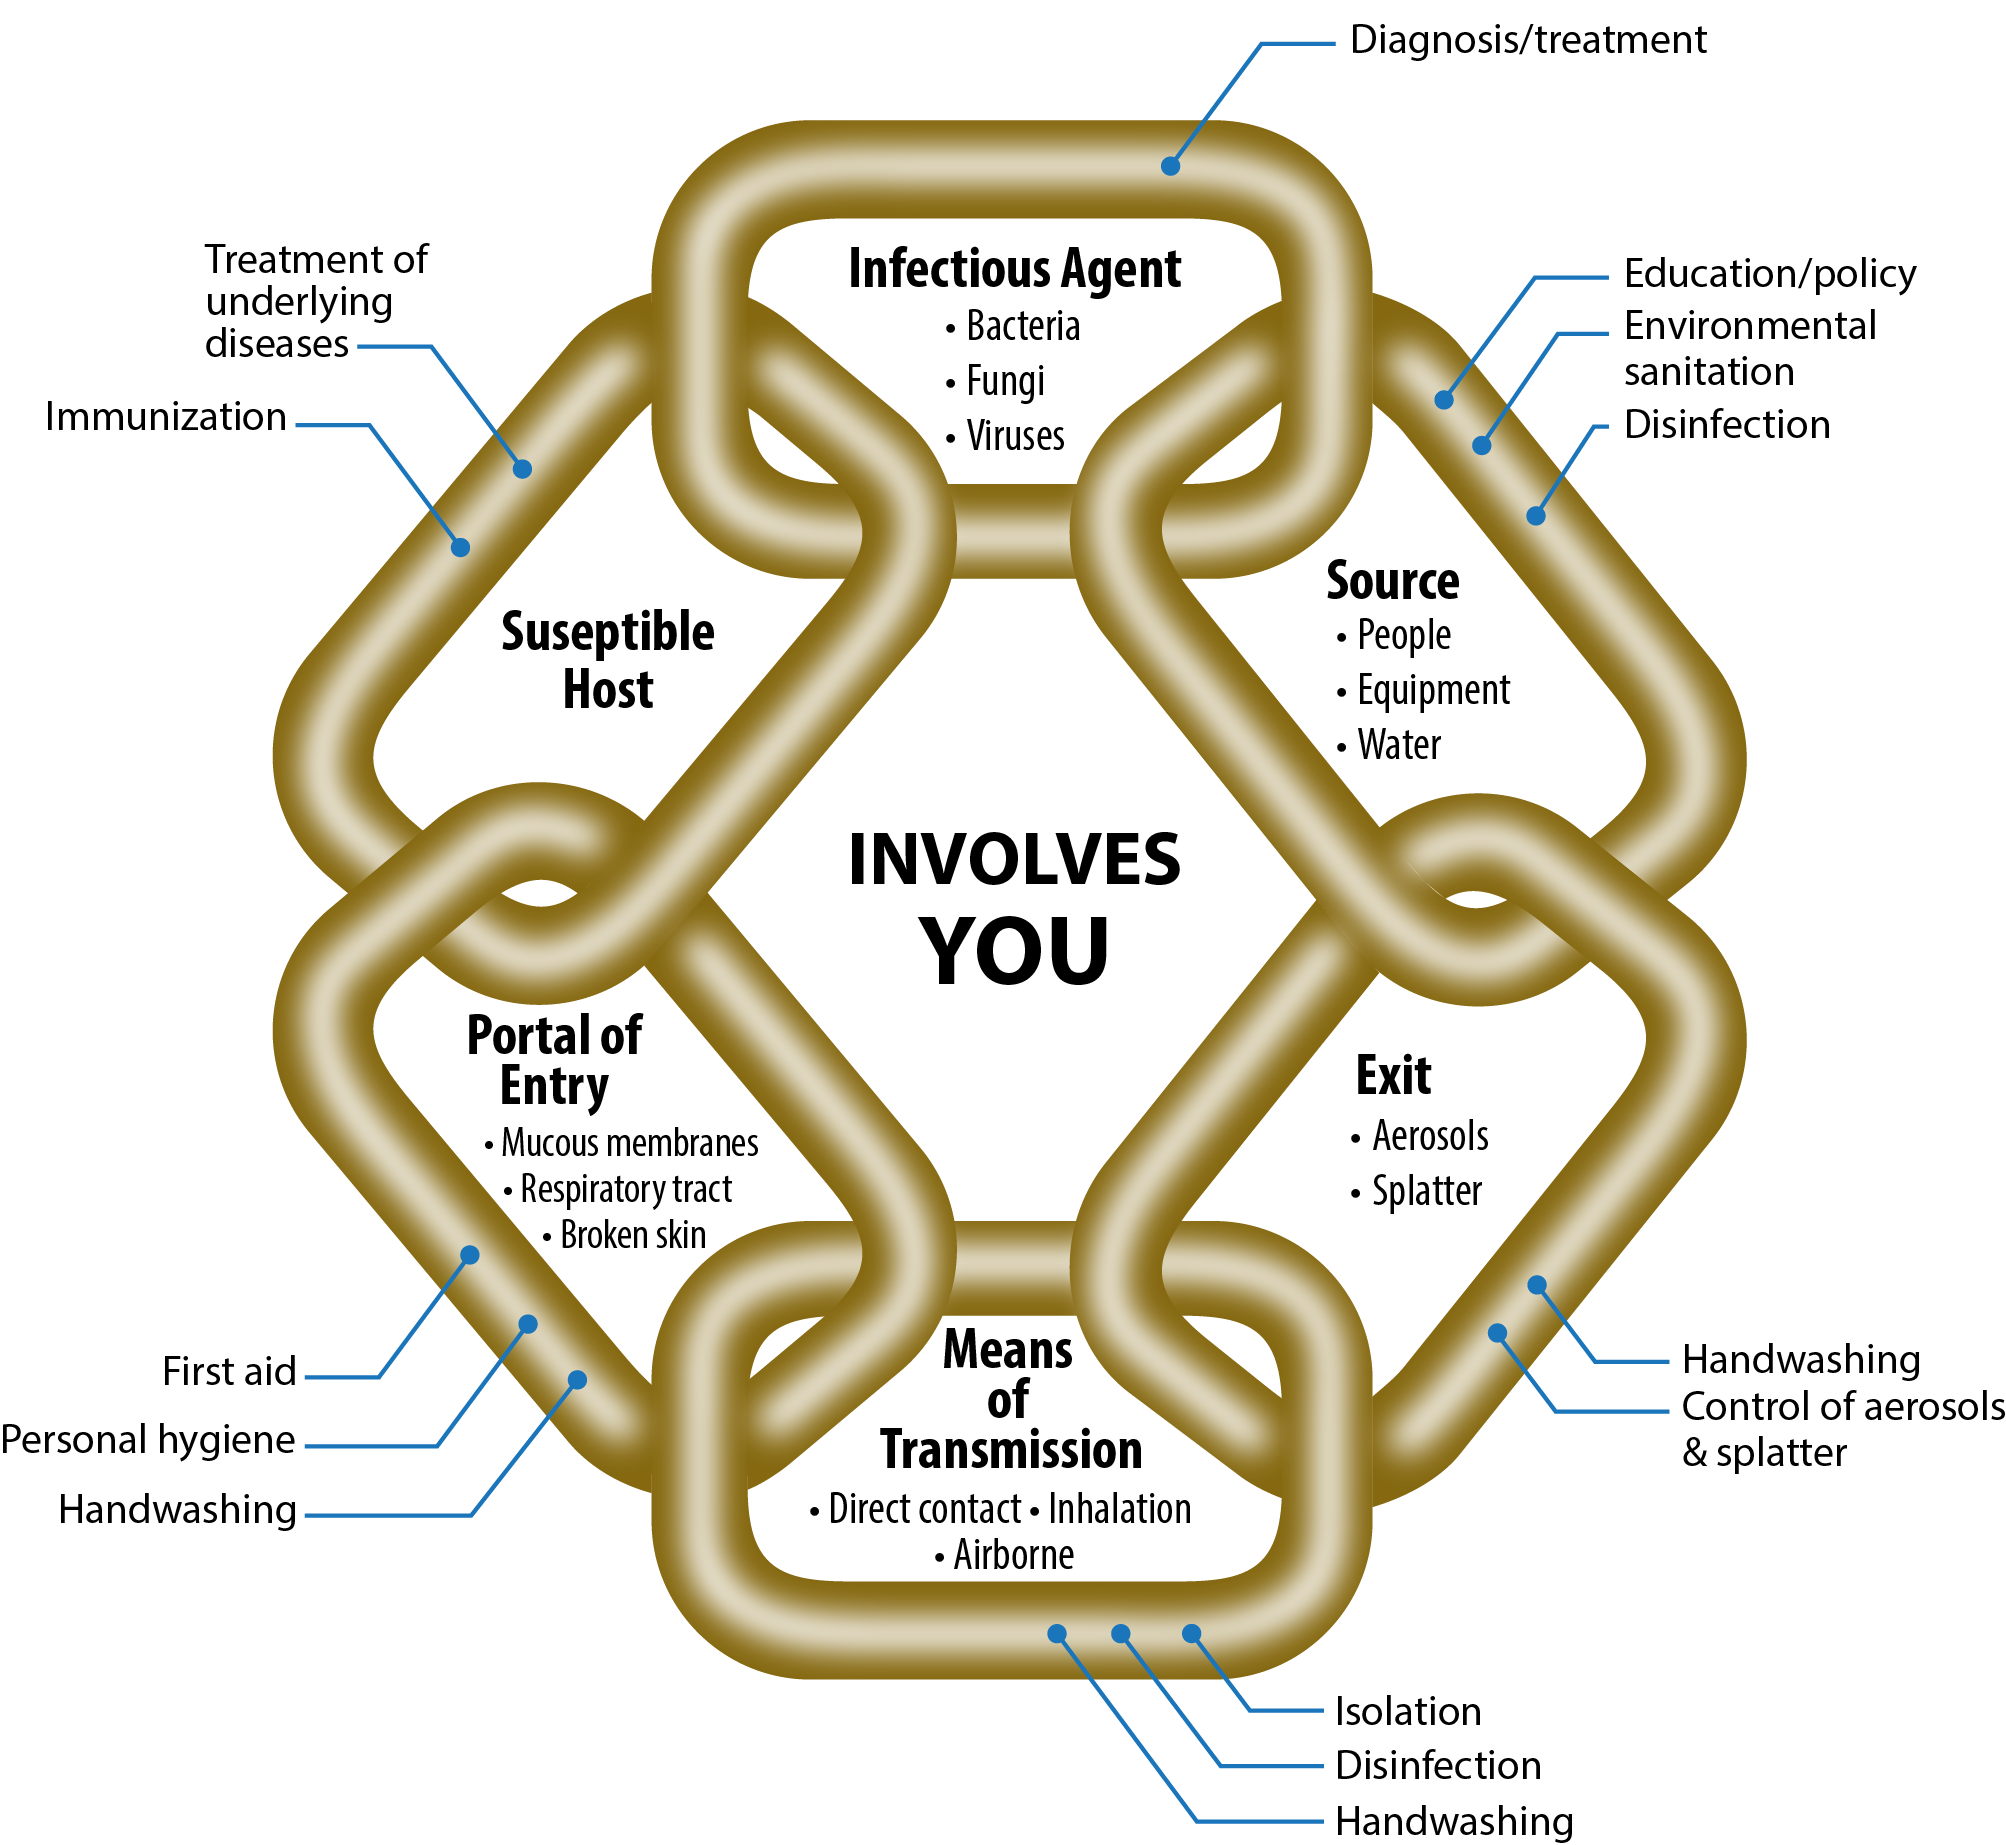
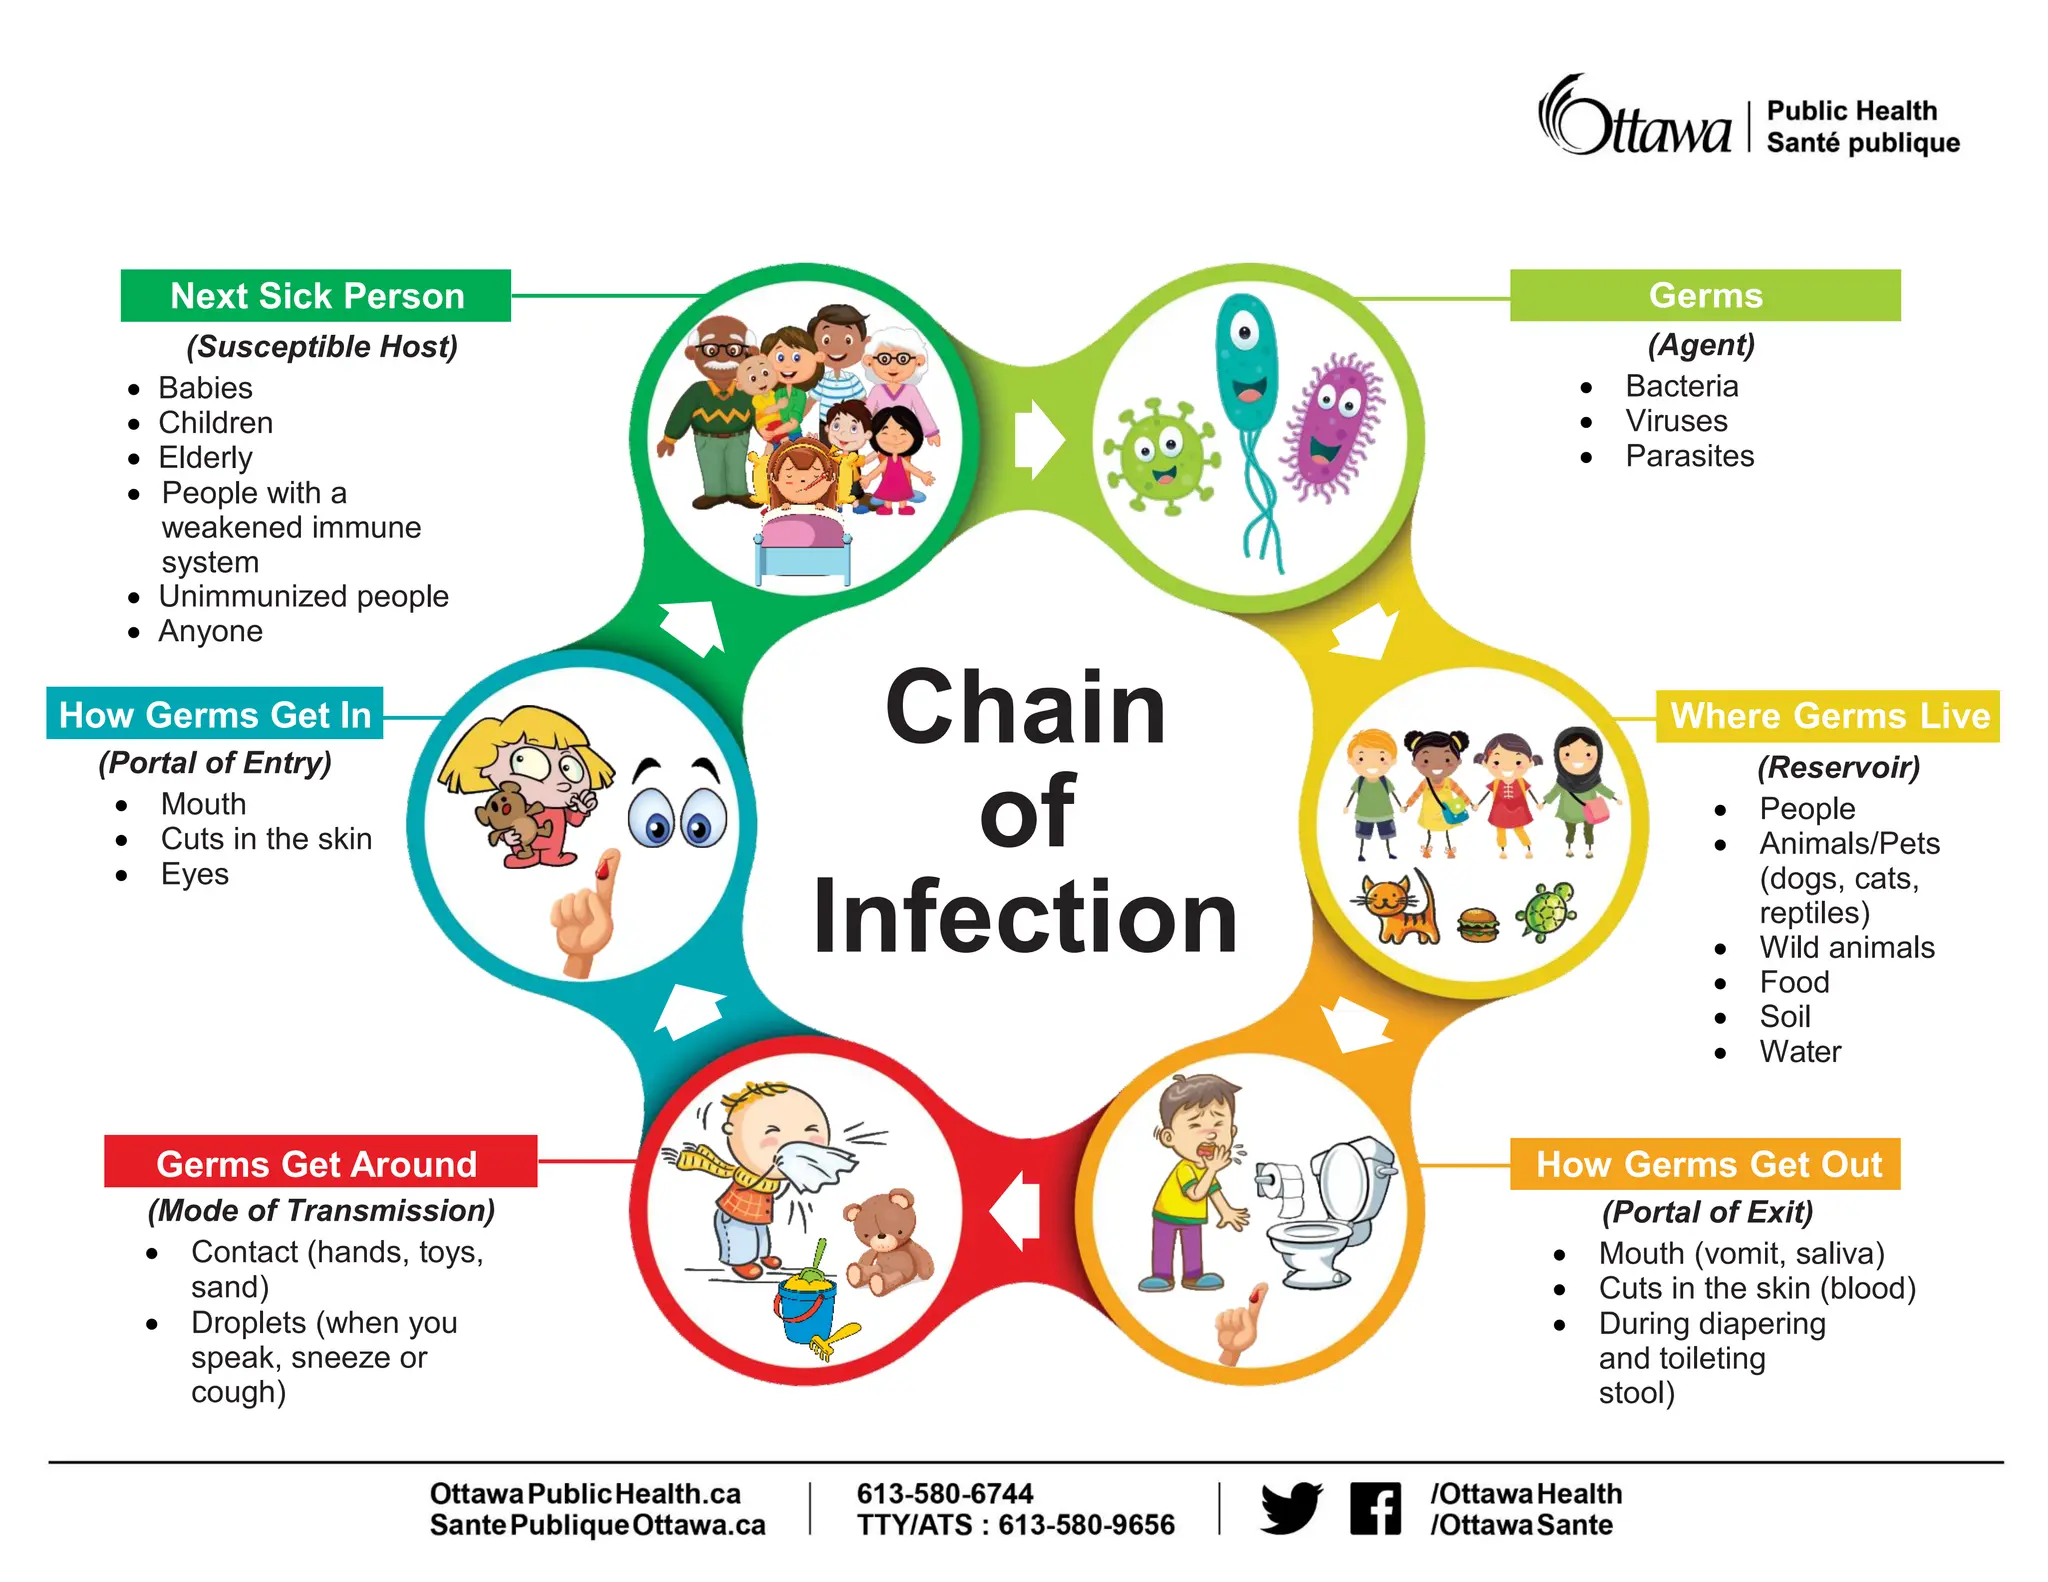
The disease chain of infection is the sequence of events that allows a pathogen to move from one host to another. If you are studying for an exam or training in healthcare, you have probably seen it laid out as five links: the infectious agent, the reservoir, the portal of exit, the mode of transmission, the portal of entry, and the susceptible host. The idea is simple enough, but in practice the chain is often broken by measures that feel unrelated to the actual biology of the organism. Start with the agent itself. Not all microbes are created equal. A spore-forming bacterium like Clostridioides difficile sits on surfaces for months and survives alcohol-based hand rubs. An enveloped virus like influenza loses infectivity within minutes on dry skin but can travel through the air on tiny droplets for longer distances. Knowing what kind of agent you are dealing with tells you which part of the chain to target, and it changes the answer entirely. The reservoir is wherever the organism lives and multiplies. Humans, animals, soil, water, medical equipment, and even the skin flora of healthcare workers can all serve as reservoirs. I once spent two weeks tracking a cluster of surgical site infections back to a single instrument tray that had been stored in a humid cabinet. The tray was the reservoir. The surgeon's gloves were the portal of exit and entry. The mode of transmission was direct contact during the procedure. Breaking just one link stopped the outbreak.
The Five Links in Detail
Infectious agent: This includes bacteria, viruses, fungi, and parasites. The agent determines virulence, transmissibility, and which interventions will work. Antibiotic-resistant organisms require different precautions than drug-sensitive ones. Some agents mutate rapidly, which means the chain can re-form through a slightly different route almost overnight. Reservoir: The natural habitat where the pathogen lives. Reservoirs can be human, animal, or environmental. In hospital settings, sinks, ventilators, and central lines are common reservoirs that people overlook because they do not look like biological material. A study of ICU patients found that the reservoir for multidrug-resistant Gram-negative bacteria was often the moist environment inside the ventilator circuit, not the patient itself. Portal of exit: How the pathogen leaves the reservoir. Common portals include the respiratory tract, gastrointestinal tract, blood, skin lesions, and genitourinary secretions. An infected wound draining onto bedding creates a different risk profile than asymptomatic respiratory shedding. The portal of exit matters because it determines what personal protective equipment is actually necessary.
Mode of transmission: This is where most public health interventions happen. Direct contact, indirect contact through fomites, droplet spread over short distances, airborne transmission through small particles that remain suspended, and vector-borne routes via insects or animals. The mode of transmission dictates the level of isolation required. Droplet precautions are completely insufficient for airborne pathogens, and I have seen that mistake cost hospitals significant money in retrofitted negative-pressure rooms after the fact. Portal of entry: The route the pathogen uses to enter a new host. Mucous membranes, broken skin, and the respiratory and gastrointestinal tracts are the usual entry points. A needlestick injury bypasses the skin barrier entirely and places the pathogen directly into the bloodstream, which is why occupational exposure protocols exist for a reason. Susceptible host: Anyone whose immune system cannot clear the pathogen quickly enough. Age, underlying disease, immunosuppression, pregnancy, and prior exposure all affect susceptibility. The same pathogen can cause severe disease in one person and nothing in another. This is why outbreak investigations always ask about comorbidities and medication use, not just contact history.
Get the Full Details

Breaking the Chain in Practice
Hand hygiene is the single most effective intervention, but compliance is notoriously difficult to measure accurately. Direct observation tends to inflate numbers because people change their behavior when they know they are being watched. Electronic monitoring systems exist but create privacy concerns and can malfunction. In my experience, the best proxy is alcohol-based hand rub consumption per patient care day, normalized by unit type. It is not perfect, but it tracks real behavior over time better than spot checks. Personal protective equipment works when it matches the mode of transmission. Gowns and gloves matter for contact precautions. N95 respirators matter for airborne precautions. Surgical masks do not provide reliable protection against airborne particles, a fact that became painfully obvious during the early pandemic months when institutions were scrambling for supplies. The type of PPE must be chosen based on the documented or suspected route, not on general caution. Environmental cleaning is often undervalued. Surface disinfection reduces the reservoir, but the choice of disinfectant matters. Quaternary ammonium compounds work against many vegetative bacteria but are ineffective against spores and some non-enveloped viruses. Hydrogen peroxide vapor and ultraviolet light systems have shown promise for terminal cleaning in outbreak situations, but they are expensive and require trained operators. I learned this the hard way when a facility invested in UV devices without proper staff training and then questioned whether the technology was ineffective.
Isolation and cohorting break the mode of transmission. Single rooms are ideal, but during surges or in resource-limited settings, cohorting infected patients together is the next best option. The key is keeping the cohort separate from non-infected individuals and ensuring that staff do not move between cohorts without changing PPE and performing hand hygiene.
Common Missteps
One mistake I see repeatedly is treating the disease chain as linear rather than dynamic. The links can loop back on themselves. A healthcare worker can be both the reservoir and the susceptible host if they acquire an organism on their hands and then contaminate a patient, later developing symptoms themselves. Another mistake is focusing only on the transmission mode while ignoring the reservoir. Cleaning a room is useless if the patient still harbors the organism and continues to shed it. A more subtle issue is assuming that standard precautions are sufficient for every situation. Standard precautions cover blood, bodily fluids, and non-intact skin, but they do not address airborne or specific contact routes that may require additional measures. During norovirus outbreaks, for example, standard hand hygiene with alcohol rub is inadequate because norovirus is not an enveloped virus and survives alcohol. Soap and water and friction are necessary, and even then, spore-forming organisms like C. diff require the same approach. Another pitfall is overreliance on antimicrobial stewardship without addressing the ecological factors that drive resistance. Prescribing narrower-spectrum antibiotics helps, but if the reservoir remains untouched and transmission continues, resistant strains will circulate regardless of prescribing patterns. Stewardship and infection control are complementary, not interchangeable.

When the Chain Breaks on Its Own
Not every outbreak requires active intervention. Some chains break naturally when the susceptible host population becomes immune through prior exposure or vaccination. Herd immunity is the epidemiological version of a broken link, though it is not a strategy you can reliably plan around, especially with emerging variants or waning vaccine-derived protection. Measles is a case in point. The basic reproduction number is so high that even small gaps in vaccination coverage can reignite transmission in a community that previously appeared protected. Vaccination remains one of the most powerful tools for protecting susceptible hosts. It does not always prevent infection, but it reduces severity and shortens the duration of infectiousness, which effectively weakens multiple links in the chain simultaneously. The hepatitis B vaccine, for instance, has reduced chronic liver disease and hepatocellular carcinoma rates significantly because it interrupts the blood-borne transmission route before chronic infection can take hold.
Limitations and When This Framework Falls Short
The disease chain model is a simplification. It works well for straightforward transmission scenarios but struggles with complex, multi-route pathogens like Mycobacterium tuberculosis, which can spread through both airborne and contact routes depending on the setting. It also does not capture the role of asymptomatic carriers, super-spreaders, or the social determinants that influence who gets exposed and who can afford to isolate. In low-resource settings, the theoretical links may exist on paper but not in practice. There may be no isolation rooms, no adequate PPE supply, and no budget for environmental cleaning. In those cases, the framework is useful for identifying the highest-leverage intervention, but the answer is rarely a simple protocol change. It usually requires structural investment that goes beyond infection control training. For healthcare workers dealing with routine admissions, the chain is a useful mental model for deciding what precautions to apply. For public health officials investigating an outbreak, it is a checklist for generating hypotheses. For patients and the general public, understanding that the chain can be broken at any point is more empowering than focusing exclusively on the pathogen itself. The organism is only part of the story. The environment, the behavior, and the host immune status are equally important.