What the Disease Model Of Addiction Actually Means In Practice
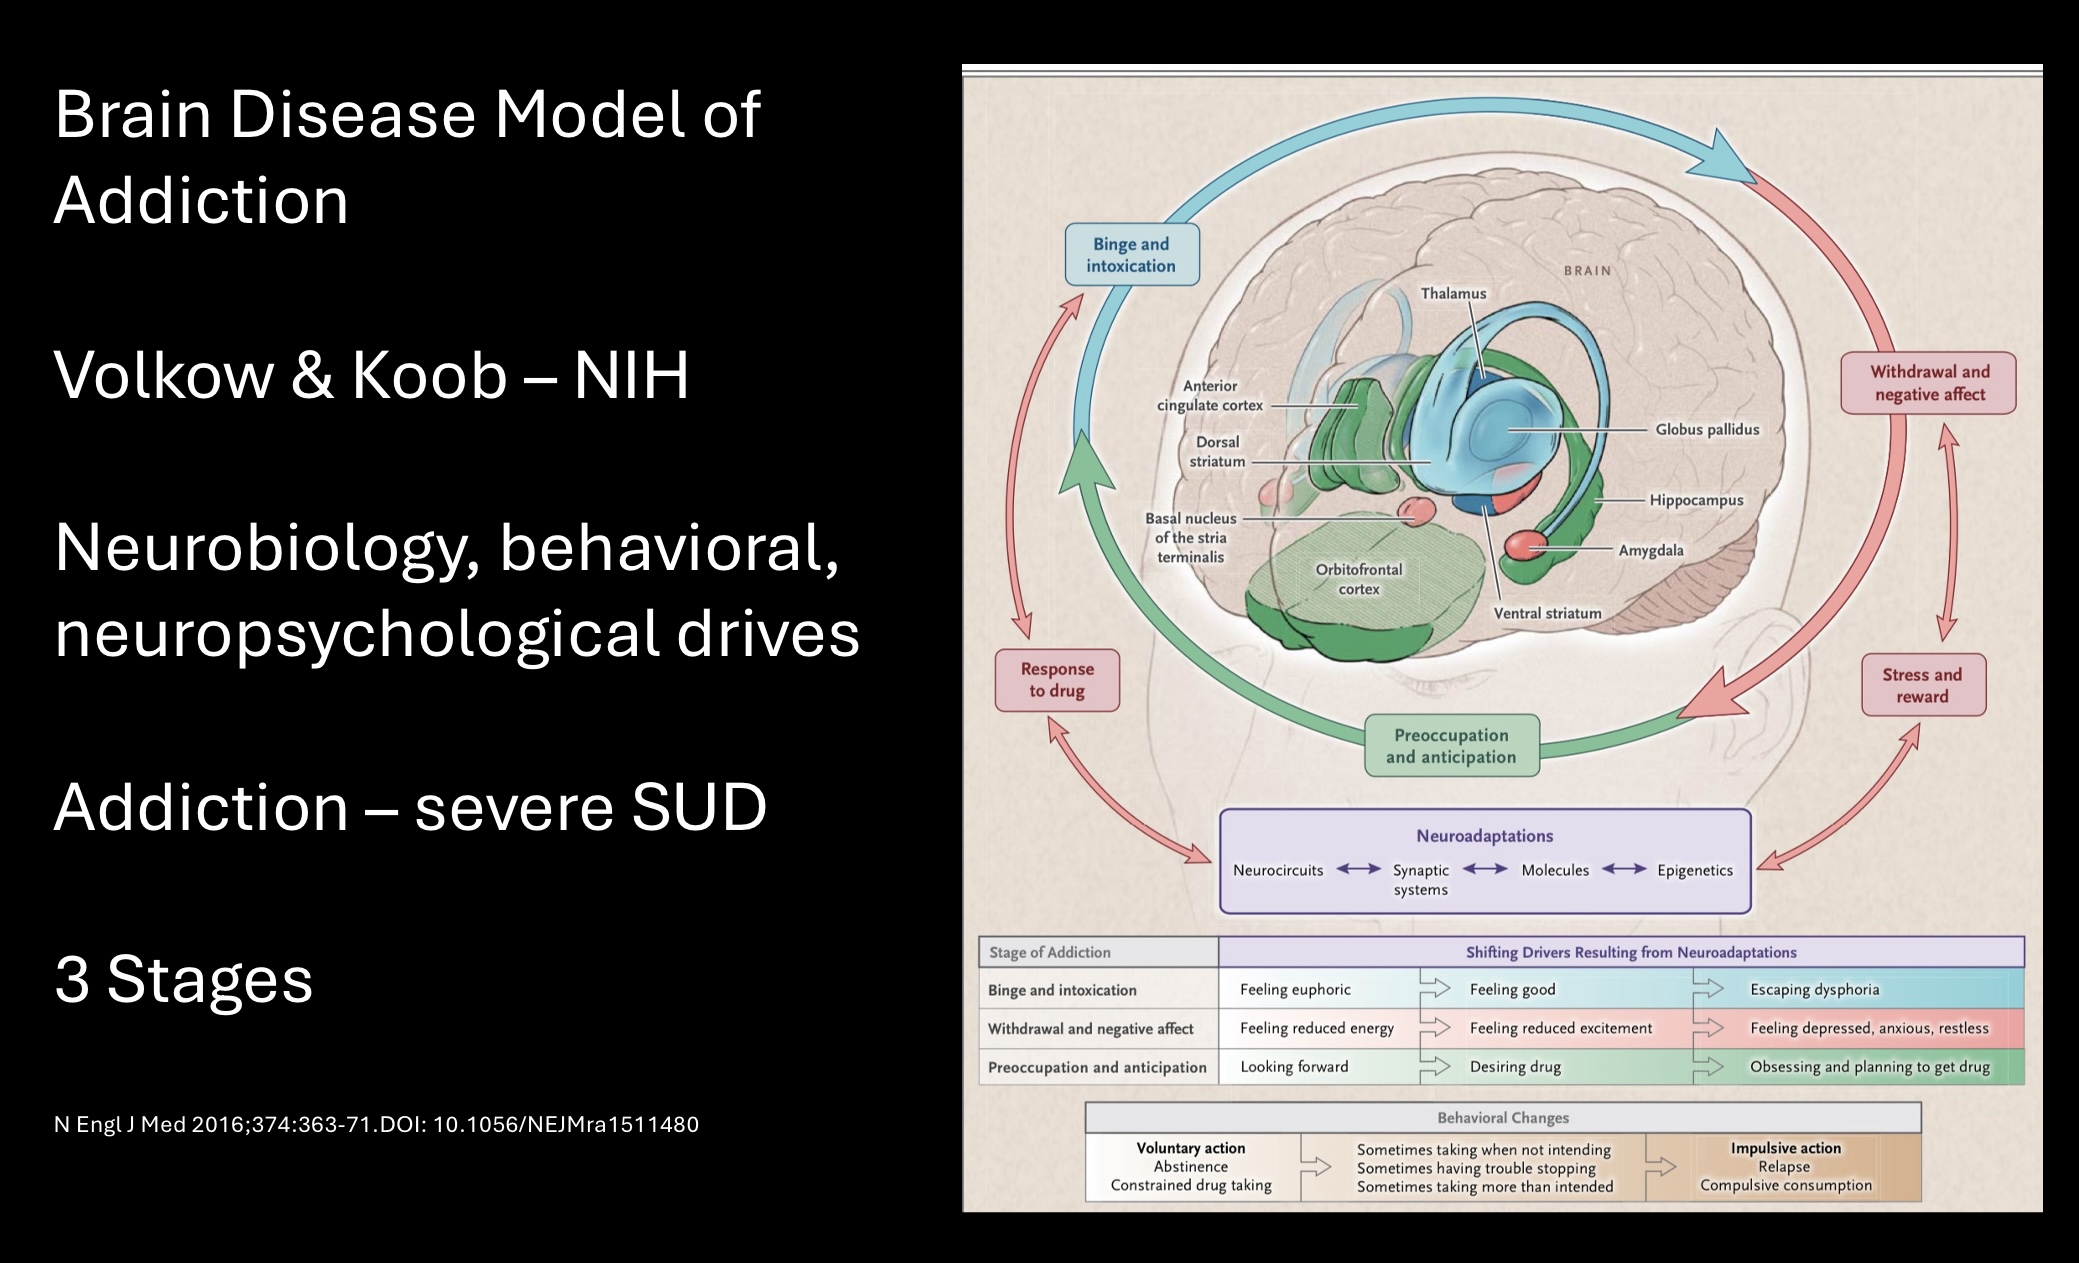
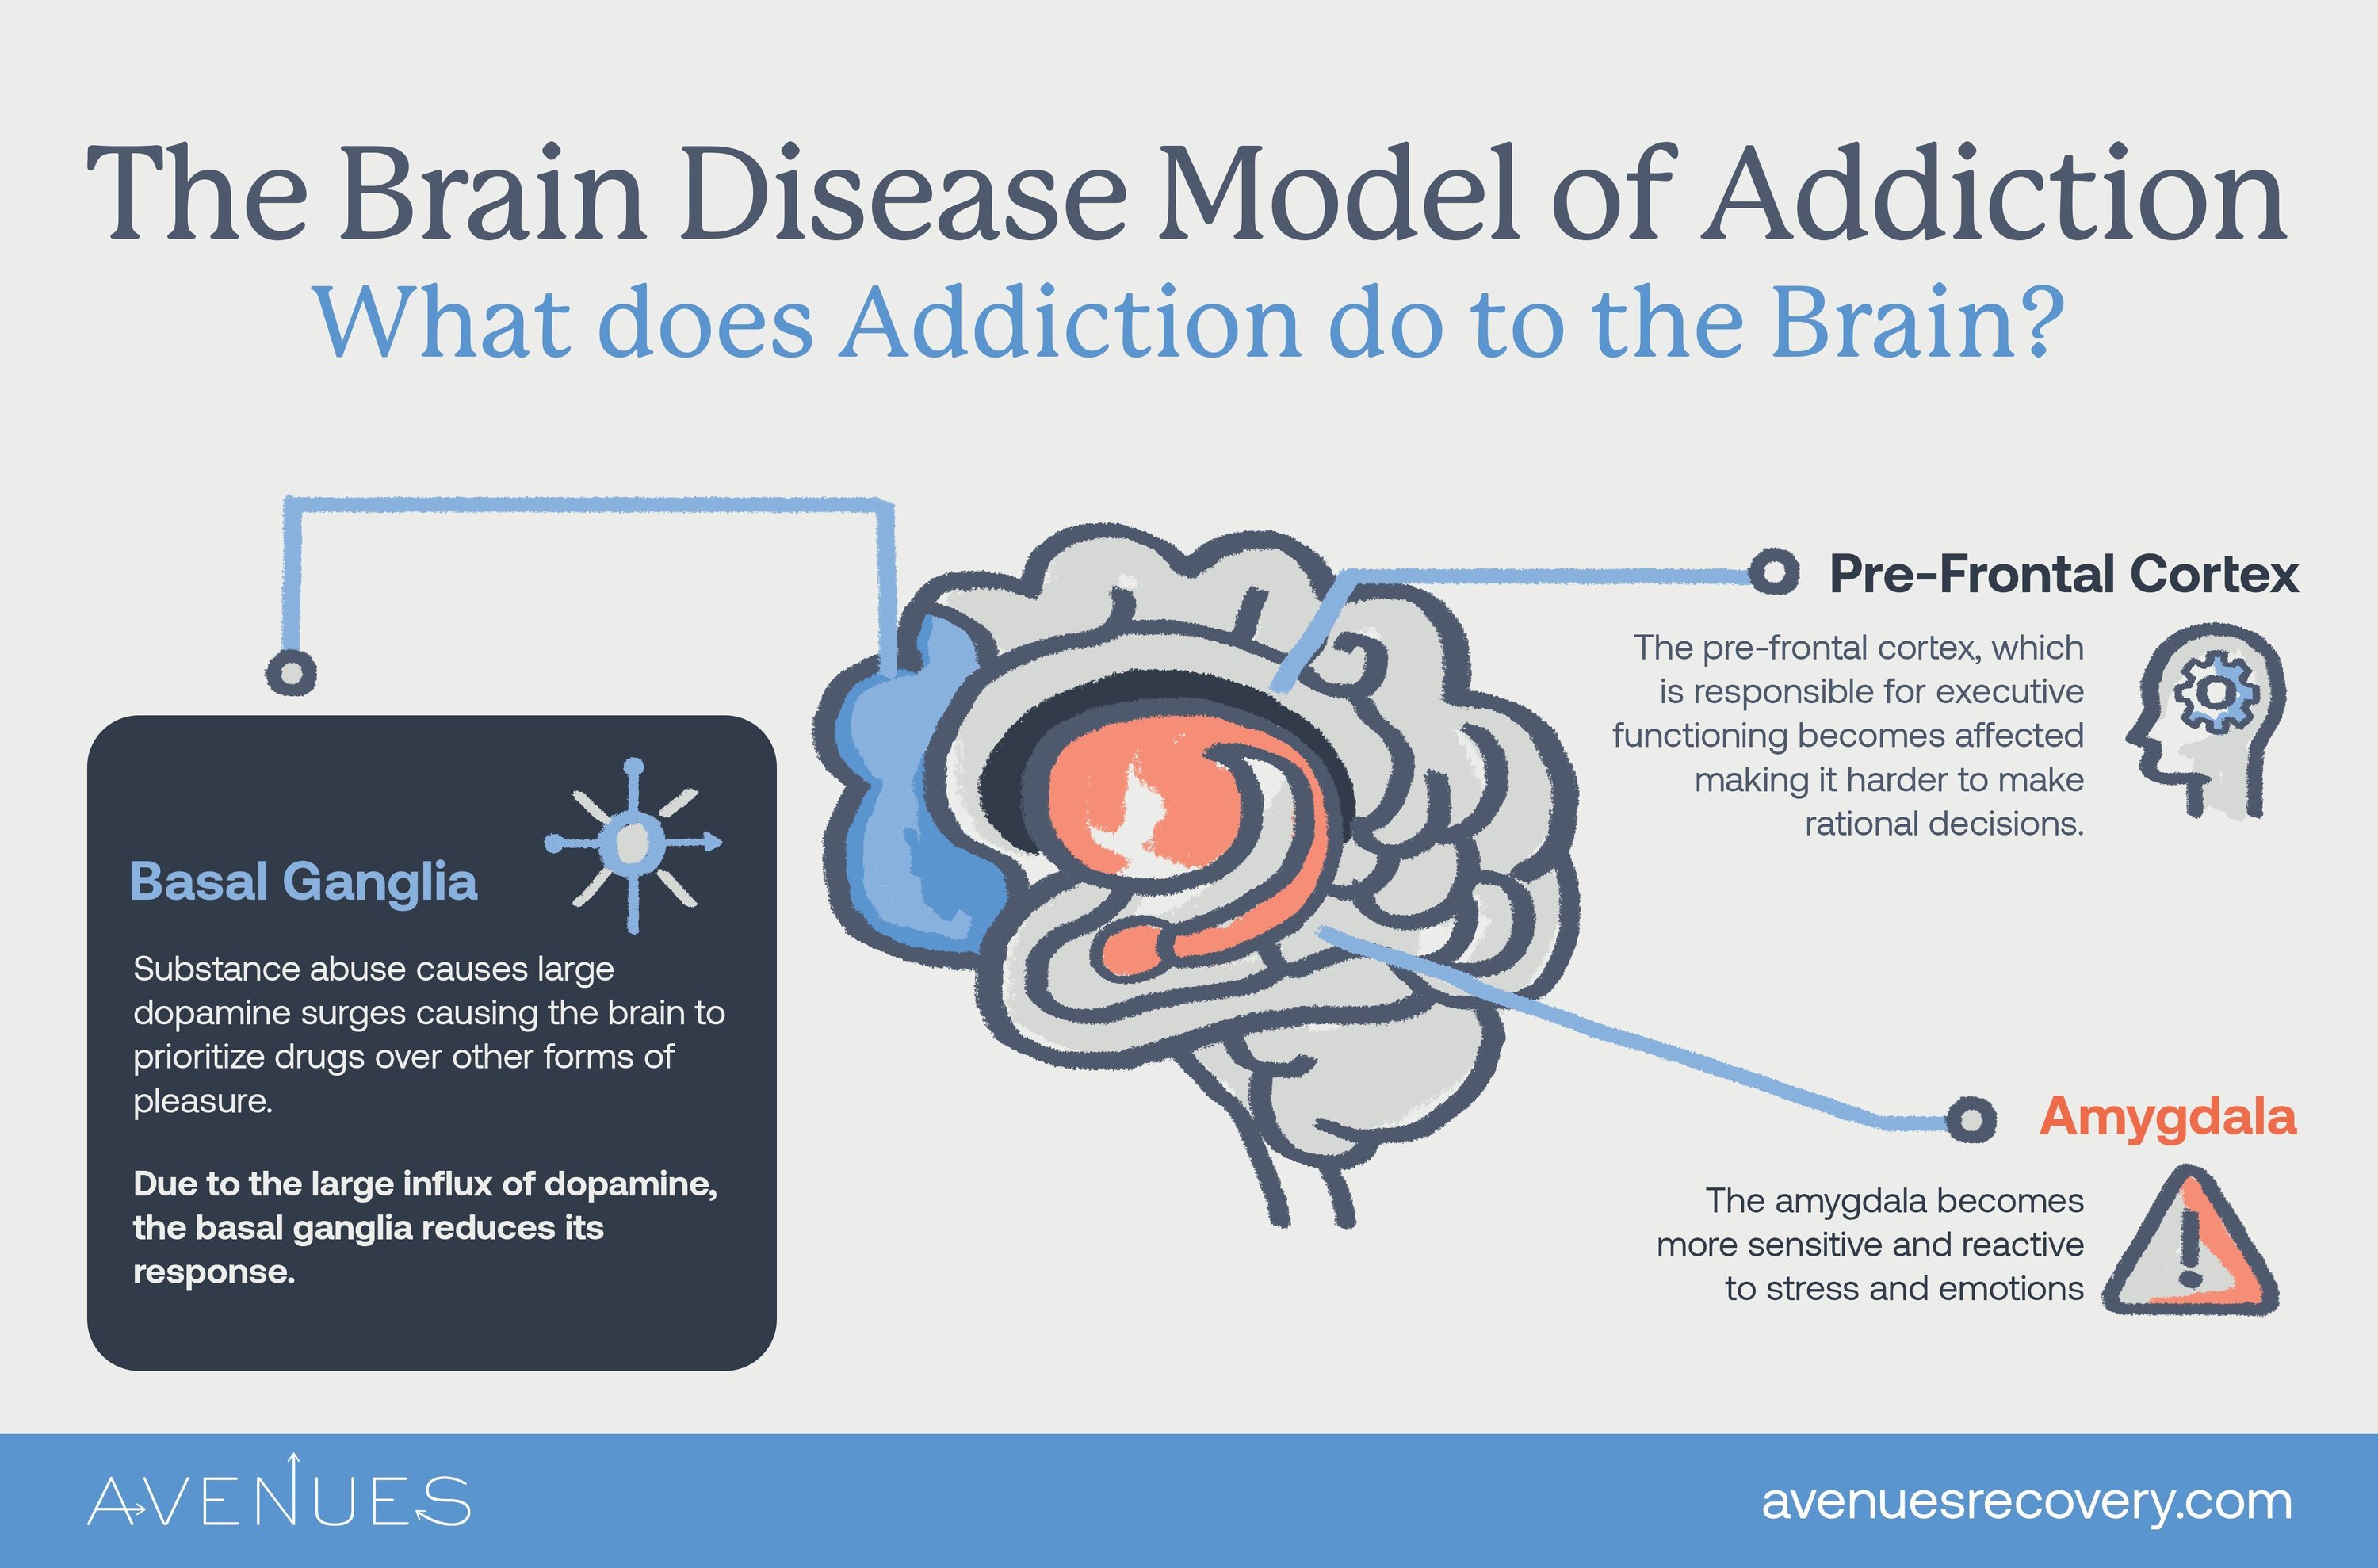
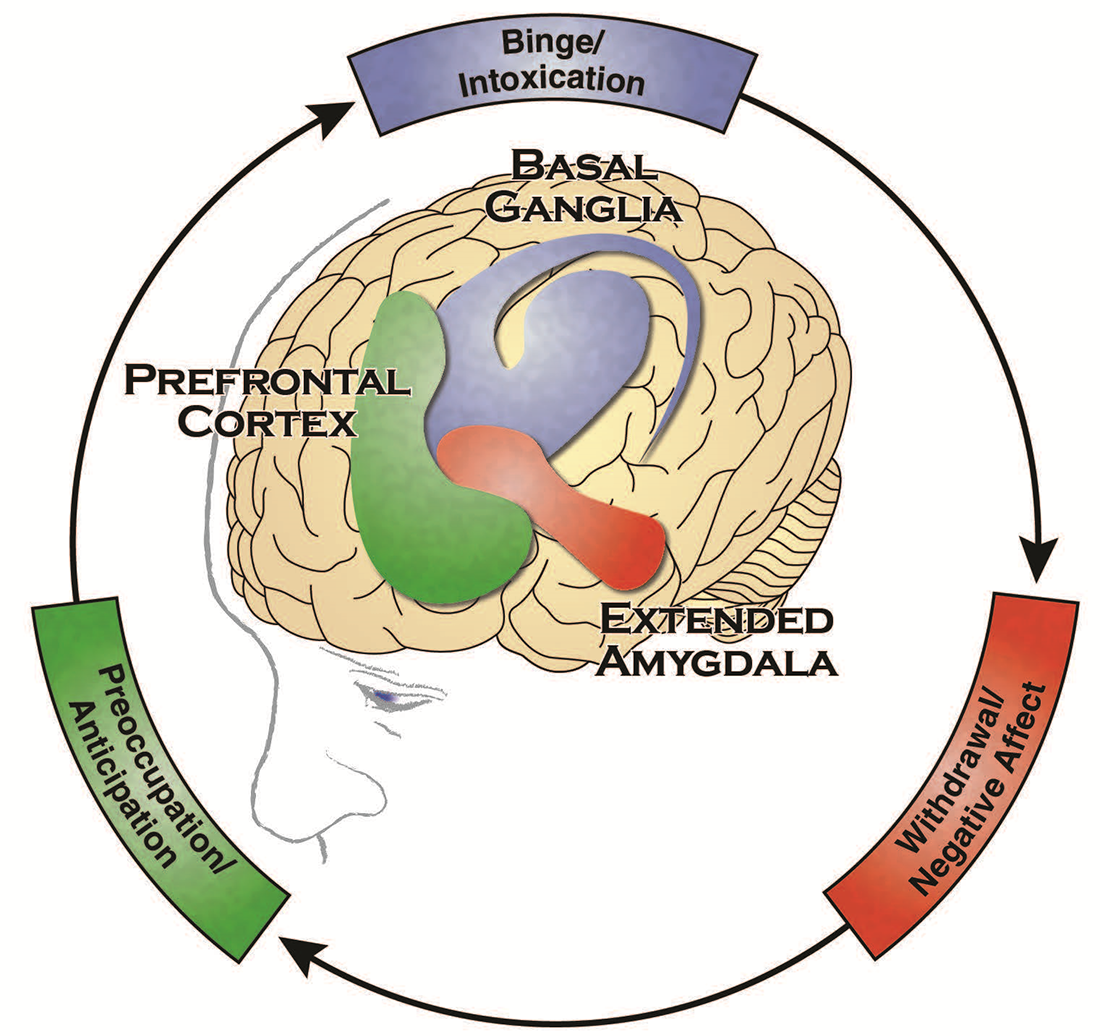
Most people think the disease model is a straightforward claim: addiction is a chronic brain disease, therefore treat it like one. The reality is messier. The model was originally framed by J. Wilson and the American Medical Association back in 1956, then refined through the 1980s and 1990s as neuroimaging caught up with clinical observation. It shifted addiction from a moral failure framework to a medical one, which opened doors for insurance coverage, evidence-based treatment protocols, and harm reduction programs that previously didn't exist. That shift matters. But it also created a lot of confusion about what the model actually predicts and where it falls apart. The core claim is that repeated substance use causes structural and functional changes in the brain, particularly in the prefrontal cortex and the mesolimbic dopamine pathway. These changes produce compulsive use despite negative consequences. The DSM-5 diagnostic criteria for substance use disorder rest heavily on this framework. I spent years watching people get labeled under those criteria and then finding out the labels didn't map cleanly onto what was actually happening in their lives.
The Problem With Treating Everything As A Chronic Disease
I ran into a case a few years back involving a patient who met full DSM-5 criteria for opioid use disorder, had a documented history of relapse, and was enrolled in a standard long-term recovery program based on the disease model. They stayed abstinent for eleven months, then had a single episode of misuse after a routine surgical procedure where oxycodone was prescribed. The program treated it as a full relapse and restarted the exact same protocol. That approach ignored the clinical reality: the triggering event was acute, medically indicated, and situational, not a return of a chronic baseline condition. The workaround was to reclassify the episode as a bordered lapse rather than a relapse event and shift the treatment plan toward a time-limited management protocol instead of indefinite chronic disease management. It made a practical difference. The patient remained stable for another three years without any further incidents. The disease model of addiction as a permanent lifelong condition didn't account for that scenario. It never was designed to. The model describes a pattern, not every possible exception to that pattern. This is where the model shows its most serious limitation. Chronic disease framing implies permanence and inevitability of progression. That implication is not well supported by longitudinal data. The National Epidemiologic Survey on Alcohol and Related Conditions (NESARC) and other large-scale studies have shown that a significant portion of people who meet criteria for substance use disorder at one point in time no longer meet those criteria years later without formal treatment. Spontaneous remission isn't rare. The disease model struggles to accommodate that finding without creating special exceptions, and those exceptions eventually erode the model's predictive value.
Another counter-intuitive detail most people miss: the disease model conflates correlation with causation in ways that matter clinically. Neuroimaging studies consistently show differences in the brains of people with substance use disorders compared to controls. But those differences are not always present before substance use begins, and they are not always consistent across substances or individuals. Some changes appear to be adaptive responses to repeated exposure rather than fixed pathological alterations. Treating adaptive changes as fixed disease markers leads to overtreatment in some cases and undertreatment in others, depending on how rigidly you apply the framework. There is also a financial and institutional dimension that the model creates but doesn't explicitly acknowledge. Insurance reimbursement, state funding allocations, and treatment facility certification standards all tie into disease model classification. When addiction is coded as a chronic medical condition, it unlocks certain payment structures and program categories that remain unavailable under alternative frameworks. This creates a real incentive to diagnose along disease model lines, even when the clinical picture is ambiguous. It is not conspiracy. It is just institutional economics operating within a system that rewards certain diagnostic choices over others. The most practical thing you can do with this model is understand its boundaries. It works well for explaining why stopping is difficult after prolonged heavy use. It explains the neurobiological mechanisms behind cravings and withdrawal reasonably accurately. It supports the case for pharmacological interventions like methadone, buprenorphine, and naltrexone in opioid use disorder. What it does not do well is predict individual trajectories, account for contextual and environmental factors that drive cessation, or justify the assumption that recovery requires indefinite management rather than time-limited intervention.
Get the Full Details
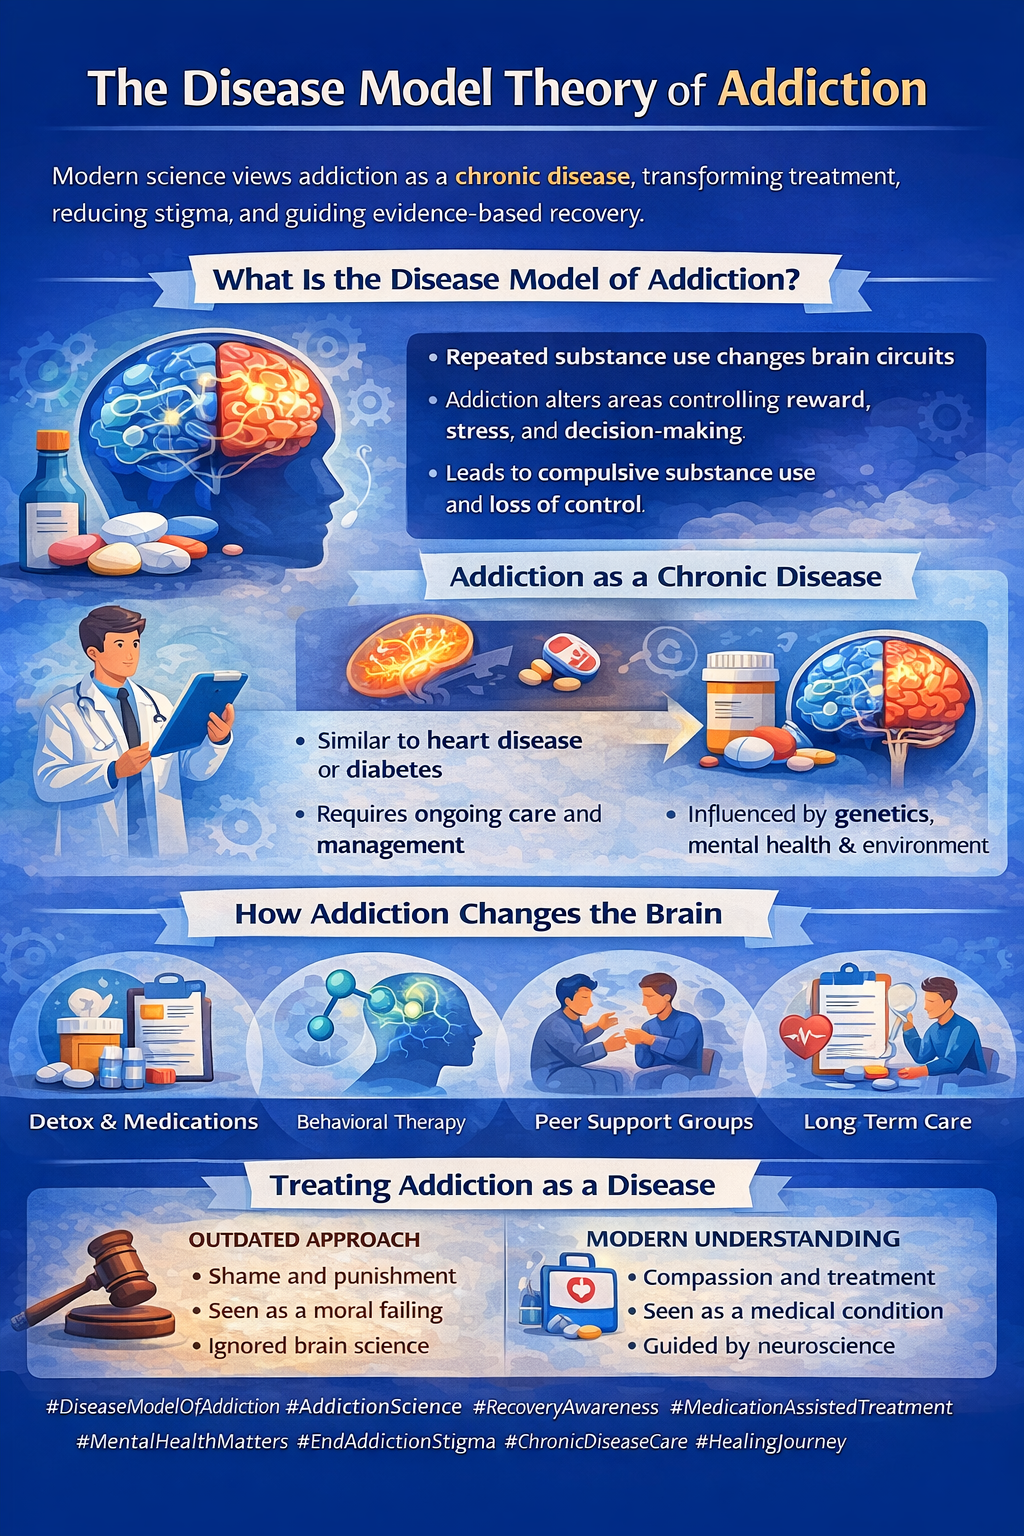
If you are working within a system that relies on the disease model, which most healthcare systems do, the best approach is to use it where it fits and supplement it with other frameworks where it does not. The biopsychosocial model covers more ground without claiming more than it can deliver. Behavioral therapies, motivational interviewing, and contingency management all operate with different assumptions about agency and change that the disease model alone cannot address. Using them together produces better outcomes than using any single framework in isolation.