How to Approach Disease Physiology When You Actually Need to Use It
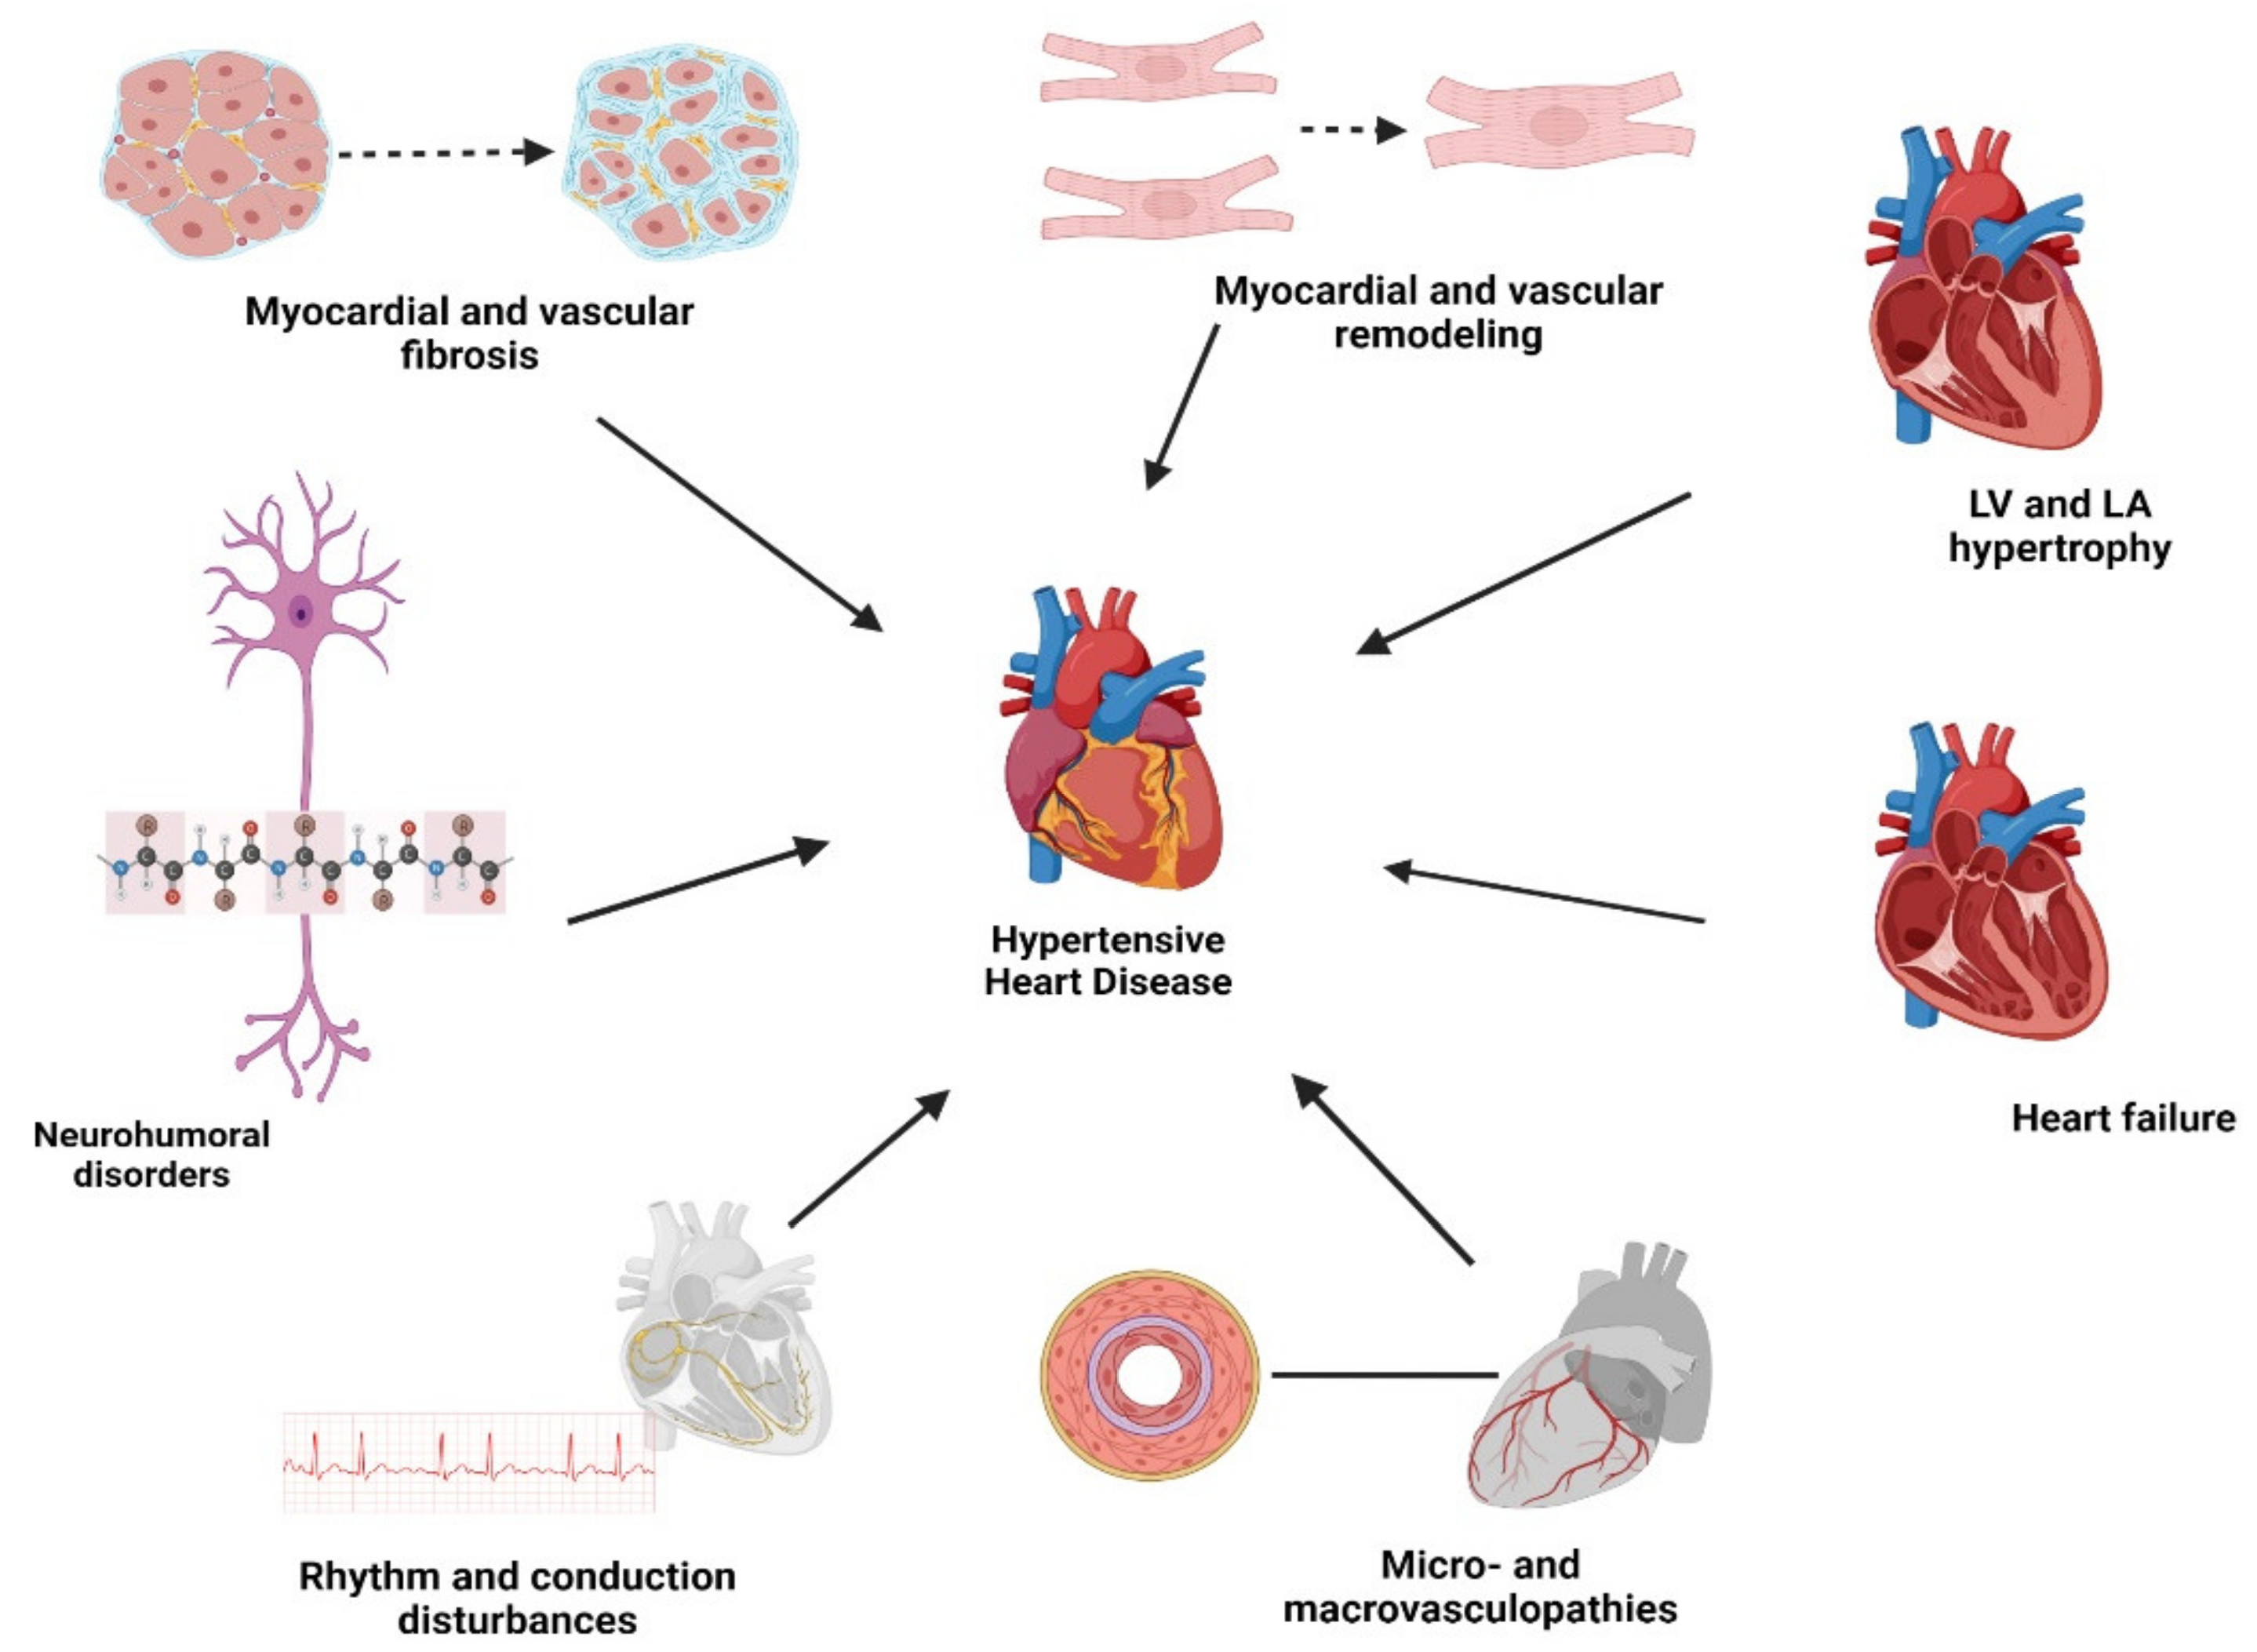
Disease Physiology is the study of how normal body functions go wrong during illness. Most students learn it by memorizing, which is why they can pass an exam and still not understand why a patient with cirrhosis has ascites. Here is how I was taught versus how it actually works in practice.The standard path in any textbook is definition first, mechanism second, clinical correlation last. I ran into problems with that order when I was reviewing for boards. I could list every step of the RAAS pathway backwards, but when a case asked about a patient on an ACE inhibitor who developed hyperkalemia, I froze. The mechanism was there in my head somewhere, but it was buried under layers of terminology. I stopped trying to memorize pathways linearly and started building them backward from the clinical presentation instead. Pick a disease. Any disease. Start with the end result you see in the patient and work backward to the molecular level. Take heart failure as an example. The patient presents with dyspnea and peripheral edema. That means fluid is accumulating somewhere it should not be. Why is fluid accumulating? Cardiac output has dropped, so perfusion pressure fell. The kidneys interpret low perfusion as hypovolemia and activate sympathetic tone and the renin-angiotensin-aldosterone system. Aldosterone holds onto sodium and water. The heart pumps against increased afterload. Over time, the heart remodels and dilates. Now you have a causal chain instead of a list of facts. The chain is what you need under pressure. I used to spend about three hours per disease trying to read through three chapters of a pathology text and make summary notes. That approach gave me maybe a B-minus on the exam and zero retention past the testing window. I switched to a different method entirely. I picked up a case-based question bank, found a relevant case, and worked through the physiology until I could explain every step out loud. It took roughly twenty minutes per disease, sometimes longer if the mechanism was tangled, but the retention was dramatically better. I could reconstruct the pathway from scratch without looking at any notes. The tradeoff is that this method requires you to already have a solid foundation in normal physiology. If you are shaky on basics like Starling forces or acid-base balance, you will get stuck before you even start building the disease pathway.
Where Most People Go Wrong
One thing nobody warns you about is that disease physiology is almost never a single linear pathway. The body compensates, and those compensatory mechanisms are often the source of new symptoms. Take diabetic ketoacidosis. The primary problem is insulin deficiency leading to hyperglycemia and ketone production. But the compensation—polyuria from osmotic diuresis—creates volume depletion, which triggers compensatory tachycardia and vasoconstriction. The treatment for the compensation (fluid resuscitation) is what actually saves the patient, not the insulin alone. Students who only learn the primary pathway miss half the clinical picture. They understand why the glucose is high but not why the patient is in shock. Another common trap is treating every disease as if it follows the same template. Sepsis physiology does not map cleanly onto nephrotic syndrome, even though both involve fluid shifts and edema. The Starling equation looks the same on paper, but in sepsis you have capillary leak from inflammatory mediators, while in nephrotic syndrome you have reduced oncotic pressure from protein loss. The treatment approaches are completely different. Confusing the two leads to wrong therapeutic decisions. I have seen this happen repeatedly in clinical rotations when residents apply a one-size-fits-all mental model to distinct pathophysiologic processes. There is also the issue of oversimplification in many textbooks. They present idealized pathways that work in animal models but behave differently in humans. The complement cascade is a good example. Textbooks describe it as a clean cascade leading to membrane attack complex formation. In human disease, regulatory proteins like CD55 and CD59 are constantly modulating the response, and genetic deficiencies in these regulators cause disease states like paroxysmal nocturnal hemoglobinuria. If you only learn the idealized version, you will not understand why certain diseases manifest the way they do. I had to spend extra time reading primary literature on complement regulation to fill in the gaps that standard textbooks left open.
A Practical Framework That Actually Works
Here is the system I use now, and it is the one I recommend to anyone who needs to internalize disease physiology rather than just recognize it on a multiple-choice exam. First, pick a disease entity. Second, write down the normal physiology baseline in one sentence. Third, identify the single point of disruption. Fourth, map every downstream consequence as a chain of cause and effect, stopping only when you reach something that does not affect the patient. Fifth, look at the treatment and reverse-engineer why each intervention works or fails based on where it sits in your chain. This takes approximately fifteen to thirty minutes per disease once you are practiced at it. Early on, when you are still building your base knowledge, expect it to take longer. The key is consistency. Doing this for ten diseases a week over a semester will give you substantially better physiological reasoning than reading fifty chapters cover to cover. The reason is that active reconstruction builds stronger neural connections than passive recognition. Your brain learns the logic, not the labels. The main limitation of this approach is that it requires access to good case material and the ability to distinguish well-established physiology from emerging or controversial mechanisms. Some newer disease models, particularly in immunology and oncology, are still being refined. If you commit too hard to a particular pathway version, you may find it outdated six months later. I got tripped up on the IL-6 signaling pathway in myasthenia gravis research a few years back because the literature was shifting toward JAK-STAT involvement. I had built an entire mental model around IL-6 that needed significant revision. The workaround was to treat intermediate resources like review articles as provisional and always check the original primary sources when the mechanism matters for clinical decision-making.
Get the Full Details

Another limitation is that this method is not efficient for diseases with highly variable presentations where the underlying physiology diverges significantly between patients. Chronic kidney disease, for instance, has so many etiologies and so much individual variation in progression that building a single causal chain is almost impossible. In those cases, you are better off learning the general principles of renal physiology and applying them flexibly rather than memorizing disease-specific pathways. No framework replaces understanding fundamentals, but a solid foundation makes this reverse-engineering method considerably faster and more reliable.
What It Feels Like When It Clicks
After a few weeks of doing this consistently, something shifts. You stop seeing disease as a collection of unrelated facts and start seeing it as broken normal function. A patient with hyperthyroidism is not just someone with weight loss and tremor. They are someone whose metabolic rate is running hot because thyroid hormone is driving Na+/K+ ATPase activity up across essentially every cell in their body. The weight loss, the tremor, the heat intolerance—all of it traces back to that single molecular mechanism. That connection is what makes disease physiology useful rather than merely examinable. I still use this approach occasionally when I need to understand a disease I have not worked with before. It is not a shortcut, but it is close to the most efficient path available. The alternative is spending months reading textbooks and hoping the patterns stick. That has never worked for me, and from what I have seen with other students, it rarely works for anyone.