Understanding Skin Disease Classification and Management
Most people entering dermatology or nursing programs get overwhelmed by the sheer volume of integumentary conditions they're expected to know. The skin is a large organ system, and it gets affected by things from autoimmune disorders to parasitic infestations. Here is how I approached learning and organizing this material when I was studying it, and what I wish someone had told me at the start.
Common Diseases For The Integumentary System: A Practical Overview
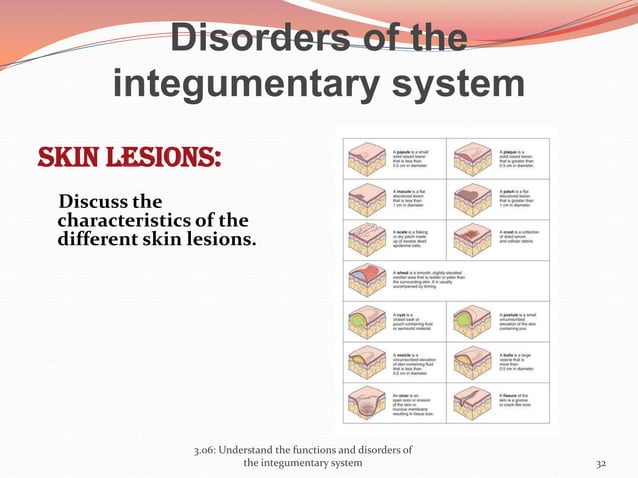
I started by grouping conditions by etiology rather than alphabetically. This made retention significantly easier. Bacterial infections like cellulitis and impetigo, fungal issues such as tinea corporis and onychomycosis, viral conditions including herpes zoster and molluscum contagiosum, inflammatory diseases like psoriasis and eczema, neoplastic growths ranging from benign seborrheic keratoses to malignant melanomas, and autoimmune conditions such as lupus erythematosus and pemphigus vulgaris. That structure stuck with me through board exams and into clinical practice.One thing nobody warns you about is that many integumentary diseases present with overlapping visual features. A lesion that looks like psoriasis could actually be mycosis fungoides, which is a type of cutaneous T-cell lymphoma. I learned this the hard way during a clinical rotation when a patient with a suspected recalcitrant plaque psoriasis flare was actually presenting with early-stage mycosis fungoides. The steroid cream was providing temporary anti-inflammatory relief that masked the underlying progression. We caught it because the attending ordered a skin biopsy after the lesions spread beyond the typical flexural distribution, and the histopathology showed Pautrier microabscesses. Without that biopsy, the disease would have been missed by months. This is why visual diagnosis alone is unreliable for persistent or atypical rashes.
Approach to Diagnosis and Workup
The diagnostic process starts with history, not the lesion itself. I always ask about duration, progression, symptom profile, systemic associations, medication history, and occupational or environmental exposures. A 45-year-old construction worker with a hyperkeratotic patch on the forearm has a completely different differential than a 22-year-old with the same appearance. Sun exposure history changes everything for actinic keratoses and non-melanoma skin cancers. When I needed a quick reference system for differential diagnosis, I used a combination of the ABCDE rule for pigmented lesions and the "Ugly Duckling" sign. The ABCDE criteria — asymmetry, border irregularity, color variation, diameter greater than six millimeters, and evolution — are standard but underutilized in their full form. Most people remember diameter but skip evolution, which is actually the single most predictive feature. The Ugly Duckling sign means any mole that looks clearly different from the patient's other nevi warrants excision or referral. I found this approach particularly useful during skin cancer screening rotations where lesion volume was high and time was limited. For infectious etiologies, potassium hydroxide preparation and fungal culture remain the gold standard for dermatophyte identification. Gram stain and bacterial culture apply for suspected pyoderma. Wood's lamp examination helps identify certain bacterial and fungal infections — Pseudomonas produces a greenish fluorescence, and erythrasma caused by Corynebacterium minutissimum shows coral-red fluorescence. It is not foolproof but it is fast and inexpensive in a clinical setting.
Get the Full Details
Treatment Frameworks by Category
Topical corticosteroid potency selection is where most trainees make errors. The skin thickness of the affected area directly determines which potency is appropriate. Using a Class I super-potent steroid like clobetasol propionate 0.05% on facial skin or intertriginous areas can cause rapid skin atrophy, telangiectasia, and steroid-induced rosacea within weeks. I recommend following the fingertip unit measurement system to avoid overtreatment. One fingertip unit covers approximately two adult palm-sized areas and is the standard dosing measure. For psoriasis, topical vitamin D analogs such as calcipotriene are first-line for mild to moderate disease and are often combined with mid-potency corticosteroids in fixed-dose combination products. This combination reduces the cumulative steroid exposure while maintaining efficacy. Systemic treatments like methotrexate, cyclosporine, and biologic agents targeting TNF-alpha, IL-17, and IL-23 pathways are reserved for moderate to severe cases. I found that patients often do not understand the difference between topical therapy, systemic therapy, and phototherapy, so explaining the mechanism and expected timeline for each was essential for adherence. Acne vulgaris management follows a stepwise approach based on severity. Comedonal acne responds to topical retinoids. Inflammatory acne adds topical or oral antibiotics. Severe nodulocystic acne may require isotretinoin, which has significant teratogenicity concerns and requires enrollment in a risk management program in the United States. I have seen patients restart isotretinoin multiple times because the initial course did not achieve complete clearance, which is not unusual — some patients require two or three cycles at different dosing schedules.
Pitfalls and Limitations
The biggest limitation in studying integumentary diseases is that textbooks present idealized images while clinical presentations are rarely textbook perfect. A patient with atopic dermatitis may not show the classic flexural distribution. A basal cell carcinoma might present as a non-healing erythematous patch rather than the pearly papule with telangiectasias. Relying solely on textbook imagery creates diagnostic inertia in real clinical settings. Another limitation is that many conditions respond initially to treatment but relapse. Chronic conditions like psoriasis and atopic dermatitis require long-term management strategies, not cure-oriented thinking. Patients who expect complete resolution after a treatment course become non-adherent when symptoms return, which is expected given the chronic nature of these conditions. For resources, I found the British Association of Dermatologists patient information leaflets to be among the most accurate and accessible references available. They are freely available online and are written by dermatologists who understand both the clinical and patient communication aspects of these conditions. Standard dermatology textbooks like Fitzpatrick's Dermatology and Bolognia's Dermatology provide comprehensive coverage but are dense reference works rather than practical guides. The CDC's dermatology section and the American Academy of Dermatology website offer updated clinical guidelines for many common conditions.
When dealing with actual clinical practice, consultation with a dermatologist for any lesion showing rapid change, unexplained pigmentation, or failure to respond to appropriate initial therapy is the standard of care. No amount of self-study replaces formal training and supervised clinical experience for diagnosis and treatment decisions.