Why Gastroenterology Feels Like Triage
Gastrointestinal diseases don't announce themselves with clean textbook presentations. They arrive as vague bloating, intermittent diarrhea, heartburn someone has learned to ignore, or a hemoglobin drop found on a routine blood draw. The workup depends on which clue actually leads somewhere. I've sat through enough colonoscopy reports and endoscopy videos to know that most of the diagnostic value comes from paying attention to patterns rather than chasing one dramatic finding. The first real step isn't ordering a panel of tests. It's narrowing the complaint into an anatomic or functional category. Is this upper GI or lower GI? Is there alarm behavior? Bleeding, unintended weight loss, nocturnal symptoms, family history of colorectal cancer or IBD, onset after age fifty. Those change the algorithm immediately. Without alarm features in someone under fifty, guidelines generally recommend starting with basic labs and a trial of targeted therapy rather than jumping straight to invasive procedures. That triage decision alone prevents a lot of unnecessary scope time and patient anxiety. I remember a case where a patient in his forties kept getting labeled as IBS-D despite a fairly standard workup. He'd been on antispasmodics, low-dose tricyclics, a bunch of dietary experiments. Nothing moved the needle. We went back and asked about the timing of his symptoms. The diarrhea wasn't truly random. It clustered about forty-five minutes after waking and after meals, with normal bowel habits in between. That pattern pointed away from IBS and toward something else entirely. We did a colonoscopy with random biopsies and found microscopic colitis. Standard colonoscopy looks normal in these cases. Without the biopsies you miss it completely. It's a classic pitfall. The workaround is making sure the pathologist knows to sample the right segments when the gross appearance doesn't explain the symptoms.
Common Conditions And What Actually Changes Management
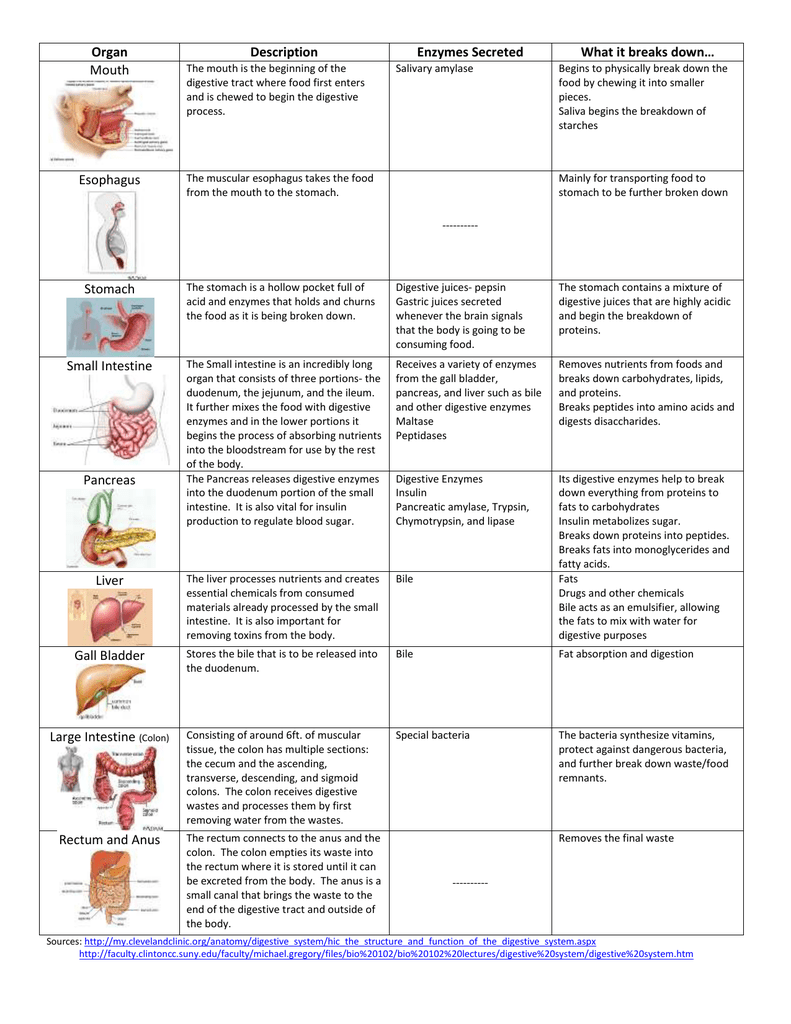
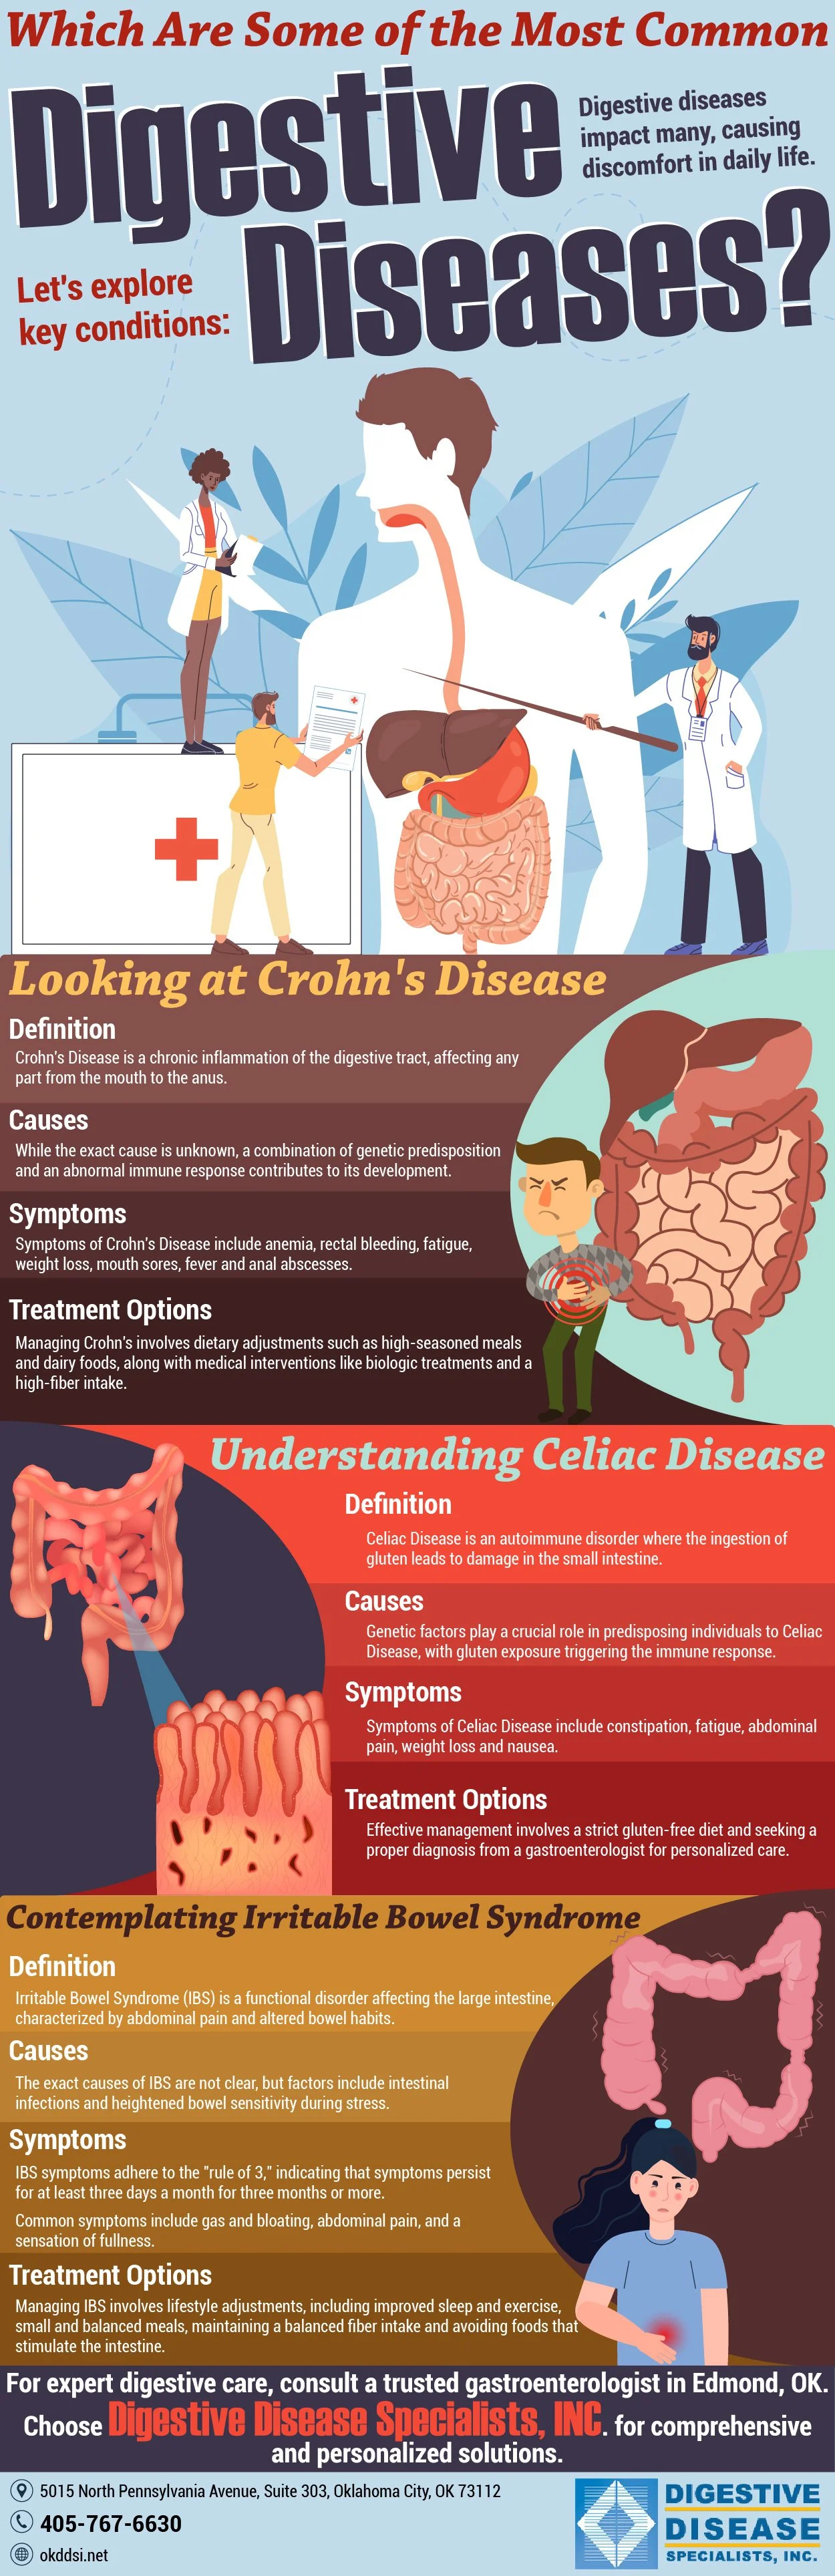
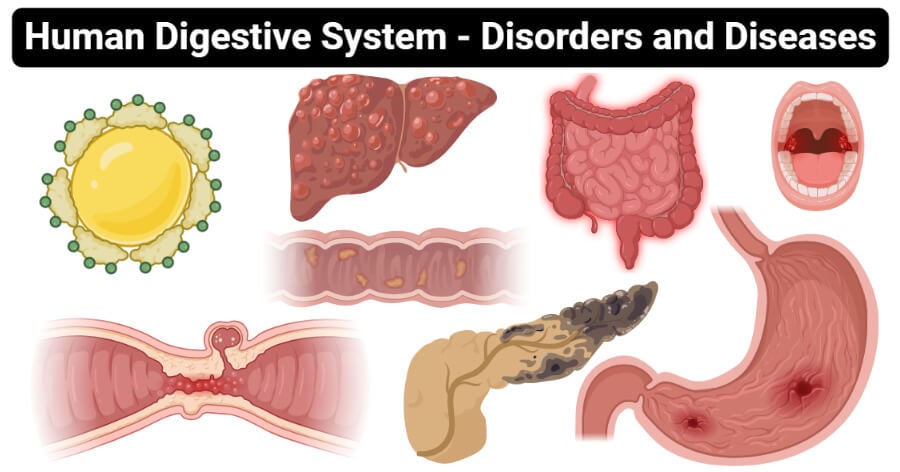
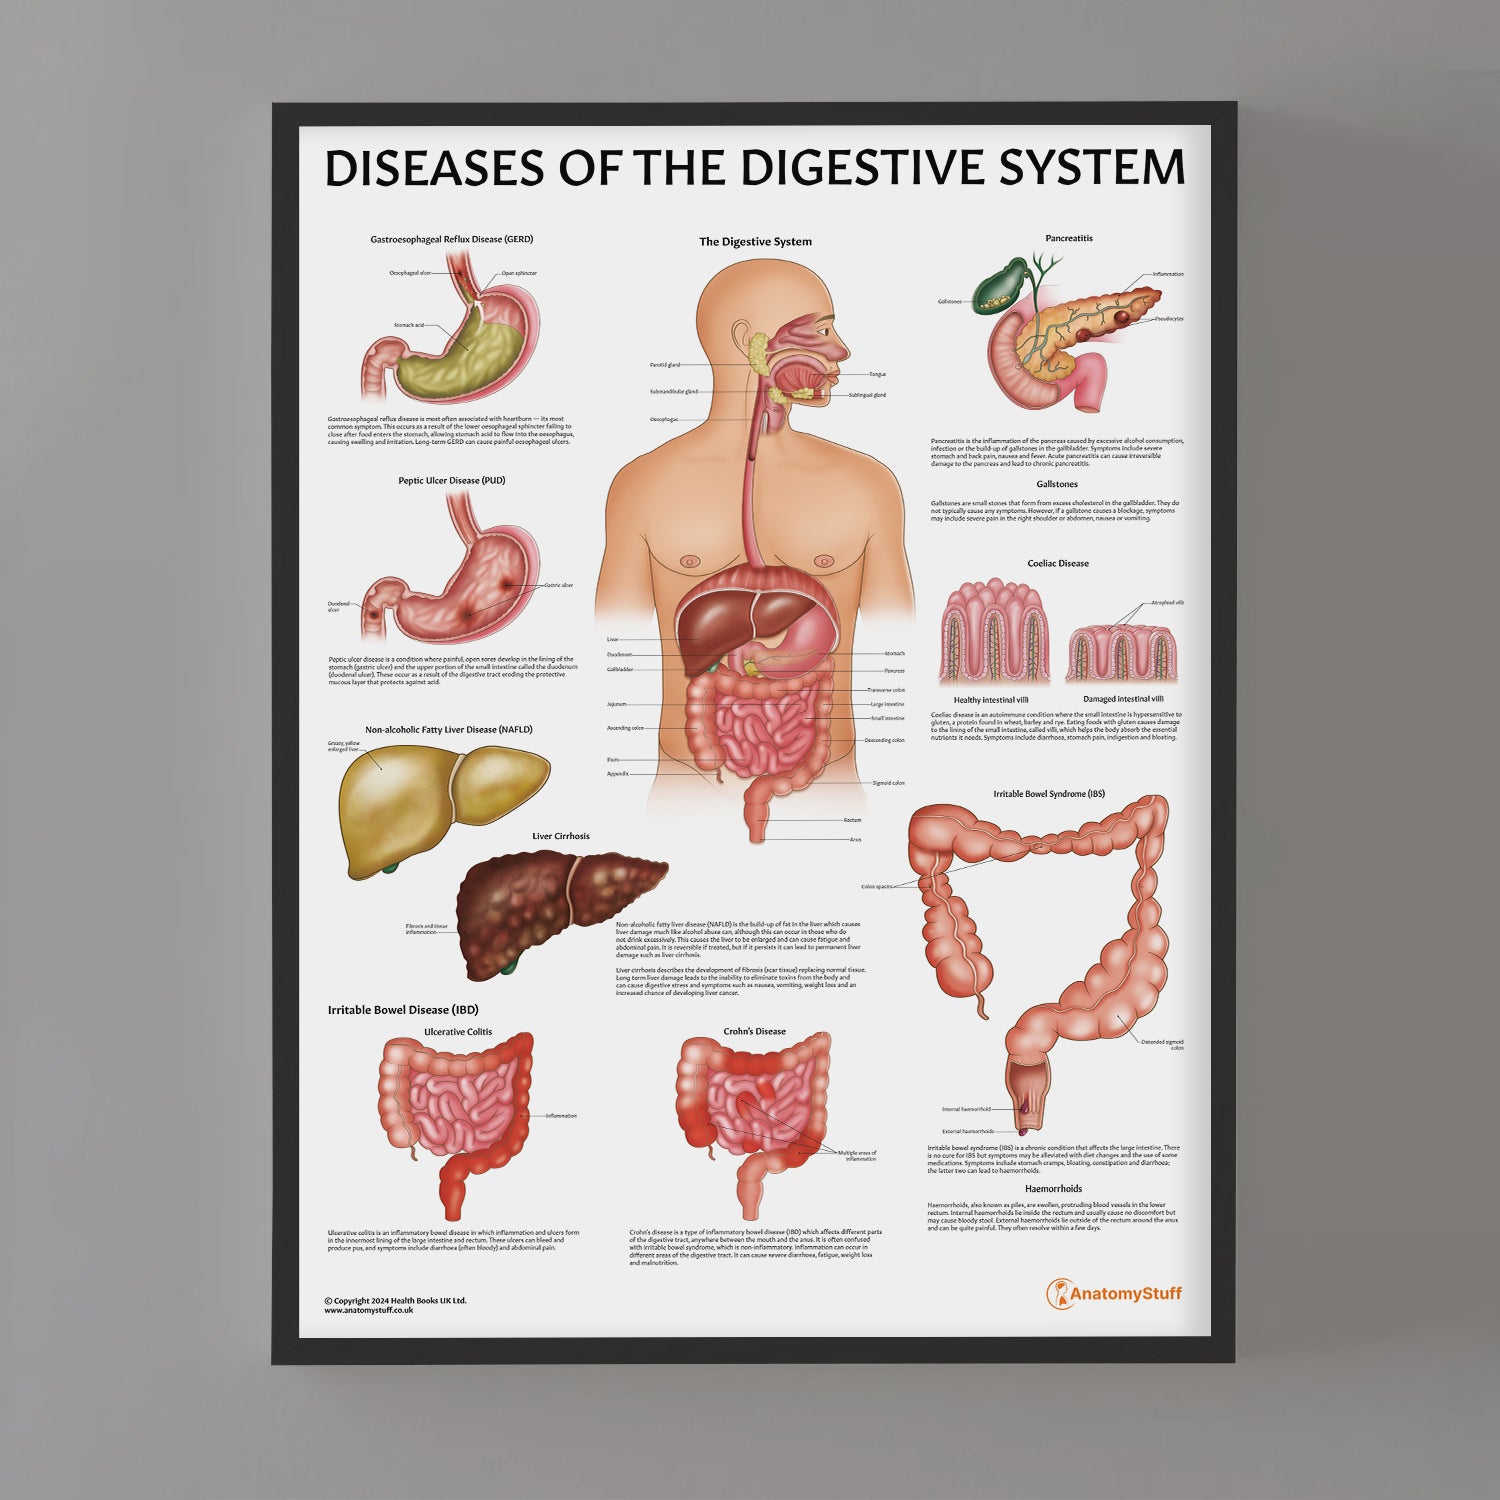
GERD and acid suppression are the bread and butter of GI practice, but the nuance is in who needs an endoscopy versus who can safely trial a PPI. Younger patients with typical reflux symptoms and no alarm features can usually get a four-to-eight week PPI trial first. If symptoms persist or return off medication, that's when you scope. The bigger concern long-term is that chronic PPI use has real downstream effects. We see hypomagnesemia, B12 deficiency, and a slightly increased risk of community-acquired pneumonia and C. difficile infection. The trick is to use the lowest effective dose and reassess every six months about whether the patient still needs it. Step-down to on-demand dosing or an H2 blocker works for a lot of people. H. pylori infection is another area where testing methodology matters more than most people realize. The stool antigen test and the urea breath test are both good for active infection, but they can't distinguish past from present exposure if you test too soon after treatment. A false negative after eradication therapy is common if you test within four weeks. You also have to make sure the patient isn't on a PPI, which suppresses bacterial load enough to cause a false negative on both tests. The recommendation is to stop PPIs for two weeks before testing and avoid antibiotics and bismuth for four weeks prior. Miss that window and you're wasting time and money. Inflammatory bowel disease diagnosis is where imaging and endoscopy converge. Crohn's and ulcerative colitis still account for the bulk of IBD cases. The distinction matters for treatment selection. Ulcerative colitis stays in the colon and involves continuous inflammation starting at the rectum. Crohn's can hit anywhere from mouth to anus and often shows skip lesions. When the presentation is ambiguous, capsule endoscopy and cross-sectional imaging like MR enterography fill in gaps that colonoscopy alone can't. I've seen patients misdiagnosed with UC who turned out to have right-sided Crohn's because the terminal ileum wasn't adequately visualized during initial colonoscopies. That changes everything about monitoring and medication choice.
Colorectal cancer screening has shifted. The starting age dropped to forty-five for average-risk patients in recent guideline updates. Fecal immunochemical testing annually, colonoscopy every ten years, or CT colonography every five years are the main options. The colonoscopy route finds and removes polyps before they become cancer, which is why it remains the gold standard despite the inconvenience. Non-polyp form lesions like serrated polyps are the ones that slip through intervals, which is part of why surveillance intervals vary based on what you find.
Get the Full Details

Pitfalls That Waste Time And Money
One of the most frustrating patterns I've seen is the endless SIBO testing cycle. Breath tests for small intestinal bacterial overgrowth have significant limitations. Hydrogen breath tests specifically can miss methanogen-overdominant cases since methane doesn't show up on standard hydrogen panels. The lactulose test also picks up colonic bacteria fermentation, not just small intestinal overgrowth, which creates false positives. I tend to rely more on clinical response to targeted antibiotic therapy in ambiguous cases rather than betting everything on a breath test result. Rifaximin for four weeks is both diagnostic and therapeutic when the presentation fits, and that's often more useful than a number from a test with variable sensitivity. Another underappreciated issue is NSAID-related enteropathy. People think of NSAIDs as stomach irritants, which they are, but they also cause diaphragm-like strictures and ulceration throughout the small bowel. Patients on chronic NSAIDs with unexplained iron deficiency anemia and negative upper and lower endoscopies should probably get small bowel imaging. Enteroscopy or capsule endoscopy catches lesions that standard scopes miss entirely. I had a patient on ibuprofen for chronic back pain whose hemoglobin hovered around nine despite oral iron. The source was small bowel ulcers. Stopping the NSAID and switching to a different pain strategy resolved the bleeding over a couple of months. Functional GI disorders deserve mention because they're diagnoses of exclusion and that distinction gets blurry. Rome IV criteria help standardize IBS diagnosis, but the overlap with other conditions is real. Bile acid malabsorption presents similarly to IBS-D. A trial of a bile acid sequestrant like cholestyramine can be both diagnostic and therapeutic. Lactose intolerance is common and easily missed when patients don't connect their symptoms to dairy. A two-week elimination followed by structured reintroduction is faster and cheaper than a hydrogen breath test for most primary care settings.
When To Refer And What Patients Should Bring
If you're seeing a gastroenterologist, bring a symptom diary. Not a vague description of "stomach issues." Actual dates, food intake, stool frequency and consistency using a Bristol Stool Chart if possible, any over-the-counter medications taken, and the timing of pain relative to meals. That information compresses hours of history-taking into minutes and often directs the workup toward the right answer faster. Insurance and gastroenterology practices both benefit from that level of detail. Red flags that should bypass watchful waiting and move straight to specialist evaluation: gastrointestinal bleeding in any form, progressive difficulty swallowing, persistent vomiting, unexplained weight loss above ten percent of body weight, a palpable abdominal mass, iron deficiency anemia in a postmenopausal woman or a man over fifty, and a first-degree relative with colorectal cancer or advanced adenomas. Family history changes screening timelines independently of personal symptoms. A parent or sibling with colorectal cancer before sixty warrants starting screening at age forty or ten years before the relative's diagnosis age, whichever comes first.
Key Takeaways For Managing Diseases Of The Gastrointestinal Tract
The gastrointestinal tract is large and its diseases overlap more than most summaries convey. A methodical approach that starts with symptom characterization, respects alarm features, and uses targeted testing rather than shotgun panels tends to produce better outcomes than aggressive early invasive workups for low-risk patients. At the same time, assuming everything is functional when organic pathology is hiding behind normal lab values is how conditions like microscopic colitis and small bowel Crohn's get delayed. The balance between observation and investigation is where clinical judgment matters most, and it's the same balance that determines whether a patient gets answers quickly or cycles through treatments that don't fit their actual problem.