Understanding UTIs From The Other Side Of The Desk
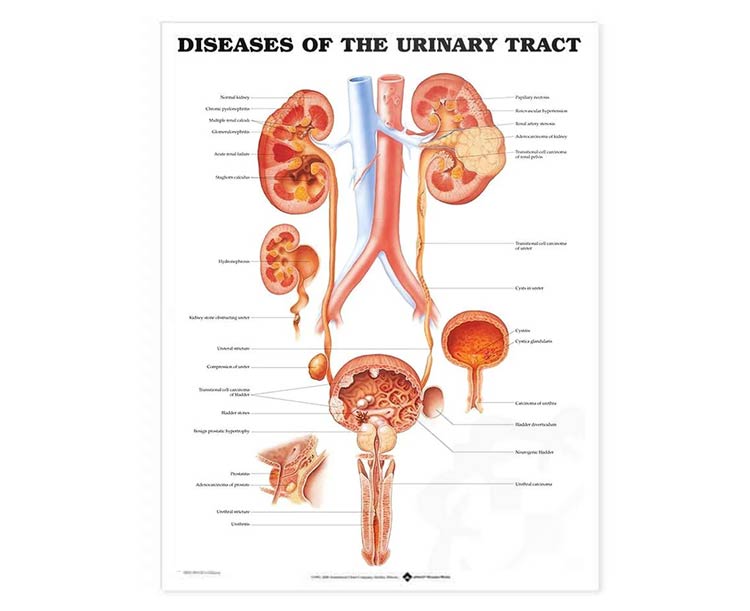
I spent years sitting through consultations where patients came in frustrated, confused, and in genuine pain. Urinary tract infections are the most common disease of the urinary system, and they are also the most poorly understood by the people dealing with them. Most of the time, the story repeats itself: burning, frequency, urgency, and then the slow march toward getting an antibiotic prescription. But the reality of treating Diseases Of The Urinary Tract System is more complicated than the standard protocol suggests, and it deserves a clearer look. The urinary system consists of kidneys, ureters, bladder, and urethra. Each part can be affected independently, and that matters enormously for diagnosis and treatment. A lower urinary tract infection involves the bladder and urethra, which accounts for roughly 80 to 85 percent of cases. Upper tract involvement means the infection has moved into the kidneys, and that shifts the entire clinical picture. Pyelonephritis is the medical term for kidney infection, and it carries a significantly higher risk of complications including sepsis, renal scarring, and hospitalization. E. coli is responsible for the majority of community-acquired UTIs, somewhere between 75 and 90 percent depending on the population studied. The remaining cases involve organisms like Klebsiella, Proteus, Enterococcus, and sometimes Staphylococcus saprophyticus, particularly in younger women. When you see recurrent infections, the first question should always be whether the initial organism was correctly identified and whether the full course of antibiotics was actually completed. I have seen too many cases where a culture was never sent, or where the pathogen was resistant to whatever empirical treatment was started.
Diagnosis That Actually Works
The standard approach is a urine dipstick followed by urinalysis and culture if indicated. The dipstick tests for leukocyte esterase and nitrites, which gives you a quick read on white blood cells and certain Gram-negative bacteria. But the dipstick is imperfect. It can miss infections caused by organisms that do not reduce nitrates, and it can produce false positives from contamination. A proper urinalysis with microscopy and a urine culture remains the gold standard for confirming the diagnosis and identifying the specific pathogen. Here is where beginners often make mistakes. They rely entirely on symptoms and skip the culture. Or they order a culture but interpret it incorrectly, treating asymptomatic bacteriuria as if it were a true infection. Asymptomatic bacteriuria is common, especially in elderly patients and those with catheters, and it should not be treated unless the patient is pregnant or undergoing a urologic procedure with mucosal bleeding. I learned this the hard way early in my career when I treated a elderly male patient for recurrent episodes that turned out to be chronic asymptomatic bacteriuria rather than symptomatic infection. The antibiotics were not helping him. Once we stopped treating the colony counts and focused on whether he actually had symptoms, the picture became much clearer.
Edge Cases And What Nobody Talks About Enough
One specific scenario I encountered involved a middle-aged woman who presented with what appeared to be recurrent cystitis. She had been prescribed multiple courses of trimethoprim-sulfamethoxazole and nitrofurantoin over several months with temporary relief each time, then recurrence within weeks. The standard protocol at the clinic was to extend the antibiotic prophylaxis, but something about the pattern did not sit right. The cultures consistently grew E. coli, but the timing and symptom profile suggested something beyond simple reinfection. I recommended imaging and a urology referral. A CT urogram revealed a small renal stone in the proximal ureter that was acting as a nidus for ongoing infection. No amount of antibiotics was going to resolve that. The stone had to be addressed surgically. Once it was removed, the recurrent infections stopped entirely. This is the kind of case that gets missed because the default assumption is always reinfection until proven otherwise, and that assumption is wrong far more often than clinicians like to admit. Structural abnormalities, stones, strictures, and incomplete bladder emptying should all be on the differential for recurrent UTIs, not just after multiple failures but earlier than many providers are comfortable going. Another underappreciated issue is biofilm formation on indwelling catheters. Catheter-associated UTIs account for roughly 75 percent of healthcare-associated infections in long-term care facilities. The bacteria adhere to the catheter surface and form biofilms that are essentially impenetrable by systemic antibiotics. Treating the infection without addressing the catheter is usually futile. The workaround is straightforward but often ignored: replace the catheter before starting antibiotics if one is in place, and remove it as soon as clinically feasible. I have lost track of the number of patients who received weeks of antibiotics through a contaminated catheter while the source was never removed. It is a systemic failure, not a knowledge gap.
Get the Full Details

Treatment Approaches And Where They Fall Short
For uncomplicated lower UTIs in otherwise healthy non-pregnant women, the first-line treatments are well established. Nitrofurantoin for five days, trimethoprim-sulfamethoxazole for three days if local resistance rates are below 20 percent, and fosfomycin as a single dose. These are effective in the majority of cases, and resistance patterns in your region should dictate your choice. If you are practicing in an area where E. coli resistance to trimethoprim-sulfamethoxazole exceeds 20 percent, using it empirically is no longer reasonable. Upper tract infections require a different approach. Oral fluoroquinolones like ciprofloxacin or levofloxacin for seven to fourteen days, or intravenous therapy with agents like ceftriaxone or piperacillin-tazobactam for patients who cannot tolerate oral medication or who appear septic. The treatment duration is longer because kidney tissue penetration and the severity of infection demand it. I have seen patients sent home with a three-day course of nitrofurantoin for suspected pyelonephritis. Nitrofurantoin does not achieve adequate tissue concentrations in the kidneys. It is a bladder-only drug, and using it for upper tract infections is a mistake that can lead to treatment failure and serious complications. There is a growing body of evidence supporting methenamine hippurate as a non-antibiotic prophylactic for recurrent UTIs. It works by converting to formaldehyde in acidic urine, creating an antimicrobial environment without contributing to antibiotic resistance. A randomized controlled trial published in the New England Journal of Medicine showed a significant reduction in recurrent UTIs among postmenopausal women taking methenamine compared to placebo. This is worth considering for patients who are facing repeated antibiotic courses, but it requires adequate renal function and acidic urine to work effectively. It will not help everyone, and it is not a substitute for addressing the underlying cause when one exists.
Prevention That Actually Has Evidence Behind It
D-mannose supplementation has gained popularity, and the evidence is mixed but promising for certain populations. A 2014 study found that D-mannose at a dose of 2 grams daily reduced recurrence rates comparably to low-dose prophylactic antibiotics in women with recurrent UTIs caused by adherent E. coli. The mechanism is specific: D-mannose prevents bacterial adhesion to the urothelium by binding to fimbriae on the bacterial surface. It does not work against all uropathogens, only those that use mannose-sensitive adhesins. For patients whose cultures consistently show these organisms, it is a reasonable option worth discussing. For others, it will likely do nothing. Cranberry products are another common recommendation, and the data does not support them as strongly as popular culture suggests. Multiple systematic reviews have found little to no benefit for cranberry in preventing UTIs. The active compound, proanthocyanidin, may inhibit adhesion in vitro, but the concentrations achieved in urine from commercial cranberry products are insufficient in most cases. If a patient wants to try it, low-dose standardized extracts are preferable to juice, which is typically high in sugar and unlikely to provide meaningful benefit. I do not recommend it routinely, but I also do not argue with patients who want to try it since the risk is low. Postcoital antibiotic prophylaxis is effective for women whose UTIs are clearly triggered by sexual activity, but it should not be the first line of defense for recurrent infections across the board. The targeted use of a single low-dose antibiotic taken after intercourse can reduce recurrence by about 96 percent in the right population, but it is a strategy that commits the patient to ongoing antibiotic exposure and should be reserved for clearly identified triggers. Behavioral modifications like hydration, voiding after intercourse, and avoiding spermicides are lower-yield interventions but carry no risk of resistance or side effects, so they are reasonable to recommend first.
When To Worry And When To Escalate
Most UTIs are straightforward. But certain presentations should raise immediate concern and prompt urgent evaluation. Fever above 38 degrees Celsius with flank pain and nausea or vomiting suggests pyelonephritis and possible systemic involvement. Hypotension, altered mental status, or tachycardia in an older adult with urinary symptoms may indicate sepsis. These patients need blood cultures, intravenous antibiotics, and possibly hospitalization. Outpatient management is inappropriate in these scenarios. Recurrent UTIs, defined as two or more infections in six months or three or more in twelve months, warrant a more thorough workup than repeated prescriptions. Imaging, urodynamic evaluation, and assessment for structural or functional abnormalities should be part of the workup, not an afterthought. I have seen this delayed for years in some practices because the assumption is that recurrent UTIs are just part of the patient's baseline. They are not. There is almost always a reason, and finding it changes the management entirely. Pregnancy changes everything. Asymptomatic bacteriuria in pregnant women should be screened and treated because the physiological changes of pregnancy increase the risk of progression to pyelonephritis by up to 30 percent. Untreated, this can lead to preterm labor and low birth weight. The screening is a simple urine culture at the first prenatal visit, and treatment follows standard guidelines adjusted for pregnancy safety. Nitrofurantoin and cephalexin are commonly used, while fluoroquinolones and tetracyclines are contraindicated.
The Resistance Problem And Why It Matters Clinically
Antibiotic resistance in uropathogens has been increasing steadily for decades. E. coli resistance to fluoroquinolones now exceeds 20 percent in many regions, and extended-spectrum beta-lactamase-producing organisms are becoming increasingly common in both community and healthcare settings. This is not abstract. It means that empirical treatment choices that worked fifteen years ago are often ineffective today, and clinicians need to be aware of local resistance patterns or they will fail their patients. The push for antibiotic stewardship is legitimate, but it should not be interpreted as withholding treatment from patients who need it. The balance between appropriate use and clinical necessity is delicate, and the consequences of overtreatment are real but so are the consequences of undertreatment. A poorly treated UTI that progresses to pyelonephritis or sepsis is far more costly, in both human and economic terms, than a appropriately targeted short course of antibiotics. Culture-guided therapy whenever possible is the standard that should be followed, not as an ideal but as routine practice. The urinary tract system is well designed for defense. Normal voiding mechanically clears organisms, urine acidity inhibits bacterial growth, and the urothelium produces antimicrobial peptides. Disease occurs when these defenses are compromised, whether by anatomy, behavior, instrumentation, or microbial virulence. Understanding which factor is at play in any given patient is the difference between managing a single episode and solving a recurring problem. The Diseases Of The Urinary Tract System are not mysterious, but they are not simple either, and treating them requires attention to detail that goes beyond the standard algorithm.