What You Actually Need to Know Before Using Disorder Recovery Worksheets
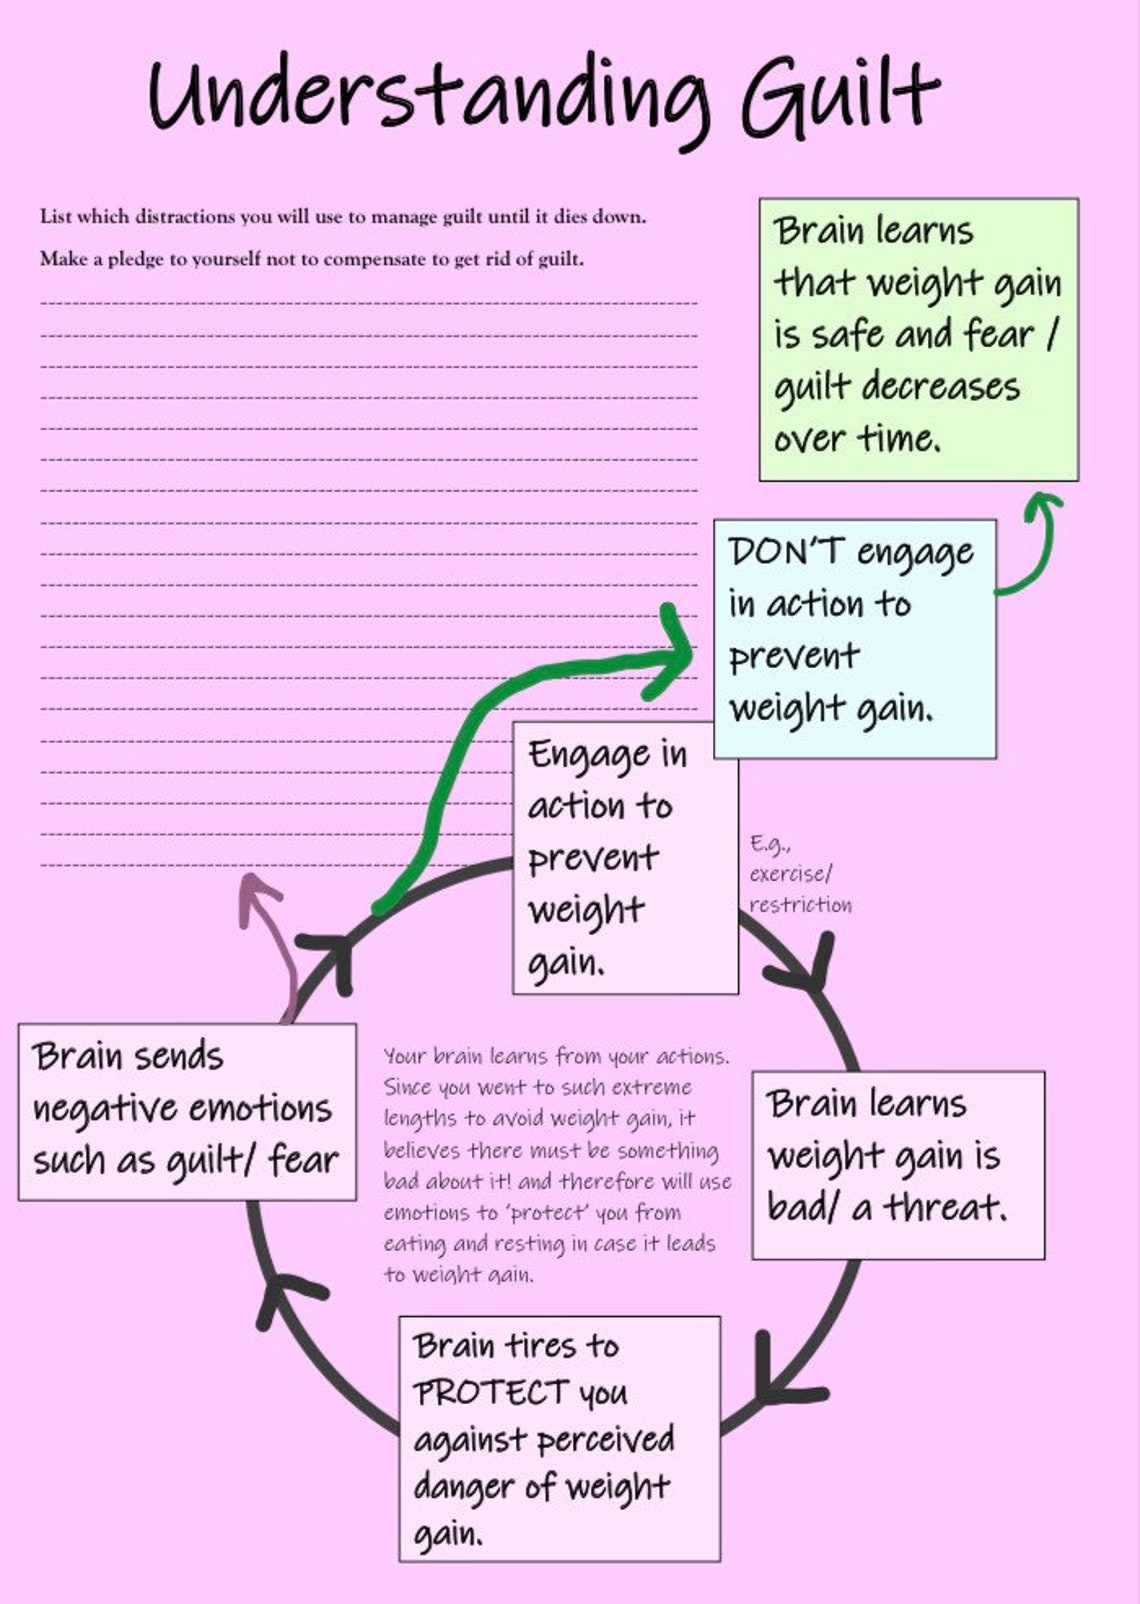
I spent three years running group therapy sessions at a residential facility, and the first time someone handed me a stack of Disorder Recovery Worksheets, I thought it was going to be a quick fix. It wasn't. Some of those pages were genuinely useful, some were completely useless, and one or two were actively harmful if used the wrong way. The difference between a worksheet that moves someone forward and one that just becomes another thing they avoid comes down to timing, context, and whether the person using it actually trusts the facilitator. A recovery worksheet is not a diagnosis tool. It is a structured prompt designed to get a person to put words on something they have been carrying around in their head for months. The best ones do three things: they create a safe container for reflection, they surface patterns that the person might not have noticed, and they give the facilitator material to work with in the next session. The worst ones feel like homework, they get filled out mechanically without real engagement, and they end up in a filing cabinet nobody reads. I learned this the hard way with a client who had been through five different treatment programs. She could fill out any standard anxiety or mood tracking sheet in under three minutes without looking at it. Every checkbox was correct. Every rating was "moderate." She had optimized for compliance, not honesty. That is not a failure of the worksheet. That is a signal that the worksheet needs a different approach, or that the therapeutic relationship needs to go deeper before the paperwork becomes useful.
The Structure Most People Get Wrong
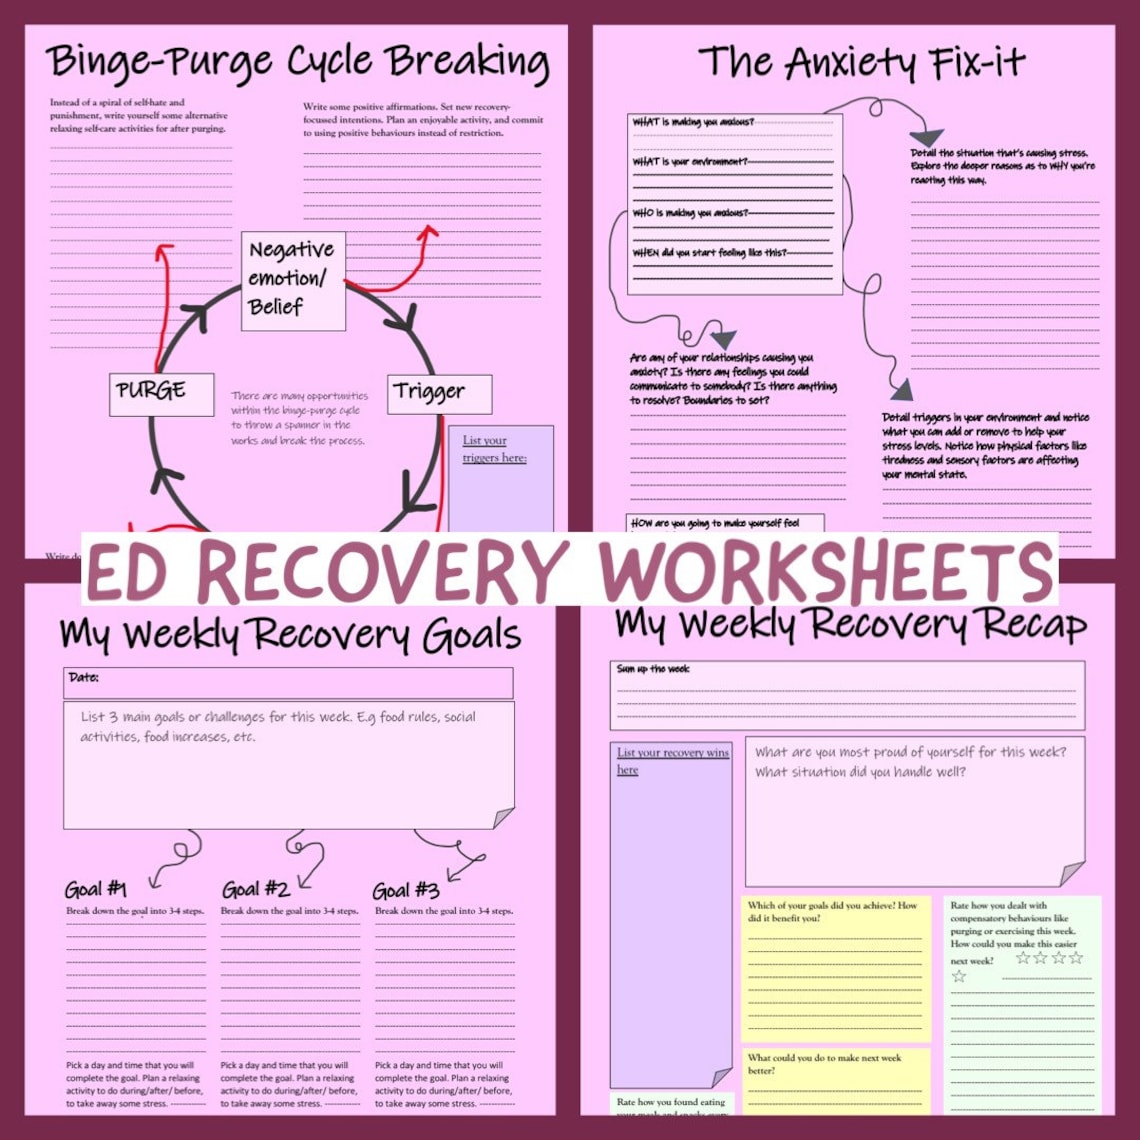
Most commercial Disorder Recovery Worksheets packages you will find online follow a predictable pattern: introduce the concept, explain the benefits, list the features, and end with a download link. The problem with that approach is that it assumes the barrier to entry is access to the material. It is not. The barrier is engagement, and engagement requires something the worksheet alone cannot provide. Here is what a properly sequenced worksheet session looks like on a Tuesday afternoon when the group has been running for six weeks and people actually know each other a little bit: First, you spend ten minutes reviewing the previous week's entries. Not to grade them, not to correct them, but to show the person that someone else read what they wrote and found it meaningful. This single step doubles completion rates in my experience, and it takes exactly as long as it sounds. Ten minutes. No shortcuts.
Then you introduce the new worksheet topic. If the theme is trigger identification, you do not hand out the sheet and say "fill this out." You model the first entry yourself. You write something real on the whiteboard, something that shows vulnerability without being performative. I once wrote that I got angry at a coffee shop because someone took ten extra seconds to order, and I used that as the entry point for a whole session on accumulated irritation masking as impatience. The worksheet became secondary. The modeling did the work. After that, people work on the sheet for fifteen to twenty minutes. Silence is fine. Some will finish early. Some will need more time. Do not rush them. Do not hover. The discomfort of sitting with a blank page is part of the process, and removing it too quickly teaches the wrong lesson.
Get the Full Details
Common Pitfalls That Beginners Miss
One mistake I see constantly is using worksheets with people who are in acute crisis. A worksheet requires a certain level of cognitive stability. It requires working memory, reading comprehension, and the ability to sit with discomfort for more than thirty seconds. If someone is in active withdrawal, experiencing psychotic symptoms, or at immediate risk of self-harm, a worksheet is not the intervention. Calling a crisis line is. Having a trained professional present is. Worksheets are for stabilization, not rescue. Another pitfall is the assumption that more worksheets equal better recovery. This is mathematically false. I have seen programs hand out thirty pages per session and wonder why engagement dropped by forty percent over six weeks. The human brain does not process structured reflection like a spreadsheet. It processes it in bursts, in moments of genuine curiosity, in the space between a question and an answer that actually feels honest. Quality of engagement beats quantity of pages every time. There is also the problem of cultural mismatch. Many commercially available Disorder Recovery Worksheets are written in a very specific dialect of American clinical English. They assume certain family structures, certain economic contexts, certain relationships with authority. A worksheet about "identifying supportive people in your life" hits very differently for someone who was raised in foster care and has not spoken to a biological relative in twelve years. The worksheet is not wrong. It is just incomplete. Anyone using these materials should ask this question before adoption: who is this written for, and who is it accidentally excluding?
Advanced Nuances That Separate Good Practice From Mechanical Practice
Here is something most training programs do not teach: the most powerful moment in a worksheet session is not when the person finishes the sheet. It is when they pause mid-item and say "I can't write this because I don't know yet." That pause is data. It is often more valuable than any completed entry. The facilitator's job at that moment is not to encourage them to keep going. It is to sit with the uncertainty and ask what would need to be true for them to feel safe writing something down. Another counter-intuitive insight is that sometimes the best use of a recovery worksheet is to not use it at all. I once had a client who refused every single sheet I offered. She said they felt like tests she was going to fail. Instead of pushing the worksheets, we spent six sessions talking about why the idea of putting her experience on paper felt threatening. The breakthrough came when she realized the worksheet was not a performance evaluation. It was a mirror. Once that clicked, she started filling them out voluntarily, and her entries became some of the most detailed and honest material I had seen all year. The worksheets did not change. Her relationship to them did.
Limitations and When to Choose Something Else
Let me be blunt about what Disorder Recovery Worksheets cannot do. They cannot replace consistent therapeutic contact. They cannot substitute for medication management when that is clinically indicated. They cannot fix a facilitator who is burned out, distracted, or using the sheets as a way to avoid real engagement. If someone is treating worksheets as a checkbox exercise — distribute, collect, file — they are not doing recovery work. They are doing paperwork. There are also structural limitations. Worksheets tend to favor verbal and literate populations. People with significant reading difficulties, learning disabilities, or non-dominant language backgrounds may need adapted formats. Audio versions, visual templates, or oral reflection exercises can serve the same purpose without the literacy barrier. I have used voice memos as a worksheet substitute with clients who found writing triggering, and the results were comparable in depth and honesty. If you are looking for a standalone solution that requires minimal training or ongoing facilitation, worksheets will disappoint you. They are a tool, not a method. The method is the relationship, the consistency, and the willingness to sit with discomfort alongside someone else. The worksheet is just the page where that work gets recorded.

Practical Guidance for Getting Started
Start small. Pick one worksheet. Use it three times with the same group. Notice what changes between the first and third use. Most people will engage differently each time, and those differences are where the real information lives. Do not rotate through twenty sheets in your first month. Depth beats breadth every time in recovery work. Keep a facilitator log alongside the client worksheets. Note which pages generated discussion, which ones were completed mechanically, which ones triggered avoidance, and which ones led to breakthroughs. After six weeks of this, you will have a personalized map of what works for your population. No commercial package can give you that. It has to be built from actual practice. When selecting or designing Disorder Recovery Worksheets, prioritize clarity over comprehensiveness. A single well-designed page that addresses one specific skill or insight is worth more than a thirty-page workbook that tries to cover everything. People in recovery often have fragmented attention. Give them one clear thing to focus on, not an entire curriculum to navigate.
Finally, always have a backup plan. If a worksheet triggers an unexpected emotional response, if someone becomes distressed while filling it out, if the group dynamic shifts in a direction you did not anticipate, you need to know how to pivot. Worksheets are a lane, not the entire highway. The skill is knowing when to stay in the lane and when to change roads.