Understanding the Nervous System When You're Actually Dealing With It
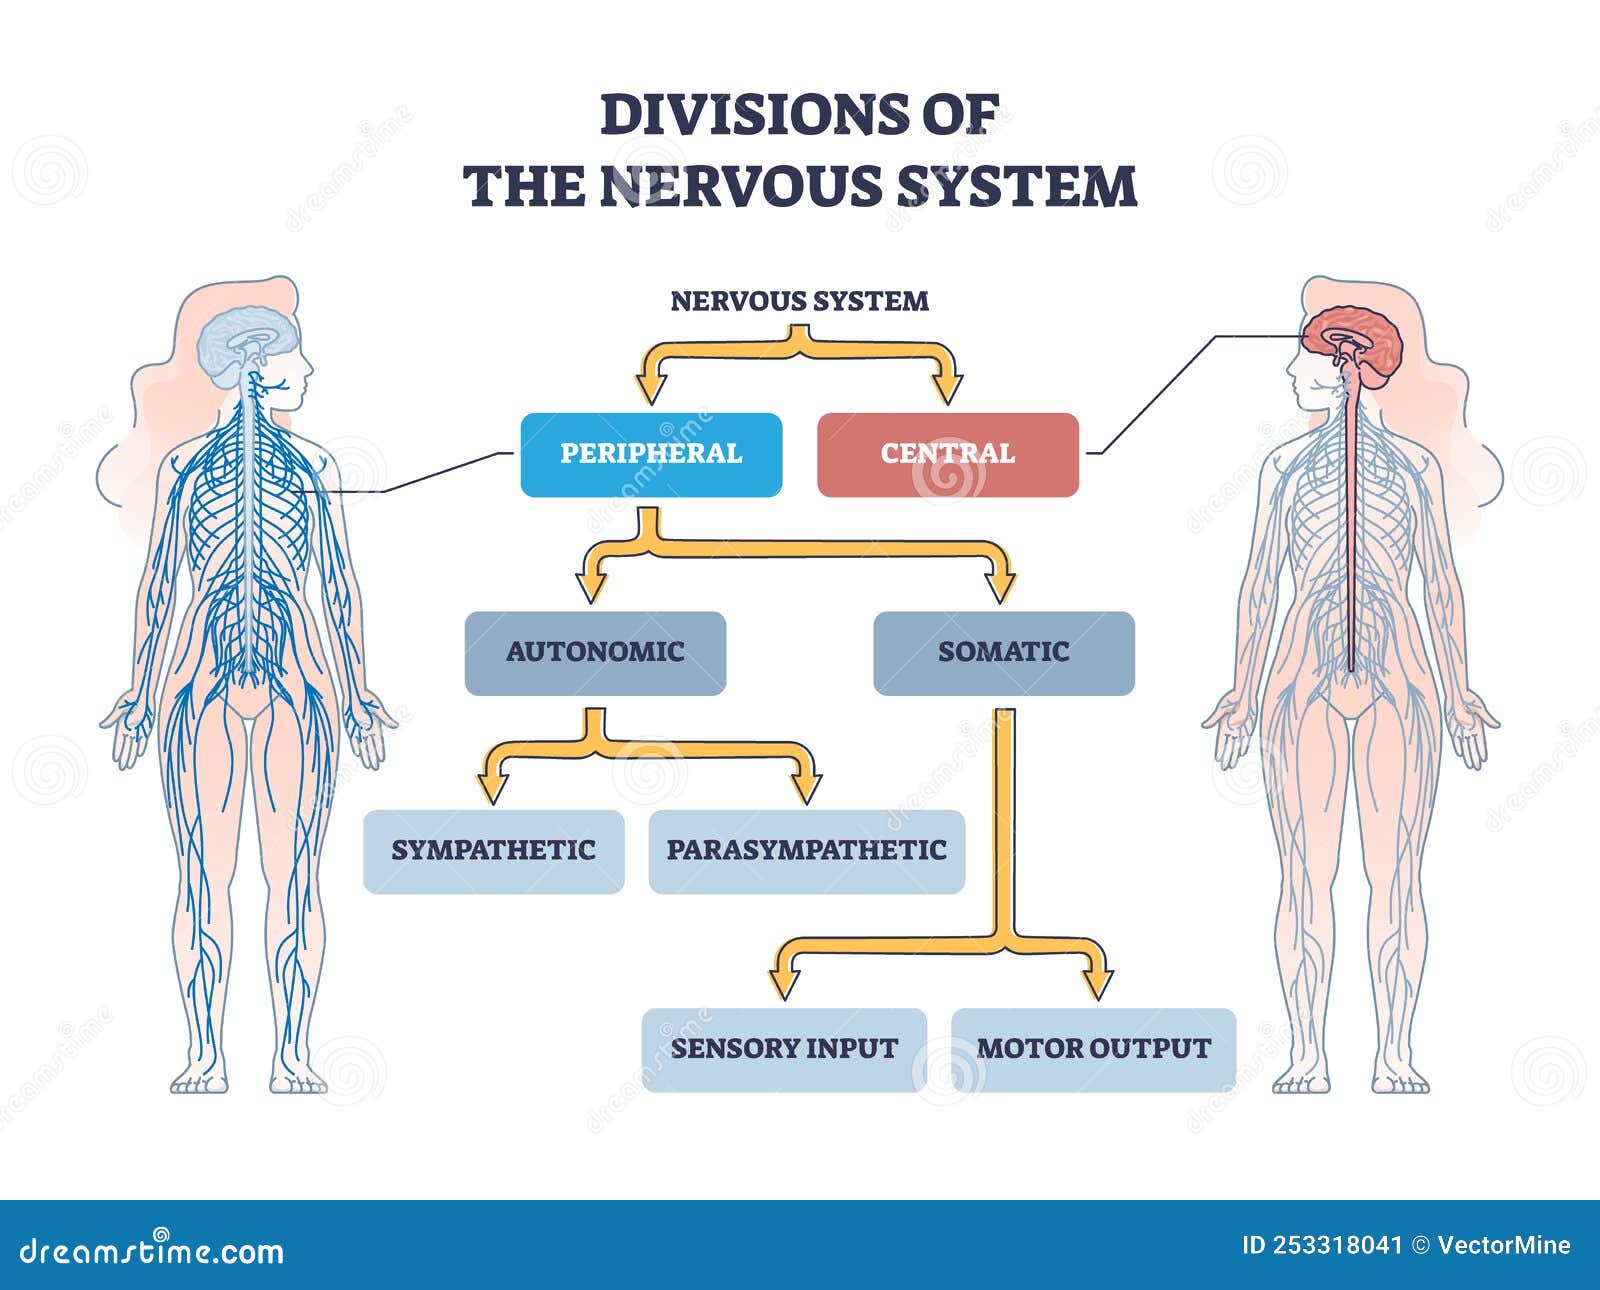
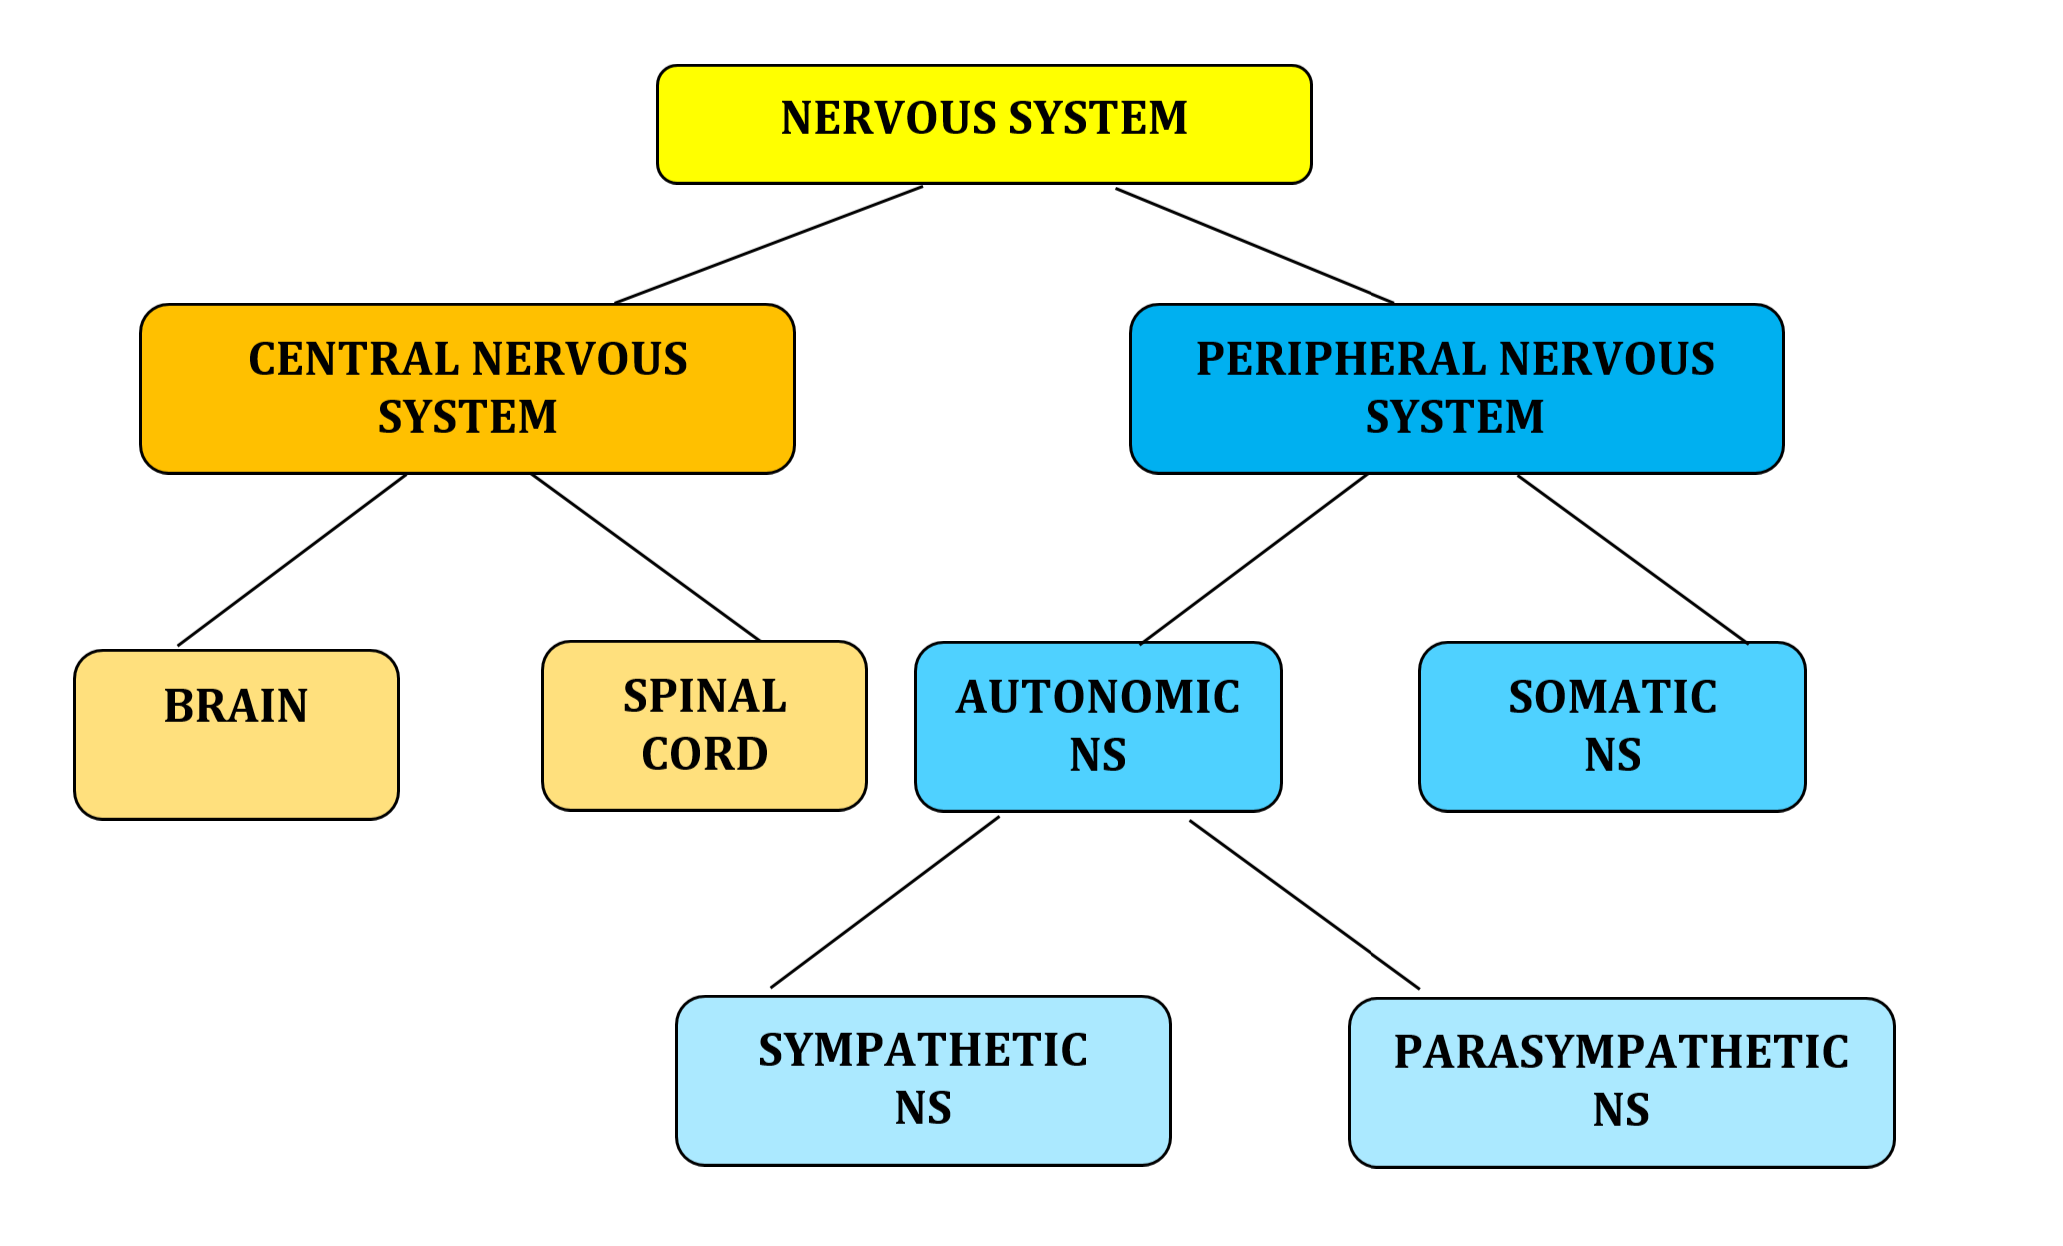
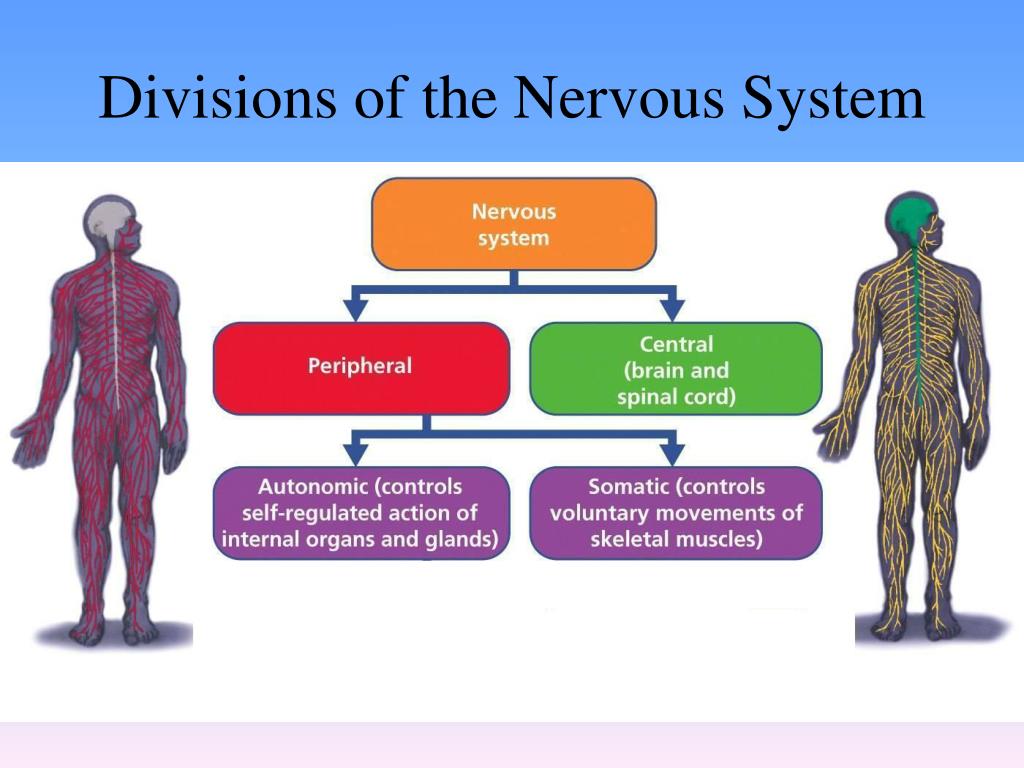
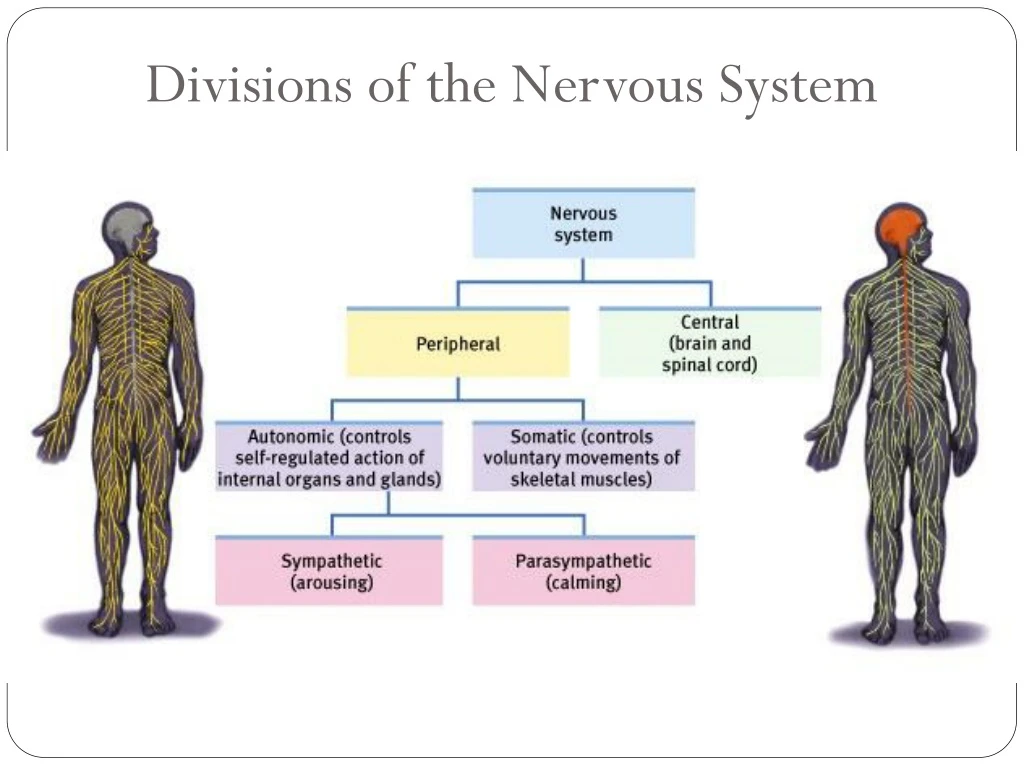
The nervous system breaks down into two primary divisions: the central nervous system (CNS) and the peripheral nervous system (PNS). That's the textbook answer. The reality of working with these systems, whether you're a medical student, a clinician, or someone studying neuroanatomy for practical purposes, is a lot messier than that clean dichotomy suggests. I spent years dealing with nerve conduction studies and interpreting electrophysiological data, and one thing I learned early was that the division between CNS and PNS isn't just an academic categorization. It directly determines what can be treated, what can be tested, and what gets ignored in a clinical setting. The PNS is where most peripheral neuropathies show up. The CNS is where things like multiple sclerosis present. But the boundary between them, particularly at the spinal nerve roots, is where diagnostic confusion happens.
Practical Divisions Of Nervous System Classification
Let me walk through how I actually approached this, not how it appears in a diagram. The CNS consists of the brain and spinal cord. Everything else falls under the PNS, which splits further into the somatic nervous system (voluntary control) and the autonomic nervous system (involuntary control). The autonomic division then breaks into sympathetic and parasympathetic branches. That's standard. Here's what most resources skip: the enteric nervous system, sometimes called the "second brain," runs through the gastrointestinal tract and operates largely independently. It's technically part of the autonomic division but functions with enough autonomy that some researchers argue it deserves its own category entirely. When I was running nerve conduction velocity tests, the distinction mattered practically. A slowed conduction in a peripheral nerve like the ulnar nerve at the elbow tells you something very different than an abnormality in a spinal cord pathway. The PNS handles signal transmission to and from limbs and organs. The CNS processes and integrates. Damage in each location produces distinctly different clinical pictures. One edge case that caught me off guard early in my career involved a patient presenting with lower extremity weakness and sensory changes. The symptoms pointed toward a lumbar radiculopathy, which sits right at the junction between CNS and PNS. The nerve root itself is technically PNS tissue, but it exits the spinal column where CNS structures are nearby. MRI showed no disc herniation pressing on the root. EMG/NCS was inconclusive. What I ended up doing was ordering a contrast-enhanced MRI of the cauda equina specifically, which revealed a small meningioma compressing the nerve roots. The tumor was peripheral enough to register as PNS involvement but close enough to the spinal canal that standard lumbar imaging missed it. It's the kind of thing that only becomes obvious when you understand that the divisions aren't clean surgical boundaries, they're functional zones that overlap anatomically.
The somatic division deserves more attention than it gets. It's responsible for voluntary motor control and sensation from the skin. When someone has a stroke affecting the motor cortex, that's CNS damage with somatic symptoms. When someone has peripheral neuropathy from diabetes, that's PNS damage with somatic symptoms. The clinical management differs significantly because the regenerative capacity of PNS axons is real, while CNS axons generally don't regenerate. That single biological difference drives entirely different treatment protocols and prognosis discussions. The autonomic system is where things get complicated fast. Sympathetic outflow originates from the thoracolumbar region (T1 through L2). Parasympathetic outflow comes from the craniosacral regions (brainstem nuclei and S2 through S4). Both feed into the same organs. This dual innervation means that autonomic dysfunction rarely presents as a simple "on" or "off" problem. It's usually a dysregulation of the balance between the two branches. I've seen patients with normal individual test results but clear clinical autonomic failure because the coordination between sympathetic and parasympathetic responses was broken. Standard reflex testing missed it because it looked at each pathway in isolation. If you're studying this material for an exam, memorize the structural divisions. If you're actually working with patients or doing research, focus on the functional overlap zones. The dorsal root ganglia sit outside the spinal cord but are embryologically continuous with it. The peripheral nerves contain both myelinated and unmyelinated fibers serving both sensory and motor functions, even though textbooks tend to draw clean lines between sensory and motor pathways. These overlaps exist because the system evolved as an integrated network, not as separate compartments designed by committee.
Get the Full Details

There's no single comprehensive resource that captures all of this in one place. Most textbooks handle the anatomy cleanly and leave the clinical applications to specialized neurology references. I've found that keeping a personal reference guide with the key distinctions between CNS and PNS pathology, along with the border zone conditions like radiculopathies and plexus injuries, saves significant time during both study and clinical work. The information is scattered across neuroanatomy, neurophysiology, and clinical neurology texts, and cross-referencing them manually is tedious but necessary for actual understanding.