Understanding the Numbers Behind a DPT Career
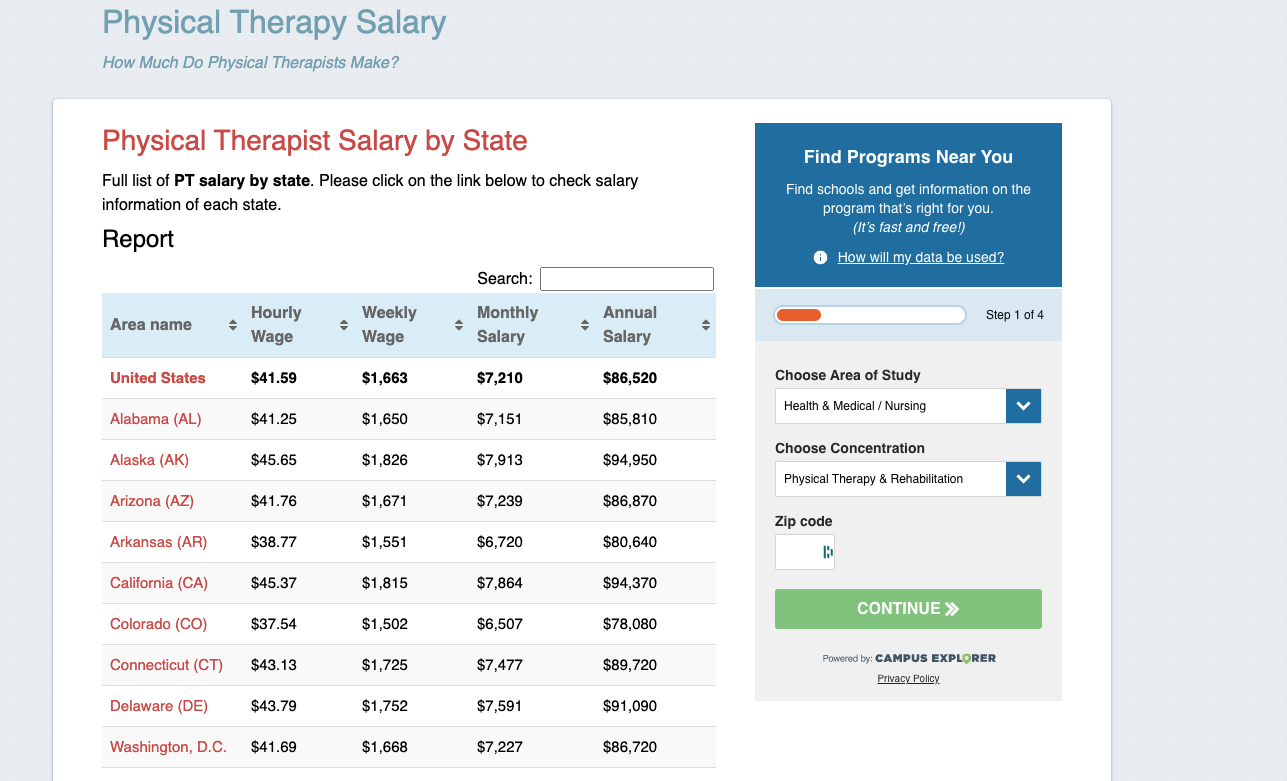
The reality of a Doctorate In Physical Therapy Salary is that it varies more by setting and geography than most people expect. I spent years crunching compensation data across clinic networks, hospital systems, and private practices, and the numbers don't always line up with what new grads assume going in. The median range sits somewhere between $85,000 and $105,000 annually for full-time roles in the United States, but that baseline number barely tells the whole story. Several factors push the number one way or another. Practice setting matters more than most job postings admit. A therapist working outpatient orthopedics in a private practice often makes less base salary than someone in a acute care hospital floor, even if the private practice offers productivity bonuses that can close the gap. Geographic location is the next big variable. Rural markets in the Midwest or South frequently pay above national median to attract candidates, while coastal metro areas like San Francisco or New York might show higher gross numbers but get eaten alive by cost of living adjustments that make the real purchasing power nearly identical to a midwestern position paying $20,000 less. I remember going through a compensation negotiation for a position in central Texas around 2019. The offer was $92,000 base plus 1.5 times the MVP (minimum vital productivity) bonus structure. On paper it looked straightforward. The real question was whether the MVP threshold was achievable given the patient panel size they planned to assign. I asked for the prior year's actual productivity data broken down by quarter, not the projection. The recruiter had no idea what that meant. When I finally got the numbers, the first two quarters of the prior year averaged only 82 percent of MVP due to a staff shortage that never got resolved. That meant the base salary was effectively the ceiling for most of the year. I walked away from that offer. The position filled two months later with someone who accepted the bonus as guaranteed income. That person left after eleven months when the productivity shortfall didn't improve.
How Compensation Structures Actually Work
Most DPT positions use one of three models: straight salary, hourly with overtime eligibility, or productivity-based comp with a floor and ceiling. The productivity model is by far the most common in outpatient settings. You get paid a base rate plus a percentage of your above-target revenue. The floor is usually set at or near national median. The upside can be significant but only if your caseload volume and visit productivity sustain it. In my experience, therapists who consistently hit 110 to 130 percent of MVP can earn in the $115,000 to $140,000 range. Those who hover around 90 to 100 percent stay locked into the base number regardless of how many hours they work. Hospital and inpatient roles tend to stick with hourly pay plus shift differentials. Night and weekend shifts can add five to fifteen percent on top of base hourly. Travel contracts in acute care run substantially higher, often $2,000 to $3,500 per week depending on market demand and assignment length, but those come with their own instability. Benefit packages differ dramatically between models. Salaried outpatient positions often include PTO, malpractice insurance, and continuing education stipends as part of the package. Hourly hospital roles may offer stronger retirement matches but charge more for benefits enrollment. A $5,000 difference in base salary means something entirely different when one employer covers your license renewal and professional dues while the other doesn't.
The Hidden Variables That Change Your Real Take-Home
Most job descriptions list a salary range that spans roughly $20,000. The bottom of that range usually assumes minimum productivity. The top assumes sustained overperformance with no burnout or extended leave. What rarely gets mentioned is how evaluation productivity calculations vary between employers. One clinic might count direct patient contact minutes toward MVP. Another counts billable visits including administrative time. The same therapist generating identical revenue can appear to produce differently depending on which counting method the payroll system uses. I encountered this exact problem when comparing two offers in the Seattle market. One employer quoted $98,000 to $125,000 based on MVP. The other quoted $95,000 to $118,000. The first job looked better on the surface. I dug into their productivity calculation policy and found that administrative documentation time counted as 50 percent productive time toward the MVP threshold. The second employer counted it at zero. After adjusting for that difference, the compensation gap narrowed to almost nothing. The first employer also required a sign-on repayment clause if you left within two years, which the second did not. I chose the second offer based on that comparison alone. The base number was lower, but the actual earnings potential over a multi-year horizon was higher once you factored in the repayment risk and the documentation credit policy.
Get the Full Details

What the Data Actually Shows Across Specialties
Specialty area influences compensation in ways that aren't always obvious. Home health and hospice physical therapists often earn higher base salaries than general outpatient orthopedics, sometimes ranging from $100,000 to $130,000 depending on region and caseload density. The tradeoff involves travel time between patient homes, irregular scheduling, and lower visit volume per day. Neurological and pediatric specialties in clinic settings tend to sit on the lower end of the salary spectrum because reimbursement rates for those diagnoses are typically lower, which limits how much revenue a therapist can generate per visit. Travel pediatric PT contracts can compensate for this with higher weekly rates, but those positions require constant geographic mobility. Sports and occupational therapy niches sometimes offer commission structures that push total compensation above $150,000 in high-volume practices. Those roles exist mostly in private sports medicine clinics and employee wellness programs. They also tend to carry higher injury risk and burnout rates. The work is physically demanding and schedule demands often include evenings and weekends for athlete availability. The money is real but so is the physical toll. I've watched therapists in their late thirties and early forties transition out of those roles because their shoulders and lower backs couldn't sustain the patient load year after year.
How to Evaluate an Offer Beyond the Base Number
Request the full comp package in writing before signing anything. Ask for the MVP calculation methodology, the prior year's productivity distribution for the team you'd join, the benefit cost breakdown, and any repayment or non-compete clauses. A salary of $95,000 with full benefits and no repayment obligation often beats $105,000 with a $4,000 benefits and a two-year sign-on clawback. The difference compounds over time. Malpractice insurance coverage type matters too. Some employers provide tail coverage when you leave. Others make you purchase it separately, which can cost $1,000 to $3,000 per incident depending on your claims history. Remote or hybrid roles exist now but they're limited to certain specialties like telehealth follow-ups and insurance review positions. Those typically pay less than direct patient care roles and cap out around $80,000 to $95,000 even at national organizations. The convenience is real but the earning potential drops noticeably. If your goal is maximizing a Doctorate In Physical Therapy Salary, direct patient care in high-volume settings remains the fastest path, provided you're willing to accept the physical and scheduling costs that come with it.