Understanding the Relationship Between Low Red Blood Cells and Anemia
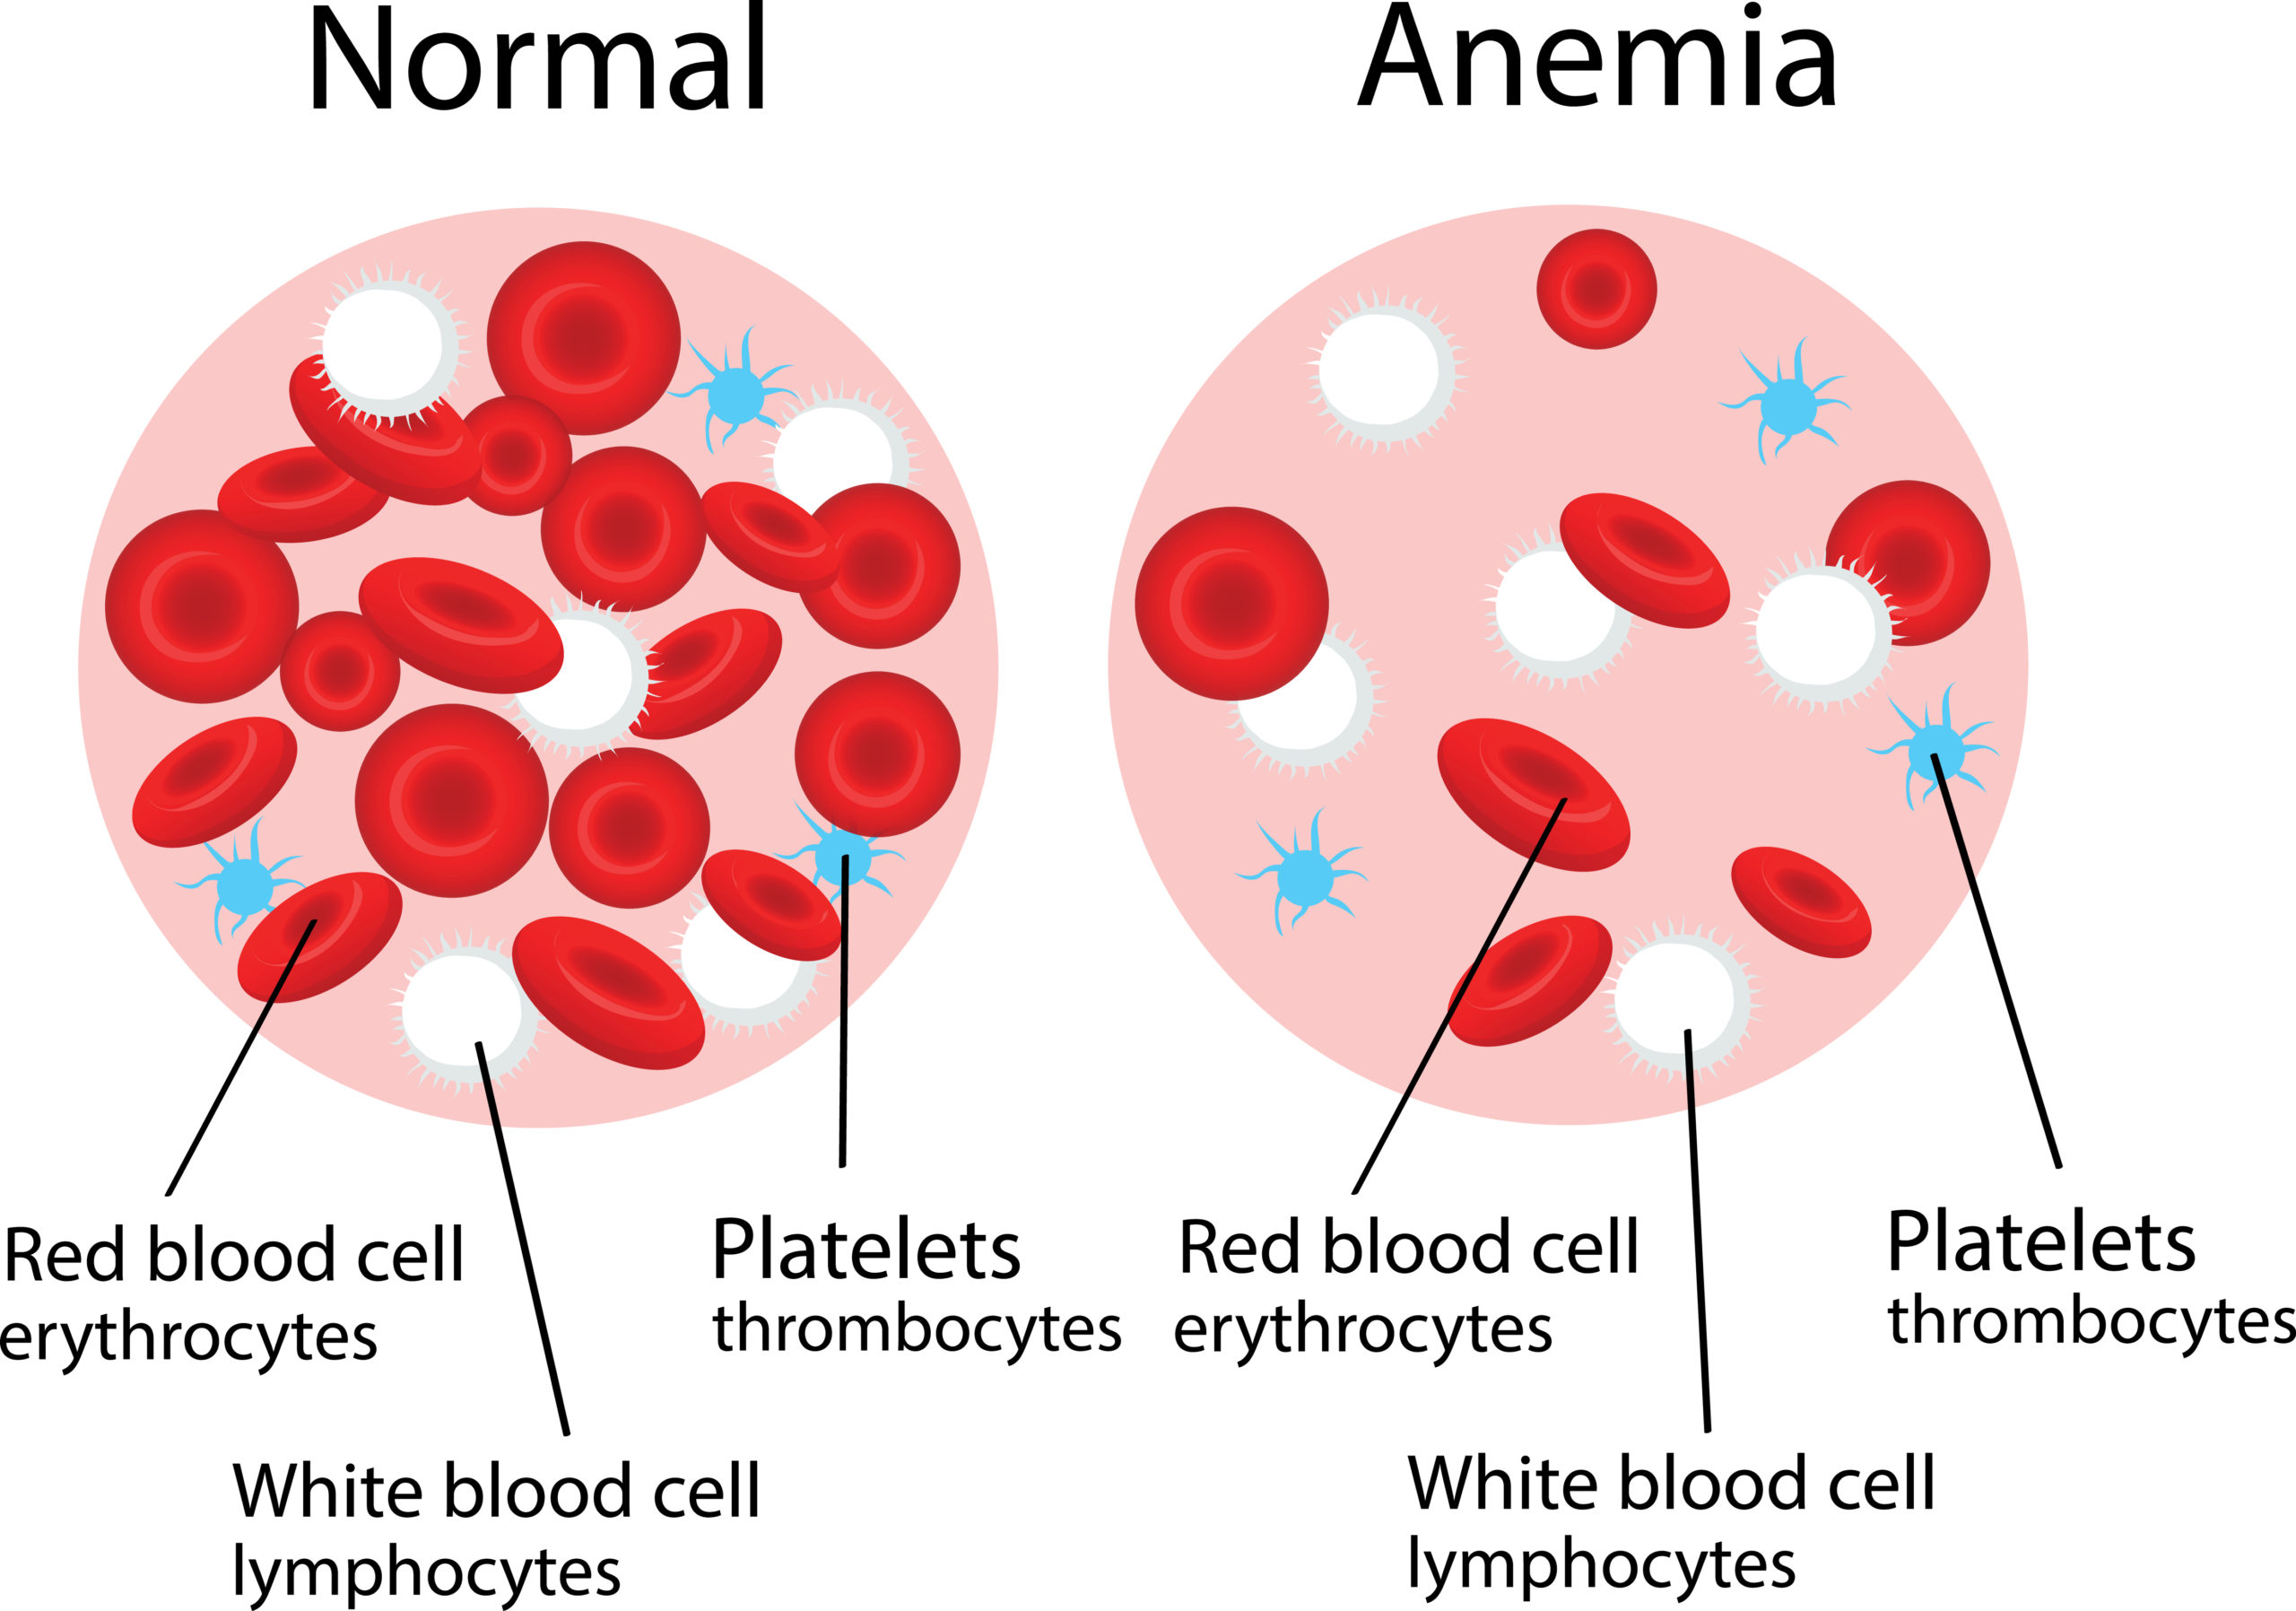
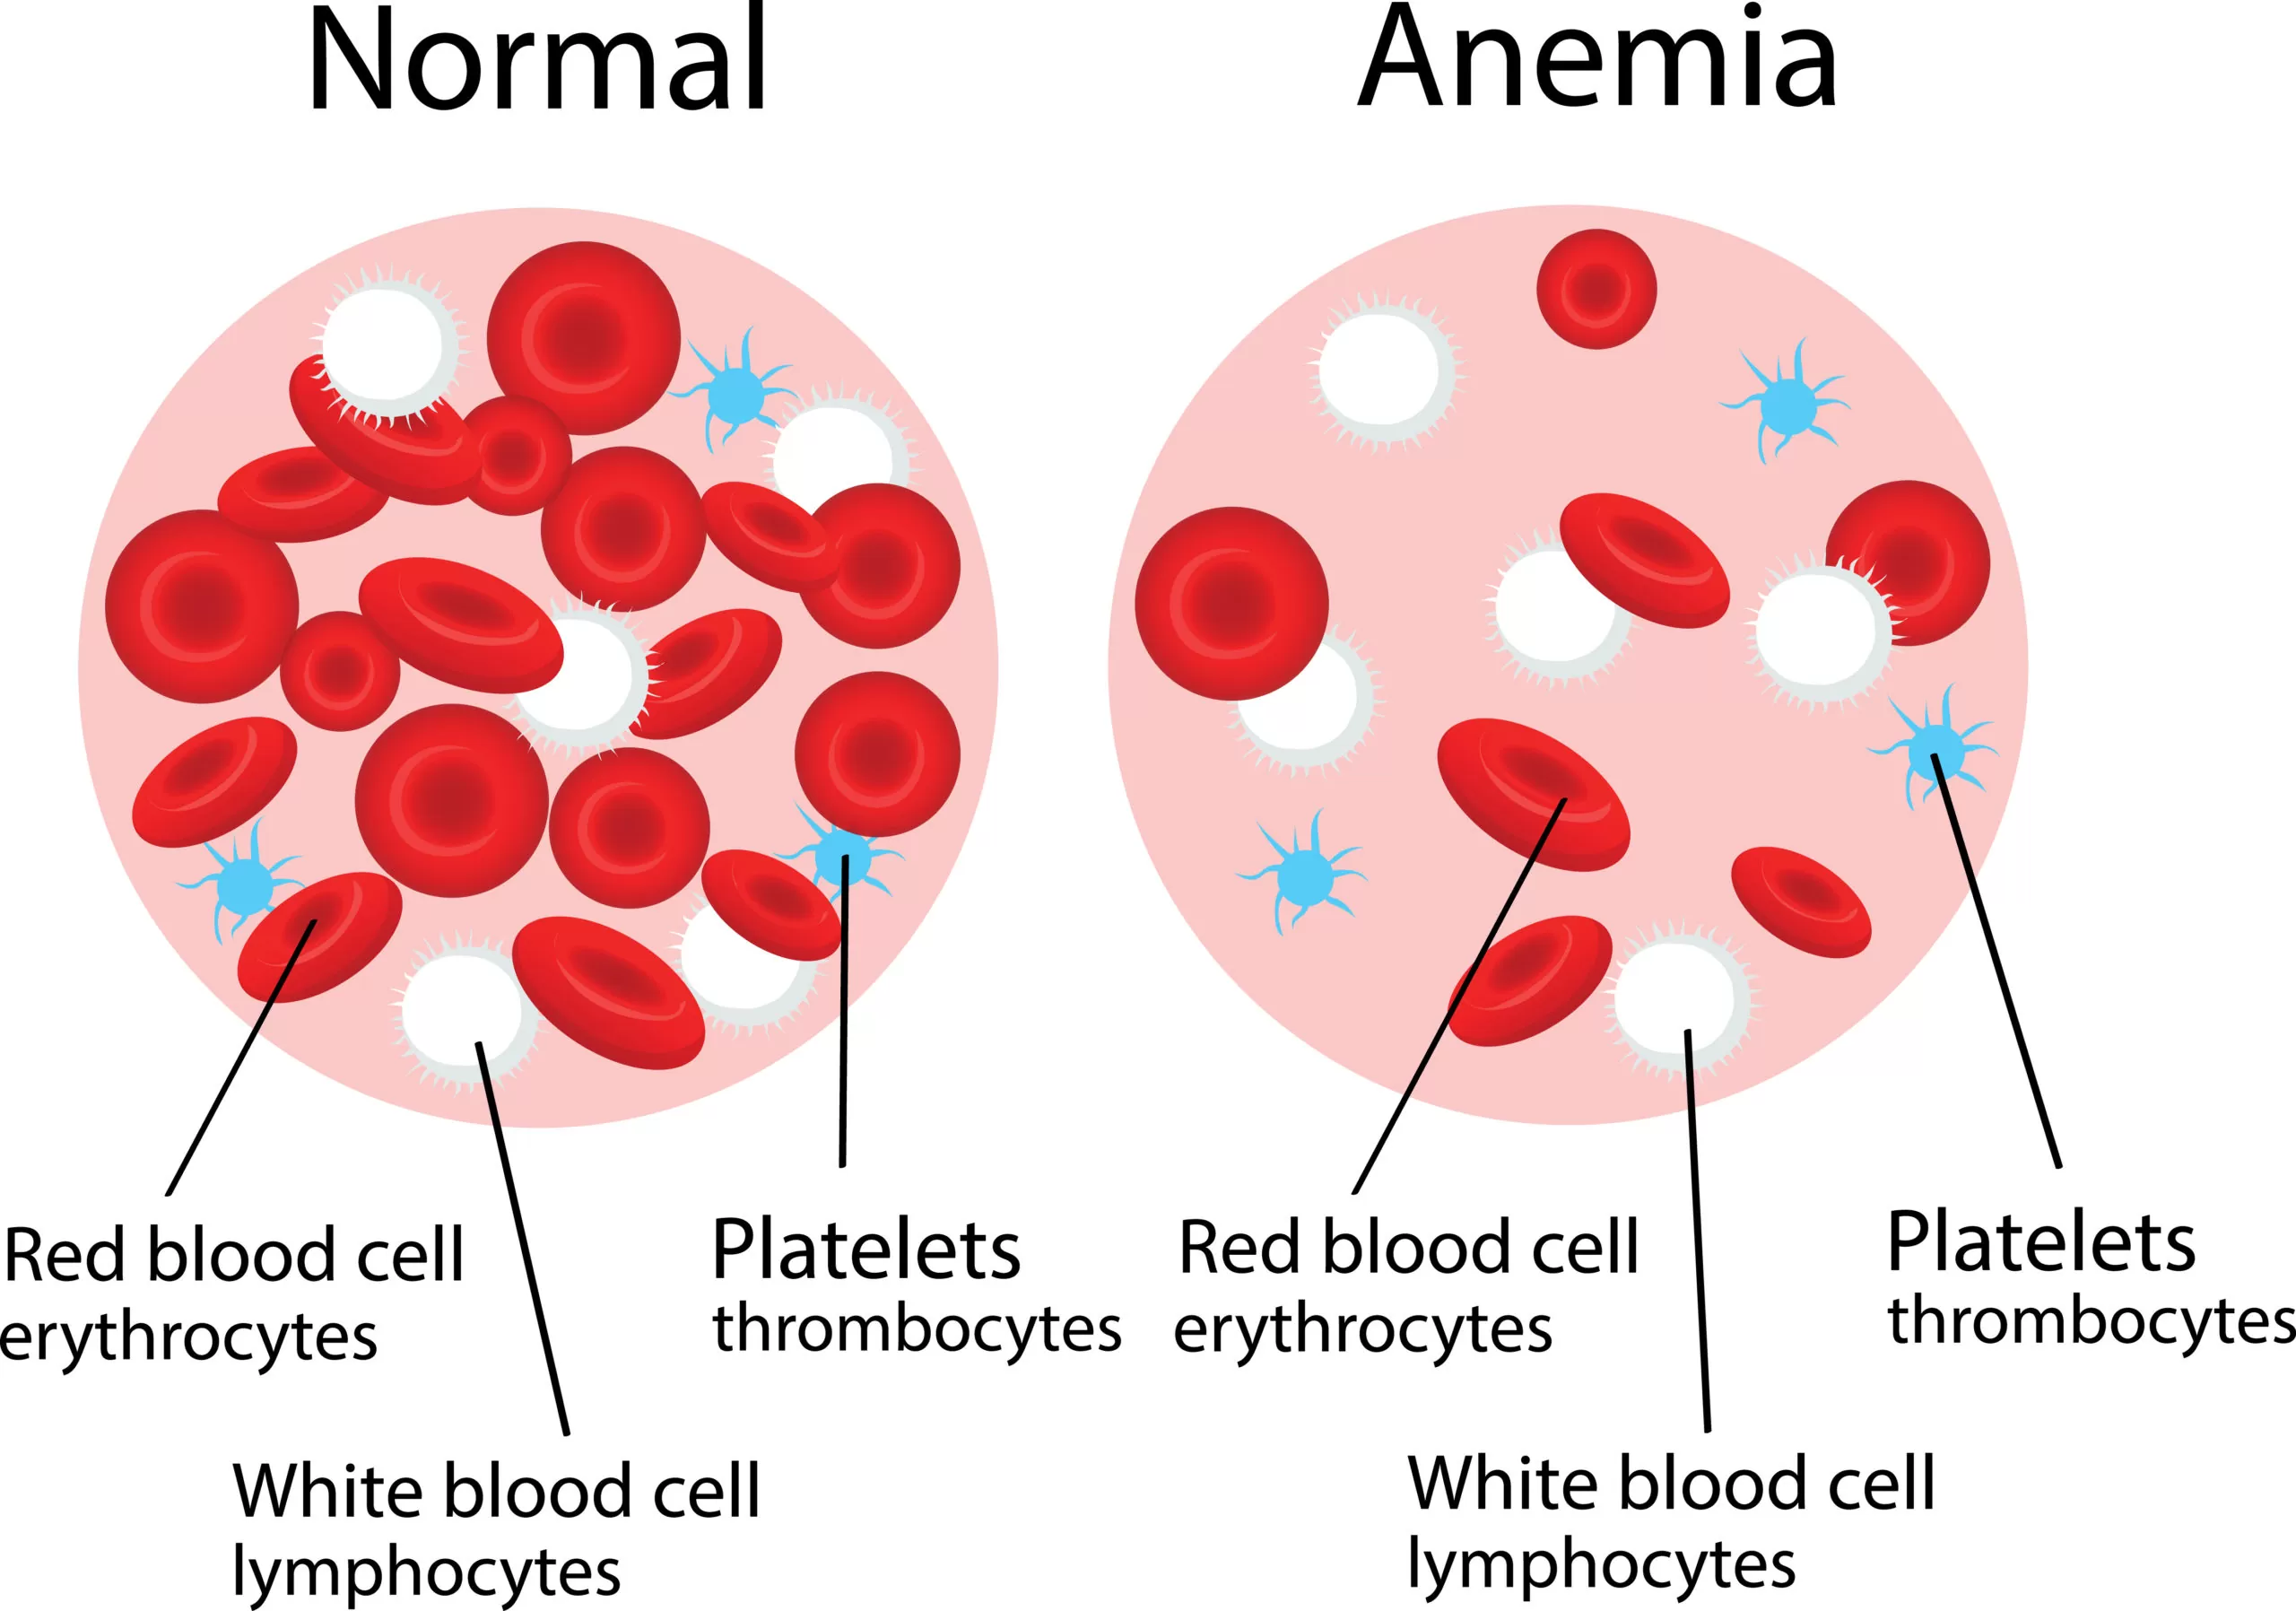
Erythrocytopenia is simply a laboratory finding that describes a lower-than-normal red blood cell count. It is not a standalone disease. When you encounter this term on a lab report, you are looking at one component of the picture that defines anemia. The question many people have is whether erythrocytopenia causes anemia or if it is simply a sign of it. The answer is more straightforward than it sounds. Anemia is clinically defined by low hemoglobin or low hematocrit, not by red blood cell count alone. Erythrocytopenia is the reduction of erythrocytes, the red blood cells themselves. So yes, having a low red blood cell count will almost always result in anemia because there are simply fewer cells carrying oxygen. But the reverse is also true—you can have anemia with a normal or near-normal RBC count if those cells are smaller or contain less hemoglobin than they should. That is the first thing most people miss when reading a CBC. I ran into this exact scenario a couple of years ago when a patient brought in a lab report that showed a borderline low RBC but a hemoglobin level that was clearly in the anemic range. The clinician had focused entirely on the RBC and assumed everything was fine. The MCV was low, the RDW was elevated, and the patient had iron deficiency. The low RBC was contributing, but the real problem was the quality of the cells, not just the quantity. Focusing on one number led to a delayed diagnosis by about three weeks.
How the Diagnosis Actually Works in Practice
A complete blood count gives you several data points. The RBC count tells you how many red cells are in a given volume of blood. Hemoglobin measures the oxygen-carrying protein. Hematocrit measures the volume percentage of red cells in your blood. MCH and MCHC tell you how much hemoglobin is packed into each cell. MCV tells you the average size. RDW tells you how much variation exists between cells. When you see erythrocytopenia on a report, you need to immediately check hemoglobin. If hemoglobin is below the reference range, you have anemia. The erythrocytopenia is part of the anemic state, not the cause of a separate condition. If hemoglobin is normal despite a low RBC, then you are dealing with a different situation, possibly macrocytic anemia where fewer but larger cells are maintaining adequate oxygen transport. This happens in B12 or folate deficiency and can be genuinely confusing if you only look at the RBC.
Common Pitfalls and What Most People Get Wrong
The biggest mistake is treating erythrocytopenia as an independent diagnosis and then searching for treatments that address it in isolation. It is a finding, not a disease. Another mistake is assuming that raising the RBC count will solve the anemia. In many cases, the RBC count is low because the bone marrow is not producing cells properly, the cells are being destroyed, or there is significant blood loss. The treatment depends entirely on the underlying mechanism. There is also a subtlety with lab reference ranges. Some laboratories use different thresholds for what counts as low RBC, and these thresholds can vary by sex, age, and altitude. A person living at high altitude will naturally have a higher baseline RBC count. Someone at sea level with the same absolute count might be flagged as having erythrocytopenia. Context matters more than the number on the page. I once spent an entire consultation with a patient who had been told they had "low red blood cells" and was panicking about a serious blood disorder. Their RBC was slightly below the reference range, but their hemoglobin, hematocrit, and all other indices were completely normal. They were dehydrated at the time of the draw, which artificially concentrated their plasma and threw off the RBC calculation slightly. Repeating the test after proper hydration showed everything was fine. The initial flag was a false positive driven by pre-analytical variables.
Get the Full Details

What to Actually Do When You See This Result
Check the hemoglobin first. If it is low, you have anemia, and the next step is determining the type. Look at MCV to categorize it as microcytic, normocytic, or macrocytic. That classification drives the entire diagnostic pathway. Microcytic anemia points toward iron deficiency, thalassemia, or anemia of chronic disease. Normocytic anemia suggests acute blood loss, hemolysis, or bone marrow issues. Macrocytic anemia points toward B12 or folate deficiency, liver disease, or hypothyroidism. If hemoglobin is normal despite low RBC, do not ignore the finding. Repeat the test, check for dehydration or overhydration, and review the MCV and RDW. Sometimes the body compensates by making larger cells, and the RBC count drops while oxygen delivery remains adequate. This is a temporary state and may not require intervention, but it warrants monitoring. The bottom line is that erythrocytopenia and anemia overlap significantly but are not identical concepts. One describes cell quantity. The other describes functional oxygen-carrying capacity. Understanding the difference prevents misdiagnosis and unnecessary treatment. The CBC is a tool, and like any tool, it requires someone who knows how to read all the outputs, not just the one that caught your eye first.