Understanding Medicare Coverage for Prostate Cancer Radiation
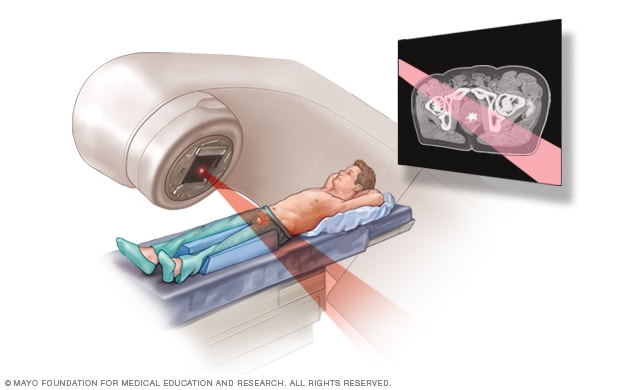
Medicare generally does cover radiation therapy for prostate cancer, but the details matter a lot. Original Medicare Part B handles the radiation treatments themselves, while Part A covers any hospital stays that might happen during or after the therapy. This isn't some tricky loophole situation, but there are enough moving parts that people end up confused or with unexpected bills. Under Part B, you'll typically pay 20 percent of the Medicare-approved amount after meeting your annual deductible. That's the standard rule. Radiation oncology is classified as a medical service under Medicare, not a hospital benefit, so it flows through Part B. Most patients who have Medicare Supplement insurance, also called Medigap, end up with very little out-of-pocket because those plans cover that 20 percent coinsurance in most cases. If you're on a Medicare Advantage plan, the costs and coverage rules change depending on the specific plan you chose. Some plans have lower copays for specialist services like radiation oncology, while others require prior authorization before anything starts. I always tell people to check their Summary of Benefits document rather than guessing, because the differences between plans can be enormous. There are several types of radiation used for prostate cancer, and Medicare covers them all when deemed medically necessary. External beam radiation therapy, which includes techniques like IMRT and VMAT, is covered. Stereotactic body radiation therapy, sometimes called SBRT or SABR, is also covered. Brachytherapy, where radioactive seeds are implanted directly into the prostate, falls under Medicare coverage as well. The key word throughout is medically necessary, which means your doctor has to document why radiation is being recommended and that it's appropriate for your specific case. Without that documentation, claims get denied, and the appeals process is tedious. I've seen patients wait six to eight weeks just for a single denial appeal to get resolved, and that's while they're supposed to be receiving treatment.
One thing most people don't realize is that the facility where you receive radiation matters significantly for costs. If your radiation oncology practice is part of a hospital system, you might get billed under both Part A and Part B depending on how the services are coded. This dual billing situation can create confusing statements that look like you were double-charged, when actually one charge is for the facility and the other is for the professional service. I had a patient last year who got three separate bills after a single day of treatment and thought Medicare had made an error. It turned out the radiation oncologist, the hospital outpatient department, and the medical physicist consulting on the case were all billing separately under different clauses of Medicare regulations. It was frustrating but completely legal, and explaining that took about twenty minutes of phone calls on my part. Prostate cancer radiation often requires multiple sessions spread over several weeks, and Medicare covers these as a course of treatment rather than counting each session individually. That structure works in your favor because you're not hitting your Part B limit after five or six treatments. The 20 percent coinsurance applies across the entire course, which can add up. A full course of external beam radiation for prostate cancer might cost between 20,000 and 50,000 dollars in total charges depending on the technique and length of treatment. Your actual out-of-pocket cost under Original Medicare without supplemental insurance could range from roughly 4,000 to 10,000 dollars, which is a significant amount for most people. This is exactly why getting Medigap or being on a Medicare Advantage plan with reasonable caps is important if you're going to pursue radiation therapy. There are some situations where Medicare coverage becomes much more complicated. If you're receiving treatment outside the United States, Original Medicare generally won't cover it except in very narrow circumstances like passing through Canada on the way from Alaska to another state. If you qualify for both Medicare and Medicaid, known as dual eligibility, Medicaid can help cover those Part B coinsurance payments, but you need to make sure both programs are aware of each other and set up properly. Some people find that Medicare will deny a claim for radiation therapy if it's being provided at a clinic that doesn't accept Medicare assignment, meaning the clinic bills Medicare directly but also bills the patient for the difference between their charge and what Medicare allows. This balance billing situation is less common now because of the No Surprises Act, but radiation oncology has some exemptions that still leave gaps, especially for out-of-network specialists at in-network facilities. I encountered this with a patient who had an in-network radiation facility but her radiation oncologist was out-of-network. She was billed for about 8,000 dollars beyond what Medicare considered reasonable, and even after appealing, she only got about 3,000 dollars reduced. The fix would have been to choose an in-network radiation oncologist before starting treatment, but that's advice you wish you had heard earlier.
If you want to minimize your costs and avoid surprise bills, start by verifying your radiation oncologist and the treatment facility are both in-network for your specific Medicare plan. Call the number on the back of your Medicare card and ask specifically about radiation oncology benefits, not just general medical coverage. Request a written estimate from the radiation oncology clinic before your first session, and ask them to submit a pre-determination to Medicare if your plan allows it. This gives you a chance to see what Medicare will pay and what you'll owe before you commit to the full course of treatment. Keep copies of every explanation of benefits statement, every denial letter, and every conversation you have with insurance representatives. The dates, names, and reference numbers matter enormously if you need to appeal anything later. The biggest mistake I see people make is assuming that Medicare approval means the full treatment is covered without question. Medicare often approves the initial sessions and then flags subsequent sessions for review if they think the treatment duration exceeds typical protocols. This is especially true for brachytherapy or longer courses of external beam radiation. Having your doctor include detailed clinical rationale in the treatment notes from the beginning can prevent these mid-course interruptions. Some patients also overlook that prescription medications related to radiation therapy, like anti-nausea drugs or steroids, are covered under Medicare Part D rather than Part B. Make sure your pharmacy plan covers those specific medications, or you'll get an unexpected bill at the pharmacy counter.
Get the Full Details





