What You Need to Know About Pulmonologists and Sleep Studies
Pulmonologists absolutely do sleep studies, but not all of them, and the ones who do aren't all doing the same thing. If you're trying to figure out whether your doctor can order and interpret the right test for your situation, here's the straightforward breakdown. The short answer is yes, most pulmonologists who specialize in sleep medicine perform and interpret sleep studies. That specialization isn't automatic though. After finishing a residency in internal medicine or pediatrics, a pulmonologist has to complete an additional fellowship in sleep medicine — usually one year — and then pass a board exam. The certificate comes from the American Board of Internal Medicine, subspecialty in Sleep Medicine. Without that extra training, a general pulmonologist might refer you elsewhere.
Does Pulmonologist Do Sleep Studies — And What Kind
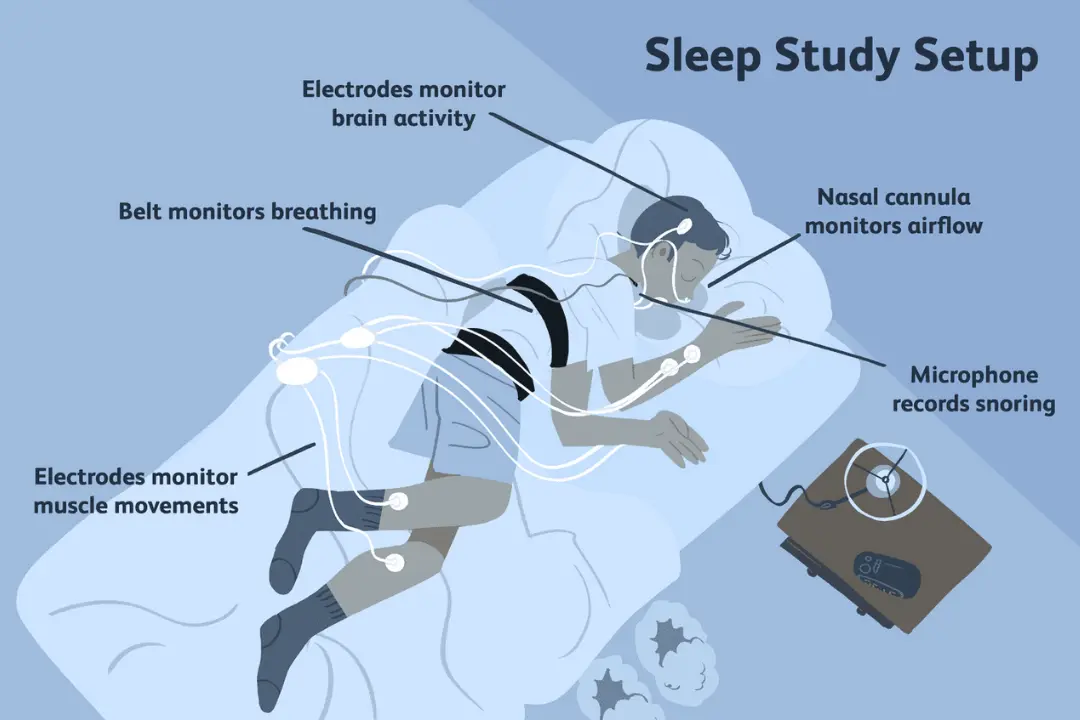
There are different levels of sleep studies, and knowing which one your pulmonologist runs matters more than just finding out whether they do any at all. Type 3 home sleep apnea tests are the most common. These are the portable devices you take home — a nasal cannula for airflow, a pulse oximeter, and a belt around your chest or abdomen. They measure breathing effort, oxygen saturation, heart rate, and airflow. They're fine for straightforward cases where obstructive sleep apnea is the clear suspicion and you don't have significant heart failure, chronic lung disease, or other complicating conditions. Full overnight polysomnography happens in a lab and is the gold standard. It records brain waves, eye movements, muscle activity, airflow, effort, oxygen levels, and heart rhythm all at once. This is the study a pulmonologist orders when the diagnosis isn't clear, when home testing failed, or when you have comorbidities that make interpretation of a simple test unreliable. Some pulmonologists also do split-night studies. You spend the first part of the night getting diagnosed, and if moderate to severe sleep apnea is confirmed, they wake you up briefly, hook you up to CPAP, and titrate the pressure while you sleep again. This saves you a second overnight visit but only works when the apnea is obvious early in the night.
What Actually Happens During the Test
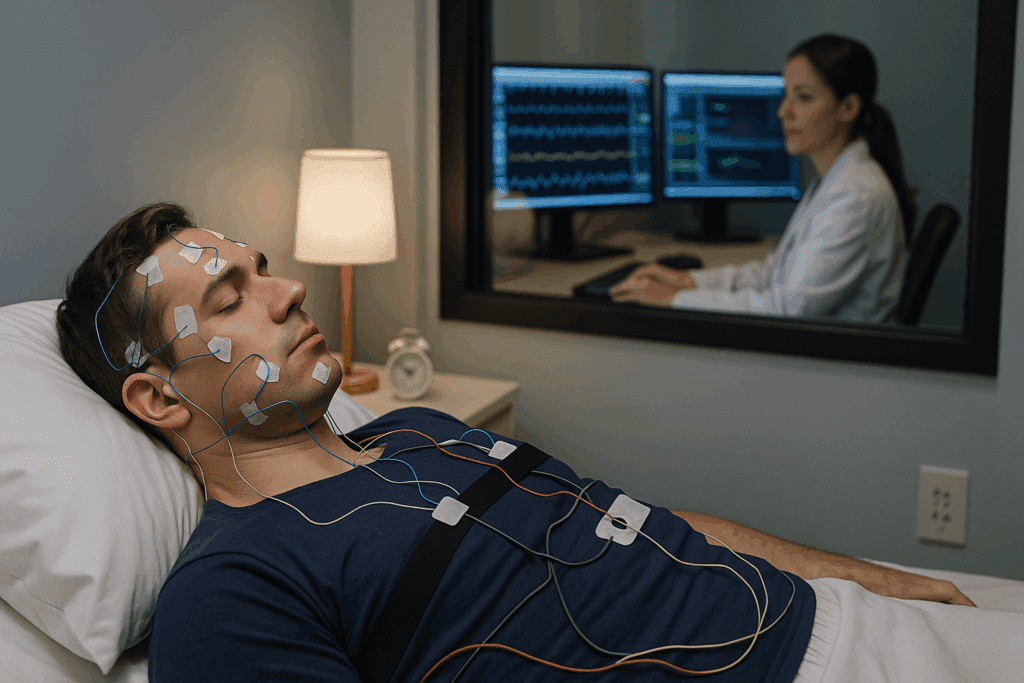
A home sleep test takes about five minutes to set up yourself. You attach the nasal prongs, stick on the finger probe, and strap the belt around your ribcage. The device records all night. In the morning you return it or mail it back. The pulmonologist's office reviews the data, calculates your apnea-hypopnea index — that's the number of breathing pauses plus partial collapses per hour of sleep — and determines severity. An AHI under 5 is normal. Five to fifteen is mild. Fifteen to thirty is moderate. Over thirty is severe. An in-lab study is different. A technician arrives about an hour before your scheduled sleep time and applies sensors — electrodes on your scalp for EEG, around your eyes for EOG, near your chin for EMG, plus the usual breathing and oxygen leads. You lie in a bed in a dark room. The tech monitors you from another room through a camera and audio link. You're expected to sleep for at least six hours. If they suspect sleep apnea and don't see it in the first few hours, they may do a CPAP titration study the next night or extend the same night with pressure adjustments.
Get the Full Details

A Problem I Ran Into That Most People Don't Expect
I once had a patient whose home sleep test came back completely normal. AHI was 2.4. No desaturations. Perfect oxygen levels all night. By every metric on that device, he didn't have sleep apnea. But he was still exhausted, waking up unrefreshed, with morning headaches and what he described as feeling like he couldn't catch his breath during the night. He'd been told to stop looking for answers because the test was clear. The problem was that the home device doesn't measure brain activity. It can't detect arousals. This patient had upper airway resistance syndrome — a condition where the airway narrows enough to increase breathing effort and trigger micro-arousals from sleep, but not enough to cause a full apnea or hypopnea that the device would count. His AHI was essentially zero, but his Respiratory Effort-Related Arousal index was through the roof. I ordered a full polysomnography with esophageal pressure monitoring, which directly measures the effort your diaphragm and chest wall are making against a narrowed airway. That confirmed UARS, and he responded well to CPAP at a much lower pressure than someone with typical OSA would need. Home sleep tests miss this. They miss a lot of this. If your symptoms are real but the home test is negative, don't just accept the result. Push for an in-lab study.
How to Find a Pulmonologist Who Actually Does This
Not every pulmonologist sees sleep patients. Some focus entirely on asthma, COPD, or critical care lung disease. When you're calling around, ask specifically whether they interpret sleep studies in-house or outsource them. Ask whether they do full polysomnography or only home tests. Ask if they're board-certified in sleep medicine. The AASM — the American Academy of Sleep Medicine — has a find a provider tool on their website where you can search by location and credentials. You should also ask about wait times. In many areas, the wait for a new patient sleep consultation runs three to six months. If you're severely symptomatic with things like choking episodes at night, daytime sleepiness that's affecting your driving, or known cardiovascular complications from untreated sleep apnea, tell them that when you're scheduling. Some offices will prioritize based on clinical urgency.
What the Study Results Actually Mean
Getting the AHI number is only the beginning. The pulmonologist will also look at your lowest oxygen saturation, the percentage of time you spent below ninety percent oxygen, how many cardiac arrhythmias occurred during the night, and whether you have periodic limb movement disorder alongside the apnea. These details change the treatment plan significantly. For mild OSA with an AHI around ten and minimal oxygen drops, the first line might be positional therapy or an oral appliance rather than CPAP. For severe OSA with an AHI over fifty and oxygen dropping below eighty percent, CPAP is pretty much mandatory, and you'd also want a cardiovascular workup because the strain on your heart at those levels is real. If you're prescribed CPAP, your pulmonologist should schedule a follow-up within sixty to ninety days to check your machine's download data. Modern CPAP devices record usage hours, leak rates, and residual AHI. If your residual AHI is still elevated on treatment, the pressure needs adjustment. If your leak rate is high, your mask fit is wrong. These are routine issues but they require active follow-up, not a set-it-and-forget-it approach.
When a Pulmonologist Isn't the Right Call
If you have narcolepsy, restless leg syndrome as your primary complaint, parasomnias like sleepwalking, or suspected central nervous system disorders affecting sleep, a pulmonologist might not be your first stop. Neurologists who are sleep-trained handle those cases. The overlap is real though — many pulmonologists who do sleep medicine can manage the full spectrum, and neurologists with sleep fellowships can diagnose and treat sleep apnea too. It comes down to who has the testing equipment and the appointment availability in your area. Some health systems have dedicated sleep centers staffed by both pulmonologists and neurologists working together. If yours does, that's the ideal setup. You get comprehensive testing and a team that can address everything from apnea to circadian rhythm disorders in one place.
Practical Things to Bring to Your Appointment
Write down your symptoms before you go. Not just "I'm tired" — specific things like snoring loudly, gasping or choking sounds witnessed by a partner, waking up with a dry mouth, morning headaches, frequent nighttime urination, difficulty staying asleep, and daytime sleepiness rated on a scale. Bring a list of all medications and supplements. Some prescriptions — beta blockers, diuretics, sedatives, antidepressants — can worsen sleep apnea or mimic its symptoms. Your pulmonologist needs to know what you're taking before making any recommendations. If you have old sleep study reports from previous tests anywhere, bring them. Comparison across multiple studies is genuinely useful. A clinician can see whether your AHI has progressed, whether treatment is actually working over time, or whether a previously normal test was a false reassurance. The whole process from first symptom recognition to final treatment plan typically takes two to four months if everything goes smoothly — referral, intake, testing, result review, and treatment initiation. It's longer if insurance pre-authorization drags or if you need a second study. But getting it right matters. Untreated moderate to severe sleep apnea increases your risk of hypertension, atrial fibrillation, stroke, and motor vehicle accidents substantially. The testing is worth the inconvenience.