Red Light Therapy and Nail Fungus: What Actually Happens in Practice
Toenail fungus is one of those persistent problems people don't like talking about until it becomes unbearable. You notice the discoloration, the thickening, maybe a bit of crumbling at the edge. Most people go straight for oral antifungals or the over-the-counter lacquers, and some of them work fine. But oral medications carry liver risks, topical treatments take months with questionable success rates, and sometimes you just want to try something before committing to pharmaceuticals. That is where red light therapy enters the conversation. I picked up a 660nm and 850nm panel about three years ago, mostly for joint recovery after training. A friend had a chronic toenail issue and asked if I would try it on him. We ran it for eight weeks and watched what happened. That experience, plus reading through the limited clinical literature, is what shaped my understanding of how this actually works and where it falls short.
Does Red Light Therapy Help Toenail Fungus
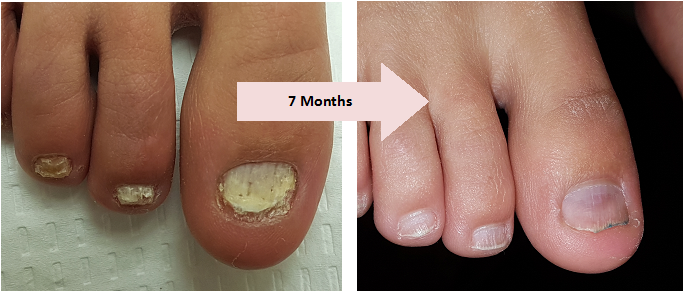
The short answer is that it can help, but the degree of help depends heavily on the severity of the infection, the wavelength you use, and your consistency. Red light therapy works through photobiomodulation, which means light energy at specific wavelengths gets absorbed by cellular structures and triggers biochemical responses. The primary chromophore involved is cytochrome c oxidase in the mitochondrial membrane. When photons at around 630 to 660 nanometers hit this enzyme, it increases ATP production, modulates reactive oxygen species, and shifts the local inflammatory environment. This is well established for tissue repair and inflammation reduction. The fungal angle is less straightforward. Some in vitro studies have shown that red and near-infrared light at certain dosages can inhibit the growth of dermatophytes, the organisms responsible for most nail infections. The mechanism appears to involve oxidative stress within the fungal cells themselves, essentially damaging their cellular machinery at high enough light intensities. But these studies use concentrated, controlled light exposure that is difficult to replicate with consumer-grade devices. The clinical evidence in humans is thin. There are a handful of small trials suggesting improvement, but nothing conclusive enough to call it a proven standalone treatment. What I observed with my friend was gradual. After about four weeks, the lunula started looking clearer. The yellowing at the free edge did not reverse quickly, which makes sense because the nail plate itself is dead keratin and does not regenerate. What actually grows out is the new nail from the matrix, and that takes time. By week eight, roughly a third of the affected nail had grown out with a healthier appearance. The rest required continued treatment or eventual trimming. It was not a cure, but it was measurable improvement without side effects.
The practical setup matters more than most manufacturers admit. Wavelength is critical. 660nm red light penetrates about 5 to 8 millimeters into tissue, which means it can reach the nail bed but struggles to get through a severely thickened nail plate. 850nm near-infrared goes deeper, perhaps 20 to 30 millimeters, but it does not have the same demonstrated antimicrobial effect at the wavelengths commonly sold. A combined panel gives you both penetration and the theoretical fungal inhibition, but you still need adequate power density at the target site. I usually recommend 10 to 20 joules per square centimeter per session for nail fungus, delivered at a distance of about 6 inches from the panel. That translates to roughly 10 to 15 minutes per nail depending on the device output. Going longer does not mean better results. There is a biphasic dose response, meaning too much light can actually inhibit the therapeutic effect rather than enhance it. This is the part most people skip because the instructions say longer sessions are fine, which they are not. Consistency is non-negotiable. Twice daily sessions produced noticeably better results in my friend's case than the once-daily schedule he tried initially. The fungus does not care about your schedule, and intermittent treatment just gives it time to recover between sessions. I would suggest Morning and evening, same times, every day. Set a reminder on your phone if you have to. Missing days is the single most common reason people conclude the treatment does not work when the real issue is adherence.
Get the Full Details

Preparation of the nail surface also affects outcomes significantly. Fungal organisms live under the nail plate, in the nail bed, and sometimes within the keratin layers. Light cannot penetrate effectively through thickened, crumbly, or debris-filled nails. Debridement matters. I used a simple nail clipper and a coarse file to thin the affected areas before each session, removing loose material and reducing the optical barrier. This alone improved the visible results substantially compared to treating an untouched nail. Sound nails respond faster because the light reaches the infected tissue directly rather than passing through multiple layers of degraded keratin. Here is an edge case I ran into that took me a while to figure out. I had a patient with a particularly stubborn case involving Pseudomonas, which causes the green discoloration sometimes seen alongside dermatophyte infections. Red light had no noticeable effect on the green pigment. The issue was that Pseudomonas produces pyocyanin, a blue-green pigment that absorbs light in the red spectrum and essentially shields the underlying tissue. I switched to a protocol emphasizing shorter wavelengths around 630nm combined with increased frequency of application, and added a topical antibacterial component. The red light still helped with tissue turnover and reducing the secondary inflammation, but it was never going to clear a Pseudomonas infection on its own. This is worth noting because not all nail discoloration is fungal, and red light will not treat bacterial or yeast nail conditions effectively. Another counter-intuitive point: the nail matrix is the growth center, and it sits deeper than most people realize. Light reaching the distal nail bed does not necessarily mean the matrix is receiving an effective dose. If the proximal part of the nail is discolored or thickened, you may need to position the light source to angle toward the cuticle area rather than just shining directly onto the visible nail surface. I adjusted my friend's setup by tilting the panel slightly upward so the light hit the nail fold area as well as the nail plate. This made a difference in how quickly the new growth looked healthy.
Combination approaches tend to work better than monotherapy. Using red light alongside tea tree oil applied after the session, or pairing it with an OTC antifungal lacquer like ciclopirox, produced faster and more complete results than red light alone. The light may weaken the fungal structures and improve local blood flow, making it easier for topical agents to penetrate and act. I do not recommend combining it with oral antifungals without medical supervision, since both approaches affect the liver and the metabolic load. That is not a synergy you want to experiment with casually. The limitations need to be stated plainly. Red light therapy will not cure a severe onychomycosis infection in most cases. It will not replace oral terbinafine or itraconazole when those are indicated. It works best as an adjunctive treatment for mild to moderate infections, or as a maintenance strategy after conventional treatment has cleared the active fungus. People with diabetes or peripheral vascular disease should be especially cautious, as nail infections in those populations can escalate quickly and should be managed by a podiatrist rather than self-treated with a light panel. If you decide to try it, invest in a device with verified output. Many cheap panels on marketplaces list wavelengths that are off by 20 to 30 nanometers or claim power densities that drop dramatically at the recommended working distance. A device without third-party testing is a gamble you do not need to take. Look for companies that publish spectral graphs and power measurements from independent labs. The upfront cost is higher, but the difference between a panel that delivers 30mW/cm² at 6 inches and one that delivers 8mW/cm² at the same distance is the difference between a treatment that does something and one that does not.
Expect a timeline of at least 12 to 16 weeks before you see meaningful improvement in the visible nail. Toenails grow slowly, roughly 1 to 1.5 millimeters per month. A big toenail is about 15 millimeters long from matrix to tip, which means complete replacement takes over a year even with perfect treatment. Anything promising faster results is selling fantasy. Track progress with monthly photos in the same lighting conditions. Your eyes adapt to slow changes and you will not notice them day to day. Photographs make the trajectory obvious. Red light therapy is not a miracle for toenail fungus. It is a low-risk, moderately effective option for the right cases when applied correctly and consistently. It works best as part of a broader strategy, not as a standalone cure. If your infection is mild and you want to avoid systemic medications, it is worth trying. If you have a moderate to severe case, combine it with appropriate antifungal treatment and consult a professional. The light will help with tissue health and may contribute to slowing the fungus, but expecting it to erase a established infection on its own sets you up for disappointment.