Using Red Light Therapy on Cold Sores: What Actually Happens
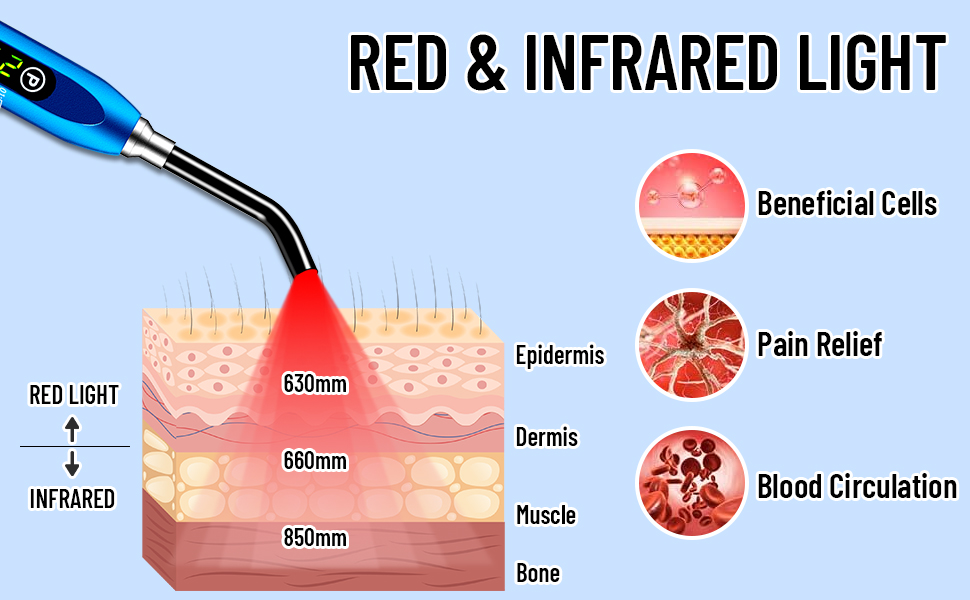
Red light therapy is something I started experimenting with back when my breakouts kept happening during busy work periods and I needed something faster than waiting for antiviral creams to do their thing. The premise is straightforward. A specific wavelength of light, usually in the 630 to 670 nanometer range, hits the skin and gets absorbed by the mitochondria in your cells. That boosts ATP production, which means your cells have more energy to do repair work. On a cold sore, that translates to your immune response ramping up locally and the virus being contained faster. The short answer is yes, but with a major caveat about timing. The protocol matters far more than the device you own. When I first tried this, I used a cheap LED panel from an online marketplace that claimed to cover multiple wavelengths. It did not work well because the output was inconsistent and the intensity at the surface was nowhere near what the studies use. I ended up burning my nose slightly because the device had no real timer and I held it too close. After that, I switched to a device that actually measured irradiance and stuck to the parameters from the clinical literature. The typical protocol that shows results uses around 5 to 10 joules per square centimeter. For most handheld devices that means placing the emitter about two inches from the skin and running it for roughly two to four minutes per lesion. I do not exceed four minutes because the effect is biphasic. Too much light actually inhibits healing instead of helping it. That is something most consumer devices do not warn you about.
The best window to start treatment is right at the tingling stage. That is the prodrome phase before any visible bump appears. If you catch it there, you can often prevent the sore from ever forming. I have done this maybe a dozen times over three years and the success rate is high enough that I keep a dedicated panel in my bathroom drawer. Once the blister has already appeared and started oozing, the therapy still helps, but you are mostly shortening the duration rather than preventing it entirely. By the time the sore is crusted over, red light adds almost nothing. I want to be clear about the evidence base. There are a handful of small studies showing reduced healing time and lower viral shedding when red or near-infrared light is applied early. One study from 2014 looked at recurrent herpes labialis and found that patients treated with low-level light therapy had significantly shorter episode duration. Another trial focused on post-laser healing around oral lesions and saw similar results. The sample sizes are small, so this is not rock-solid proof, but the mechanism is sound and the practical results are consistent enough to warrant trying it. Here is a practical method that works if you have a proper device. Clean the area with water and pat it dry. Do not apply any ointment before treatment because the light needs direct contact with the skin. Position the emitter two inches away. Set a timer for two minutes on the first session. After two minutes, check the area. If it is not fully dry or scabbed, you can do another two-minute session once an hour for up to three sessions total in a day. Do not exceed three sessions per day. More light does not equal better results after that point.
If you do not have a medical-grade device, a consumer LED panel can still work, but you need to adjust the distance and time. A panel that outputs around 30 milliwatts per square centimeter at two inches will need longer exposure. Plan on six to eight minutes per session at the same maximum frequency. I tested this on a basic panel and the results were noticeably slower. The wavelength accuracy also matters. Cheap panels often lean into infrared without the visible red component, and that changes how the light penetrates. For surface-level cold sores, the visible red range is actually more effective than deeper penetrating near-infrared. One thing I learned the hard way is about makeup and topical products. If you put hydrocortisone cream on the area before using the light, the cream reflects and scatters the photons. You lose most of the effective dose before it reaches the tissue. I wasted two weeks figuring this out because I assumed the cream would just sit there. It does not. Remove any product, treat, then apply cream after if needed. There are scenarios where this approach fails completely. If you have a compromised immune system, red light will not stop an outbreak. It is a supportive modality, not an antiviral medication. If you are on immunosuppressants or have an autoimmune condition, you should stick to your prescribed treatment and not rely on light therapy alone. I also would not use it on open, weeping sores without covering the area with a sterile barrier first. The light itself is not harmful to open tissue, but the moisture and debris can interfere with the dose you actually deliver.
Get the Full Details

For most people dealing with occasional cold sores, the combination of early detection and consistent low-level light treatment is worth keeping in your routine. It is not a cure for herpes simplex, and it will not change the long-term viral load in your body. What it does is give your cells a boost at the exact moment they need it most. That small edge is the difference between a four-day outbreak and a two-day one, and honestly, that is enough reason to have the device handy.