What the GAPS Diet Actually Is
The GAPS (Gut and Psychology Syndrome) diet was created by Dr. Natasha Campbell-McBride in the early 2000s. It is a six-phase elimination diet designed to heal leaky gut and, according to its proponents, improve conditions ranging from autism and ADHD to autoimmune disorders. The core premise is that gut permeability drives systemic inflammation, which in turn affects the brain and immune function. The diet cuts out grains, sugars, starchy vegetables, and most processed foods while emphasizing bone broth, fermented foods, raw dairy, and organ meats. I want to address something most people don't talk about openly. The strictness of the initial phases is brutal. We are talking full elimination of practically everything you'd consider a normal meal. People quit during Phase 1 because it is that harsh. I watched a patient try it for three weeks and end up just bingeing on dark chocolate because the restrictions became psychologically unsustainable. That is not a failure of the person — that is a feature of a protocol that demands near-monastic compliance for months at a time.
Does The Gaps Diet Work
The honest answer depends entirely on what condition you are treating and how you define "work." For confirmed leaky gut or small intestinal bacterial overgrowth (SIBO), there is some mechanistic logic behind the approach. Removing fermentable carbohydrates and gluten can reduce bacterial fermentation and intestinal permeability in certain individuals. The bone broth and gelatin provide amino acids like glycine and proline that support tight junction repair. That part makes physiological sense. But here is where it gets complicated. The evidence for GAPS specifically treating autism, ADHD, or depression is extremely limited. There are no large randomized controlled trials. The published data consists mostly of case studies and anecdotal reports. A 2020 review in Nutrients noted that while gut-brain axis research is a legitimate and growing field, GAPS itself has not been subjected to rigorous clinical testing. So when you see dramatic before-and-after stories online, understand that selection bias is massive. People who succeed post about it. People who try it for two months and see zero change usually stop mentioning it. I had a client — let's call him Mark — who came to me after his functional medicine doctor put him on GAPS for treatment-resistant IBS and mild anxiety. Mark followed it rigidly for four months. His bowel symptoms improved slightly, but his anxiety actually worsened. The issue was nutritional deficiency. The diet is very low in certain B vitamins and minerals during the early phases, especially if you are not eating enough organ meats or supplementing properly. I ran a comprehensive micronutrient panel and found he was borderline deficient in zinc and B6. We added targeted supplementation and introduced sweet potatoes earlier than the protocol allows, which stabilized his energy and mood. He eventually transitioned to a less restrictive version and maintained most of the gut improvement without the psychological toll.
The Six Phases Explained
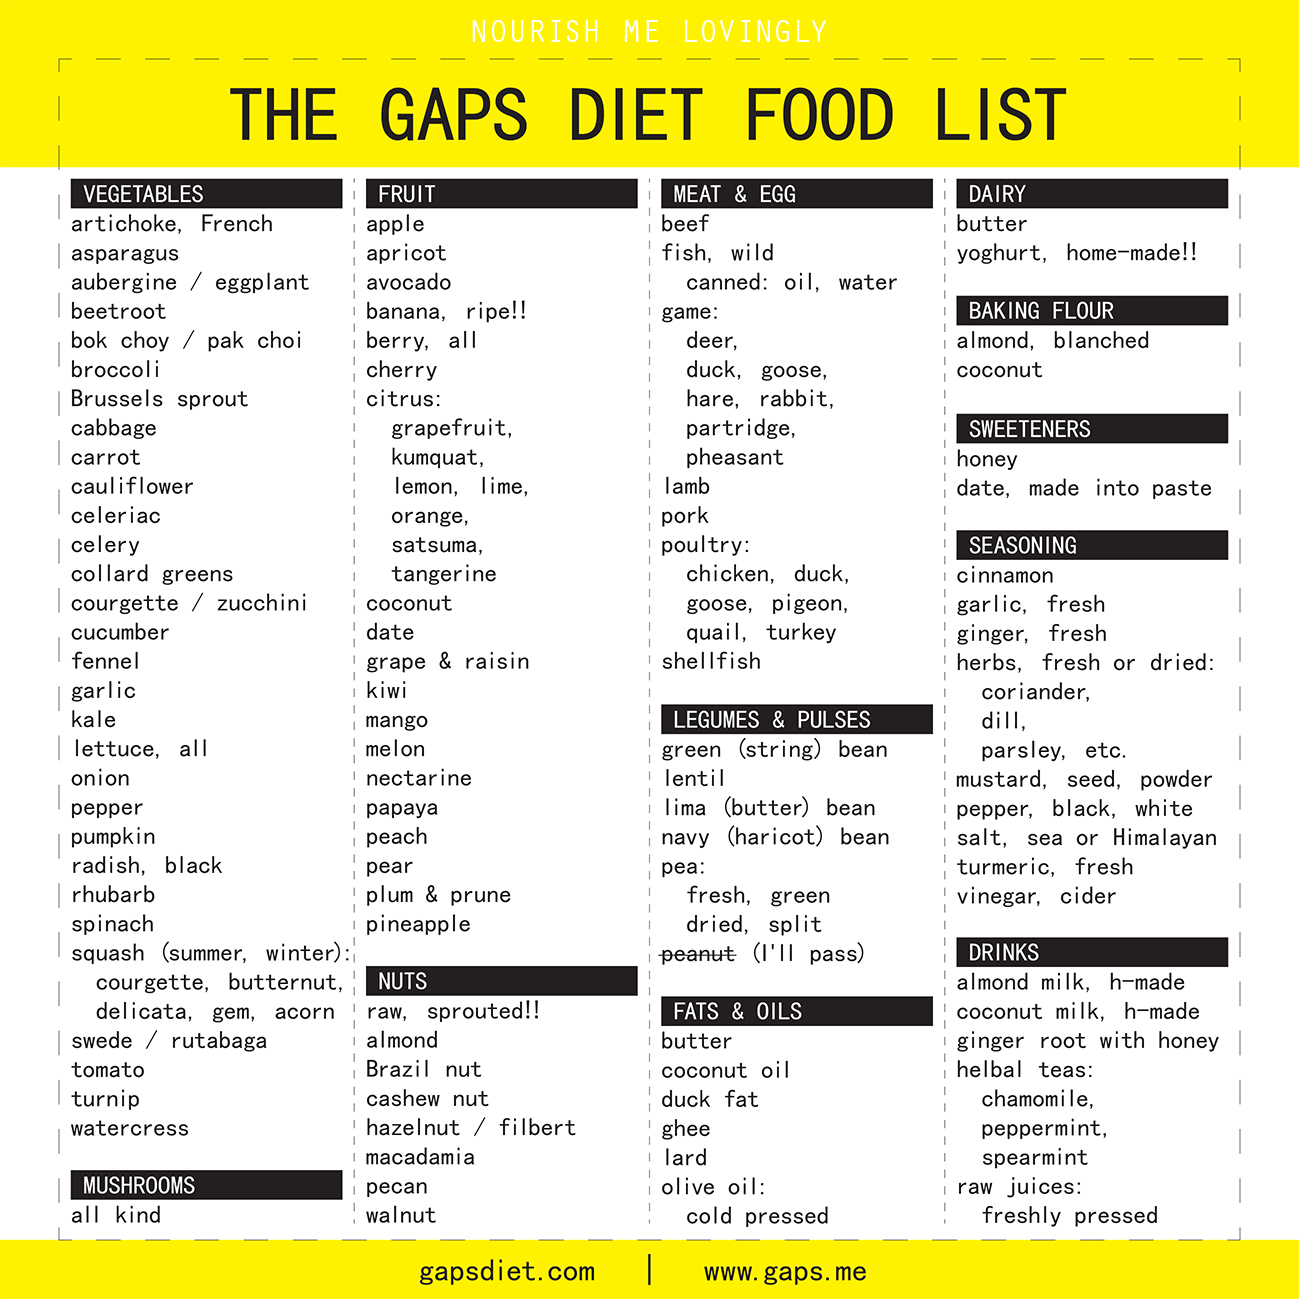
Phase 1 is the Introduction Diet, which is divided into six stages. You start with homemade meat stocks, then add cooked vegetables, followed by fermented foods like kefir and sauerkraut juice, then proteins like eggs and fish, then more varied meats and organ meats, and finally healthy fats and a broader range of vegetables. Each stage lasts about two weeks, but you only advance when symptoms have significantly improved. Some people never make it past Stage 3. Phase 2 is the Full GAPS Diet. This is the maintenance phase where you continue eliminating all grains, refined sugars, and starchy vegetables. You eat freely from the approved list: meat, fish, eggs, raw dairy, fermented foods, non-starchy vegetables, and healthy fats. This phase can last anywhere from six months to several years depending on the condition being addressed. The later phases involve slowly reintroducing foods. This is where most people stumble because the reintroduction protocol is vague. The diet says to add one new food every three days and monitor for reactions, but it does not give clear criteria for what counts as a reaction versus normal digestive noise. I recommend keeping a detailed symptom journal with timestamps. Track sleep quality, stool consistency (Bristol Stool Chart is useful here), energy levels, and any skin or mood changes. Without that documentation, you are guessing.
Get the Full Details

Practical Problems People Don't Warn You About
The cost is a major factor. Raw dairy, grass-fed meats, organ meats, and high-quality supplements add up quickly. In my experience, clients typically spend two to three times their normal grocery budget during the active phases. That is before you factor in the time investment. Making your own bone broth weekly, fermenting vegetables, and preparing every meal from scratch means someone is spending roughly two to three extra hours per day on food preparation. Most people cannot sustain that for more than a few months without significant lifestyle disruption. Another overlooked issue is the oxalate problem. As people progress through the diet and start eating more raw vegetables, spinach, nuts, and cocoa, oxalate load increases. For individuals with genetic variants in the AOXT enzyme or those who already have kidney stone history, this can trigger issues within weeks. I had a patient develop kidney pain after three months on GAPS because she was eating large amounts of spinach and almond butter daily. We dropped the high-oxalate foods and her symptoms resolved within a week. This is not mentioned in any GAPS literature I have seen. Social isolation is real and underappreciated. Dining out becomes nearly impossible. Family gatherings require either bringing your own food or explaining why you cannot eat anything on the table. I know several people who ended the diet prematurely because the social cost outweighed the marginal health benefits they were experiencing.
Who Should and Should Not Try This
GAPS may be worth considering if you have a confirmed gut-related condition like IBS, SIBO, or ulcerative colitis and have not responded to standard treatment. It is also reasonable if you have tried other elimination diets without success and want a more structured approach with a clear timeline. It is probably not worth it if you are looking for a quick fix, if you have a history of disordered eating, if you cannot afford the financial and time investment, or if you are hoping it will replace conventional treatment for serious conditions. The diet should never replace medical care for autoimmune disease, psychiatric conditions, or metabolic disorders. For people who find GAPS too extreme, a modified low-FODMAP diet or the Specific Carbohydrate Diet (SCD) offer similar mechanisms with less restriction. SCD was actually the precursor to GAPS and has slightly more clinical backing for inflammatory bowel disease. The Monash University low-FODMAP approach has the most robust research overall, though it is primarily designed for IBS rather than the broader set of conditions GAPS claims to address.
If you decide to proceed, do it with supervision. Work with a nutritionist or functional medicine practitioner who can monitor your labs, adjust the phases based on your progress, and catch deficiencies before they become problems. Going it alone is possible but significantly riskier and less likely to produce lasting results.