
Why Your Dog's Hind Leg Is Dragging
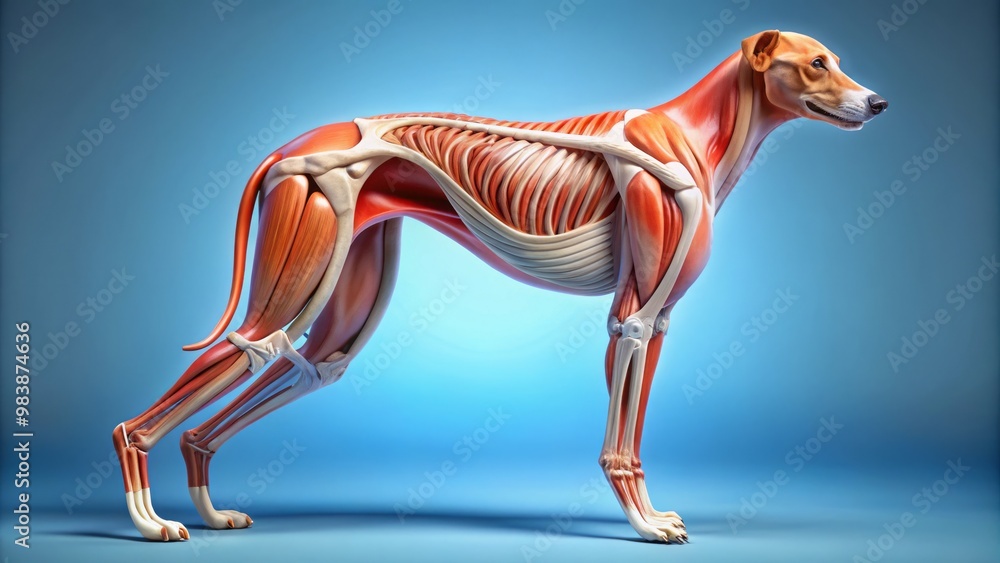
The first time I ran into this, I was looking at a German Shepherd who couldn't extend her stifle properly after a long ride home from the vet. She'd been fine the morning of, but by afternoon she was walking stiff, favoring the right hind leg. Turns out it was the biceps femoris tendon. Not torn. Just inflamed from some weird combination of being confined in the car and sleeping on a cold concrete floor the night before. If you're trying to understand what went wrong, you have to know the anatomy first. Really know it. When I teach veterinary students how to study Dog Anatomy Muscles And Tendons, I tell them to stop using those cheap atlas books with watercolor illustrations. You need cadaver dissection photos or, better yet, ultrasound images showing the structures in cross-section. The textbooks get the relationships wrong way too often. I've seen three editions of the same textbook that depicted the semitendinosus origin differently. It starts on the ischial tuberosity, not the pubis. They just copied each other's mistakes for decades.
Studying Dog Anatomy Muscles And Tendons Without Wasting Months
Here's what actually works. Pick one limb. Just one. Start with the left hind leg because it's closer to your heart when you're dis'ecting and less intimidating for your first go. You'll need a fresh cadaver if you can get one from your local vet school — call the pathology department directly, don't go through the registrar's office. They keep a cooler out back and will often hand you one without making you fill out any forms. Start superficial. Define the skin incision line from the tuber coxae down the lateral thigh to the calcaneus. You're laying up the subcutaneous tissue now. Notice how the fascia lata — that's the tough connective tissue sheet — wraps around the entire limb like cellophane. It's continuous with the thoracolumbar fascia on the back. This matters because inflammation here can refer pain all the way up to the loin region. I learned that the hard way with a Doberman who was showing signs of lower back pain for six months. The actual source was a chronic myositis of the biceps femoris that tracked along the fascia lata into the lumbar region. Six months. Six months of unnecessary steroid treatments because nobody palpated the thigh properly. Now you're peeling back the deep fascia. The gluteal muscles are your next landmark. The middle gluteus is the big one — it's what people call the "hamstring" when they're pointing at a dog's rear. It's not a hamstring. It inserts on theGreater trochanter of the femur and on the fascia lata. The tensor fasciae latae, which sits cranial to it, inserts into the fascia lata and then continues distally as the iliotibial tract. That tract blends with the lateral head of the biceps femoris. When you're trying to figure out lameness originating in that region, you can't treat these as separate structures. They're a kinetic chain and they fail together.
I spent two years working in a sports rehab clinic for dogs before I ever saw someone diagnose a tensor fasciae latae strain correctly. Everybody called it a hamstring injury. The treatment was always wrong because they were stretching the semitendinosus and semimembranosus when the real problem was the TFL pulling on that iliotibial tract. The telltale sign was a horse stance in the hind limbs and difficulty getting up from a down position. The dog would stand with the legs spread wide apart instead of under the body. Once I started treating the TFL directly with targeted release work, those cases resolved in weeks instead of months.
Get the Full Details

The Major Muscle Groups and What They Actually Do
The quadriceps femoris group is the big extensor of the stifle. Four muscles: rectus femoris, vastus lateralis, vastus medialis, and vastus intermedius. The rectus femoris is the only one that crosses the hip joint as well, so it functions in both hip flexion and knee extension. When a dog is sprinting, this muscle fires in rapid concentric-eccentric cycles. The vasti do pure knee extension. If you're palpating for soreness after exercise, the vastus intermedius sits deepest and is the hardest to reach. You feel it through the other three. Most soft tissue injuries in this group go undetected because the superficial muscles take the brunt of the manual examination. The hamstring complex on the caudal thigh consists of the biceps femoris, semitendinosus, and semimembranosus. The biceps femoris has two heads — the cranial (fleshy) head and the caudal (tendinous) head. That tendinous interface is a known failure point. I've seen avulsion injuries where the tendinous head separated from the fleshy head after a dog hit its caudal thigh against a gate while running backward. The dog was non-weight bearing on that leg for three weeks. Ultrasound showed the two heads completely dissociated with a hematoma between them. Surgery wasn't an option because of the dog's age, so we managed conservatively with strict confinement and NSAIDs. It healed, but the range of motion never fully returned to the contralateral side. Atrophy of the caudal thigh musculature was permanent. The owner noticed it more than anyone else at the dog park. The adductor group along the medial thigh is almost never examined during a routine orthopedic assessment. Adductor longus, magnus, and brevis — they originate from the pubis and ischium and insert along the linea aspera of the femur. Their job is adduction and hip flexion. Dogs rarely present with primary adductor injuries because the surrounding muscles compensate so well. But when you see a dog that can't bring its hind leg fully under its body when standing up, especially after a pelvic fracture repair, think about the adductors. scar tissue from the surgery can tether them and limit their glide.
On the lateral aspect, the iliopsoas deserves more attention than it gets. It's the primary hip flexor and it originates from the lumbar vertebrae and the iliac fossa. The psoas minor and psoas major merge to form a single tendon that passes under the inguinal ligament and inserts on the lesser trochanter. Lumbar disc disease can irritate this muscle because of its lumbar origin. A dog with a L6-S1 disc extrusion might present with hind limb weakness that looks exactly like a myopathic problem. The difference is you'd see pain on cervical and lumbar manipulation, and the iliopsoas would be hypersensitive to palpation in the cranial thigh. I once misdiagnosed this in a border collie. Treated her for presumed myositis for two months before getting an MRI. The disc was compressing the lumbosacral trunk. Two months of pointless steroid injections on top of the real problem.
Tendon Insertions and the Places They Fail
Tendons are where the rubber meets the road, literally. They transfer muscular force to bone and they fail at predictable points. The patellar tendon — technically the patellar ligament since it's a continuation of the quadriceps tendon — runs from the patella to the tibial tuberosity. Rupture here is rare in dogs unless there's concurrent patellar luxation or a penetrating wound. More common is chronic degradation from repetitive microtrauma in high-drive breeds. I've seen Labrador retrievers with thickened, nodular patellar ligaments that weren't painful on palpation but caused abnormal stifle tracking. The dog was subtly off when landing from jumps. Owners dismissed it as "just getting older." It wasn't. It was tendinosis. Degeneration without inflammation. Steroids make this worse because they suppress collagen synthesis. You need controlled eccentric loading protocols to remodel the tendon. That's a whole different conversation. The Achilles tendon — the common calcaneal tendon formed by the gastrocnemius and the superficial digital flexor, with contribution from the plantaris in some dogs — is the most clinically significant tendon in the hind limb. Rupture or attenuation here means the dog can't plantarflex the hock. The hock drags on the ground when the dog lifts its leg. You'll see a characteristic crouched posture because the hock can't extend properly during weight bearing. Complete ruptures need surgical repair. Partial ruptures are a gray area. I've managed partial tears conservatively in working dogs where surgery would mean time off the field anyway. Strict rest, then progressive loading. The tendon heals in a disorganized fashion no matter what you do, so the goal is to align the collagen fibers as much as possible through controlled mechanical stress. The supraspinatus tendon at the shoulder is another notorious failure point. It passes through the narrow subacromial space and gets impinged during extreme abduction. In dogs, this usually shows up as intermittent lameness that comes and goes over months. The owner notices it after vigorous exercise and assumes the dog just pulled a muscle. But the supraspinatus doesn't recover like skeletal muscle does. Tendons have poor blood supply. The intratendinous variety of calcification that develops over time — enthesiopathy — is basically permanent. We can manage the inflammation but we can't reverse the structural change. I stop recommending strenuous activity to dogs with confirmed supraspinatus tendinopathy. Swimming is the exception. The reduced weight bearing and the range of motion in water don't load the tendon the same way.
Practical Examination Tips
When you're learning Dog Anatomy Muscles And Tendons through hands-on work, palpation technique matters more than you'd think. Don't just press. Slide your fingers along the muscle belly in the direction of the fiber orientation. You're feeling for nodules, thickening, or areas that are hotter than the surrounding tissue. A normal muscle should feel uniformly firm and elastic. If you encounter a discrete nodule that moves independently of the surrounding tissue, that's likely intramuscular fibrosis or a calcified focus from prior trauma. Note it. Track it over time. If it grows, it needs imaging. The goniometer is useful but most people misuse it. You need to stabilize the proximal segment before measuring joint angles. If the dog shifts its pelvis while you're trying to measure stifle flexion, your numbers are garbage. I use a partner or just have the dog in lateral recumbency with the limb being examined on top. Gravity holds everything in place. Measure both limbs every time. The difference between left and right is more informative than the absolute angle on either side. Ultrasound has changed how I approach this entirely. Twenty years ago, diagnosing a muscle tear meant waiting for the dog to heal enough for the swelling to resolve so I could palpate the defect. Now I can see the tear on day one. The muscle fibers appear discontinuous with hypoechoic material between them — that's the hemorrhage and edema filling the gap. I can measure the extent of the injury and give the owner a realistic timeline. Grade one strains typically resolve in three to four weeks with relative rest. Grade two, meaning partial thickness with some fiber disruption, takes six to eight weeks. Grade three, complete rupture, is surgical territory and the prognosis depends on which muscle is involved. The gastrocnemius has a better healing potential than the biceps femoris because of its vascularity.
One thing I wish everyone learning this subject understood: the myofascial connections are real and they matter clinically. The thoracolumbar fascia continues as the superficial fascia of the hind limb. Tension in the back can alter the biomechanics of the entire rear end. I had a case where a boxer was being treated for recurrent right hind limb lameness that kept coming back no matter what we did. All the local treatments failed. Turns out the issue was chronic tension in the thoracolumbar region from a poorly fitted saddle on a cart it pulled for years. The myofascial line was so tight that it was chronically shortening the caudal thigh muscles. Once we addressed the back with manual therapy and adjusted the cart setup, the lameness stopped recurring. Local treatment alone would have kept failing because the root cause was upstream. If you want to actually retain this information instead of memorizing it for a test and forgetting it, dissect the structures yourself or watch detailed dissection videos at real speed, not the sped-up ones. Listen to the sound of the scalpel separating tissue planes. That auditory feedback tells you when you're in the right layer. Fascia sounds different from muscle. Muscle sounds different from fat. You develop a sense for it. I've seen students who could name every muscle from a diagram but couldn't identify the correct tissue plane during dissection. Reading and doing are different skills. You need both. The biggest mistake I see people make is studying muscles in isolation. A dog doesn't walk with individual muscles. It walks with coordinated chains. The superficial hind limb muscle layer, the deep hind limb muscle layer, the perineal muscle group — they all interact. When you learn Dog Anatomy Muscles And Tendons, learn the layers and learn how they slide past each other. A muscle that can't glide within its fascial envelope is a muscle that will fail under load. That's the practical takeaway. Everything else is detail.


