Locating the Jugular Vein in Canines
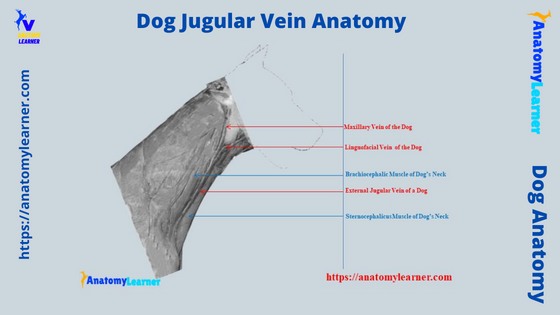
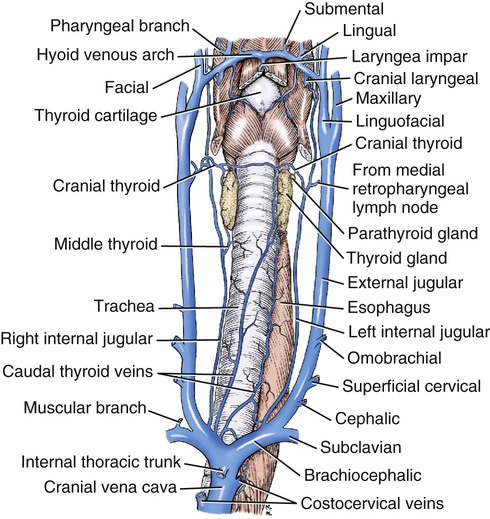
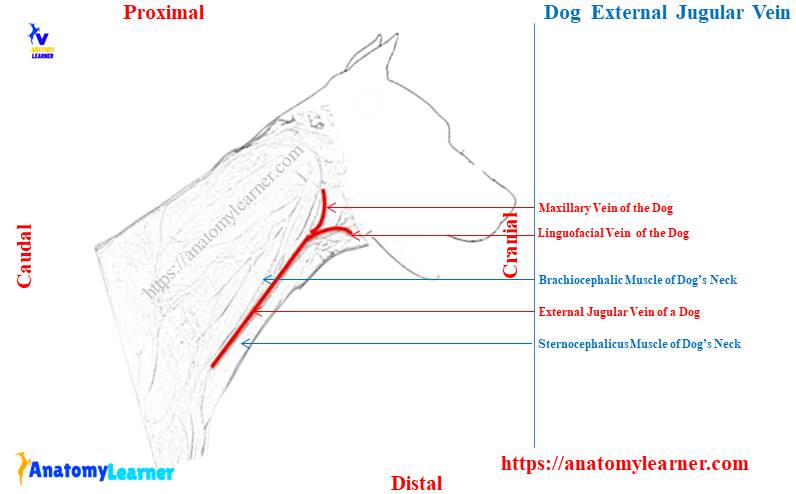
The jugular vein sits right where you'd expect it, but that doesn't make it easy to access. In dogs, the right external jugular vein is the standard choice for venipuncture because it's larger and more superficial than the left side. The vessel runs along the ventral neck within the jugular groove, bordered medially by the sternothyrohyoideus muscle and laterally by the sternocephalicus. You palpate it along that groove from the base of the ear down toward the shoulder. A healthy vein will feel like a soft, compressible tube under the skin. If it's rolling or not easily collapsed, you've missed it and need to reposition your fingers slightly. I've spent years doing this on everything from Chihuahuas to Great Danes, and the variance in anatomy between breeds is something people don't talk about enough. A Greyhound's jugular is nearly subcutaneous and visible at rest. A Bulldog's neck is so short and muscular that the vein often lies deeper and requires more pressure to localize. I once had a case with an obese Maltese where the jugular groove was completely obscured by adipose tissue. I couldn't palpate the vein at all. What I ended up doing was positioning the dog in sternal recumbency with the head slightly lowered, which uses gravity to distend the vein, then I used a Doppler probe to locate the flow. That took about three minutes that otherwise would have been fifteen minutes of blind pokes.
Common Pitfalls in Dog Jugular Vein Anatomy
The biggest mistake beginners make is confusing the carotid artery with the jugular vein. They run parallel in the same sheath, and on a tense or anxious dog, the carotid can feel surprisingly compressible. The difference is pulse. Always confirm absence of a pulsation before introducing a needle. I saw a vet tech once aspirate bright red blood from what she thought was the jugular. It was the carotid. She applied pressure for ten minutes and the dog was fine, but it was an unnecessary scare for everyone involved. Another issue is the jugular fold. In some dogs, especially large breeds, the skin over the jugular groove forms a loose fold when the neck is extended. If you're not careful, you can miss the groove entirely and stick into subcutaneous tissue above it. Keep the neck in a neutral position or slightly extended, not fully stretched out. The vein distends best when the head is level with or slightly below the heart, which increases venous pressure and makes the vessel easier to target. The left jugular is smaller and often more tortuous than the right. I only use it when the right side is compromised, such as from previous IV catheter placement or thrombosis. The anatomy is the same on both sides, but the left vein has a more acute angle as it approaches the thoracic inlet, which makes cannulation technically more difficult. If you're placing a long-term catheter and need to choose a side, right every time unless there's a specific reason not to.
Catheter Placement Technique
Shave a small area, about two centimeters by four centimeters, along the middle to distal third of the jugular groove. Clip rather than shave if the dog will need repeated access, because regrowth is faster and the hair doesn't get trapped against the skin. Restrain the dog with the neck extended but not stretched. For a standing restraint, have an assistant stand on the opposite side of the vein you're targeting and gently pull the head away from you. This keeps the vein taut and accessible. Palpate the vein with your non-dominant hand. Use your thumb and index finger to compress the vein proximal to your intended insertion site. You should see distension below your fingers. Once you've confirmed the location, clean the area with alcohol or chlorhexidine and let it dry. Hold the skin caudal to the insertion site between your thumb and middle finger to stabilize it. The skin over the jugular is loose, so if you don't anchor it, the vein will roll when you introduce the needle. Insert the catheter at a 15 to 30 degree angle, bevel up, advancing toward the heart. You'll see a flash of dark blood in the chamber almost immediately if you're in the lumen. Advance the catheter another centimeter or so to ensure the entire tip is inside the vein, then lower the angle to nearly parallel with the skin and slide the catheter off the needle. A common failure point here is advancing the needle too deeply after the flash. Once you pass through the far wall of the vein, you won't get aspiration on the next attempt without repositioning. Pull back slightly if you lose flashback and redirect.
Get the Full Details
Secure the catheter with a commercial jugular wrap or adhesive strips. The neck is a high-movement area, so standard tape patterns fail within hours. I use a figure-eight pattern around the neck with porous surgical tape, followed by a light layer of veterinary wrap. Change the dressing every 48 to 72 hours depending on the patient's condition and whether there's any serosanguinous exudate. Catheters placed in the jugular typically remain functional for five to seven days with proper care, though some clinics replace them sooner as a routine protocol.
Anatomical Variations and Complications
jugular vein anatomy varies significantly between individual dogs, and certain conditions make venipuncture considerably harder. Brachycephalic breeds have shortened, thick necks where landmarks are compressed and the jugular groove is less defined. In these cases, ultrasonography-guided access is worth learning. Even a basic portable ultrasound unit lets you visualize the vein in real time and eliminates the guesswork entirely. Dehydrated dogs present a different challenge. Their jugular veins collapse and may not distend even with proper compression. I check venous refill time before attempting jugular access in any patient that looks dehydrated. Press on the vein for five seconds, release, and watch how quickly it refills. If it takes more than three seconds, the dog is likely dehydrated enough to make jugular access unreliable. Go for a saphenous or cephalic alternative instead. Thrombophlebitis is the most serious complication of jugular catheterization. The incidence in veterinary practice is low, maybe one to two percent of long-term catheter cases, but when it occurs it's serious. Signs include swelling along the neck, pain on palpation, and sometimes a palpable cord along the vein. If you suspect thrombophlebitis, remove the catheter immediately, apply warm compresses, and start anti-inflammatory treatment. Most cases resolve within a week, but severe thrombosis can lead to septic thrombophlebitis, which requires aggressive antibiotic therapy and sometimes surgical intervention.
Jugular vein rupture is rare but catastrophic. It happens when the needle passes completely through the vein, usually during blind advancement after flashback is lost. Blood accumulates in the surrounding tissues and can compromise the airway if the hematoma is large enough. The immediate response is firm direct pressure. Don't release it to check for bleeding. Maintain pressure for at least five minutes, then reassess. In severe cases, surgical exploration and ligation may be necessary, but most ruptures stop with sustained pressure alone.
Practical Notes
The jugular vein remains the preferred site for central venous catheter placement in critical patients because it provides direct access to the caudal vena cava and right atrium. Pressure readings taken from a jugular catheter are reliable for monitoring central venous pressure, which is valuable in cases of fluid overload, cardiac disease, or shock. The measurement should be taken with the dog in lateral recumbency and the transducer aligned with the right atrium, which is located at the level of the fourth intercostal space. For routine blood collection, the jugular is fast and efficient. A single puncture yields enough volume for a full biochemistry panel, complete blood count, and additional tests in most adult dogs. I typically draw from the catheter after flushing with heparinized saline, discarding the first one or two milliliters to avoid contaminating the sample with flush solution. This is faster than attempting cephalic or saphenous draws in a restrained or stressed dog, and it reduces hemolysis risk because the larger bore of the jugular vein produces smoother blood flow through the needle. One thing to keep in mind is that jugular venipuncture is contraindicated in dogs with significant coagulopathy. The vein is large and the surrounding tissue is loose, so bleeding can be extensive and difficult to control. I check a clotting profile or at minimum a buccal mucosa bleeding time before proceeding in any patient where coagulopathy is suspected. If the dog is on anticoagulant medication, that's a contraindication until the drug clears the system or the indication for testing outweighs the bleeding risk, which is a clinical judgment call.