Understanding the Framework
Most people approaching Domestic Violence And Psychology A Critical Perspective start from the wrong angle. They expect psychology to provide a clean diagnostic checklist for identifying abusers or predicting escalation. It doesn't work that way. The research literature treats domestic violence as one of the most complex intersection points in clinical psychology, and for good reason. You're dealing with power dynamics, trauma bonding, co-occurring personality disorders, substance abuse, and structural barriers all at once. The psychology doesn't neatly separate from the sociology here. I spent years working with survivors and perpetrators in clinical settings before I stopped trying to force these frameworks into neat boxes. The first thing I learned is that standard psychological assessment tools were largely built on white, middle-class samples and don't translate well across cultures or socioeconomic groups. The CTS2 (Conflict Tactics Scale), which is the most commonly used instrument in both research and some clinical settings, has been heavily criticized for missing the contextual meaning behind behaviors. A shove recorded on a survey sheet isn't the same thing as understanding the pattern of isolation, financial control, and intermittent reinforcement that actually defines the abuse.
Domestic Violence And Psychology A Critical Perspective
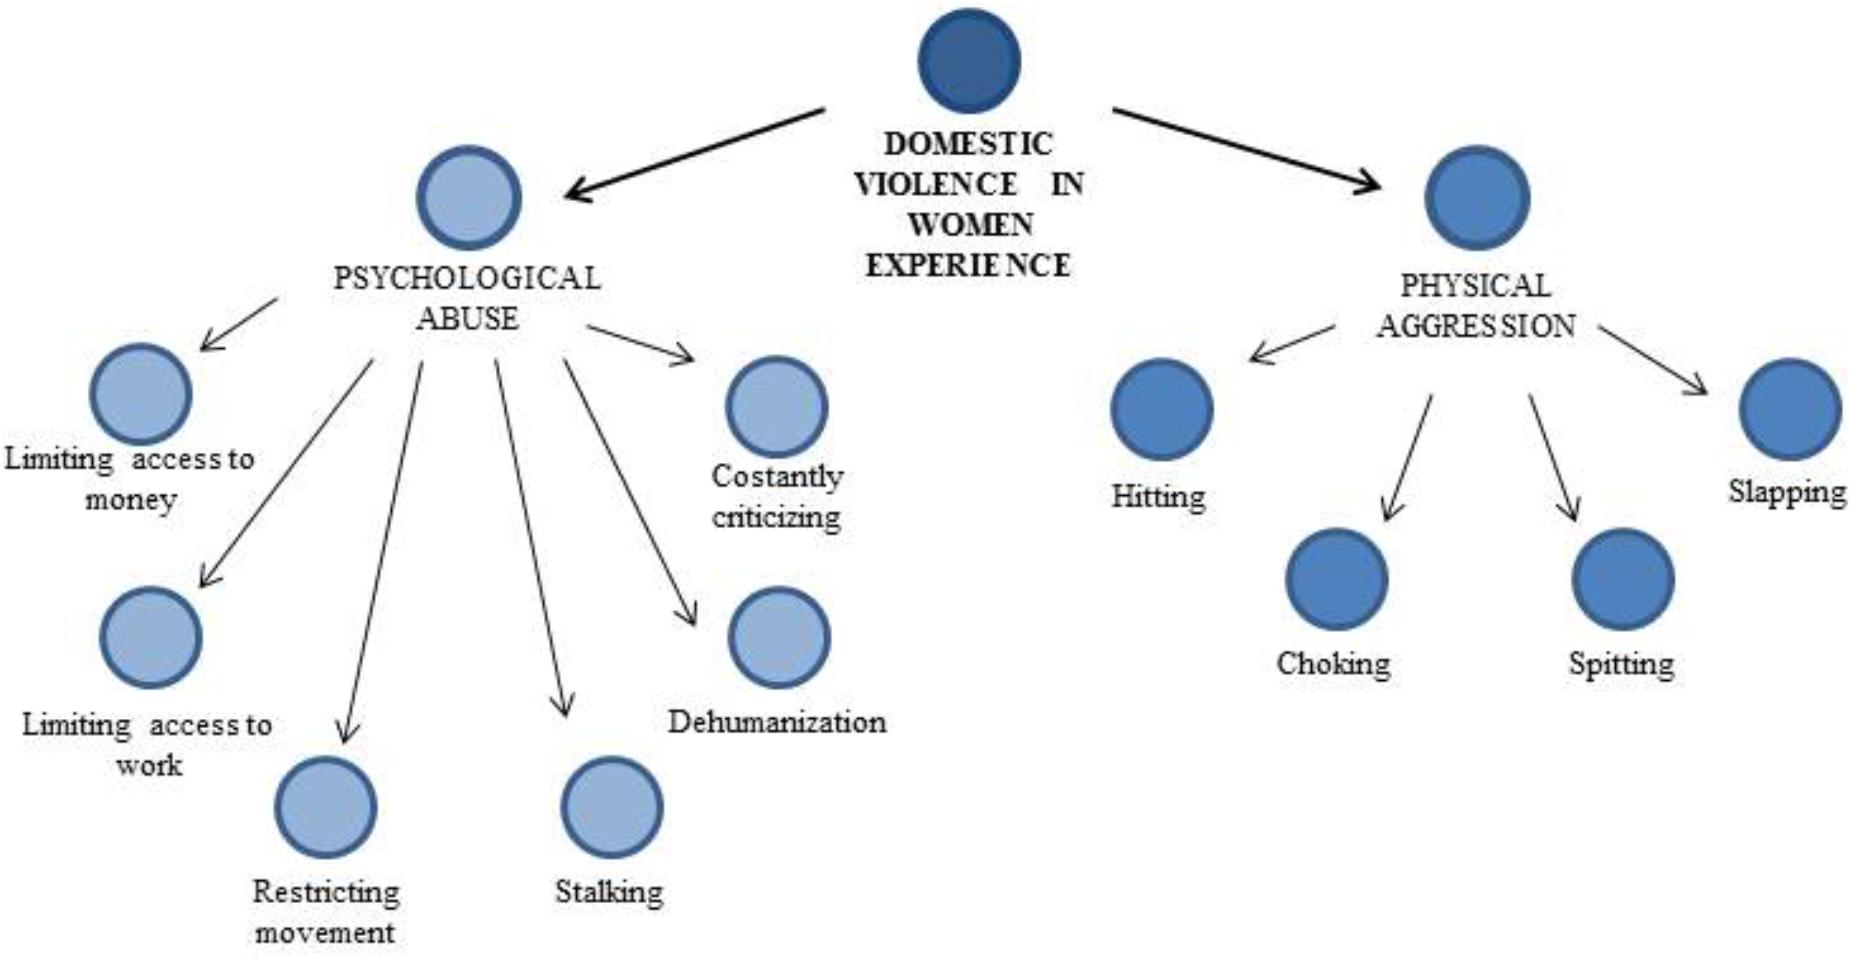
This critical perspective emerged primarily from feminist psychology and intersectional theory in the late 1980s and 1990s. Scholars like Evan Stark, Diana Russell, and Patricia Pearson challenged the dominant psychological models that framed domestic violence as a conflict resolution problem or a product of individual psychopathology. Their argument was straightforward and still mostly correct: you cannot understand intimate partner violence through standard clinical psychology alone because the standard models ignore power, gender, and structural inequality. Stark's concept of coercive control became particularly influential. He argued that what makes domestic violence abusive isn't primarily the physical violence itself but the pattern of domination that orchestrates it. Isolation from support networks, monitoring of daily activities, economic control, psychological intimidation, and reproductive coercion form a system of control that physical assault alone doesn't capture. Most standard psychological risk assessment tools still miss this entirely because they weight physical violence far too heavily compared to non-physical control tactics. There's a practical implication for anyone doing this work. If you're assessing risk using only tools like the SARA (Spousal Assault Risk Assessment) or the ODARA (Ontario Domestic Assault Risk Assessment), you're getting a snapshot that leans heavily toward acute physical violence. A survivor might not have been physically assaulted in months, but the coercive control could be intensifying. I saw this exact scenario play out in a case where a man had zero physical assault records over two years of documented interactions. He had, however, systematically destroyed his partner's ability to maintain employment, cut off her from her family, and made repeated threats that were carefully worded to avoid police involvement. She was killed six months after her last police report. The risk tools said low risk. The pattern said otherwise.
How the Framework Actually Works in Practice
The critical perspective shifts the clinical question from "what's wrong with this person" to "what system is producing this behavior." That sounds like a minor semantic change but it completely alters assessment, intervention, and treatment approaches. Individual therapy models that focus on anger management or emotion regulation for perpetrators tend to have abysmal recidivism rates because they treat the symptoms while ignoring the function. A 2019 meta-analysis in the Journal of Interpersonal Violence found that standard anger management programs showed no significant reduction in reoffending compared to control groups. Duluth-based or power-and-control informed programs showed marginally better outcomes, but even those have limitations I'll get to. For survivors, the critical perspective changes how you understand their responses. Trauma bonding isn't a clinical diagnosis you'll find in the DSM. It's a colloquial term that describes something real but gets misused constantly. The actual clinical construct closer to what people mean is traumatic attachment, which involves the intermittent reinforcement cycle that creates trauma bonds. When an abuser alternates between cruelty and affection, the victim's nervous system becomes dysregulated in a way that mirrors addiction. The dopamine spikes during reconciliation phases create genuine neurochemical dependency. This isn't weakness or poor judgment. It's a predictable biological response to an unpredictable environment. Here's where the critical perspective gets uncomfortable for traditional psychology. Many evidence-based treatments for trauma, including certain modalities of EMDR and prolonged exposure therapy, assume a linear trajectory of recovery where the threat is removed and the nervous system can process the trauma. Domestic violence complicates this because the threat often isn't removed. Survivors may remain economically dependent, share custody of children, or live in housing situations where separation isn't immediately possible. I had a client who completed a standard trauma protocol and then went back to her abuser because she had nowhere else to go and no money. The therapy hadn't accounted for material reality. It treated her return as a relapse rather than what it actually was: a rational survival decision.
Get the Full Details

The Counter-Intuitive Stuff Beginners Miss
The biggest misconception I see repeated in introductory courses is that domestic violence predominantly occurs in low-income households. The data doesn't support this. Research consistently shows that intimate partner violence crosses all socioeconomic lines, though reporting patterns and access to resources vary significantly by class. What does vary by socioeconomic status is which form of violence is more likely to be reported and how the system responds. Wealthier survivors have more access to private legal counsel, private therapy, and alternative housing. They also face different barriers to disclosure, including professional reputation concerns and greater financial entanglement. Another counter-intuitive finding is about gender and perpetration. The Conflict Tactics Scale research by Murray Straus and others found surprisingly symmetrical rates of violence between men and women in general population samples. This became a massive controversy in the field. The critical perspective argues that this symmetry is an artifact of how violence is measured rather than a reflection of reality. Women do initiate physical violence at comparable rates in some surveys, but the context, motivation, and consequences are radically different. Male-initiated violence is far more likely to result in injury, to occur within a broader pattern of control, and to cause lasting psychological harm. Women's physical aggression in relationships is more often defensive or reactive. The critical perspective doesn't deny female perpetration exists. It insists that treating symmetrical statistics as evidence of symmetrical harm is analytically fraudulent. There's also the issue of comorbid personality disorders. BPD gets thrown around carelessly in this context. Some practitioners will pathologize a survivor's justified anger or hypervigilance as borderline traits. The critical perspective demands careful differential diagnosis. Trauma symptoms and personality disorder symptoms overlap substantially, and a survivor who developed paranoid ideation in response to an actual monitoring abuser isn't experiencing a personality disorder. They're experiencing adaptive vigilance in a dangerous environment. I've seen this misdiagnosis lead to survivors being told their abuse allegations weren't credible because they had "personality pathology."
What Actually Helps and What Doesn't
Perpetrator intervention programs that incorporate the power-and-control framework show some promise but have real bottlenecks. The main issue is voluntary versus mandated attendance. Men who volunteer tend to have higher motivation and better outcomes than those court-mandated. But court-mandated participants make up the majority of program enrollment. Attrition rates for mandated programs are typically between 40 and 60 percent. The men who complete the full program show modest reductions in violence, but the effect sizes are small and durability beyond two years is questionable. For survivors, the most evidence-supported interventions focus on safety planning rather than traditional trauma processing in the acute phase. The Nurse-Family Partnership and several demonstrated safety planning interventions show reduced injury rates when survivors receive structured safety assessments and personalized exit plans. This isn't therapeutic in the traditional sense but it's where the evidence actually points. Trauma therapy comes later, if at all, and only after the survivor is in a stable environment. I want to be blunt about what doesn't work because I've seen it cause harm. Couple's therapy is contraindicated in almost all cases of ongoing domestic violence. The research is clear on this. Framing IPV as a relationship problem that can be solved through communication training gives the abuser a platform to continue manipulation and puts the survivor at increased risk. There are narrow exceptions in long-term relationships where the violence has completely ceased and both parties understand the power dynamics, but those are rare. Most practitioners who recommend couples therapy for IPV are either misinformed or ignoring the safety implications.
Practical Application for Clinicians and Advocates
If you're working in this space, the critical perspective should change how you ask questions during assessment. Instead of leading with "has there been any physical violence," start with behavioral questions that map onto coercive control. Ask about monitoring, isolation, financial control, and threats. Ask about how decisions are made in the relationship. Ask about the partner's access to communication devices and transportation. These questions take thirty seconds longer but they reveal patterns that standard screening tools miss. Documentation matters more than you might think. I worked with a survivor whose restraining order was dismissed because her prior reports showed periods where she had contact with her abuser. The judge interpreted those contacts as evidence the abuse wasn't severe. Those contacts occurred during cycles of reconciliation that are well-documented in the literature. Her own therapist had noted the cycle in clinical notes but the legal system didn't have access to those notes in the same way. Keeping detailed, timestamped records of incidents and behavioral patterns can be the difference between a survivor being believed and being discredited. The intersectionality piece is non-negotiable. A Black survivor faces different barriers than a white survivor. An undocumented survivor faces different barriers than a citizen. A transgender survivor faces barriers that most mainstream DV programs aren't equipped to handle. The critical perspective requires you to examine your own assumptions about what abuse looks like and who victims are. The stereotype of the battered woman in rural America with a broken nose and an alcoholic husband is real but incomplete. It excludes enormous populations of survivors who don't fit that image and therefore don't get help.

The Hard Limitations
Psychology as a discipline has real blind spots when it comes to domestic violence. It tends to individualize what is fundamentally a structural problem. No amount of trauma-informed therapy can compensate for lack of affordable housing, inadequate legal protections, or economic dependence. The field also struggles with its own history of pathologizing survivors. The hysteria about false abuse allegations in the 1980s and 90s, though largely debunked, left a residue of skepticism that still influences practice. False reporting rates for domestic violence are estimated at 2 to 10 percent, comparable to other crimes, yet survivors continue to face heightened scrutiny. The critical perspective also has its own limitations. It can sometimes flatten individual variation in favor of structural analysis. Not every abusive man is motivated by a desire for patriarchal control. Some are driven by pathological jealousy, substance abuse, or untreated mental illness. The framework doesn't erase those factors but it does risk overcorrecting toward structural explanations at the expense of individual accountability. The best practitioners I've worked with hold both truths simultaneously: the structural context matters enormously, and individual responsibility still exists. If you're looking for resources, the National Coalition Against Domestic Violence and the Love Is Respect platform offer evidence-based guides. The book Why Does He Do That? by Lundy Bancroft remains one of the more accessible treatments of the power-and-control framework, though some of its gender-specific claims have been debated. For the clinical side, the journal Violence Against Women publishes the most rigorous research in the field. The critical perspective isn't a therapy model you can certify in. It's a lens. And like any lens, it reveals certain things clearly while leaving others in shadow.