Understanding the Layout of the Human Trunk
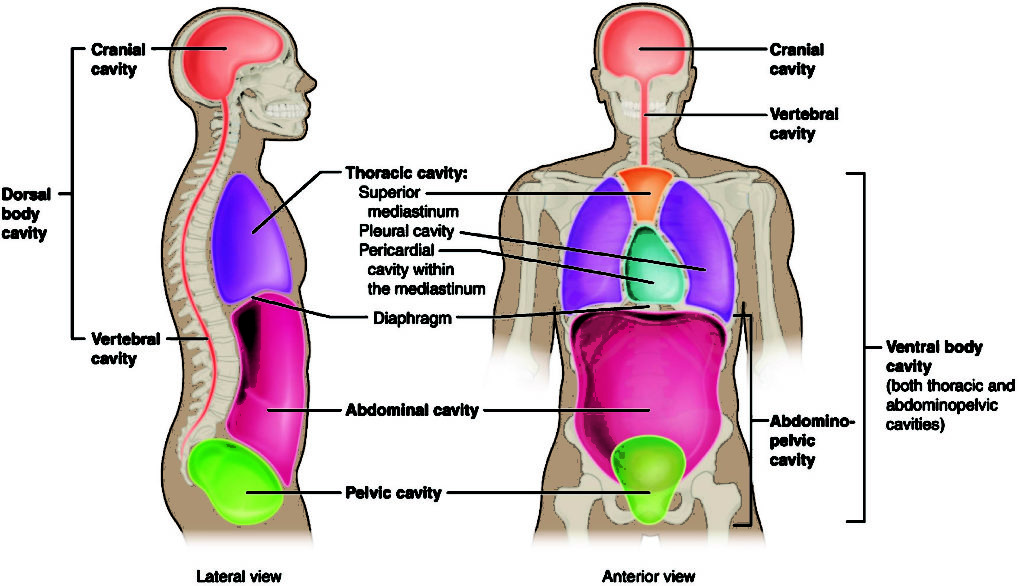
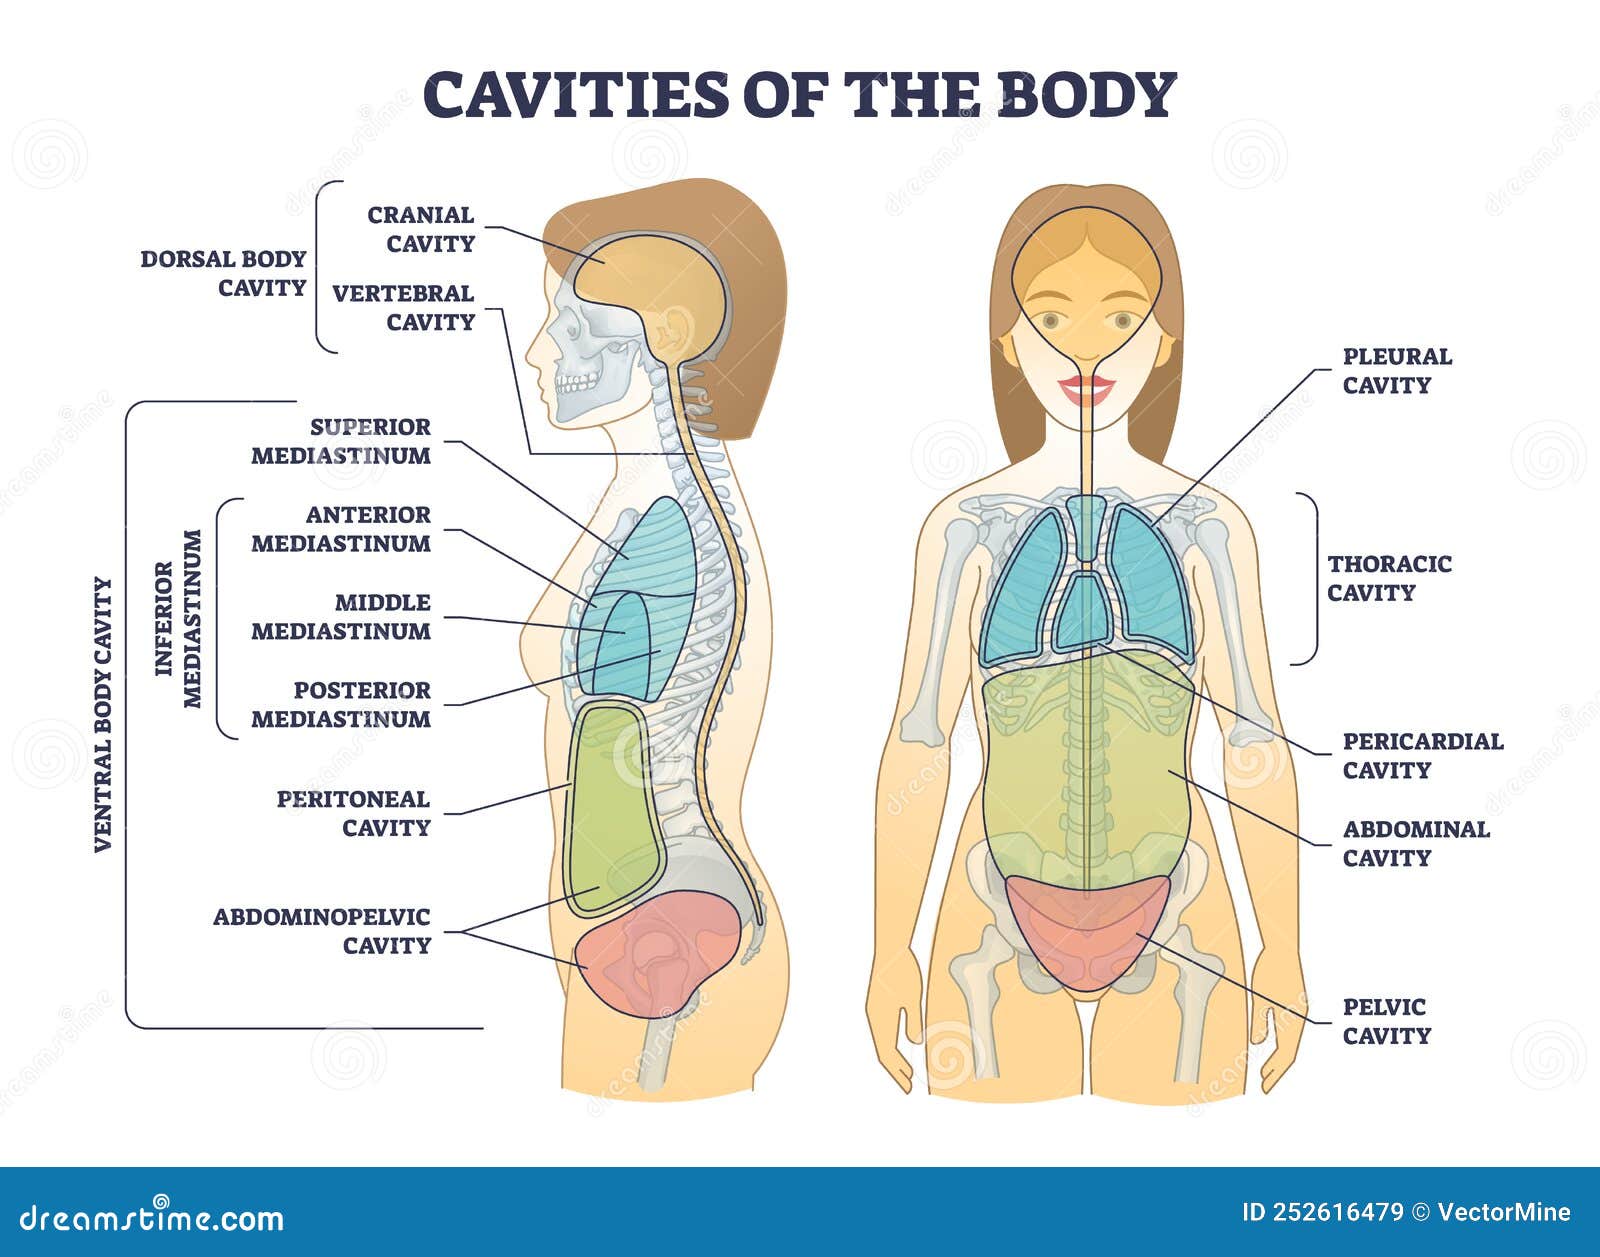
The body is essentially a tube within a tube, and the cavities are just the lined spaces inside those tubes. When I first learned this in undergrad, I kept drawing them as separate rooms rather than continuous compartments, which made everything confusing during practical exams. The reason people struggle with Dorsal And Ventral Body Cavities isn't because the concepts are hard — it's because textbooks present them as five isolated flashcard terms instead of one connected system.The ventral cavity sits on the anterior side of the trunk and is the larger of the two main spaces. It's divided by the diaphragm into the thoracic cavity above and the abdominopelvic cavity below. The dorsal cavity runs along the posterior midline and houses the neural tissue. That's the basic map. What people usually miss is how the serous membranes actually line these spaces, because that detail shows up repeatedly in dissection labs and imaging reports.
Dorsal And Ventral Body Cavities: The Membranes That Make It Work
Each organ within the ventral cavity is wrapped or backed by a double-layered serous membrane. The parietal layer lines the cavity wall. The visceral layer adheres to the organ surface. Between them sits a thin film of serous fluid that reduces friction during movement. This arrangement applies uniformly across the pleural, pericardial, peritoneal, and tunica vaginalis spaces.I remember spending an entire lab session trying to identify whether a particular serous sac was parietal or visceral just by looking at its attachment point. The answer came down to whether the membrane was anchored to the body wall or hugging the organ itself. That distinction matters clinically. If you're reading a CT scan and someone mentions a pleural effusion, you now know exactly where that fluid accumulates — between the parietal and visceral pleura, pushing them apart. The meninges themselves have three layers. The dura mater is the tough outer layer. The arachnoid mater sits in the middle. The pia mater clings directly to the brain and spinal cord surface. During lumbar punctures, the needle passes through all three to reach the subarachnoid space where cerebrospinal fluid collects. This is typically performed at the L3–L4 or L4–L5 interspace to avoid injuring the spinal cord, which usually terminates around L1–L2 in adults. A common misconception is that the dorsal cavity is just a protective shell with no functional complexity. In reality, the flow dynamics of cerebrospinal fluid through the ventricles and subarachnoid space are tightly regulated, and blockages here can cause hydrocephalus within hours. I once watched a resident misinterpret a non-contrast CT because they forgot that the ventricular system sits within the cranial cavity, not separate from it. The enlarged lateral ventricles were the first clue.
The Ventral Cavity Breakdown
The ventral cavity splits at the diaphragm into two distinct zones. The thoracic cavity holds the heart, lungs, thymus, esophagus, and major vessels. The abdominopelvic cavity holds the stomach, intestines, liver, pancreas, spleen, kidneys, and reproductive organs. The division isn't arbitrary — it reflects embryological origin and innervation patterns that persist into adulthood.Within the thoracic cavity, the mediastinum is the central compartment that separates the two pleural sacs. It contains the heart within the pericardial cavity, the trachea, the esophagus, the thymus, and all the great vessels. The remaining thoracic space on each side belongs to the lung and its covering pleura. This is why a pneumothorax on one side doesn't immediately collapse the other lung — they're separated by both bone and soft tissue. The peritoneum deserves more attention than it gets. It's not just a wrapper around abdominal organs. It forms mesenteries that suspend the gut from the posterior wall, creating the omenta and ligaments that carry blood vessels and nerves. When surgeons operate on the small intestine, they're often working through or around these mesenteric attachments. A poorly placed incision can damage the vascular supply before you even reach the organ itself. I learned this the hard way during a simulation where I nicked a branch of the superior mesenteric artery instead of the intended access point.
Clinical Relevance You'll Actually Encounter
Knowing the cavity anatomy translates directly into diagnostic reasoning. Ascites, for example, is fluid accumulation within the peritoneal cavity. You detect it clinically by shifting dullness on percussion or visually on ultrasound. Pleural effusions follow the same logic but sit within the pleural space. Pneumoperitoneum — free air in the peritoneal cavity — typically indicates a perforated viscus and shows up as a crescent of radiolucency under the diaphragm on an upright chest X-ray.Epidermoid cysts and dermoid cysts sometimes develop along embryonic fusion lines within these cavities. I encountered one case where a retroperitoneal mass turned out to be a teratoma that had been sitting quietly for years before causing compression symptoms. The location alone — posterior to the peritoneal lining, within the dorsal aspect of the abdominal cavity — gave the first clue about its origin. The dorsal and ventral cavities also differ in their autonomic innervation. Thoracic and abdominal viscera receive sympathetic input from the thoracolumbar outflow and parasympathetic input primarily through the vagus nerve. The pelvis receives sacral parasympathetic contribution via the pelvic splanchnic nerves. This isn't just academic — it explains why cardiac pain refers to the left arm and chest wall, and why appendicitis starts as vague periumbilical discomfort before localizing to the right lower quadrant. Using cadaveric dissection or high-quality 3D anatomy software helps enormously. I used a platform called Complete Anatomy alongside my lab sessions, and being able to rotate the serous membranes in three dimensions made the parietal-visceral distinction click almost immediately. Textbook cross-sections flatten the relationships in ways that don't match what you see in reality.
Get the Full Details
If you're preparing for boards or clinical rotations, focus on the clinically actionable details: where fluid accumulates in each space, which organs are intraperitoneal versus retroperitoneal, and how cavity boundaries change during pathological states like herniation or distension. The rest is memorization that will stick if you've built the spatial framework first.


