Working With Ankle Motion: What Actually Happens When You Move
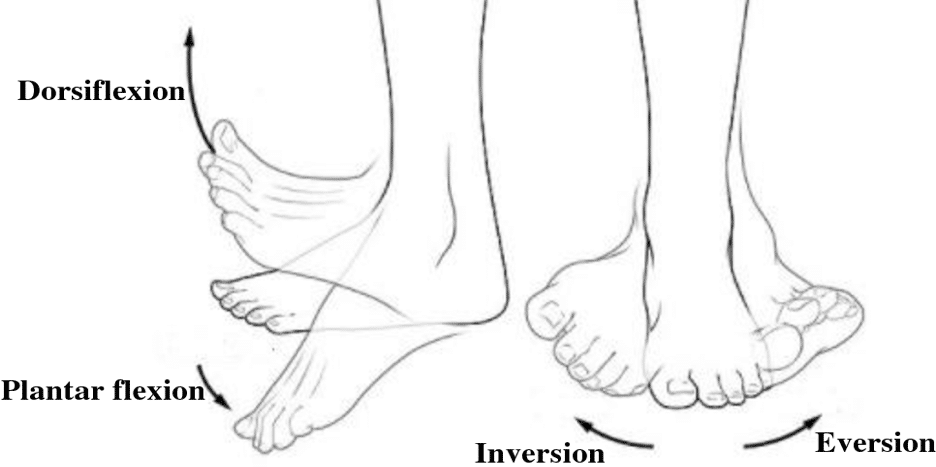
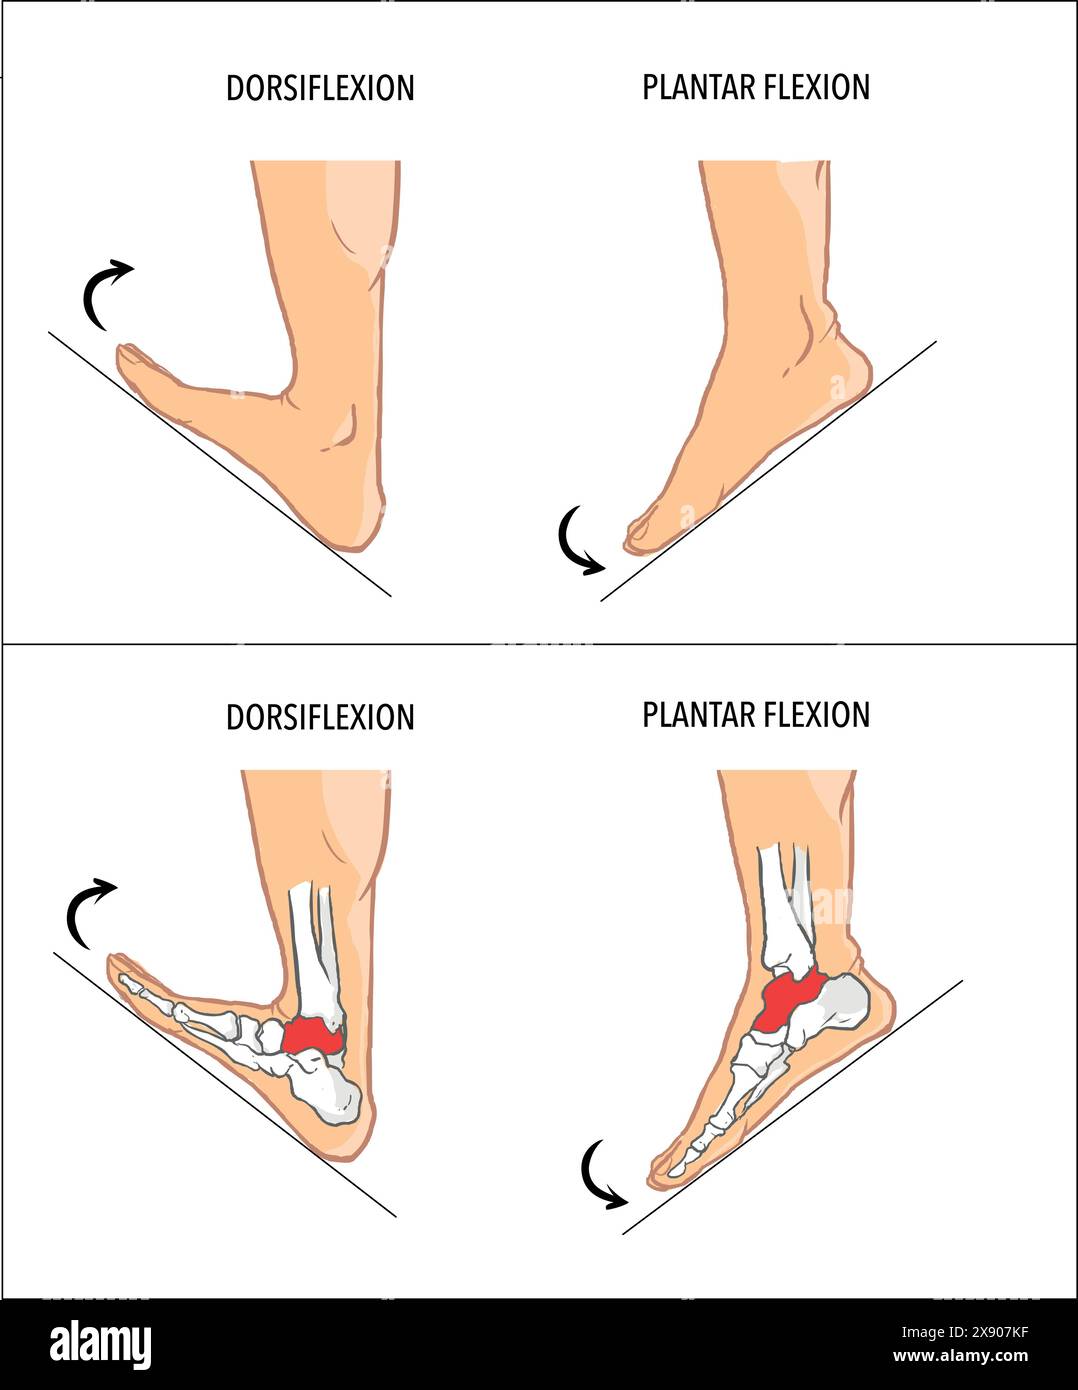
Dorsiflexion And Plantar Flexion are just medical terms for pointing your toes up versus down. That's it. Most people learn these terms in an anatomy class and then never think about them again until something breaks. The ankle joint is a hinge that rarely gets respect, and that's usually when people notice it. I'm going to walk through what these movements actually are, how to use them, and where things go wrong in practice. Dorsiflexion is when your foot pulls upward toward your shin. Your toes move closer to your face. Plantar flexion is the opposite - pushing away from your body like a ballet dancer standing on their toes or someone pressing down hard on a gas pedal. The talocrural joint, which is where the tibia and fibula meet the talus bone, is the primary structure involved. It's a synovial hinge joint, meaning it moves in one plane: up and down. Range of motion varies between individuals. Most people get about 20 degrees of dorsiflexion and 45 to 50 degrees of plantar flexion. Those numbers aren't set in stone. Athletes often exceed them. People who sit at desks all day rarely hit the lower end without effort. I measured my own ankle flexibility a few years back using a simple goniometer, and my dorsiflexion was sitting at about 12 degrees in my right ankle and 18 in my left. Asymmetry is normal. Significant asymmetry usually signals a problem somewhere.
How To Actually Train These Movements
Start with standing calf raises for plantar flexion. Stand on the edge of a step, lower your heels below the step level, then push up through the balls of your feet. Three sets of twelve reps works for most people. For dorsiflexion, wall ankle mobilizations are effective. Stand facing a wall with your foot about four inches away from it. Keep your heel down and drive your knee toward the wall without letting it cave inward. Push until you feel a stretch in the back of the ankle. Hold for thirty seconds and repeat three times per leg. Progression matters here. If your dorsiflexion is restricted, don't jump into squatting drills with deep knee bend. Your body will find another way to compensate, and that usually means your lower back or knees take over. I see this constantly in training facilities. Someone can't get their knee over their toe, so they either lean forward excessively or lift their heel off the ground. Both are workarounds that create secondary problems. Stick to the foundational movements first. Get the range. Then add load.
A Problem I Encountered With Restricted Dorsiflexion
A client came to me a few years ago with chronic Achilles tendon pain on the right side. His dorsiflexion was limited to about 5 degrees due to a stiff posterior capsule and a chronically tight gastrocnemius. Every time he tried to increase his squat depth, the pain flared up within two days. Standard stretching wasn't touching it. The issue wasn't just muscle tightness - it was joint quality. The workaround I used was a combination of weight-bearing ankle mobilizations with a band and prone calf stretches with the knee bent versus straight. Bending the knee isolates the soleus. Straightening it targets the gastrocnemius. Doing both for ten minutes daily, combined with slow tempo calf lowers, restored about 12 degrees of dorsiflexion over eight weeks. The Achilles pain resolved because the joint wasn't being forced beyond its mechanical limits anymore. It wasn't quick. It wasn't dramatic. It just worked.
Get the Full Details

Things Beginners Miss About Ankle Motion
Most people treat dorsiflexion and plantar flexion as independent movements. They're not. The subtalar joint and midfoot joints contribute to both. When your foot pronates - meaning the arch flattens and the talus drops - your ankle gains roughly 5 to 7 degrees of additional dorsiflexion through a mechanism called the windlass effect. This is why someone with flat feet might actually have decent dorsiflexion range while someone with a high rigid arch struggles. Arch structure changes the math. I've seen people with seemingly perfect form fail at basic ankle mobility because nobody checked their foot type first. Another counter-intuitive point: plantar flexion isn't just about the calf. The tibialis posterior, which sits underneath the calf, plays a role in controlling the rate of plantar flexion during the loading phase of walking and running. When it's weak or inhibited, the ankle collapses into excessive pronation during push-off, and the person ends up with what looks like good plantar flexion strength but poor control. Measuring strength without measuring control gives a false sense of security.
Where This Approach Falls Short
Simple stretching and mobilization don't fix structural limitations. If someone has a bony block in the ankle - an osteophyte or a talus with abnormal shape - no amount of stretching will increase range. The bone physically prevents further movement. I've had clients who spent months trying to "stretch out" their stiff ankles, only to discover through imaging that they had subtle impingement syndrome. Dorsiflexion went nowhere because the joint space itself was compromised. In those cases, the only real options are modification of activity, orthotic support, or in severe instances, surgical consultation. Stretching won't reshape bone. Similarly, neurological conditions like stroke or cerebral palsy can severely limit voluntary control of these movements regardless of flexibility. Passive range may be normal, but active control is the issue. Training protocols for these populations require different parameters entirely. What works for a sedentary office worker with stiff ankles will not work for someone with upper motor neuron involvement.
Practical Takeaways
Assess both sides before assuming symmetry is fine. A difference of more than 5 degrees between left and right ankle dorsiflexion typically warrants attention. Use wall slides as a quick screening tool - you don't need expensive equipment. If you can't get your knee past your second toe with your foot flat on the ground, your dorsiflexion is likely restricted. Address the restriction before adding heavy loading to squats or lunges. For plantar flexion, don't equate strength with range. Someone can have powerful calves and still lack functional control through the full range of motion. Single-leg heel raises with a slow three-second lowering phase will reveal control issues that bilateral exercises hide. The slower the tempo, the more honest the test. Both movements interact with hip and knee mechanics. Limited dorsiflexion forces compensation up the kinetic chain. I've traced knee pain back to ankle stiffness in enough cases that I now screen the ankle before the knee every time. It's faster to fix the root cause than to chase symptoms downstream. The ankle doesn't operate in isolation, and treating it as if it does is one of the most common mistakes I see in practice.