Understanding the Dorsum Of The Hand: What You Actually Need to Know
The dorsum of the hand is simply the back side of your hand. It sits opposite the palmar surface and is where most IV starts happen because the veins are close to the surface. That's its claim to fame, really. But there's more going on under the skin than just veins waiting to be punctured. Here is a breakdown of the anatomy, the common problems, and the things that usually trip people up. I spent years doing procedures on this area and some of it is worth knowing before you ever touch it.
Vessels, Nerves, and Tendons on the Dorsum Of The Hand
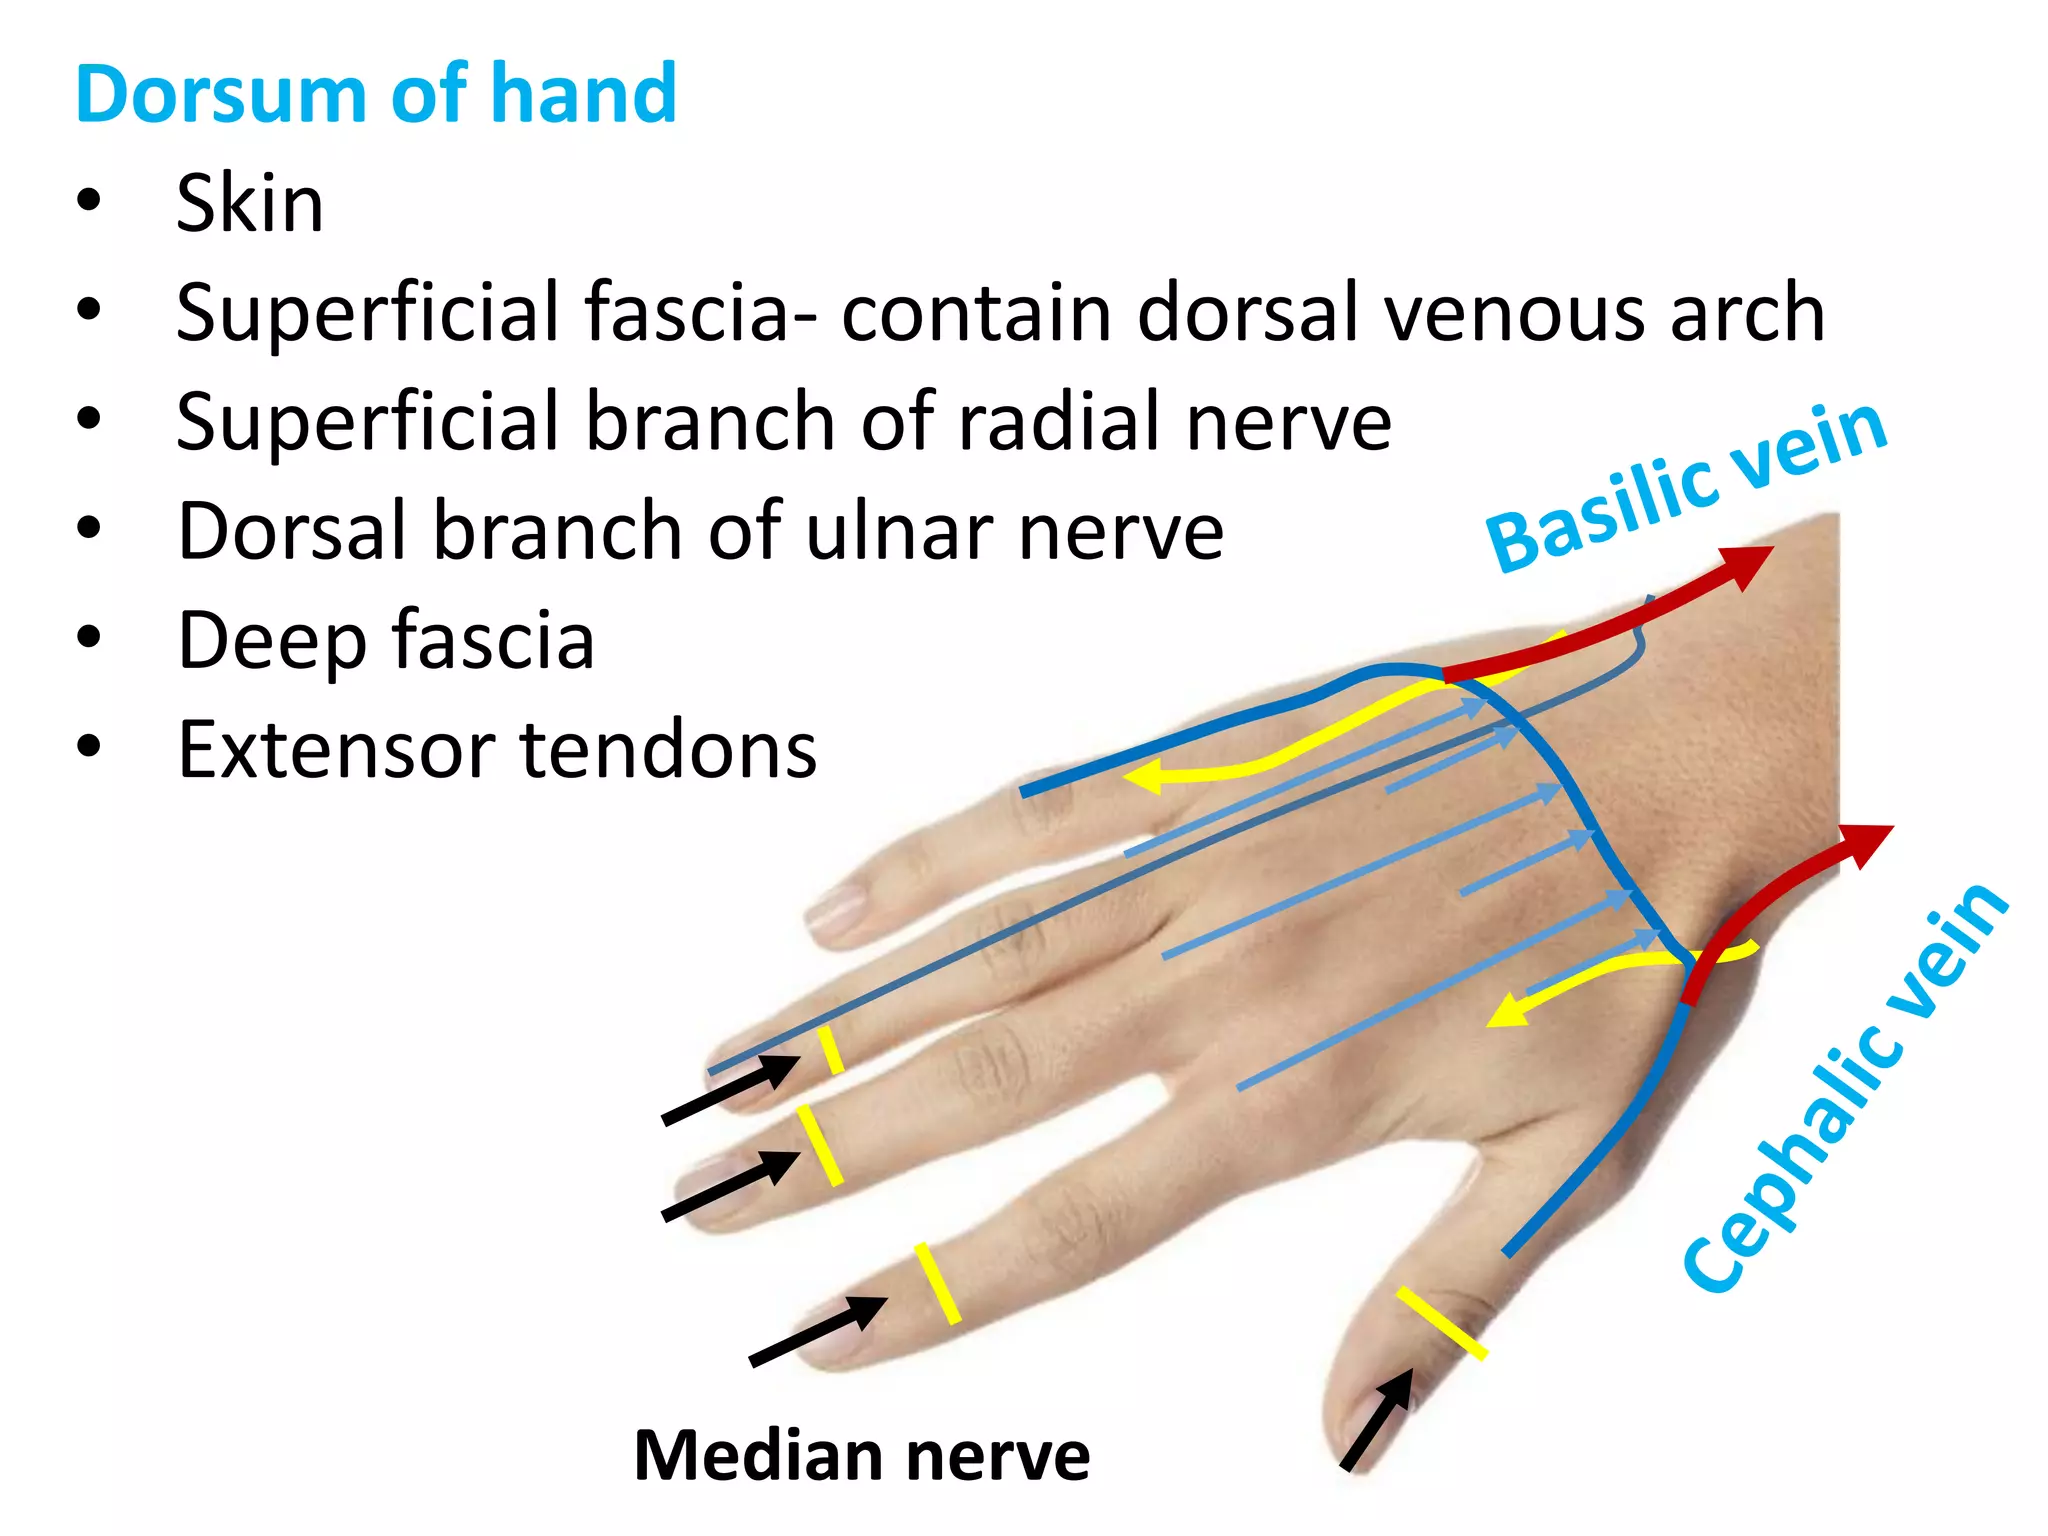
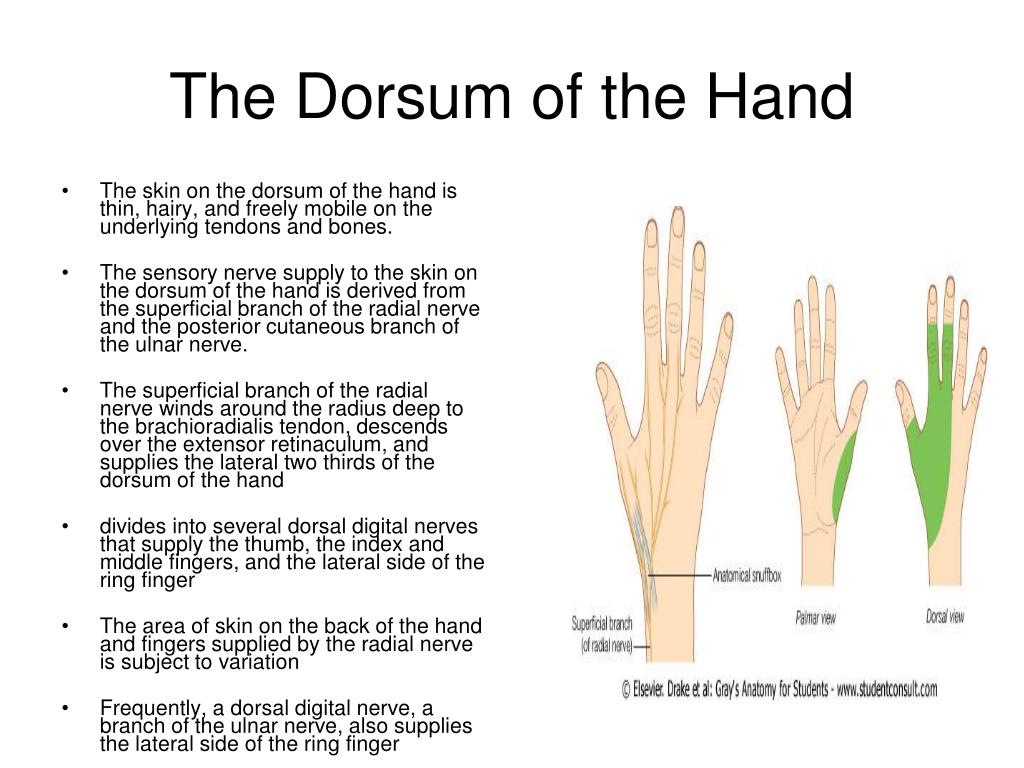
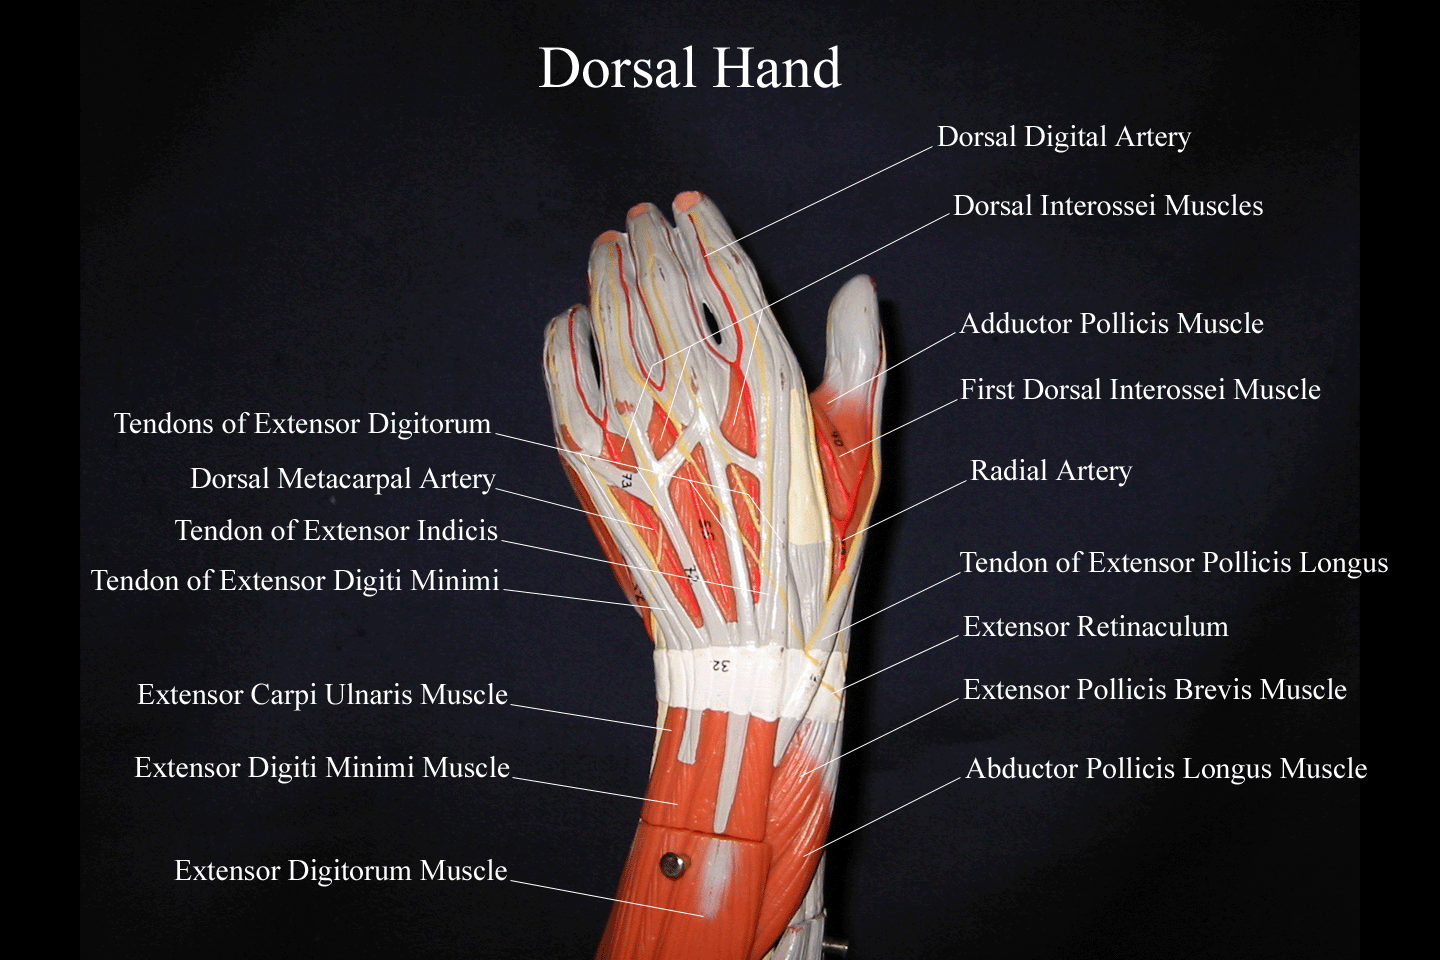
The most superficial layer is skin. It is thinner than the palm, which is why veins show through so clearly. Right under the skin is the dorsal venous network, a loose web of veins that drains into the cephalic vein on the radial side and the basilic vein on the ulnar side. Between this network and the deeper structures lies loose areolar tissue. That tissue pocket is why swelling shows up so visibly on the back of the hand. The superficial dorsal nerves come from the radial and ulnar nerves. They supply sensation to the skin over the dorsum. The radial nerve branch covers the lateral half, including the thumb and index finger area. The ulnar branch covers the medial half. If you are working in this region and a patient reports numbness or tingling afterward, one of these branches likely got irritated or nicked. It is not always permanent, but it is a real complication. Deeper still are the extensor tendons. They pass under the extensor retinaculum at the wrist, then fan out across the dorsum. Each finger has its own tendon for extension, plus contributions from the extensor digitorum communis. The tendons sit in fibro-osseous tunnels that keep them close to the bone. When those tendons inflame, you get tenosynovitis, which is painful and limits movement significantly.
Clinical Work: Starting an IV on the Dorsal Hand
This is the most common reason anyone interacts with the dorsum of the hand. The dorsal venous network provides reliable access points. Here is how I approach it in practice. First, have the patient dangle their hand below heart level for about thirty seconds. Gravity fills the veins. Then apply a tourniquet about four inches above the wrist, not too tight, just enough to impede venous return without stopping arterial flow. Use your non-dominant hand to stabilize the hand and gently stretch the skin taut toward the wrist. The vein should pop into view. Puncture at a 15 to 30 degree angle with the bevel facing up. Advance slowly. Flashback means you are in. Once you confirm, lower the needle angle to nearly parallel with the skin and advance the catheter. Secure it with transparent dressing and tape. Do not use adhesive tape directly over the puncture site because it can cause skin damage when removed later.
Get the Full Details

The main problem people run into is rolling veins. The dorsum of the hand has very little subcutaneous fat, so veins can shift laterally when you push on them. The workaround is to anchor the vein by pulling the skin taut in the direction opposite to where the vein tends to roll. I usually pull toward the wrist. This locks the vein in place long enough to get the needle in.
Fractures and Injuries Commonly Seen Here
When someone falls onto an outstretched hand, the force travels through the carpal bones and the metacarpals. The scaphoid is the most commonly fractured carpal bone, and it is located on the radial side of the wrist, just below the base of the thumb. A scaphoid fracture can present with subtle pain in the anatomical snuffbox. I have seen cases where the initial X-ray looked normal and the fracture was only visible weeks later on a follow-up scan. If you suspect a scaphoid injury, immobilize the thumb and wrist and send for advanced imaging regardless of what the first X-ray shows. Metacarpal fractures are also frequent. The fifth metacarpal neck fracture, called a boxer's fracture, happens when someone punches something hard. The head of the fifth metacarpal displaces volarly. Reduction may be needed if the angulation exceeds thirty degrees. Anything less than that usually heals fine with splinting alone.
A Specific Edge Case I Ran Into
Once I had a patient whose dorsal hand veins were visible and accessible on inspection, but every time I advanced the catheter, the vein would collapse. The problem was that the vein wall was sclerotic from repeated prior accesses. The lumen was narrow and fragile. Standard technique kept failing. The workaround was to use a smaller gauge catheter, specifically a 24-gauge, and to insert it at a shallower angle, closer to ten degrees. I also avoided advancing the needle too far into the vein after flashback because the sclerotic segment had very little room to spare. Instead, I threaded the catheter gently, almost entirely on its own, with minimal needle manipulation. It took longer than a standard IV start but held well. Using a ultrasound-guided approach would have been faster in hindsight, but in a busy setting, I work with what I have.

Compartment Syndrome: A Serious but Rare Concern
The dorsum of the hand has potential space for swelling, but true compartment syndrome here is extremely rare compared to the forearm or lower leg. Still, it can happen after significant trauma or excessive IV fluid extravasation. The signs are pain out of proportion to the injury, pain with passive finger extension, paresthesia, and tense swelling. If you notice these, escalate immediately. Do not wait. Compartment syndrome is a surgical emergency. Most people think the dorsum of the hand is easy access because the veins are superficial. That is true, but they overlook two things. First, the skin on the dorsum is mobile and thin, which means the vein can move more freely than on the antecubital fossa. Second, the veins here are smaller and more delicate, making them prone to blowout. If you meet resistance while advancing the catheter, stop. Do not force it. Back off, reassess, and try a different site if needed. The cephalic vein at the wrist or the forearm veins are better alternatives for long-term IV therapy. Another thing beginners miss is the relationship between the extensor tendons and the underlying joints. When assessing range of motion after an injury, ask the patient to make a fist and then fully extend their fingers. Watch for any lag or inability to extend a particular finger. That points to a tendon issue, not a fracture. Ordering imaging for a tendon injury wastes time and money. Clinical exam often gives you the answer.
Summary of Key Points
The dorsum of the hand contains the dorsal venous network, superficial dorsal nerves, extensor tendons, and the distal rows of carpal bones. It is a common site for IV access but carries risks like vein rolling, sclerosis, and nerve irritation. Scaphoid fractures should always be suspected after a fall on an outstretched hand, even with normal initial imaging. Boxer's fractures involve the fifth metacarpal and typically require reduction if angulation is severe. Always examine tendon function clinically before ordering imaging for finger extension problems. And remember that smaller, more fragile veins on the dorsum require gentler technique and sometimes smaller gauge equipment.