What This Combo Drops Actually Do
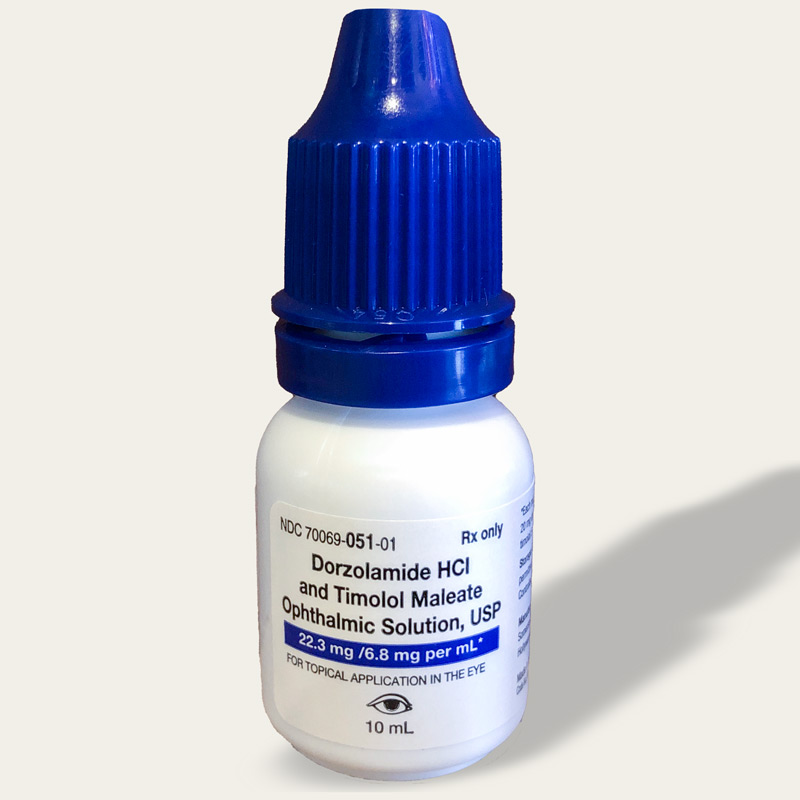
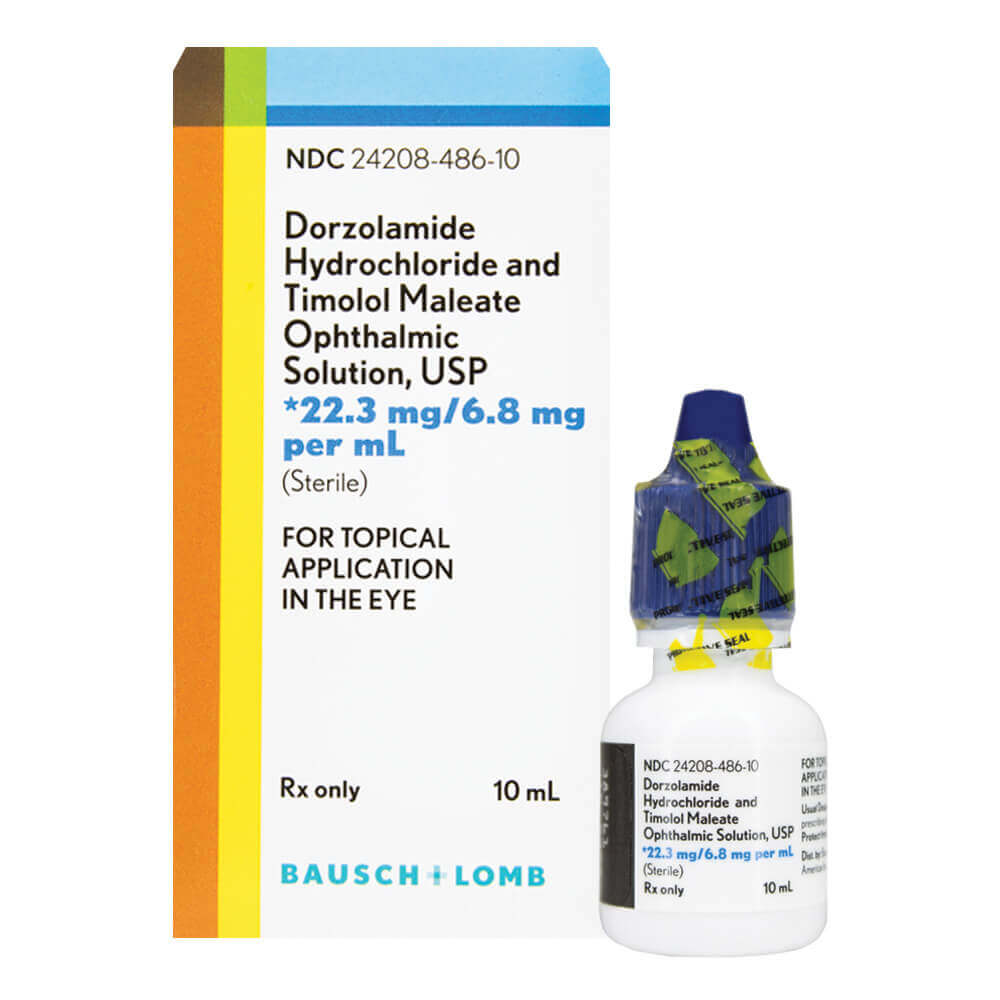
Dorzolamide hydrochloride is a carbonic anhydrase inhibitor that reduces aqueous humor production by blocking the enzyme in the ciliary body. Timolol maleate is a non-selective beta-blocker doing the same job from a different angle. Put them together and you get a single ophthalmic solution that targets intraocular pressure through two complementary mechanisms. The fixed-dose combination means patients don't have to juggle two separate bottles, which sounds simple but actually matters more than most people realize when compliance is the real problem. I've watched patients who were perfectly managing their glaucoma on monotherapy fall apart the moment they got switched to a two-bottle regimen. Two drops, thirty seconds apart, twice daily. Eventually someone skips the second drop or mixes up the timing. The combo solution eliminates that failure mode entirely. That's the practical win, not some abstract pharmacological elegance.
Dorzolamide Hydrochloride Timolol Maleate Ophthalmic Solution How It Works in Practice
The solution comes as a preservative-containing formulation, usually with benzalkonium chloride, at concentrations around 2% dorzolamide and 0.5% timolol. You instill one drop in the affected eye(s) twice daily. That's it for dosing. The starting point for most patients is already moderate-to-severe glaucoma where monotherapy isn't cutting it, so you're not beginning here unless pressure was already uncontrolled. One thing people miss is that the timolol component crosses into systemic circulation through the nasolacrimal drainage pathway. I had a patient in her seventies who presented with bradycardia and fatigue after starting this medication. Her ophthalmologist hadn't considered that she was already on a oral beta-blocker for hypertension. The combination stacked on top of her existing metoprolol pushed her heart rate down to the fifties. We coordinated with her cardiologist, switched her to a different glaucoma class entirely, and resolved the issue within a week. This is the kind of interaction that doesn't show up in the summary prescribing information until someone actually runs into it. Another practical detail: the dorzolamide makes the solution slightly acidic, around pH 7.4 but it can sting on instillation. Patients report burning for maybe ten to fifteen seconds. Some stop using it because of that sting. Tell them it's normal, it passes, and skipping doses because of discomfort is worse than dealing with the brief irritation. A cold bottle tends to sting less than room temperature, so refrigerating it before use helps a noticeable amount.
When This Isn't the Right Call
Non-selective beta-blockers hit both beta-1 and beta-2 receptors. That means asthma and COPD patients need careful evaluation before starting. I've seen cases where the label clearly lists respiratory contraindications and the prescriber still wrote it anyway because they were focused on the eye pressure numbers. The lung effect is real and can be significant. Beta-2 blockade in the airways causes bronchoconstriction. It's not theoretical. Cardiac conduction issues are another boundary. Sinus bradycardia, second or third-degree AV block, and overt heart failure are contraindications. If the patient's resting heart rate is below fifty-five or they're symptomatic from their conduction disease, this medication is going to make things worse before anything else. Check the baseline vitals before prescribing. It takes thirty seconds and prevents a visit to the emergency department. The preservative is worth mentioning separately. Benzalkonium chloride accumulates on the ocular surface with chronic use. For patients already dealing with dry eye syndrome, which is extremely common in the glaucoma population, this combo can worsen surface disease substantially. I recommend a preservative-free alternative or at minimum adding a preservative-free artificial tear regimen when I see corneal staining developing on fluorescein exam. Don't wait for the patient to complain. The staining shows up first.
Get the Full Details
Administration Technique That Actually Matters
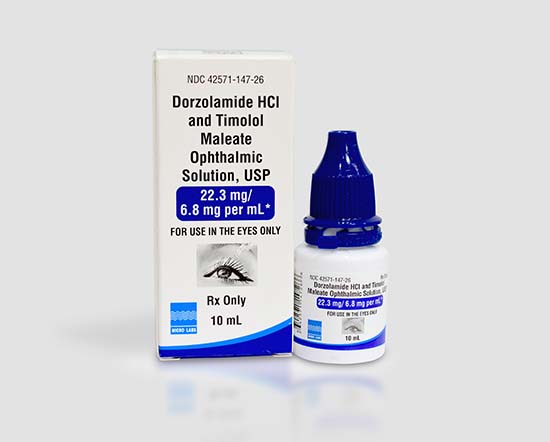
Most patients still aren't doing punctal occlusion correctly. Pressing on the inner corner of the eye for sixty seconds after instillation reduces systemic absorption significantly. The literature varies on the exact reduction percentage, but it's meaningful for patients who are sensitive to the beta-blocker effects. I tell my patients to think of it as closing the drain rather than just waiting for the drop to spread. The difference in technique matters more than they expect. If a second dose is prescribed within the same session, space them by at least five minutes. The first drop displaces roughly ten microliters of tear film. Anything instilled immediately after mostly washes out. Five minutes gives enough time for the first dose to be absorbed through the cornea. This is one of those details where perfect technique looks like laziness but actually improves outcomes. Another edge case I run into occasionally: patients who wear soft contact lenses. The benzalkonium chloride gets absorbed into the lens material and concentrates there, then slowly leaches back onto the cornea. This can cause toxicity keratopathy over time. The recommendation is to remove lenses before instillation and wait fifteen minutes before reinserting. Some patients find this cumbersome and simply stop wearing their drops consistently. It's a real compliance trap. If a contact lens wearer is struggling with this medication, switching to a preservative-free formulation or discussing lens-compatible options early prevents months of inconsistent use.
Monitoring and Follow-Up Realities
Intraocular pressure should be rechecked within four to six weeks of starting or changing the dose. That's the pharmacologic steady state for these agents. Checking earlier doesn't give you useful information and checking later misses the window where dose adjustments matter most. Target pressure depends on the glaucoma stage, but the general expectation is a reduction of twenty to thirty percent from baseline with this combination. If you're not seeing that range of reduction, something needs to change—whether that's a dose increase, adding a different class, or moving toward surgical intervention. Pulse and blood pressure checks at follow-up visits are standard but frequently skipped in busy practice settings. Write them down. Track the trend. A downward shift in heart rate of ten to fifteen beats per minute is common and usually not concerning, but a shift beyond that warrants investigation. Same with blood pressure. The topical route still delivers systemically active drug. Vision quality monitoring matters too. Some patients report blurry vision immediately after instillation, which is expected from the vehicle itself. If blurry vision persists beyond five minutes or is accompanied by eye redness that doesn't resolve, that's not the normal response and should be evaluated.conjunctival injection that lasts for hours suggests either an allergy to the preservative or a formulation intolerance, and continuing the same drops isn't going to help.
Alternatives When This Falls Short
Prostaglandin analogs like latanoprost are generally first-line for glaucoma today, and many patients never need to reach the dorzolamide-timolol combination. But if prostaglandin monotherapy isn't controlling pressure, this combo is a logical next step before adding a third agent or considering surgery. The fixed combination saves money compared to buying two separate generics and reduces the pill burden in a way that actually affects adherence. For patients who can't tolerate the preservative or the beta-blocker systemically, brimonidine combinations or selective laser trabeculoplasty are reasonable discussions. SLT in particular has moved up the treatment algorithm considerably in recent years. It's not a replacement for every case, but it deserves to be on the table earlier than it used to be. I've had patients avoid lifelong multi-drop regimens entirely after a single SLT procedure. There's also the matter of cost and insurance coverage. Generic dorzolamide-timolol is widely available and usually inexpensive, but brand-name combinations and newer formulations vary significantly by plan. Patients sometimes switch medications mid-treatment because their insurance changed formulary tiers, and that disruption can cost them months of unstable pressure control. Staying on a medication that works and is covered is usually better than chasing a theoretically superior option that introduces variability.
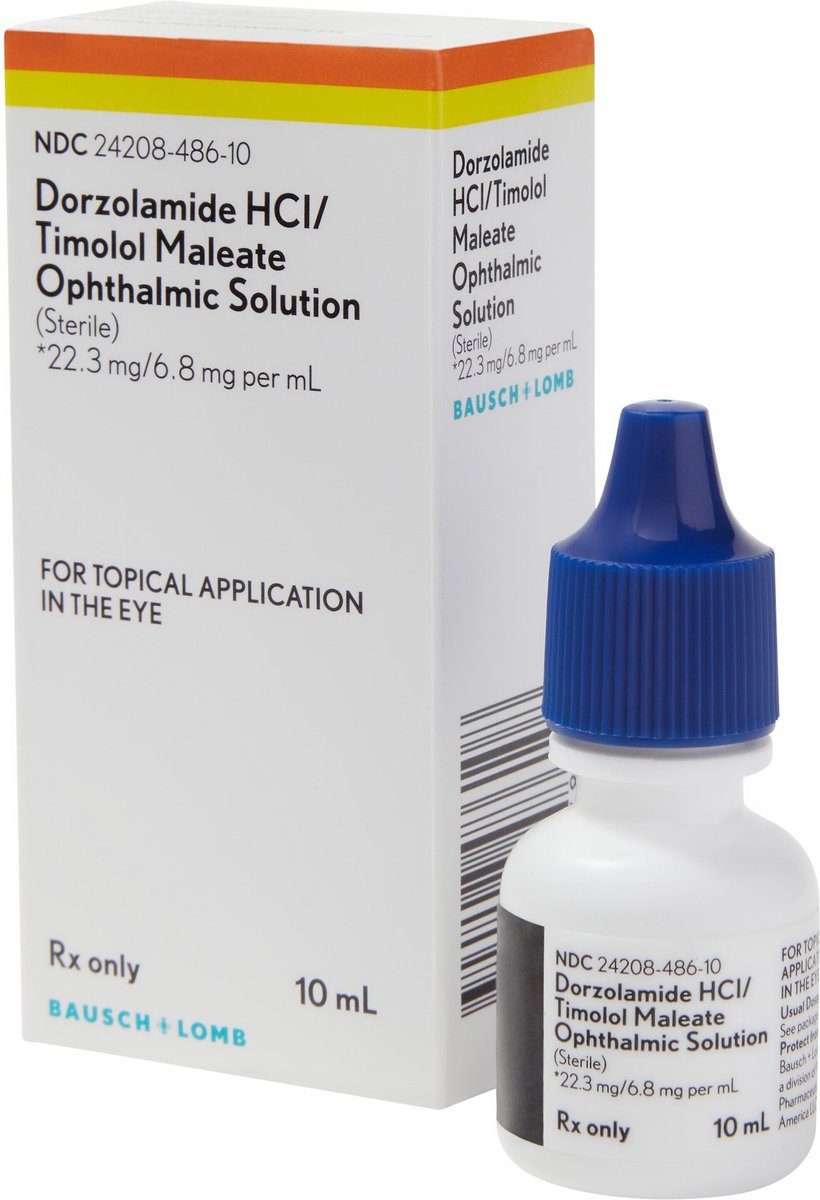
The combination remains a workhorse in glaucoma management for the right patients. It's not the first drug most people will try, but it's not a last resort either. It sits in that middle ground where two established mechanisms solve a problem that one mechanism can't, and the convenience of a single bottle keeps people using it consistently enough for it to actually work the way it's supposed to. That's the honest assessment.