Understanding Dosage Forms in Pharmacy Compounding
Compounding pharmacies deal with a wide range of dosage forms, and having a clear reference system matters more than most people realize. When you are pulling together a Dosage Forms To Compond Ppt for training purposes or internal reference, the goal is not to create a decorative presentation. It is to build something that actually helps technicians and pharmacists make correct decisions at the bench. I have seen too many compounding training decks that list dosage forms in alphabetical order with generic images. That approach causes problems the moment someone tries to use it during actual preparation. The order should follow workflow logic, not dictionary logic.
Dosage Forms To Compond Ppt
Oral Solid Dosage Forms
Capsules and tablets dominate the compounding world. Capsule filling is the most common service request I see in community compounding pharmacies. The standard sizes run from 000 down to 5, and each size has a known volume capacity that varies by powder density. A medium-flow lactose blend will pack differently than a low-dose active with poor flow characteristics. Tragacanth and microcrystalline cellulose are your go-to bulking agents when the API volume is too small. The problem most people miss is that MCC does not always flow the same way between lots. I spent three weeks troubleshooting capsule fill weight variation on a 50 mg prednisolone formulation before I realized the batch of MCC from our supplier had different particle sizing. Switching to a consistent grade and pre-sieving everything through a #40 mesh solved it immediately. Tablets require compression or moulding. The moulding method is simpler for most compounding operations but produces less hard tablets. If the patient needs a tablet that survives shipping, compression is the right call. The tradeoff is equipment cost and cleaning time between formulations.
Oral Liquid Dosage Forms
Suspensions and solutions are where most compounding errors happen, and it is usually because someone skips the wetting step. Hydrophobic powders like griseofulvin or thyroxine will not suspend properly if you just dump them into the vehicle. You need to geometrically dilute the API into a wetting agent first. Sorbitol solution or a small amount of the final vehicle works fine. The particle size after trituration should be under 10 microns for acceptable suspension stability. Pacific seaweed and xanthan gum are standard suspending agents. Carbomer gives better clarity but is much harder to work with at the bench. I recommend starting with xanthan gum unless the prescription specifically requires a preservative-free system. Solutions are straightforward until the solvent system is wrong. Oil-soluble APIs like vitamin D or testosterone in oral solution form will precipitate if you use too much water as a co-solvent. Propylene glycol and PEG 300 are the standard co-solvents. The solubility limit of your API in whatever combination you choose should be confirmed before you commit to a concentration.
Get the Full Details
Semi-Solid Dosage Forms
Ointments, creams, and gels each have different base requirements. The oleaginous bases like white petrolatum and Anhydrous Lanolin are simple to work with but can be greasy and stain clothing. Water-removable bases are what patients actually prefer, even though they require more careful preservation. The counter-intuitive part about creams is that the phase temperature during compounding matters more than most people account for. If your aqueous and oleaginous phases differ by more than five degrees Celsius when you combine them, the emulsion can break during cooling. Keep both phases between 70 and 75 degrees Celsius before mixing. Use a digital probe thermometer, not just the water bath setting. Gels require carbopol neutralization, and that step is where things commonly go wrong. Adding TEA or NaOH to a carbopol dispersion raises the pH and causes immediate viscosity development. If you add the base too quickly, you get localized clumping that never fully disperses. Add the neutralizing agent as a dilute solution while stirring continuously. The final pH should land between 5.5 and 7.0 for patient comfort.
Topical and Transdermal Systems
Transdermal patches from a compounding perspective usually mean semi-solid patches rather than matrix membranes. The adhesive layer needs to stay tacky without migrating drug prematurely. My experience shows that using a combination of acriflavine-free adhesive and a backing layer of lanolin-based ointment gives acceptable adhesion for up to 24 hours. Anything longer requires a proper polymeric matrix, which is beyond most compounding capabilities. Solutions for injection or ophthalmic use require aseptic technique and sterility testing. This is where the skill gap in most compounding operations becomes visible. Endotoxin testing, particulate matter evaluation, and container closure integrity are not optional. A Dosage Forms To Compond Ppt that covers sterile products should include specific protocols for each step, not just a general statement about laminar flow. I once had a batch of compounded dexamethasone injection fail sterility testing because the filtration setup had a defect in the tubing connector that was not visible during normal inspection. The lesson was to do a pressure hold test on the entire assembly before use. Five minutes of extra work prevented a recall.
Mucosal and Specialty Dosage Forms
Vaginal tablets, suppositories, and troches each have their own challenges. Cocoa butter suppositories melt at body temperature, which is useful but means they need cool storage. Polyethylene glycol bases do not melt at body temperature, so they dissolve slowly instead. The choice depends entirely on the therapeutic requirement. Troches dissolve in the mouth and are popular for local throat effects or systemic absorption of certain drugs. The base mixture of sugar, gelatin, and glycerin needs to be heated to the soft crack stage, approximately 150 degrees Celsius. Temperature control at that range is difficult without a proper candy thermometer. Guessing leads to crystallization or burning.
Practical Considerations for Your Reference Material
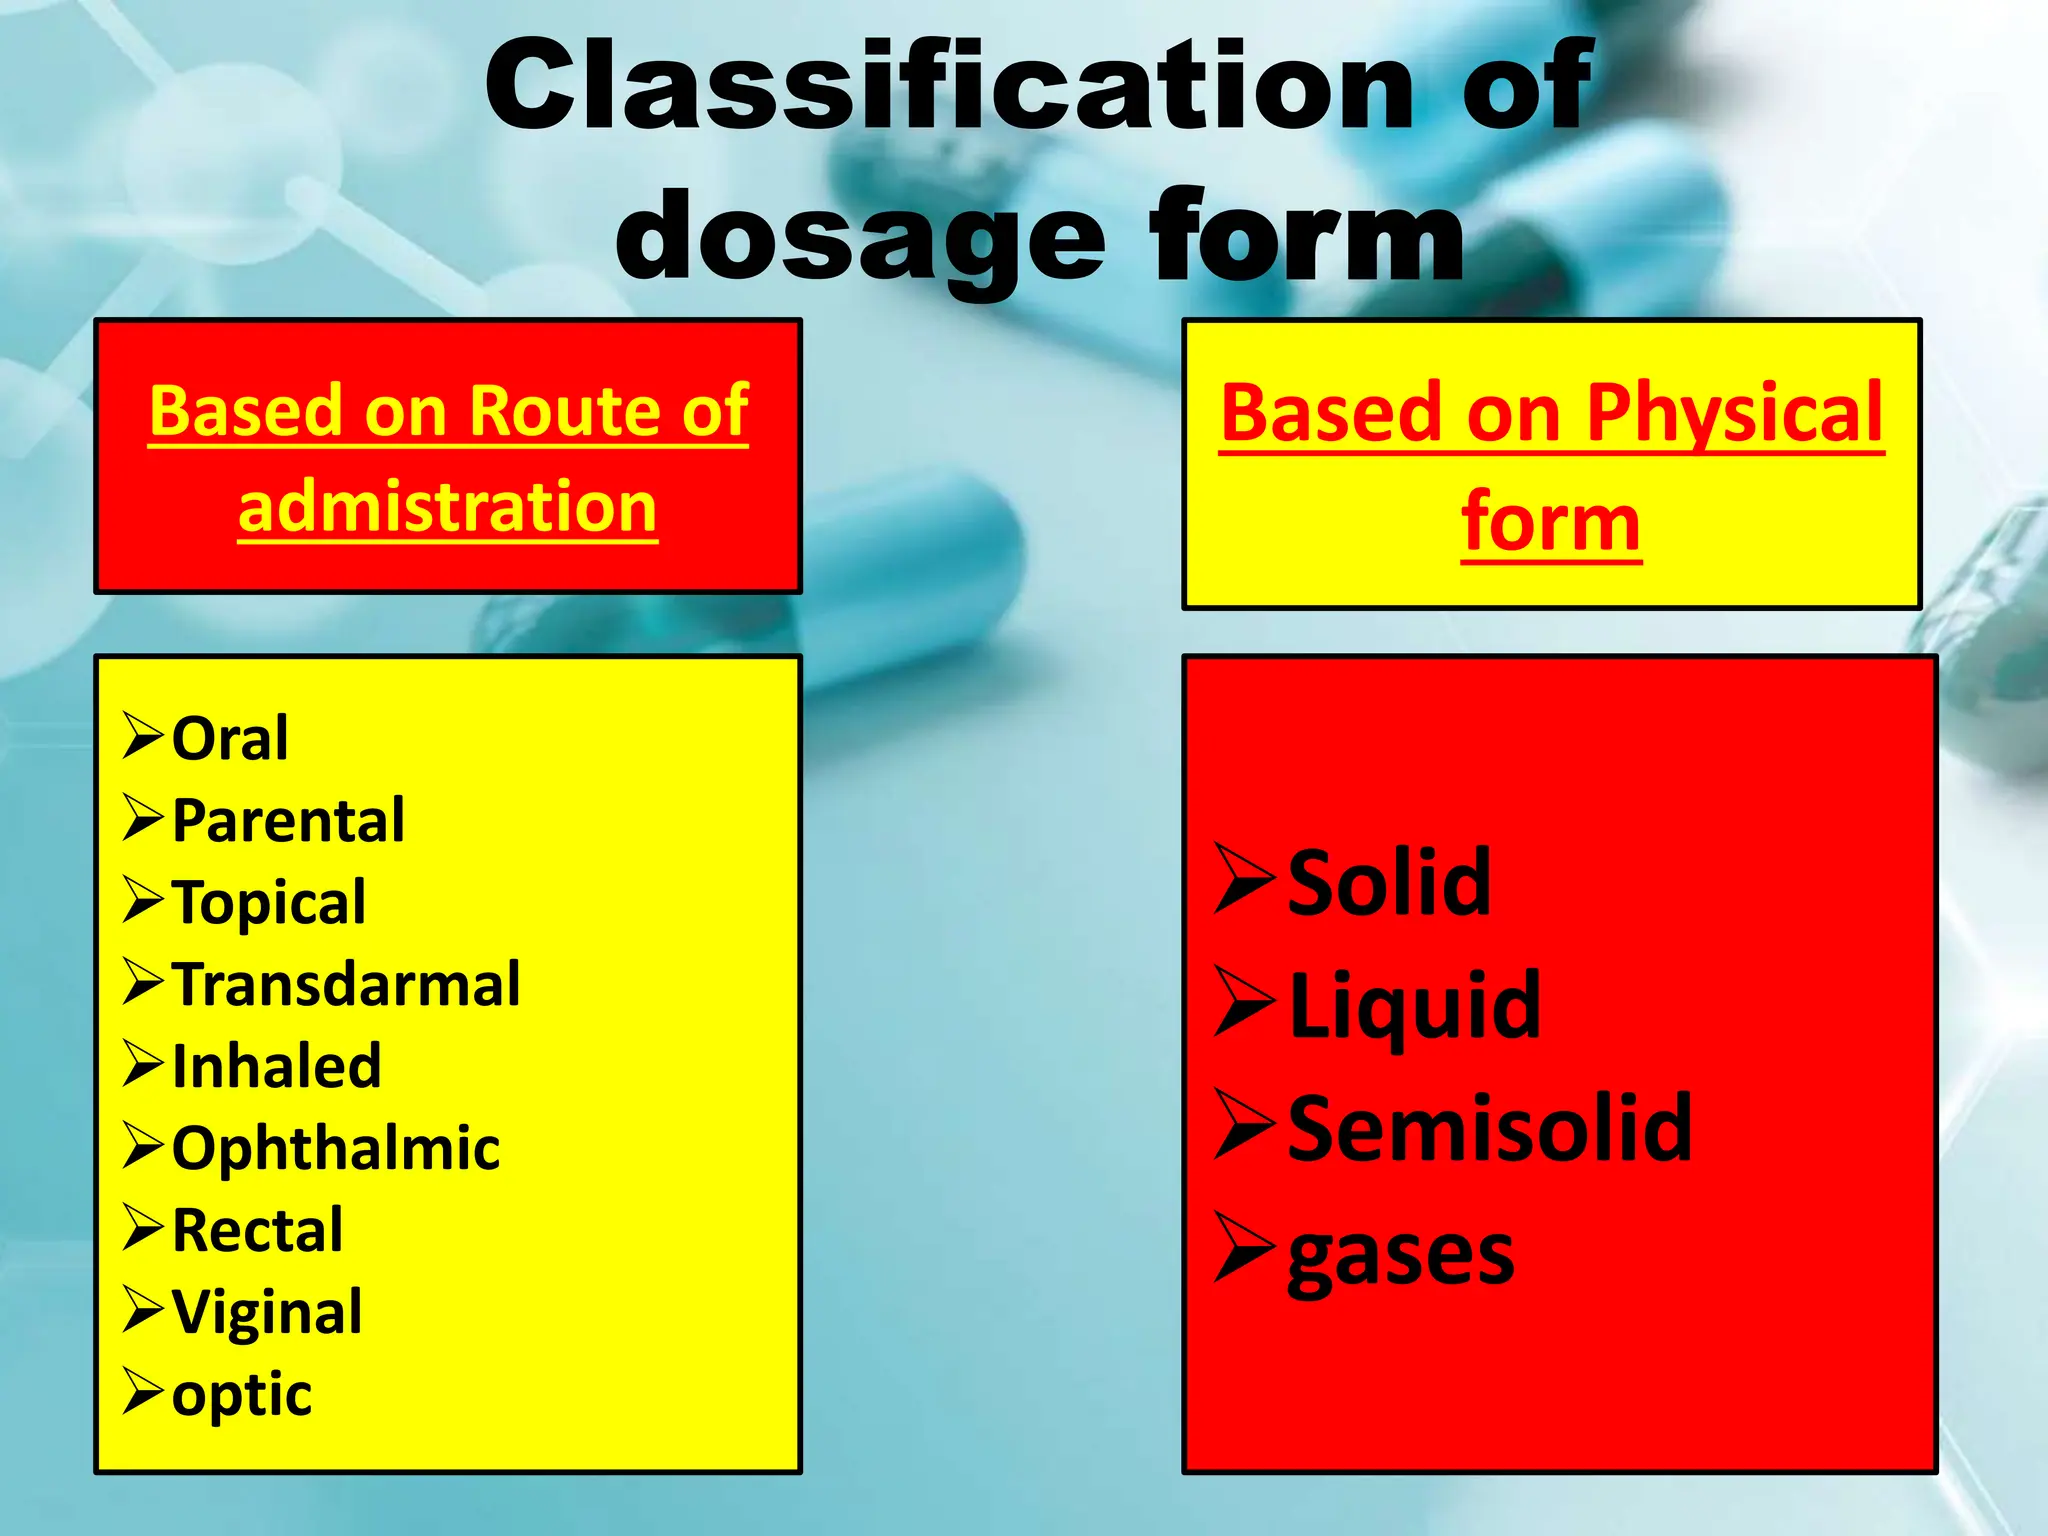
When building out your compounding reference materials, prioritize content that addresses the decisions pharmacists actually face. Stability data, compatibility information, and calculation worksheets are more useful than theoretical descriptions. Include actual calculation examples with real numbers, not placeholder values. The difference between a 0.5 percent and a 5 percent w/v concentration changes everything about the excipient selection. Another thing that rarely gets enough attention is labeling requirements. Each dosage form has different labeling considerations. Suspensions need shake well directions and expiration dating based on stability data. Topicals need application instructions. Oral solids need storage conditions. A good training deck includes labeling standards alongside the preparation methods. The limitation of any static reference document is that it cannot adapt to every formulation variation. New APIs come in with unknown solubility profiles. Different manufacturers supply the same excipient with different grades. Your reference system should include a framework for evaluating new formulations rather than just a list of existing ones. The ability to look up a solubility parameter and predict whether a formulation will work is more valuable long-term than memorizing fifty specific recipes.
Calculated shelf life estimates from predictive stability models are useful starting points but should always be verified with actual testing when the compound is dispensed regularly. The difference between a predicted six-month stability and an actual three-month result is enough to cause patient safety issues if you rely solely on the model.