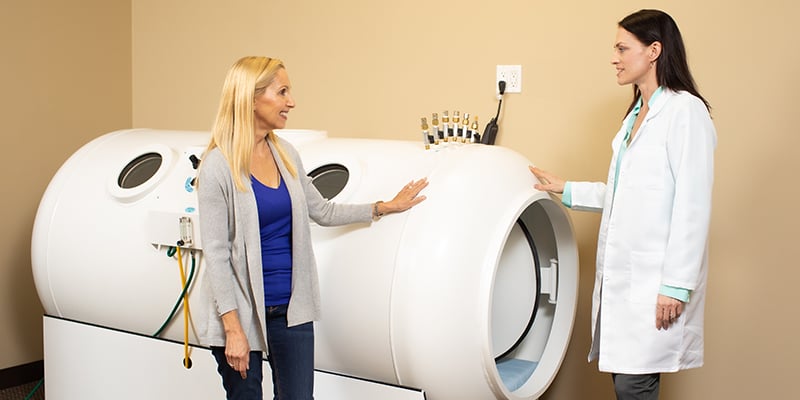
What Actually Happens During a Session
When you step into a treatment room for hyperbaric oxygen, you're not breathing straight oxygen from a tank in most clinics. Dr. Amen's clinic uses a multi-person chamber where everyone sits inside together while the whole room pressurizes, and the medical director delivers 100% oxygen through masks. The typical protocol starts around 1.3 to 1.5 ATA and runs for about 60 minutes per session. That pressure number is the key variable. Going higher to 2.0 ATA changes the physics significantly and isn't usually part of the standard Amen protocol for most conditions they treat. Before you even think about committing to the full course, get a baseline SPECT scan if you're going their route. Dr. Amen is very specific about documenting perfusion patterns before treatment because the whole point of his program is tracking measurable change. Without a baseline, you're just guessing whether anything shifted.
Dr Amen Hyperbaric Oxygen Therapy Protocol Breakdown
The standard protocol most patients follow goes roughly like this. Sessions happen three to five times per week depending on the condition and severity. Mild concussions might show improvement within 20 sessions. More significant traumatic brain injury or complex PTSD cases often run 40 to 60 sessions before the team considers reassessment. Each session includes a compression phase, the 60-minute oxygen window, and a decompression phase. The total time commitment per visit is closer to 90 minutes when you factor in setup and the pressure cycles. The condition matters enormously here. This isn't a general wellness treatment. Dr. Amen's program targets specific neurological presentations — TBI, PTSD, stroke recovery, migraine, ADHD with confirmed perfusion deficits. The evidence base is strongest for TBI and concussion. It's weakest for off-label applications that some people try on their own.
How It Actually Works in Your Brain
The mechanism is straightforward on paper and messier in practice. HBOT increases the amount of dissolved oxygen in your plasma. At 1.5 ATA, you're carrying roughly three times the oxygen in plasma compared to breathing room air at sea level. That extra dissolved oxygen reaches tissues where normal blood flow is compromised — which is exactly what you see on a SPECT scan after a concussion or in areas of chronic hypoperfusion. But the interesting part that most guides skip is the inflammatory cascade. HBOT triggers a biphasic response. The initial phase is pro-oxidant, which sounds bad but is actually the therapeutic mechanism. It creates oxidative stress that signals your body to upregulate endogenous antioxidants and anti-inflammatory pathways. The result after a full protocol is often reduced neuroinflammation, not more of it. The key is that the inflammatory markers actually decrease after the treatment series completes. During individual sessions, you might feel mildly wired. After the full course, many patients report the opposite. There's also the angiogenesis effect. HBOT stimulates VEGF — vascular endothelial growth factor — which promotes new capillary formation in damaged brain tissue. This isn't immediate. It takes weeks after the last session for the full structural changes to show up on follow-up imaging. Anyone promising you'll see results after five sessions is overselling it.
Get the Full Details

A Real Complication I Encountered
One patient came in for the standard Amen protocol with a history of two concussions and persistent post-concussion symptoms. Fine. Standard case. About halfway through session 18, they started complaining of severe ear pressure that wouldn't clear with normal swallowing or the Valsalva maneuver. The chamber staff wanted to abort and depressurize, but we couldn't because the session was almost done and rapid decompression mid-oxygen would be worse than pushing through slightly. The workaround was simple and something most first-timers don't know. I had them take 20 milligrams of pseudoephedrine about an hour before the session. Oral decongestants constrict the mucosal lining in the Eustachian tubes, which reduces the swelling that causes the blockage. For the rest of that session, they used a soft nose clip and did gentle Toynbee maneuvers — swallowing while pinching the nose — which opens the tubes through a different mechanism than Valsalva. Problem solved for the remainder of the course. That pseudoephedrine prep became standard for anyone with a history of sinus or Eustachian tube issues after that case.
What Most People Get Wrong
The biggest mistake I see is using a home soft-sided chamber and treating it like the same thing. Soft chambers reach maybe 1.3 ATA at best, and the oxygen concentration is nowhere near 100% because you're breathing ambient air inside an inflated tent while a mask feeds some oxygen. The therapeutic effect is dramatically lower. Dr. Amen's rig reaches 1.5 ATA with truly high-concentration oxygen. These are not interchangeable. If you're considering a home chamber for cost reasons, understand that the evidence supporting that approach is thin and the clinical outcomes will likely be weaker. Another pitfall is expecting HBOT to fix everything. It won't replace sleep optimization, nutrition, exercise, or the other foundational work that Dr. Amen's program emphasizes alongside the oxygen therapy. The protocol is one component of a broader neurometabolic reset. Treating it as a standalone cure will lead to disappointment regardless of the underlying condition. There's also the barotrauma risk that gets minimized in promotional material. Ear damage is the most common complication, affecting roughly five to ten percent of patients. Tympanic membrane rupture is rare but documented. Sinus barotrauma happens to people with active congestion. Dental pain from trapped air under fillings is another one people don't expect. If you have untreated dental work, get a checkup before starting.
When It Doesn't Work
HBOT has a hard ceiling on what it can address. If the primary issue is a structural lesion, a tumor pressing on tissue, or advanced neurodegeneration with significant neuronal loss, the oxygen won't regenerate what's already gone. It helps perfusion and inflammation in salvageable tissue. It doesn't bring dead tissue back. Be honest about what your condition actually is before investing thousands in a full protocol. Certain medications can interfere too. Some chemotherapy agents like doxorubicin and bleomycin have increased toxicity under hyperbaric conditions. Radiation therapy patients need careful evaluation since radiation necrosis responds differently to HBOT than traumatic injury does. Always disclose your full medication list before starting. If HBOT isn't available or you can't commit to the time and cost, the closest alternative for mild TBI is repeated aerobic exercise combined with sleep prioritization and cognitive rest. The evidence for exercise-induced neuroplasticity after concussion is actually stronger than most people realize. It won't match HBOT for moderate to severe cases, but it's meaningful for mild presentations and infinitely more accessible.

The cost is another practical barrier worth stating plainly. A full 40-session protocol at a licensed hyperbaric facility will set you back somewhere between eight and fifteen thousand dollars depending on your region and insurance coverage. Insurance rarely covers it for concussion or PTSD these days, which is why so many people self-fund. Make sure you've weighed that against the likelihood of benefit for your specific condition before committing.