Practical Drug-Nutrient Interactions
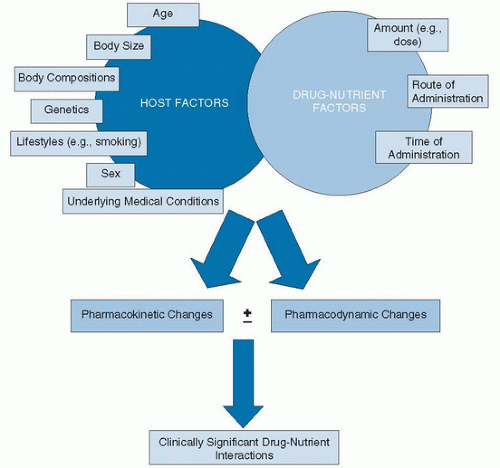
A Drug Nutrient Interaction Definition would describe any situation where a medication changes how the body handles vitamins, minerals, or other dietary compounds, or where a nutrient changes how a drug works. It sounds simple enough, but the clinical reality is messy. Most interactions aren't dramatic single events. They are slow, cumulative processes that matter mostly when patients are on long-term medication regimens with poor baseline nutrition. I ran into this concretely with a patient on omeprazole for six years who kept coming back with fatigue and paresthesia. Her B12 levels were borderline. Standard supplementation wasn't moving the needle. The issue wasn't just B12—proton pump inhibitors strip stomach acid, which means you can't cleave protein-bound B12 from food. Even if you're eating well, you're not absorbing it. The fix was switching her to sublingual methylcobalamin at 1000mcg daily, which bypasses the stomach entirely. We also checked her iron and found it low. Same mechanism—acid is required for ferric to ferrous iron conversion. Without acid, oral iron just passes through. That patient has been stable on supplements for two years now, but it took about eight months of tracking to untangle what was going on.
The Drug Nutrient Interaction Definition in Practice
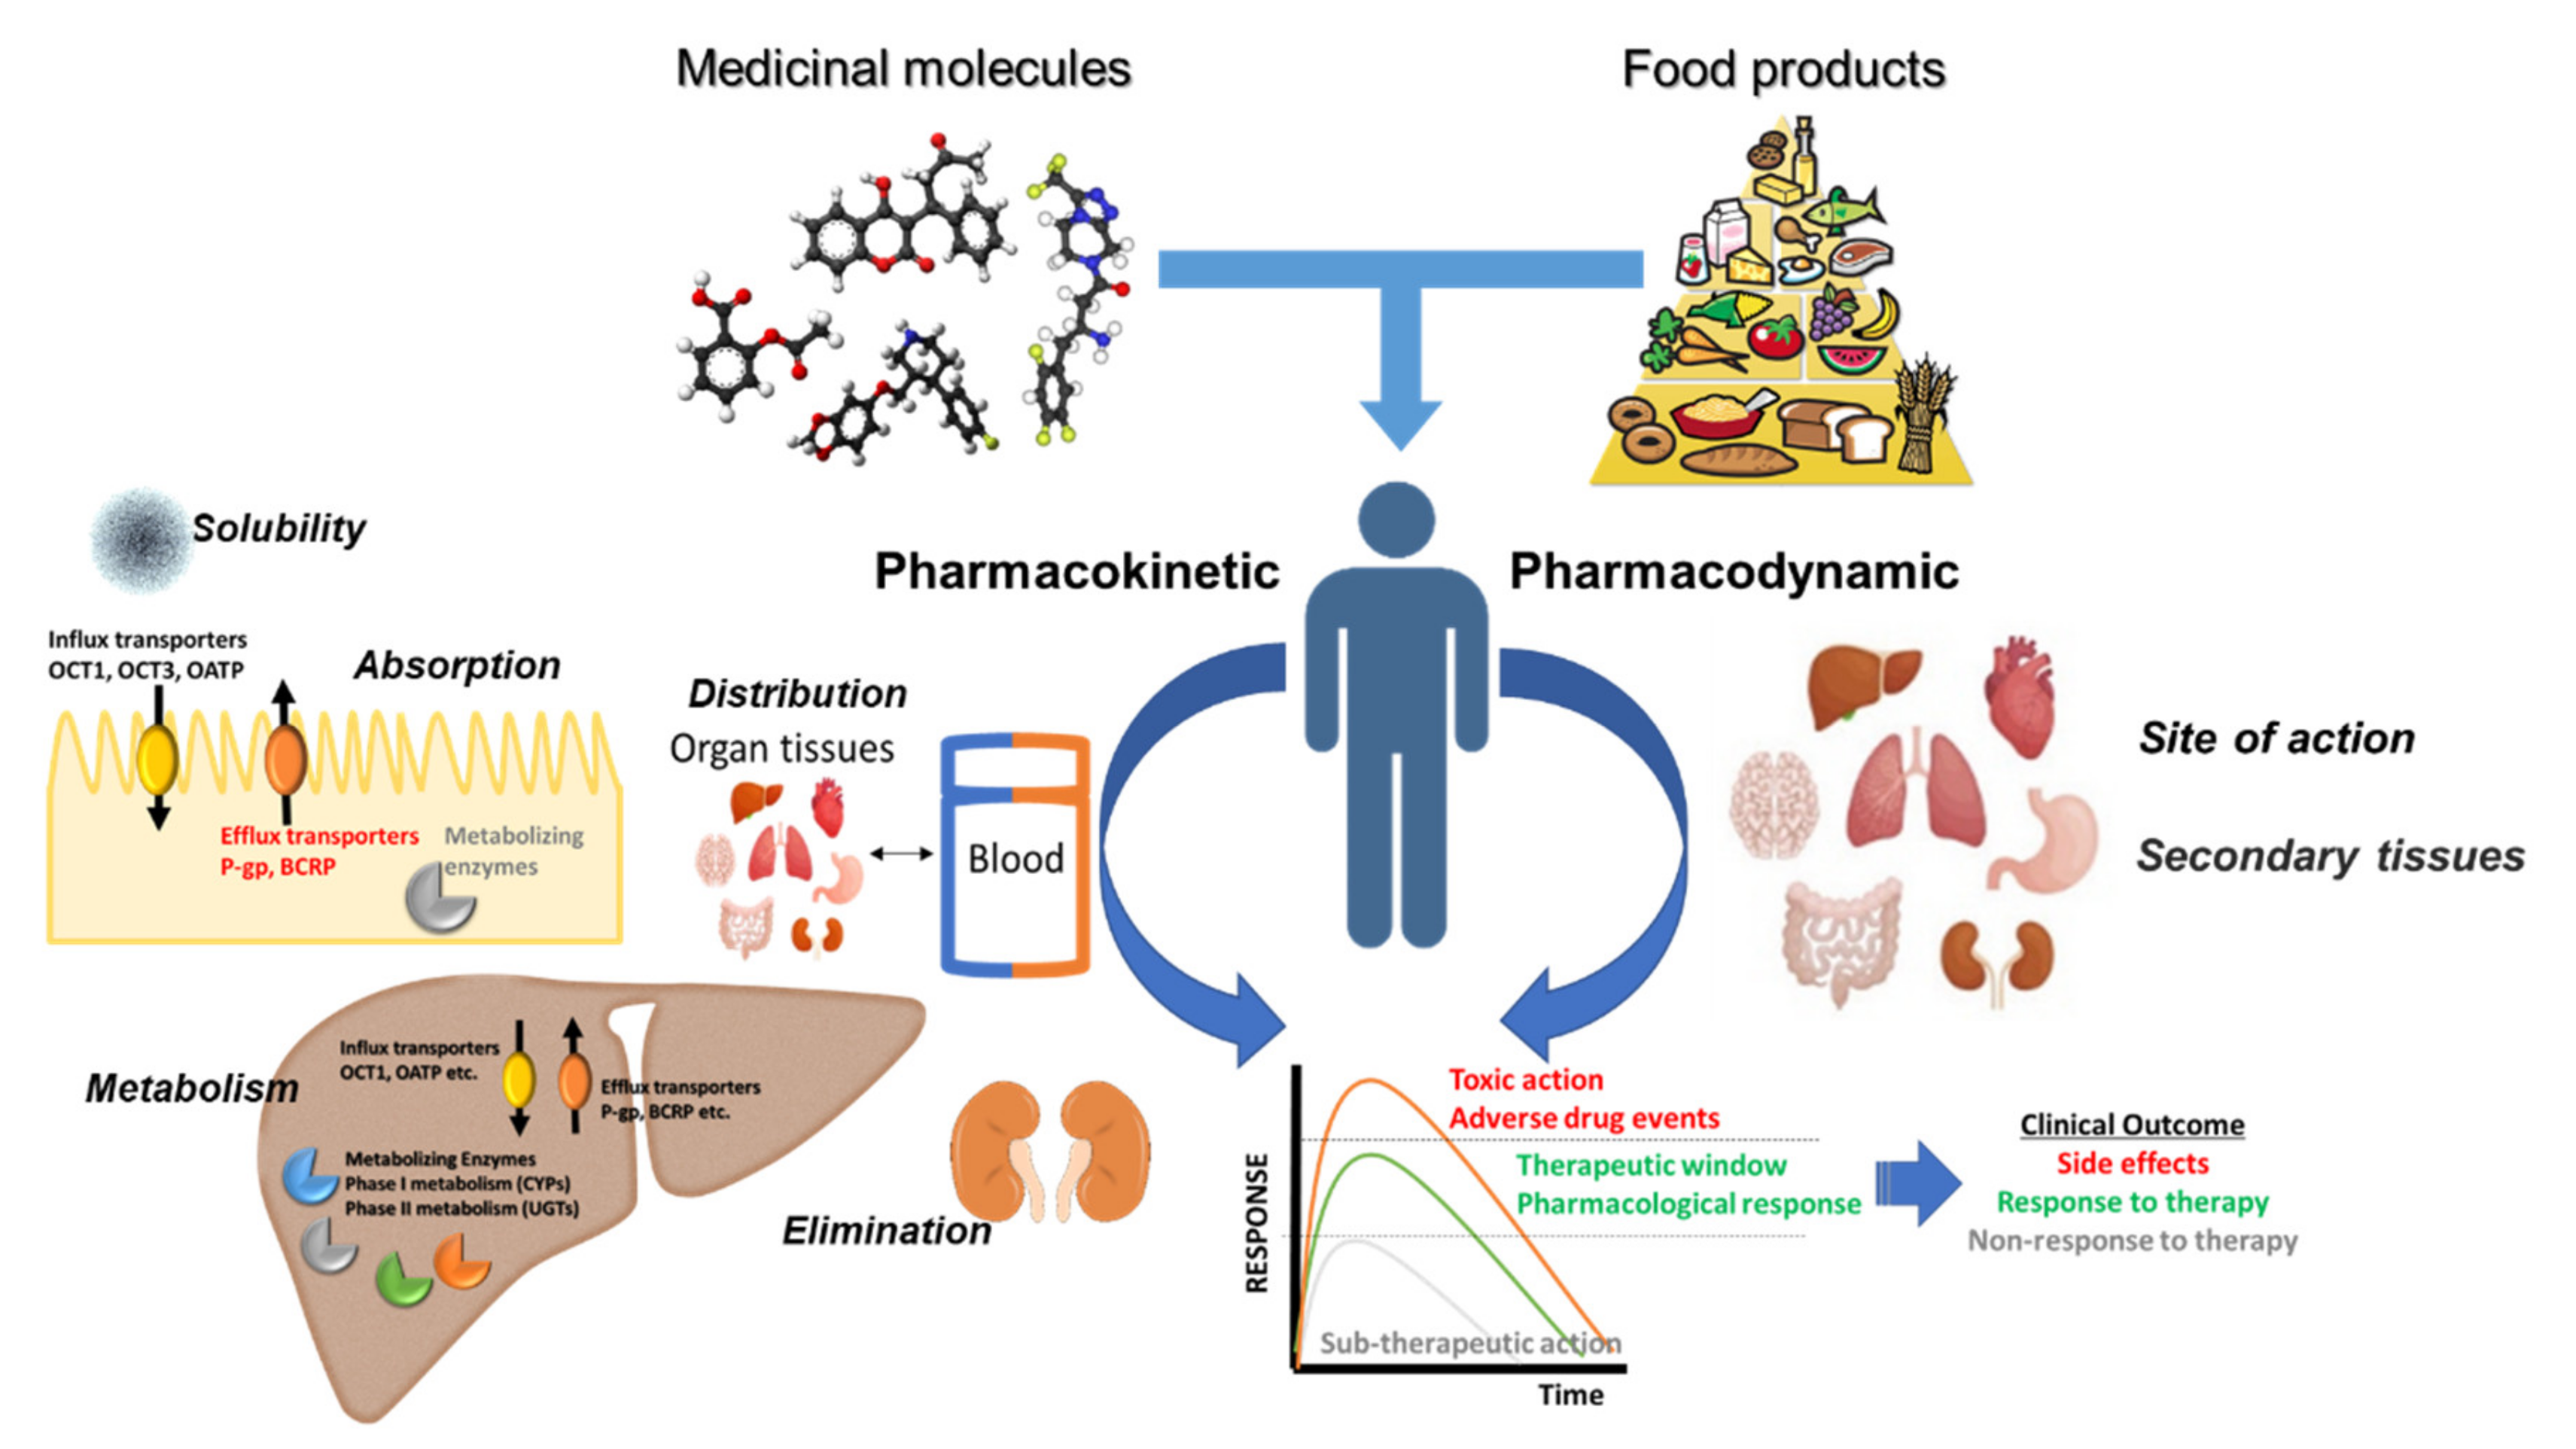
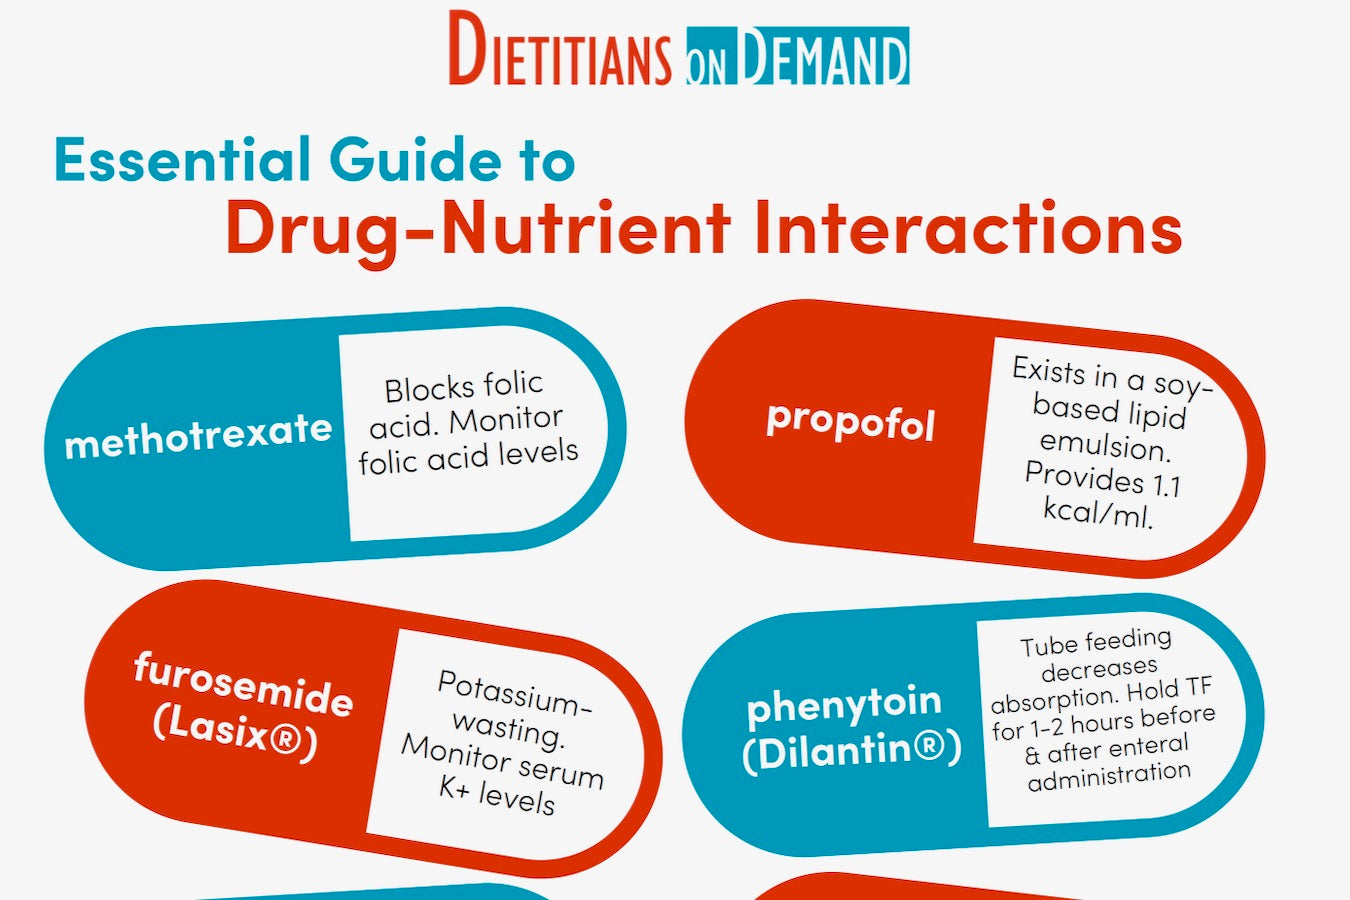
The interactions generally fall into three buckets: absorption, metabolism, and excretion. Absorption issues are the most common and the most ignored. Metformin decreases B12 absorption by altering calcium-dependent membrane actions in the ileum. That's not theoretical—metformin users have significantly higher B12 deficiency rates compared to the general population, and it's not addressed in most prescribing guidelines. I see it constantly. Metformin, then fatigue, then we discover the B12 has been dropping for years. Warfarin and vitamin K is the interaction everyone knows, but it's more nuanced than the standard warning suggests. It's not about avoiding leafy greens. It's about consistency. A patient on a stable warfarin dose who suddenly doubles their intake of spinach or kale will see their INR drop. But a patient who eats the same amount week to week generally has no problem. The issue is variability, not the nutrient itself. I once had a patient whose INR went unstable because she started a green smoothie routine without telling anyone. It took three weeks to recalibrate her dose. Another one that surprises people: tetracycline and fluoroquinolone antibiotics bind to divalent cations. Calcium, magnesium, iron, zinc—they all form insoluble complexes with these drugs in the gut. Bioavailability of the antibiotic drops significantly. The standard advice is to separate by two hours, but in practice I recommend four to six hours. That gives a wider margin and accounts for gastric emptying time. I track this with my patients on chronic medications and it prevents a lot of silent treatment failures.
Statin use is another area where nutrient depletion matters. Statins inhibit HMG-CoA reductase, which is the same pathway that produces CoQ10. Supplementing with CoQ10 at 100-200mg daily is reasonable for patients on long-term statin therapy, particularly if they report muscle symptoms. The evidence isn't conclusive, but the mechanistic link is solid and the supplement is low risk. I don't prescribe it routinely, but I bring it up at follow-up visits. There are also interactions that work in reverse—nutrients affecting drug metabolism. Grapefruit juice inhibits CYP3A4 in the intestinal wall. This isn't just a drug interaction warning on a brochure. It's clinically significant for drugs like simvastatin, felodipine, and some immunosuppressants. One grapefruit or a glass of juice can increase drug exposure by 2-3 fold. The effect lasts about three days because the enzyme inhibition is irreversible—new enzyme has to be synthesized. Patients often don't connect the dots because they might have a glass of juice once and not notice anything immediately. Here's what most guides leave out: the timing of meals relative to medication matters more than most people realize. Taking levothyroxine with breakfast, even black coffee, reduces absorption. The recommendation is empty stomach, 30-60 minutes before food. But a lot of patients don't adhere to this. I've had patients whose TSH was marginally elevated despite adequate dosing. The issue was they were taking it with their morning coffee. Switching to bedtime dosing resolved it without changing the dose.
Get the Full Details
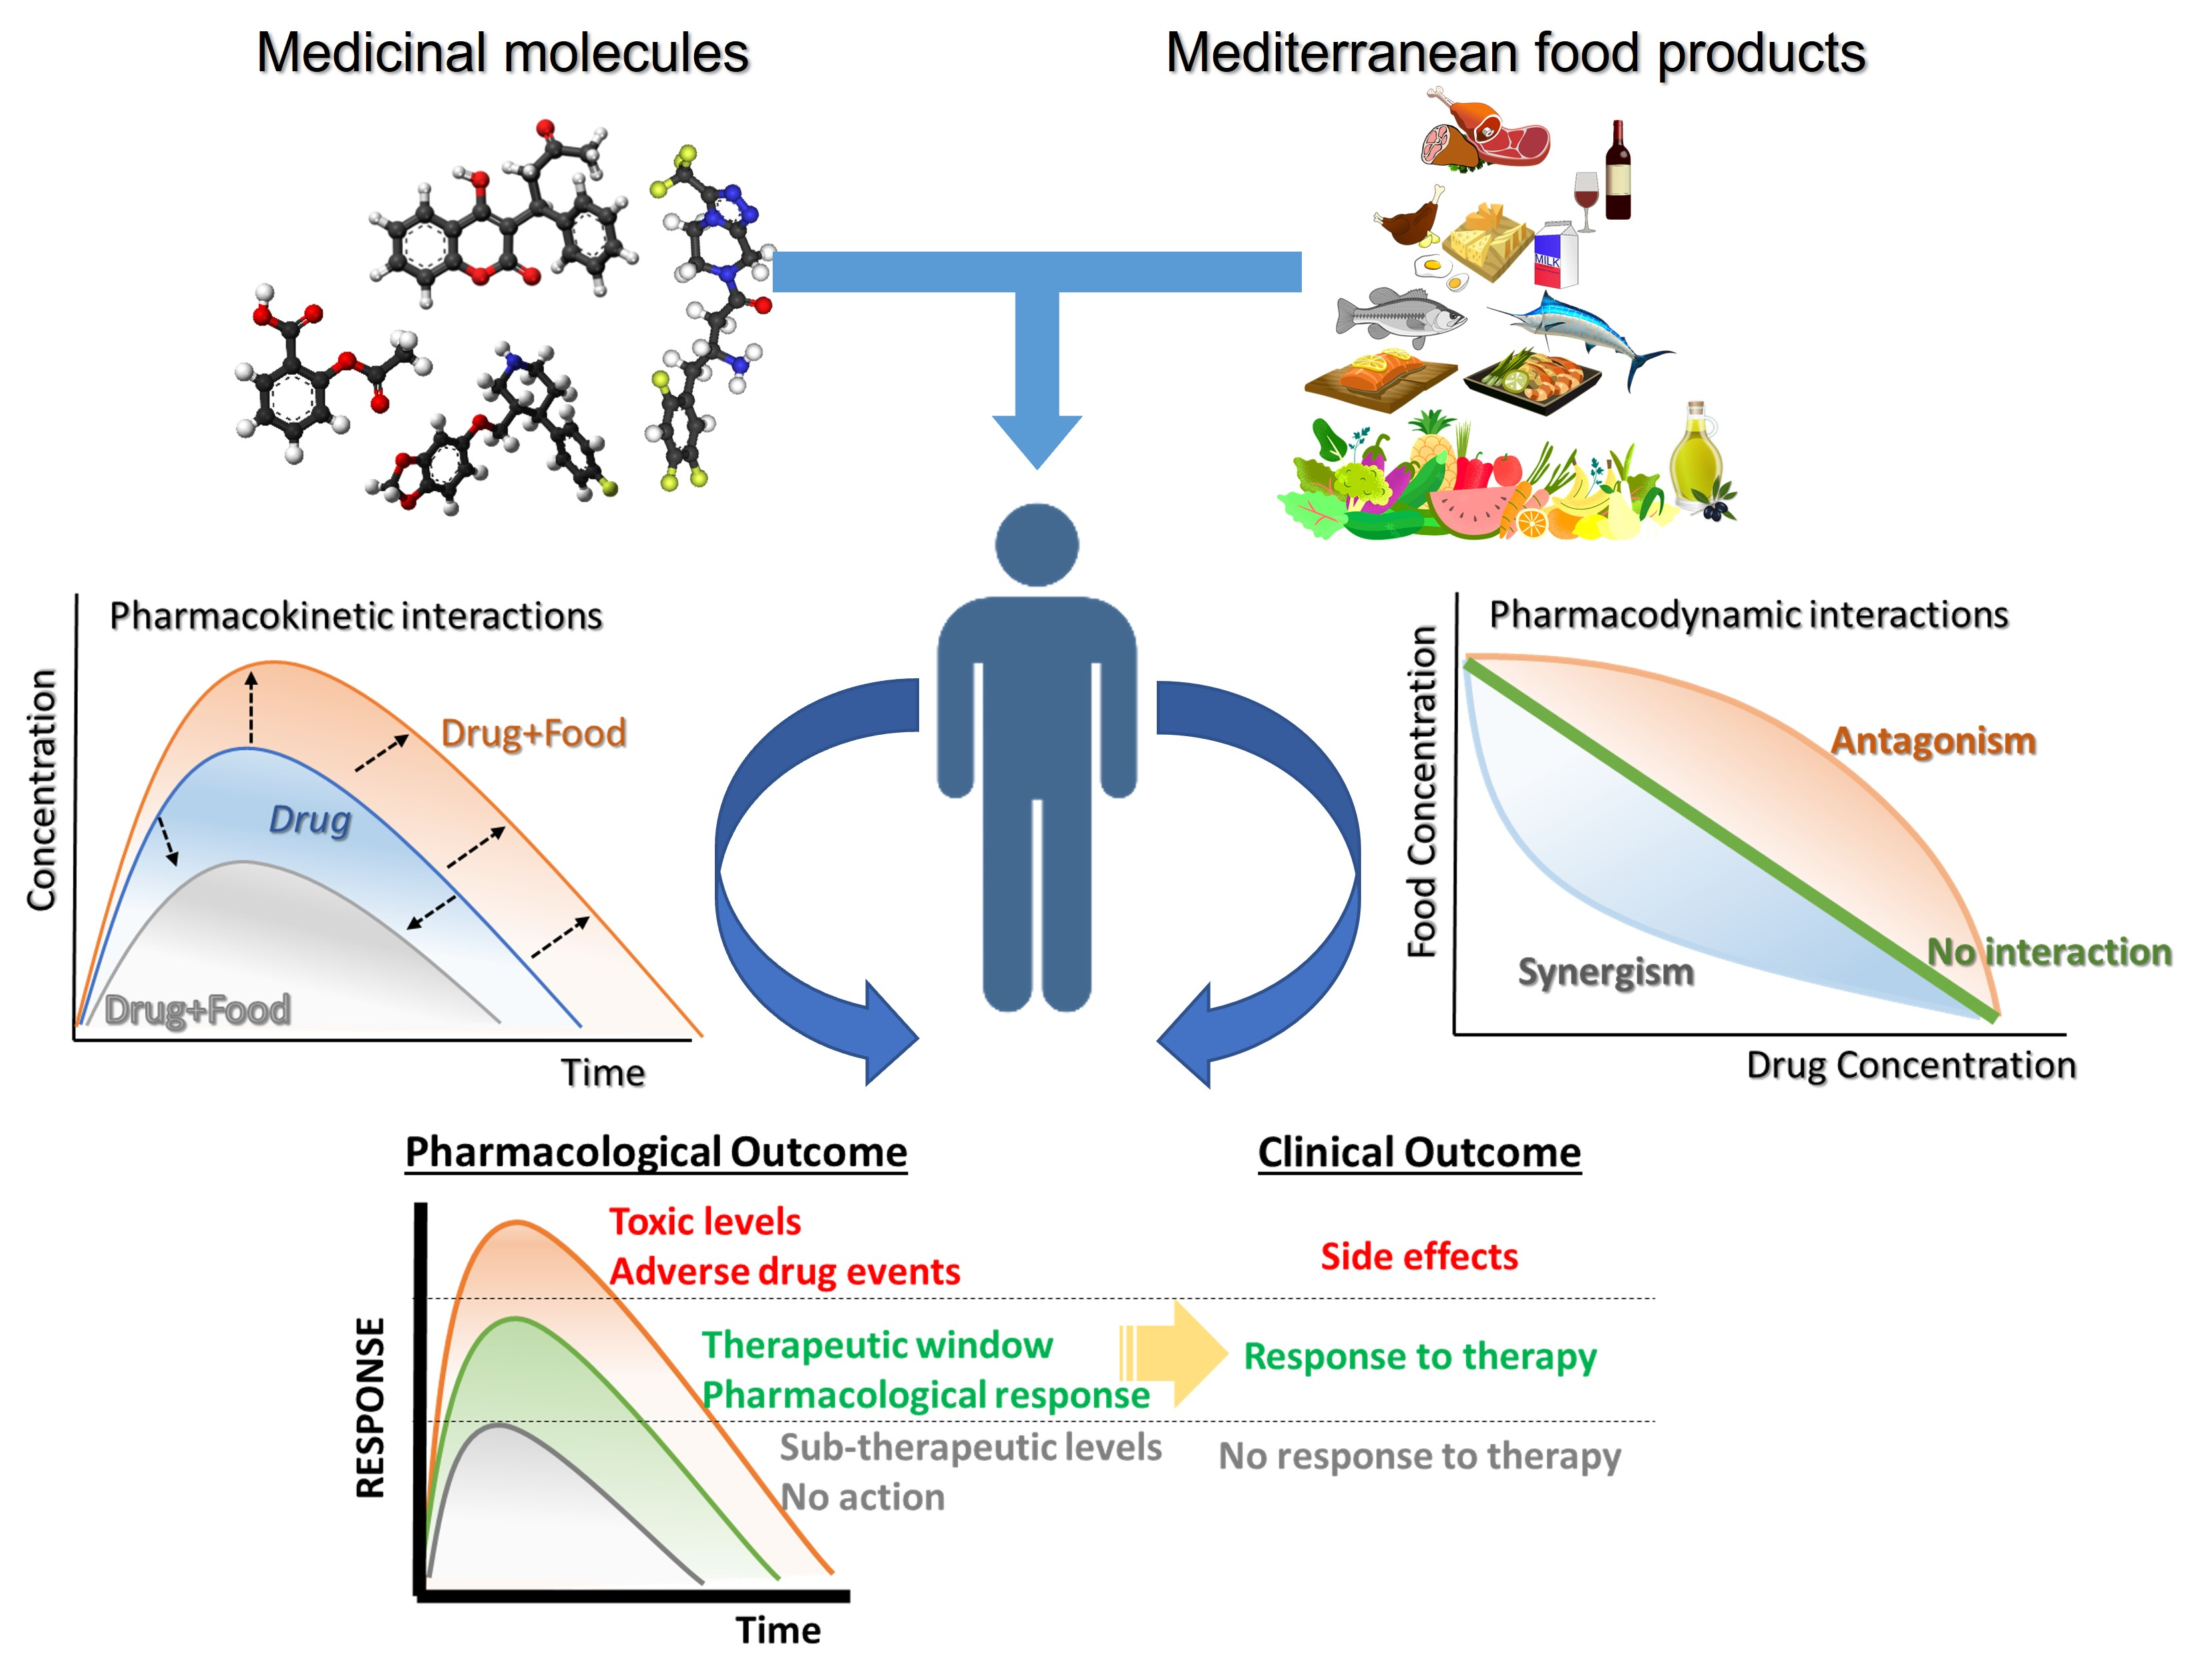
Alcohol is its own category. Chronic use induces CYP2E1 and other enzymes, which accelerates the metabolism of certain drugs. Acetaminophen is the classic example—alcohol + acetaminophen = increased risk of hepatotoxicity because both compete for glutathione depletion pathways. But it's not just acetaminophen. Alcohol also depletes folate, zinc, and magnesium, which compounds the problem over time. I ask every patient about alcohol intake when reviewing medications. It's a five-second question that catches a lot of issues. The biggest limitation I have to acknowledge is that interaction checkers are terrible. Most online tools have absurd sensitivity—they'll flag 300 potential interactions for a given drug, and 95% of them are theoretical or clinically irrelevant. They're useful as a starting point but dangerous as a final answer. I rely on naturalmed.org and the Micromedex drug-nutrient database because they're more selective and cite primary sources. Even those have gaps. There's no comprehensive database that accounts for the full spectrum of individual variability—genetics, baseline nutrition, gut health, age, kidney function. Any interaction checker that claims to is overselling itself. Another blind spot is that most databases don't distinguish between isolated nutrients and whole foods. Getting iron from a spinach salad is different from taking an iron supplement, because the food matrix affects absorption rate and the presence of other compounds can either enhance or inhibit uptake. The interaction profile of a supplement isn't the same as the interaction profile of a meal.
For anyone managing this clinically or personally, the practical takeaway is straightforward: review medications quarterly with a focus on known depleters, check baseline nutrients before starting long-term therapy when possible, and separate supplements from medications by at least two hours as a default. That last part alone prevents most absorption-related interactions without requiring detailed knowledge of every specific combination.