Understanding the Dys Prefix in Medical Terminology
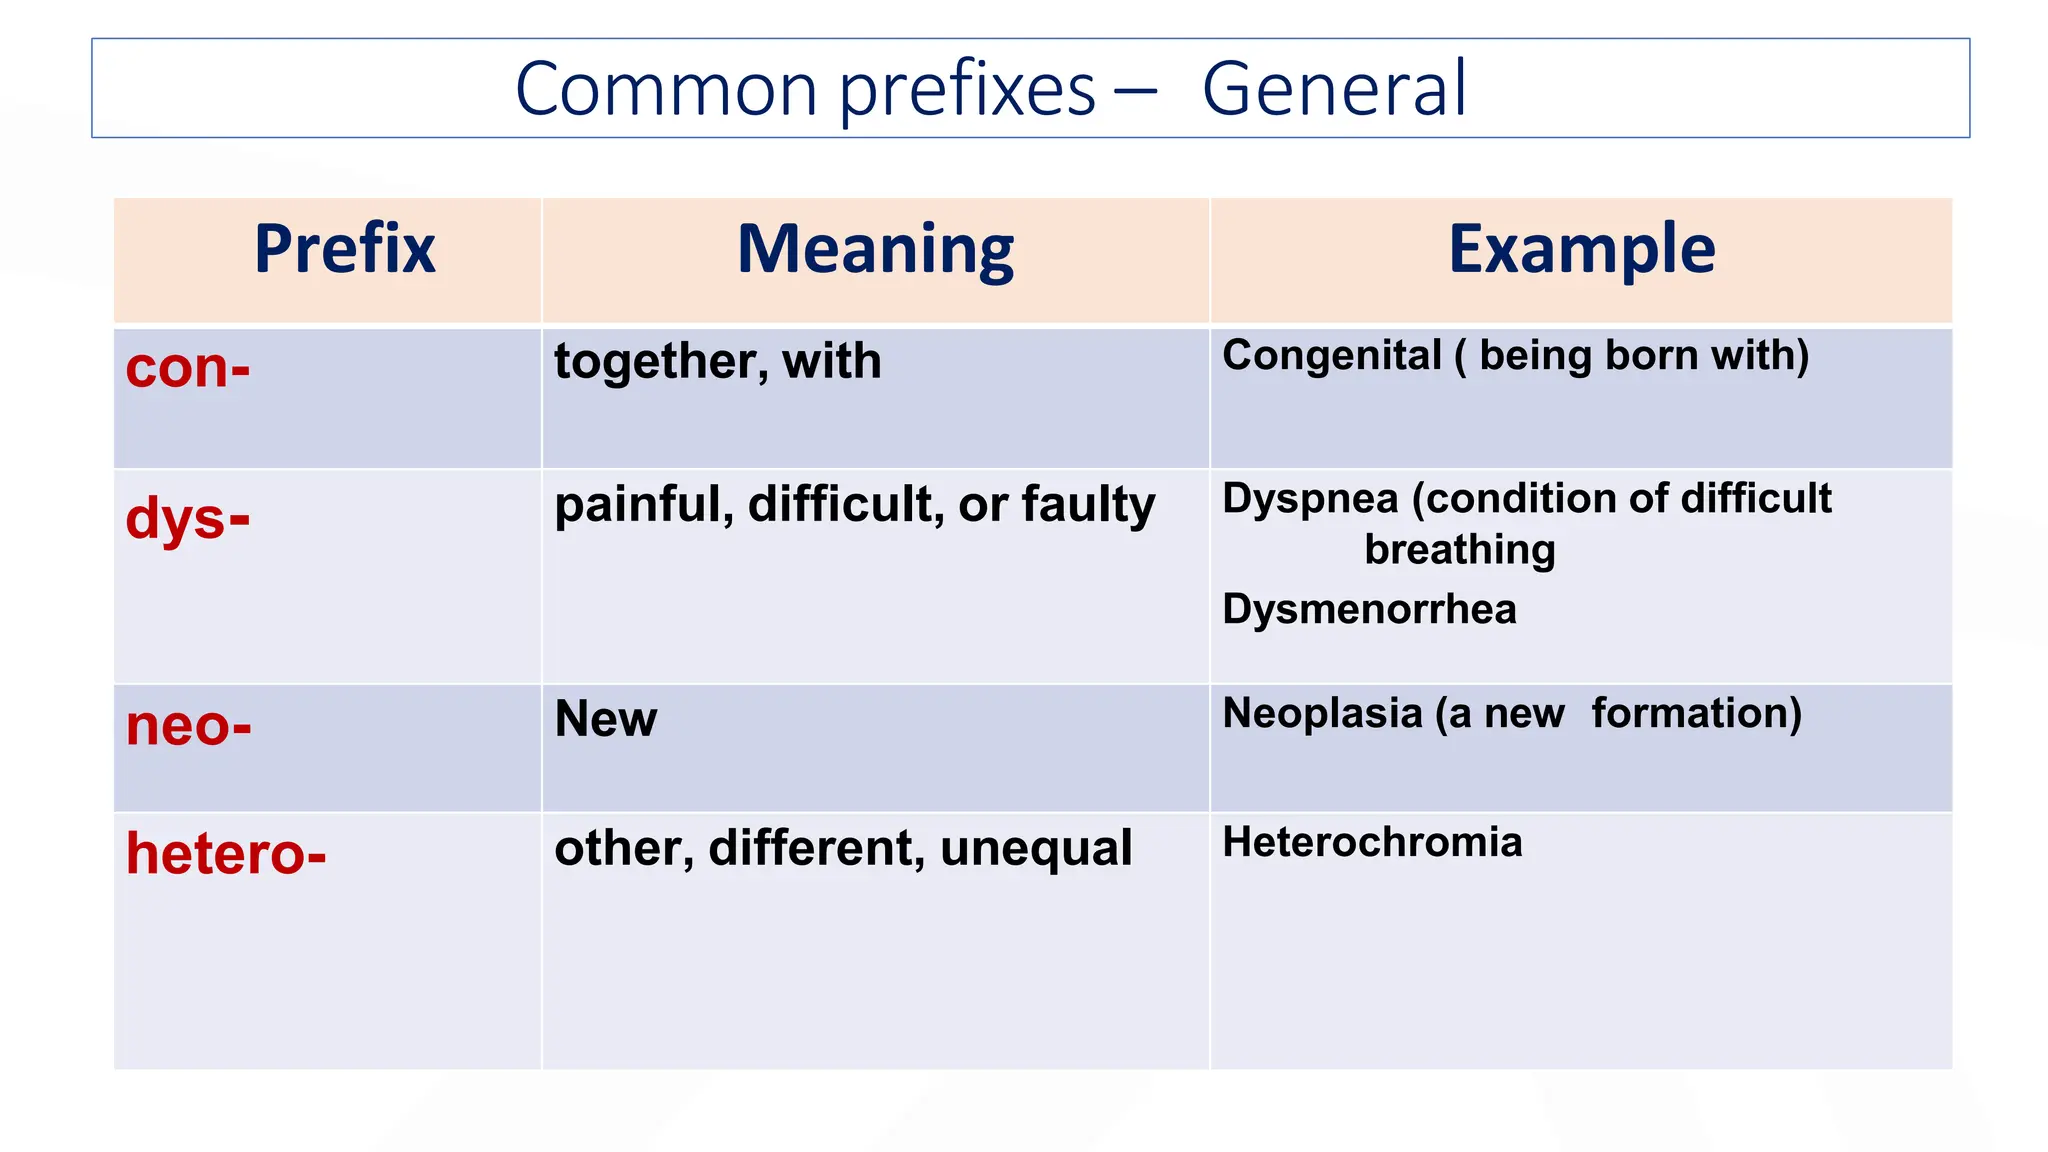
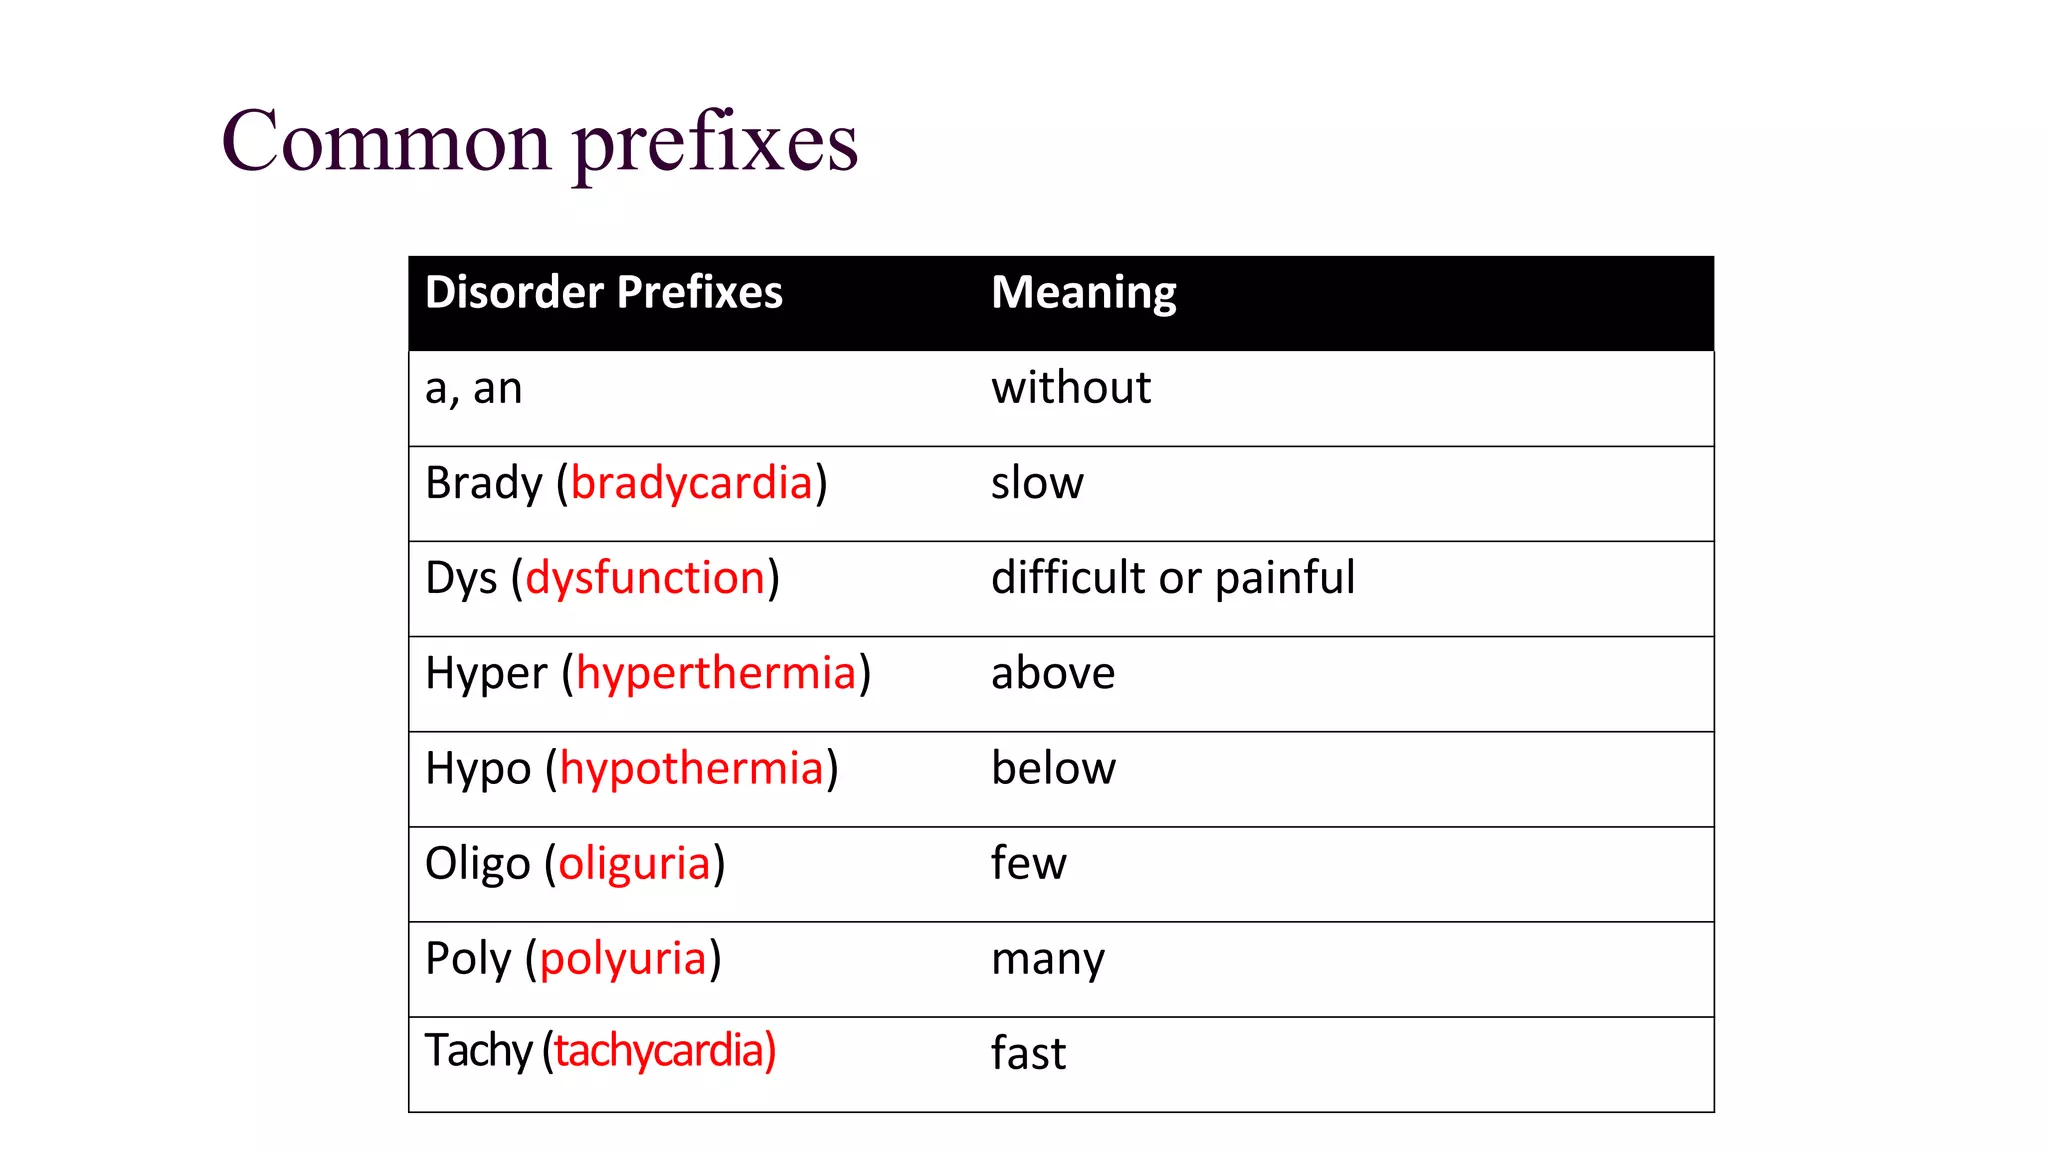
The prefix dys- comes from Greek and basically means "bad," "difficult," or "abnormal." It shows up constantly in clinical language, and if you're studying for exams or working in a medical setting, you'll see it everywhere. The key thing to understand is that dys- doesn't point to one specific disease. It describes a category of dysfunction across multiple body systems. When you see dys- attached to a root word, it signals that a particular function is impaired or abnormal. Dystonia means abnormal muscle tone. Dysphagia means difficulty swallowing. Dyspnea means difficult breathing. The pattern is consistent. The prefix modifies the root to indicate something isn't working the way it should. I've found that the trick to really locking this in is understanding what the root word means first. If you don't know that phagia relates to swallowing, then dysphagia is just a random string of letters. But if you break it down, it becomes dys + phagia = bad/hard swallowing. That's how medical terminology actually works. You build from the root outward.
One edge case that catches people up is when dys- appears in conditions where the abnormality isn't just "difficulty" but actually pathological absence. Dysgenesis, for instance, doesn't mean "hard to generate." It means defective or abnormal development of an organ. I ran into a resident once who confidently told me dysplasia meant "poor growth" when I asked about cervical dysplasia. It technically means disordered growth, but in clinical practice it specifically refers to pre-cancerous cellular changes. Saying it means "poor growth" would get you in trouble on rounds.
How to Use This in Practice
The most useful approach I've found is to group the terms by body system rather than trying to memorize a giant alphabetical list. Here's the breakdown that actually stuck for me: Respiratory system: Dyspnea is the big one. It's not just "shortness of breath" in casual speech. In a clinical context, it's a standardized symptom that patients describe as air hunger, chest tightness, or inability to get a full breath. You'll see it documented constantly in COPD, asthma, and heart failure charts. Then there's dysphonia, which is specifically abnormal voice production due to vocal cord dysfunction. Gastrointestinal system: Dysphagia covers difficulty swallowing at any level, from the mouth down through the esophagus. The distinction between oropharyngeal and esophageal dysphagia matters because the workup is completely different. Oropharyngeal usually points to neuromuscular problems. Esophageal often means mechanical obstruction or motility disorder. Dyspepsia is another common one — it means indigestion or discomfort in the upper abdomen, but in practice it's a diagnosis of exclusion after you rule out ulcers, gallbladder disease, and H. pylori infection.
Get the Full Details

Neurological system: Dysarthria is impaired speech due to neurological damage affecting the muscles of articulation. Differentiate this from aphasia, which is a language processing problem. I've seen plenty of people mix those two up because both affect speech. Dyspraxia involves difficulty with planned motor movements. This shows up in developmental coordination disorder and can also occur after stroke. Genitourinary system: Dysuria is painful or difficult urination. This is one of the most common presenting complaints in both outpatient and emergency settings. The differential is broad — UTI, STI, prostate issues, interstitial cystitis, kidney stones. It sounds simple but the workup takes time. Oncology and pathology: Dysplasia and neoplasia are terms you need to separate clearly. Dysplasia is disordered cell growth that can be reversible. Neoplasia is new, uncontrolled growth that is generally irreversible. The progression from dysplasia to neoplasia to carcinoma in situ to invasive cancer is a timeline that matters for staging and treatment decisions. I worked through a case where a patient had severe cervical dysplasia that was monitored for two years before progressing. That's why the grading system (CIN 1, 2, 3) exists — low-grade dysplasia often resolves on its own, high-grade usually needs intervention.
Common Pitfalls to Avoid
The biggest mistake people make is assuming dys- always means the same severity. It doesn't. Dysphagia could be mild trouble with dry foods or it could be complete inability to swallow liquids. The prefix itself doesn't convey degree. You need the clinical context or modifiers to understand how bad it actually is. Another issue is confusing dys- with related prefixes. Para- means abnormal but also partial or beside. It's not interchangeable with dys-. Poly- means many. Neither one functions the same way. And di- means twice or double, which is completely different despite sometimes appearing in similar contexts. The prefix also has limits. It describes dysfunction but not cause. Saying a patient has dyspnea tells you they're having trouble breathing. It doesn't tell you whether it's cardiac, pulmonary, metabolic, or anxiety-related. That's the next step in the actual workup. The prefix is a starting point, not a diagnosis.
I'll also note that dys- terms can overlap. A patient with advanced heart failure might present with dyspnea on exertion AND dysuria from a concurrent UTI. The prefix alone won't help you figure out which is primary. You need the full clinical picture. That's just how it is.

A Quick Reference for Common Terms
Dysphagia — difficulty swallowing Dyspnea — difficulty breathing Dysuria — painful urination
Dysarthria — impaired speech production Dysphonia — abnormal voice quality Dysmenorrhea — painful menstruation
Dyslexia — specific reading and language disorder Dysplasia — abnormal tissue development Dystonia — abnormal muscle tone or posture

Dysgenesis — defective organ formation Dyspepsia — indigestion or upper abdominal discomfort Dyslipidemia — abnormal lipid levels
Dysautonomia — dysfunction of the autonomic nervous system Learning these by rote helps for flashcards, but the real utility comes from understanding the structure. Once you know that dys- modifies the root to indicate dysfunction, you can decode terms you've never seen before. If you encounter dyschiria, for example, you can infer it means abnormal directional sense even if you've never heard the word. That's the practical advantage of actually learning the system instead of memorizing individual definitions.