
Where to Start When You're Drowning in Leads
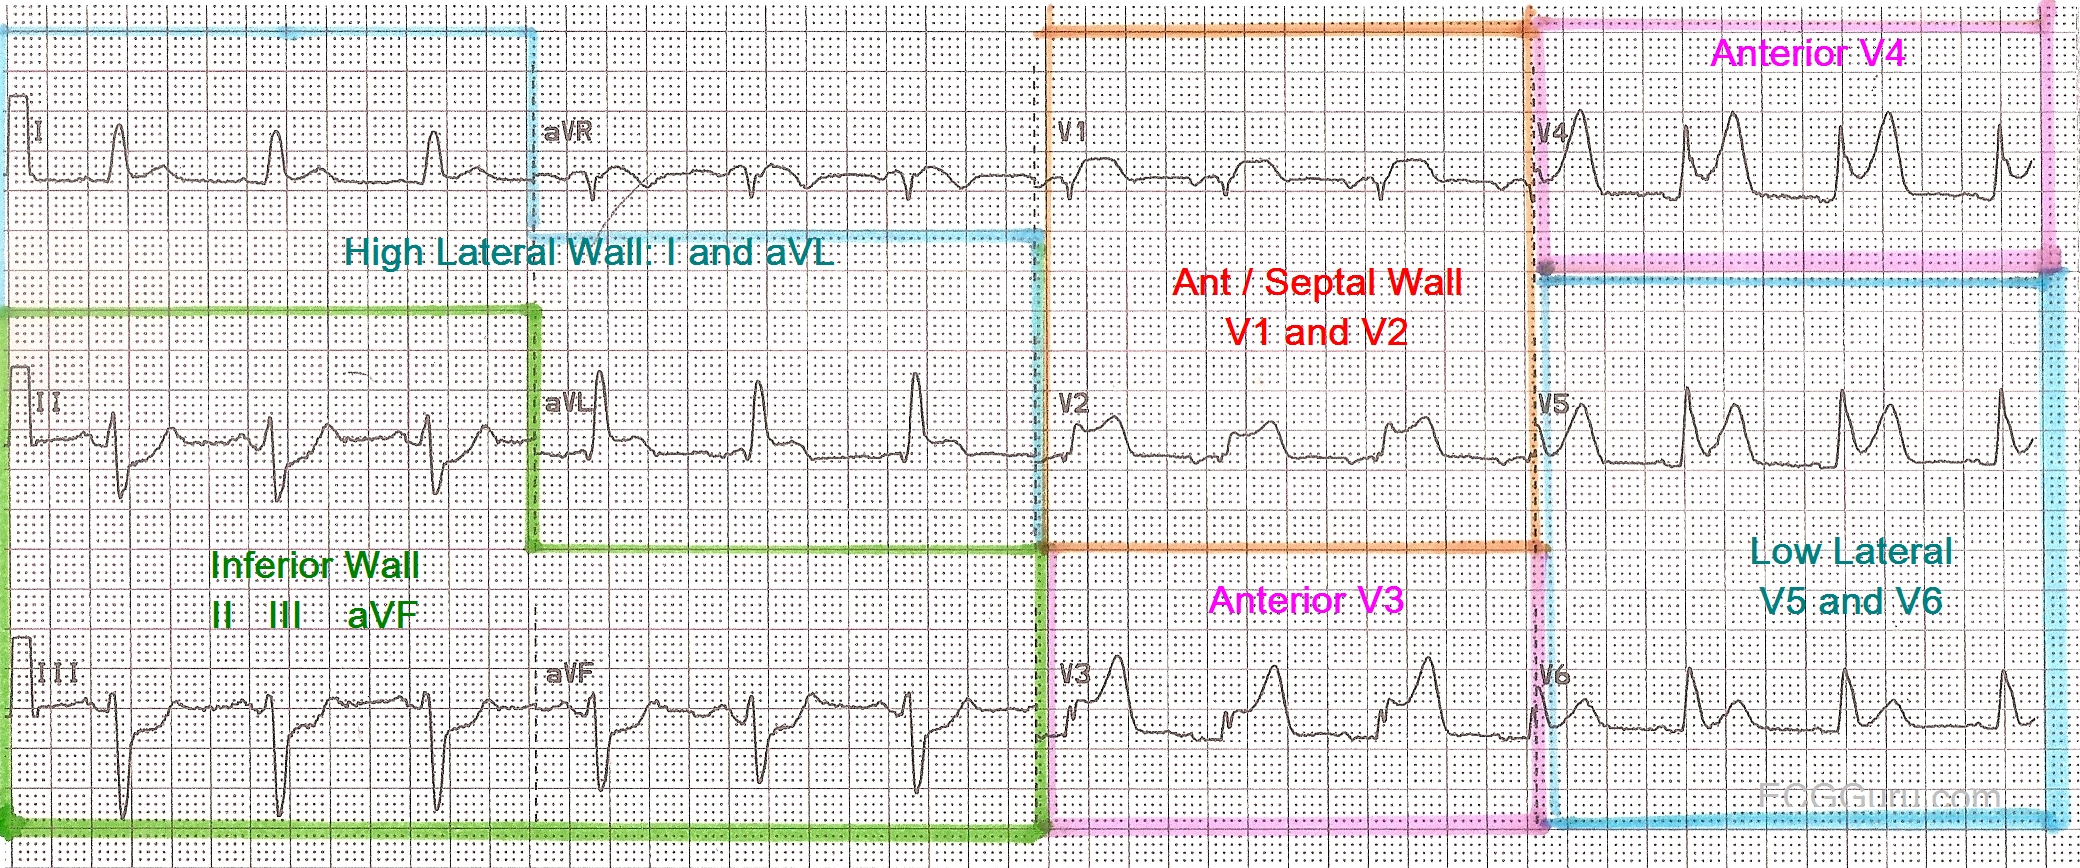
The most useful way to approach a 12-lead ECG is to stop looking at all twelve leads at once. It doesn't work. The method that actually saved my sanity was reading the rhythm first, then scanning for the axis, then moving lead by lead in a fixed sequence, and only then deciding what was abnormal. That's it. When you look for everything everywhere, you miss the actual pathology. I learned this the hard way during a night shift when a patient came in with chest pain and I spent forty-five seconds staring at V3 while a massive lateral ST elevation walked right past me because I was scanning for Q waves instead of ST segments. Here is the workflow I actually use, not some textbook fantasy version. First, pick your rhythm lead. Lead II is usually the cleanest. Check the rate, check the regularity, and determine whether there is a P wave before every QRS. If there's no P wave, you now know you're dealing with an arrhythmia and the rest of the interpretation shifts entirely. Second, calculate the axis using leads I and aVF. Positive both means normal axis. Positive I, negative aVF means left axis deviation. Negative I, positive aVF means right axis deviation. Both negative means extreme axis deviation or poor lead placement. This takes about ten seconds and tells you more than you'd think. Third, look at the precordial leads V1 through V6 in order. Watch the R-wave progression. If the R wave never gets bigger than about 7mm by V3 or V4, you may have poor R-wave progression, which can indicate a prior anterior infarct, lead misplacement, or just a technically difficult patient. Fourth, examine each lead for ST changes. I look at the J point, which is the junction between the QRS complex and the ST segment. ST elevation or depression at the J point is where the real signal lives. Fifth, check the QT interval. Roughly speaking, if the QT is less than half the R-R interval, you're probably fine. If it's longer, calculate it properly with Bazett's formula because a prolonged QT changes your entire risk assessment for this patient.
What People Get Wrong on Their First Read
The biggest mistake beginners make is calling early repolarization an inferior wall MI. They see ST elevation in II, III, and aVF and immediately think acute injury. The differentiator is usually the morphology. Early repolarization has concave ST segments that slope gently upward into the T wave, often with a notched J point. Inferior STEMI has convex ST segments, sometimes with reciprocal depression in aVL. Also look at the PR segment. In pericarditis, you get diffuse ST elevation with PR depression. In early repolarization, the PR segment stays where it belongs. These distinctions matter when the difference between sending a patient home and activating the cath lab. Another common error is missing posterior wall MI. The standard 12-lead doesn't directly visualize the posterior wall. What you see on a routine ECG is reciprocal change: tall R waves in V1 and V2, ST depression in the anterior leads, and upright T waves in those same leads. If you're suspicious, place posterior leads V7, V8, and V9 and you'll see actual ST elevation confirming the diagnosis. I remember a patient with posterior MI who looked completely non-diagnostic on the standard 12 leads except for some vague ST depression in V3. The posterior leads showed 3mm of ST elevation. That patient went straight to the cath lab and had a totally occluded right coronary artery. Time matters here.
A Real Problem I Encountered
Two years ago I was interpreting an ECG from a patient who had undergone a left upper extremity amputation. The standard lead placement guidelines didn't apply cleanly. I ended up placing the left arm lead on the residual limb just distal to the amputation site, which gave usable signals but introduced some artifact. The workaround was swapping the arm leads and placing the left arm electrode on the left shoulder instead of the left wrist. This is documented in the literature as an acceptable alternative when standard placement isn't possible. The QRS morphology changed slightly because the electrical vector relative to the electrodes shifted, but the diagnostic information remained adequate. I noted the modified placement on the ECG tracing itself so whoever reads it next knows what to expect. This kind of thing never comes up in the basics, but it happens often enough in clinical practice that you need a strategy before you need it. One thing that surprises people is that lead aVR can be diagnostically crucial and most beginners completely ignore it. aVR looks at the heart from the right shoulder. In left main coronary artery occlusion, you'll see ST depression across most of the ECG and ST elevation specifically in aVR. In the right ventricular infarct scenario, you need right-sided leads and V4R shows the ST elevation that standard V1 through V6 might miss entirely. Another counter-intuitive point: sinus tachycardia is rarely the primary diagnosis. It's almost always a response to something else. When you see a fast rate with normal P waves, your job is to find the cause. Pain, fever, hypovolemia, sepsis, pulmonary embolism, anemia, hyperthyroidism. The ECG doesn't tell you which one, but it rules out the ones that would kill you fastest. A note on AI-assisted interpretation tools: There are automated reading software packages available, some free and some paid, that claim to assist with 12-lead ECG interpretation. I've used several over the years. They catch obvious abnormalities surprisingly well, but they also generate false positives at a rate that makes them more of a nuisance than a help in low-prevalence settings. A study published in 2022 found that automated ECG readers had a specificity of around 82% in general cardiology populations, meaning roughly one in five "abnormal" flags was wrong. Use them as a second pair of eyes, not a first opinion. The algorithm missed a subtle Brugada pattern in one of my patients last year. I caught it because I was looking at the right place. The machine called it normal sinus rhythm.
Get the Full Details
Limitations You Need to Accept
The 12-lead ECG has real limitations. It's a snapshot in time. A patient with intermittent angina can have a completely normal ECG between episodes. Serial tracings are better. The ECG also has limited sensitivity for non-ST-elevation ACS. Up to 50% of patients with acute coronary syndrome have no diagnostic ST changes on their initial ECG. Troponin and clinical context fill that gap. For atrial fibrillation detection, a single 12-lead is decent but ambulatory monitoring catches paroxysmal cases that a one-time ECG misses entirely. And of course, lead placement errors account for probably 10 to 15% of "abnormal" readings in busy clinical settings. If the ECG doesn't match the clinical picture, repeat it with careful attention to anatomical landmarks before changing your management plan. I don't maintain a dedicated downloadable guide for Easy 12 Lead Ecg Interpretation anymore, but the American Heart Association publishes free quick-reference cards that cover the standard interpretation framework. The QR code on the back of most ECG paper stock links to a basic interpretation algorithm from Philips Healthcare. For clinical purposes, the Marriott Practical Electrocardiography textbook remains the gold standard reference, though it's expensive. Free alternatives include the ECG Wave-Maven case library from Brigham and Women's Hospital, which has hundreds of real cases with expert commentary. I recommend working through at least fifty cases from that database before you feel comfortable interpreting ECGs independently. When you're first learning, spend time on normal ECGs. A hundred normal tracings will train your brain faster than fifty abnormal ones because you need a baseline. Abnormal stands out against normal. Without the baseline, everything looks weird. Shave chest hair before placing electrodes if the patient is hairy. Poor skin contact is the most common technical reason for artifact. Clean the skin with alcohol swabs if the adhesives don't stick well. Ask the patient to remain still and stop talking during the recording. Movement artifact can mimic atrial flutter or ventricular tachycardia. I've seen both misread because of patient movement during acquisition.
For the QT interval specifically, measure in lead II or V5, not V1, because V1 can artificially prolong the measurement. Use the tangent method for the QT boundary when the T wave merges with the ST segment rather than trying to pick an end point by eye. This reduces inter-observer variability significantly. And when in doubt about any finding, compare to a prior ECG. A new change is always more concerning than a chronic one, even if the absolute appearance looks dramatic. Prior tracings are the single most underutilized diagnostic tool in emergency and inpatient medicine. Request them early and don't skip the comparison step.


