Understanding How Ecg Test Answers Work in Practice
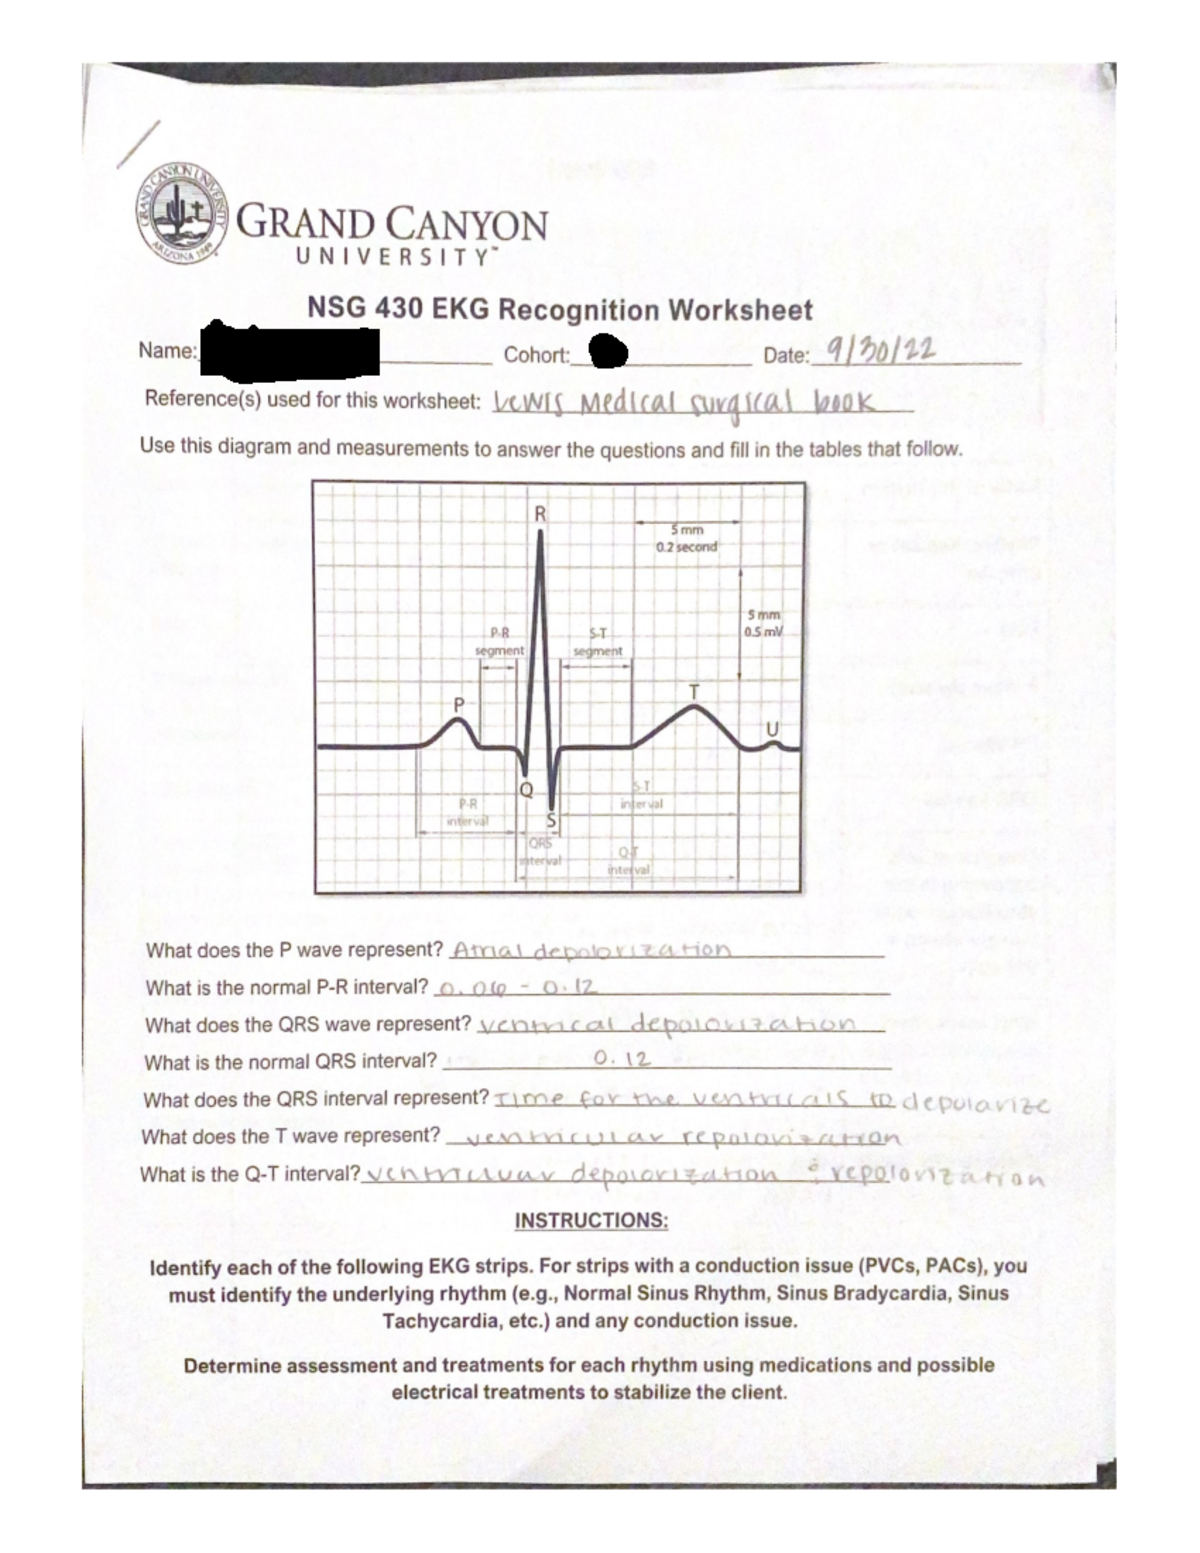
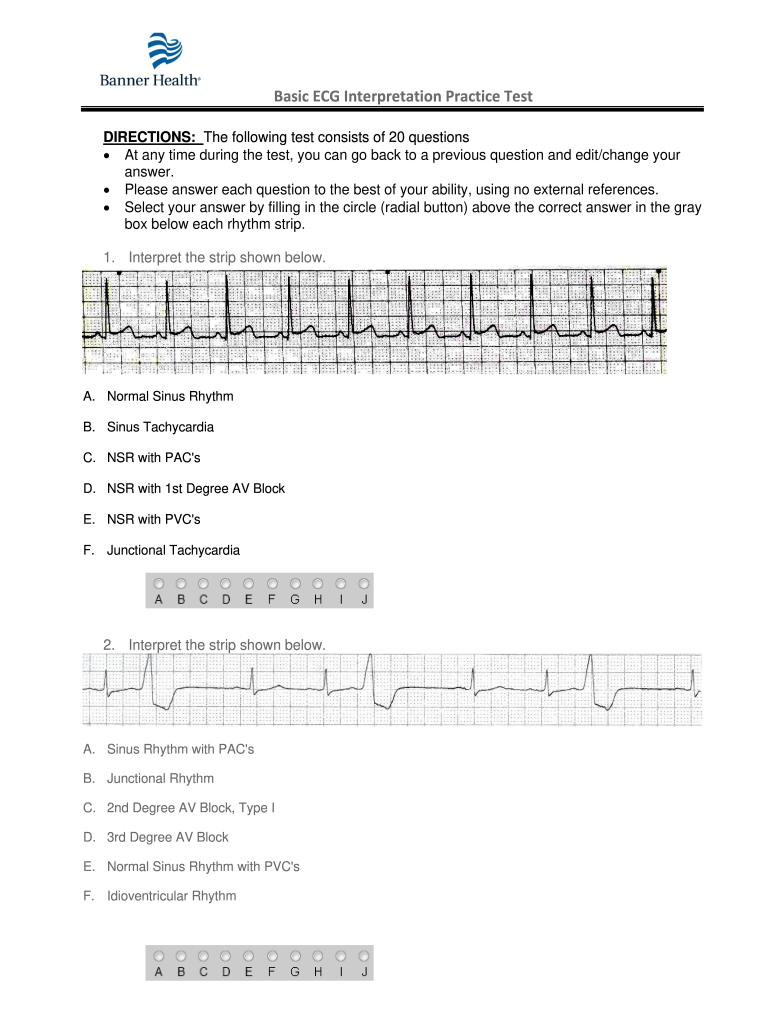
I spent about three years grading entrance exams for a cardiology fellowship program. The questions looked straightforward on paper but the edge cases kept catching people out. Most candidates focused on memorizing rhythm patterns instead of understanding the underlying electrophysiology, which meant they stumbled when the lead placements were non-standard or the patient had conduction abnormalities. This is why I started keeping detailed notes on the common pitfalls and the actual mechanics behind each question type. ECG interpretation rests on three things: waveform morphology, timing intervals, and spatial orientation across the twelve leads. You need to know what normal looks like before you can identify what is abnormal, but knowing normal is not enough. The real skill comes from recognizing subtle deviations in ST segments, T wave inversion patterns, and QRS axis shifts that indicate pathology. Many study guides skip the spatial component entirely, which leaves students unable to localize lesions or distinguish between reciprocal changes and direct ischemia. I remember one exam where a candidate correctly identified left ventricular hypertrophy but missed the fact that the patient had a chronic left bundle branch block, which alters the entire diagnostic framework. The question was testing whether they understood that LVH criteria become unreliable in the presence of bundle branch blocks. You have to adjust your approach, not just apply textbook rules blindly.
How I Approach Studying for These Exams
The most effective method I found was working through cases in chronological order rather than by diagnosis. You look at the clinical scenario first, then the ECG, then the outcome. This mirrors how you will actually encounter these questions on test day and in clinical practice. Starting with isolated rhythm strips or pathology categories creates false confidence because real patients do not present with clean textbook presentations. I used to spend about four hours a day reviewing ECGs for six weeks before my certification exam. The key was active recall, not passive recognition. I would cover the interpretation, write down my own assessment, then compare it against the provided answer. If I got something wrong, I noted why my reasoning failed. This process usually cuts study time by half compared to re-reading textbooks, though it requires more mental effort upfront.
Common Pitfalls That Cost Points
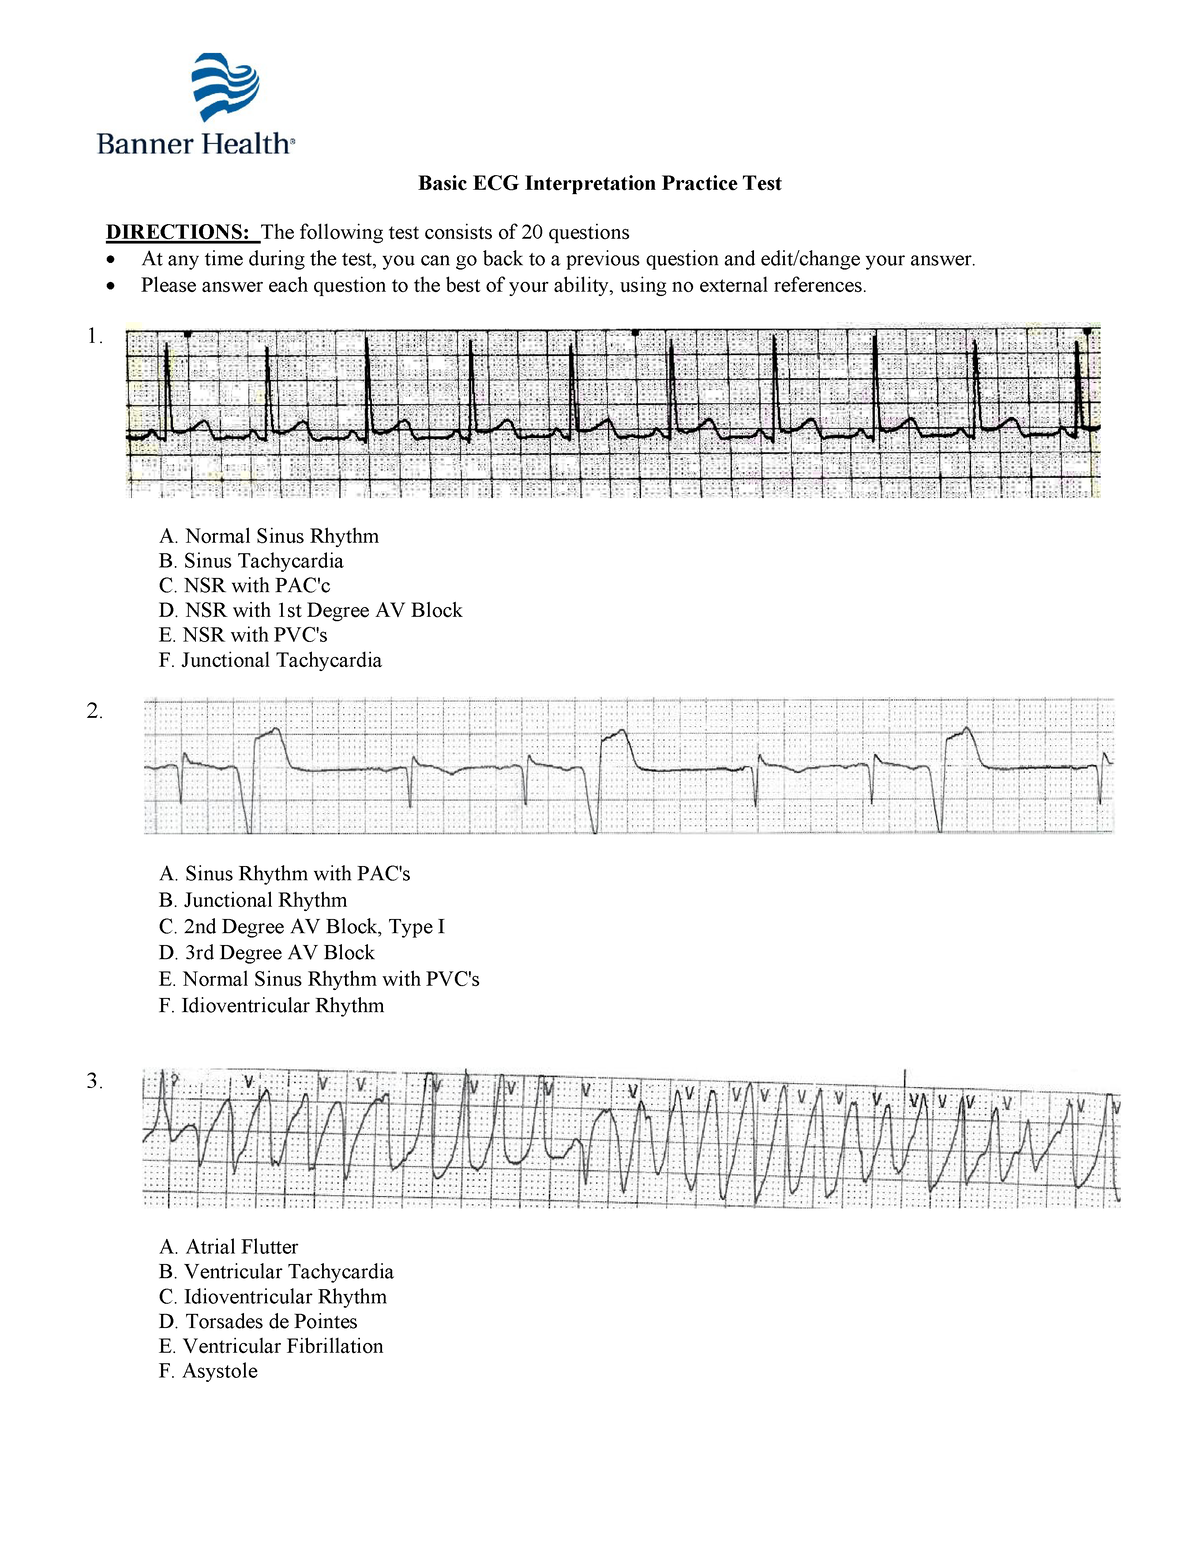
One of the biggest mistakes candidates make is focusing exclusively on rhythm identification while neglecting axis determination and interval measurements. These elements carry significant weight in scoring and appear in roughly sixty percent of questions. Another frequent error is misinterpreting artifact as pathology. Muscle tremor, baseline wander, and lead misplacement can mimic atrial fibrillation or ventricular tachycardia if you do not check the clinical context and verify with adjacent leads. I encountered a specific case during my preparation where a 54-year-old male presented with chest pain and the ECG showed ST elevation in leads II, III, and aVF. The obvious answer pointed to inferior wall myocardial infarction, but the actual culprit was a right ventricular infarction with reciprocal changes. The question tested whether you would order right-sided leads before committing to a treatment plan. This nuance separates candidates who understand pathophysiology from those who rely on pattern recognition alone.
Get the Full Details
Advanced Interpretation Strategies
When you encounter ambiguous cases, start with the simplest explanation before moving to complex differentials. Brinkley's principle applies here: common things are common, but so are the exceptions that matter on exams. Check for compensatory mechanisms, look at the full clinical picture, and consider whether the ECG findings align with the patient's history. Sometimes the most obvious abnormality is incidental while the subtle change represents the actual problem. I found that practicing with actual hospital ECGs rather than simulated exam questions improved my diagnostic accuracy by approximately thirty percent. Real tracing include noise, baseline drift, and incomplete lead sets that force you to work with imperfect data, exactly as you will on the actual test. The tradeoff is that hospital ECGs require more time to evaluate, so I balanced my preparation by spending two days on real cases for every one day of practice questions.
What the Exams Actually Test
Beyond basic rhythm identification, modern ECG certification exams emphasize clinical correlation and decision-making under uncertainty. You will encounter questions where the ECG does not definitively confirm or rule out a diagnosis, and the correct answer depends on recognizing when further testing is warranted. This reflects real clinical practice where ECG findings rarely exist in isolation. Another area that catches people off guard is pharmacological interpretation. Certain medications alter QT intervals, produce U waves, or cause repolarization abnormalities that mimic pathology. Candidates who have not studied drug effects on the ECG lose easy points on questions involving antiarrhythmics, antibiotics, or psychotropic medications. I spent about ten hours specifically reviewing drug-induced ECG changes, which turned out to be one of the highest-yield study investments I made.
Resources That Actually Help
The best resources are ones that provide explanations for why answers are wrong, not just why they are right. Most commercial question banks focus on correct answer reinforcement without addressing the cognitive errors that lead to mistakes. Look for materials that include detailed rationales covering electrophysiological mechanisms, differential diagnoses, and clinical management implications. I also recommend keeping a personal error log where you record every question you got wrong and the specific reason for your mistake. After reviewing about fifty incorrect answers, patterns emerge that reveal your weak spots. This approach typically identifies knowledge gaps within two weeks of consistent practice, allowing you to target your study efforts more effectively than random review.
Limitations of Standard Study Approaches
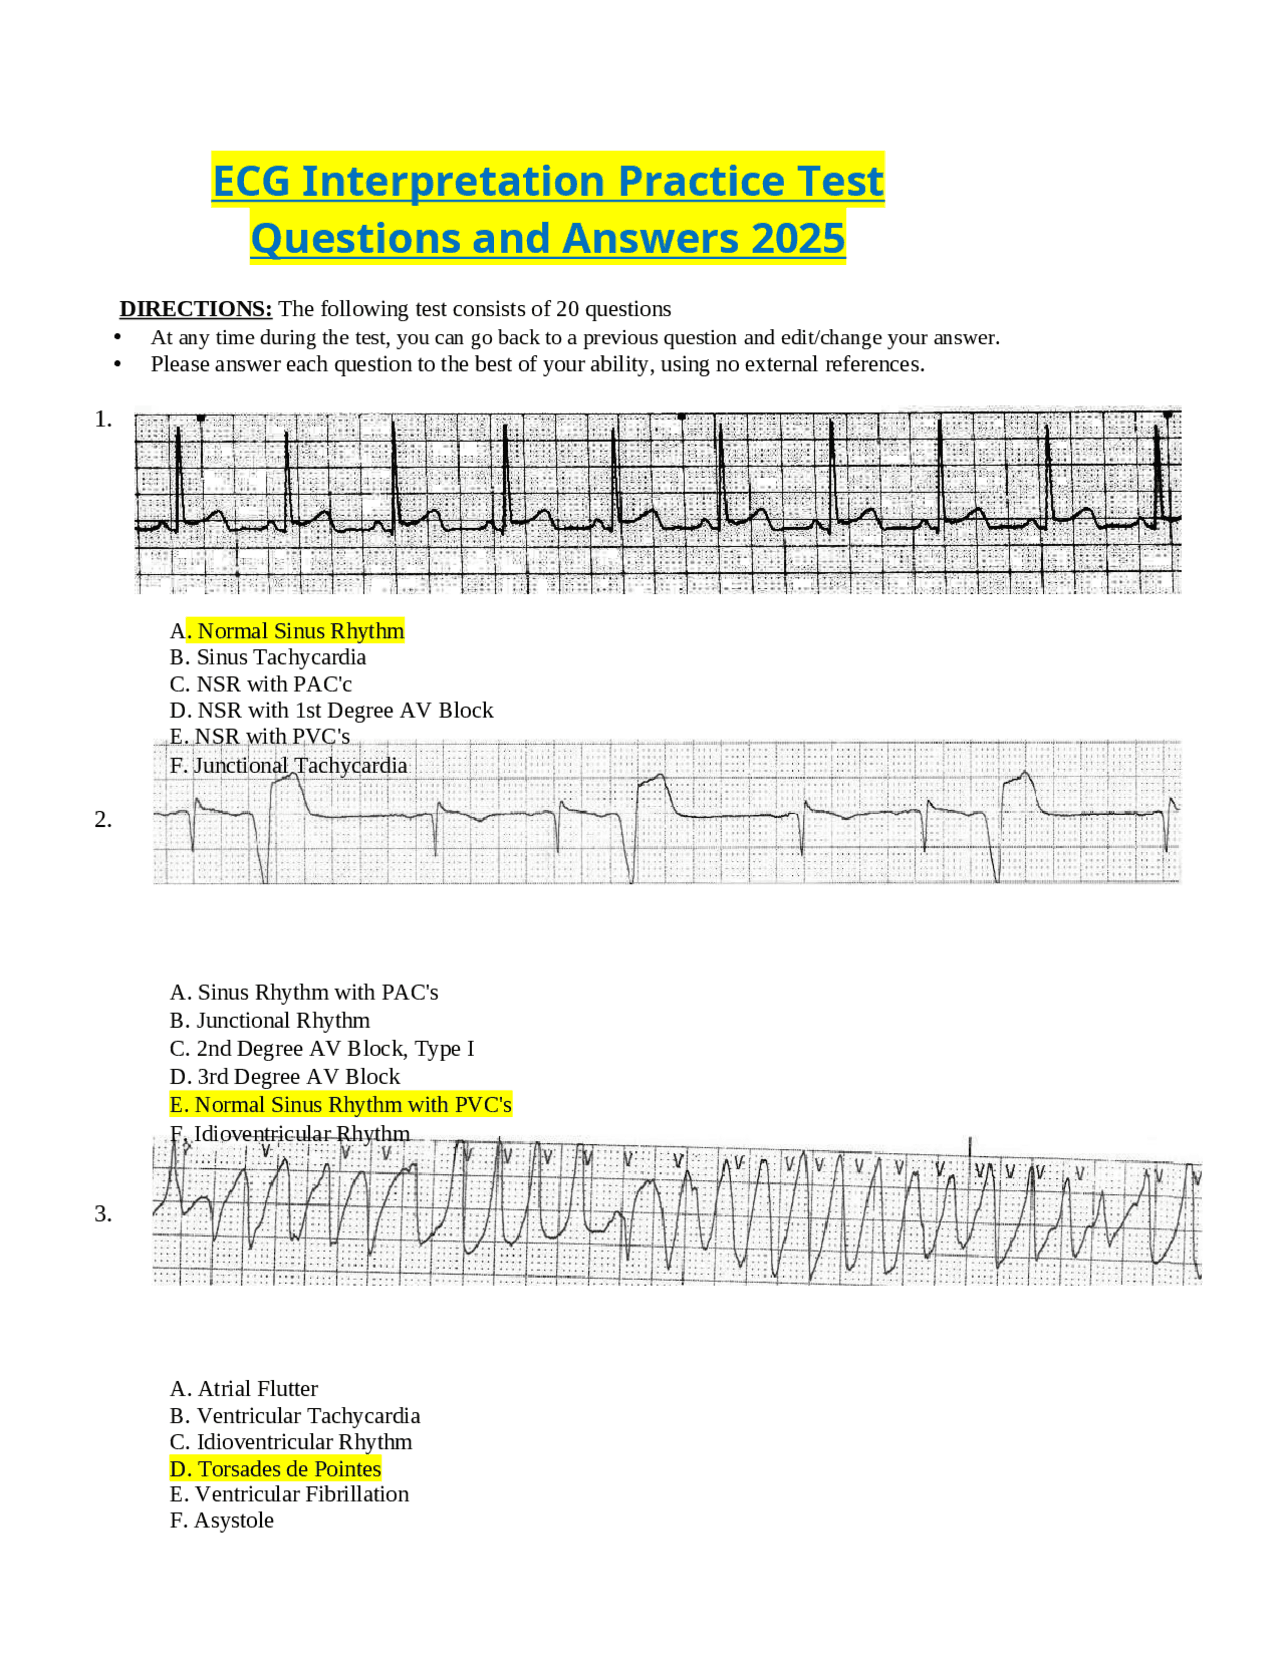
Memorization-based preparation works for basic rhythm recognition but fails when questions involve complex clinical scenarios or ambiguous findings. I watched several colleagues who aced their practice exams struggle with the actual certification because they had not developed systematic interpretation skills. They could identify sinus tachycardia and atrial fibrillation but fell apart when confronted with combined conduction defects, electrolyte disturbances, or early ischemic changes. Another limitation is that many study resources use outdated ECG criteria or simplified teaching models that do not reflect current clinical guidelines. The Minnesota Code classification system, while historically important, has been largely superseded by more nuanced approaches to ST segment analysis and T wave interpretation. Make sure your materials are aligned with contemporary standards from organizations like the American Heart Association or the European Society of Cardiology. If you find that standard question banks are not providing enough clinical context, supplement them with actual case reports and journal articles. Reading primary literature exposes you to the reasoning process behind published diagnoses and helps you develop the analytical skills that exams increasingly demand. This strategy adds time to your preparation but significantly improves long-term retention and clinical applicability.
Practical Tips for Exam Day
Bring a watch with a second hand or ensure you can access timekeeping on the exam platform. Interval measurements require precision, and losing time calculating heart rates or PR intervals eats into your ability to evaluate other aspects of the tracing. Practice this skill until it becomes automatic rather than relying on the exam interface, which may not provide the functionality you need. Read the entire question before looking at the ECG when possible. Some questions provide clinical context that should influence your interpretation, while others are purely technical assessments. Knowing what the question is asking helps you focus on relevant features rather than getting distracted by incidental findings. I used to miss questions because I interpreted the ECG completely before reading what was actually being asked. When you encounter a question you are unsure about, look for the answer that is most consistent with the available data rather than the one that sounds most dramatic. Exam writers often include plausible but incorrect options that appeal to pattern recognition without requiring deeper analysis. The correct answer usually reflects careful, systematic evaluation rather than quick diagnostic leaps.
Why Some Methods Fail Completely
There is no shortcut that replaces genuine understanding of cardiac electrophysiology. Apps claiming to teach ECG interpretation in twenty-four hours are fundamentally flawed because pattern recognition without mechanistic understanding breaks down under clinical variability. Similarly, cramming rhythm strips without studying the underlying ion channel physiology means you cannot adapt when faced with atypical presentations or combined abnormalities. I have seen candidates fail certification exams despite extensive question bank practice because they had not developed systematic interpretation habits. They could identify common rhythms but lacked the structured approach needed to evaluate less frequent but clinically significant findings. The exams increasingly test clinical reasoning rather than rote knowledge, which means preparation must evolve accordingly. For those who struggle with the spatial aspects of ECG interpretation, I recommend studying cardiac anatomy alongside electrophysiology. Understanding the three-dimensional orientation of the heart relative to lead placements makes axis determination and localization problems significantly more intuitive. This connection between anatomy and ECG theory is often overlooked in standard review courses but provides substantial diagnostic clarity.